The Other Health Care Cliff Americans Are About to Fall Off

In mid-December, members of Congress members left Capitol Hill for the final time in 2025, thus ensuring that the year would end with a failure arguably more significant than anything they accomplished during the prior 12 months: the end, despite a widespread public clamor for action, of subsidies put in place during the pandemic that made premiums of ACA marketplace plans affordable for millions of Americans.

Although important health care stories often fail to get much media attention, the failed efforts – mostly, but not exclusively, by Democrats – to save the Affordable Care Act/Obamacare subsidies were different. As patients from Maine to California opened their yearly renewal letters, many were shocked to see their monthly premiums for 2026 would be doubling or even tripling – right when the rising cost of living was already the No. 1 voter concern.

But there’s another aspect to America’s looming health care crisis that almost no one is talking about.

This is the other side of the coin – the out-of-pocket expenses that everyday consumers pay for doctor visits or prescription drugs – because of higher deductibles, or because of the growing number of patients who will risk not having any insurance at all next year because they can no longer afford it.

Even before the new year began, many Americans were dreading a double whammy of skyrocketing premiums and a sharp spike of what they expect to pay on top of that, out of their own pockets.

For example, Doug Butchart of Elgin, Ill., told ABC News that while his wife Shadene – who is living with the neurological disorder amyotrophic lateral sclerosis (ALS) – paid about $3,000 in out-of-pocket costs last year, that’s expected to rise as high as $10,000 in 2026, on top of monthly premiums that are tripling with government inaction on the ACA subsidies. It’s all more than the senior couple currently earns from Social Security.

Of course, millions of other Americans who switched to insurance plans that trade lower monthly premiums for sharply higher deductibles are taking an economic gamble that won’t play out until they see how healthy they are in 2026. In particular, those joining the surge of patients switching their ACA health coverage from the common Silver plan to the lower-premium Bronze coverage could pay thousands more as a result.

An analysis by KFF, the health care think tank, found that the average deductible in 2026 for patients who sign up for a Silver plan, assuming no reductions for cost sharing, will rise to $5,304, but for those who opt into a Bronze plan, the average deductible will spike to $7,576 – meaning a more than $2,000 higher outlay for sicker patients who max out on their covered expenses.

Katie Keith, director of Georgetown University’s Center for Health Policy and the Law and a former Biden administration aide, said the skyrocketing cost of insurance means “people are so premium sensitive that they might still go with Bronze and kind of leave money on the table – then they’re facing at least a $9,000 deductible, or whatever out-of-pocket max is, and just huge burdens.”

Keith and other health policy experts see a perfect storm of negative factors for higher out-of-pocket expenses in 2026 – from the impact of generally rising health costs to the added burden of government inaction or indifference in Washington. Among the factors behind a looming crisis:

  • Last summer, the Trump administration finalized new rules for the ACA that changed a key calculation and thus increased the maximum in out-of-pocket expenses that can be set by insurers – a ruling that also affects the millions of Americans who receive health insurance through a private employer.
  • The new math proposed by the Trump administration’s Centers for Medicare and Medicaid Services (CMS) adds yet another 4% hike on top of an already expected steep increase. The higher limit means individuals in some plans will pay $10,600 before their insurance kicks in, with a bump to $21,200 for families – an overall increase of 83% for individuals and 67% for families since the out-of-pocket maximum established by the ACA went into effect in 2014.
  • The Center on Budget and Policy Priorities reported that, because of these changes, a family of two or more people on the same plan could face an additional $900 in medical bills if a family member is seriously ill or injured in 2026.
  • Increasingly, employers are putting more of the economic burden on their workers for health care costs, especially through higher deductibles. For one thing, the KFF Employer Health Benefits Study has found that – for employees whose coverage carries a deductible, on individual plans – that average out-of-pocket cost has outpaced inflation and more than tripled in less than two decades, from $567 in 2006 to $1,887 in 2025.
  • What’s more, increasing pressure for workers to share the cost burdens of their health insurance has also caused more employer plans to offer a higher deductible option, and more people are signing up for that risk. Federal data shows that while only 38% of private-company employees had the option for a high-deductible plan in 2015, that number has now risen to more than half.
  • Perhaps the biggest factor is the end, for now, of the tax credits that had been holding down the cost of monthly premiums for ACA marketplace coverage since the COVID-19 epidemic. In states gathering data about early enrollment trends this past fall as higher premium notices went out, the shift away from traditionally popular Silver plans into Bronze coverage, with its higher out of pocket costs, has been dramatic.

For example, in California, where the Covered California program is considered a trailblazer in public health plans, officials told NBC News they’ve seen a “substantial” movement of enrollees choosing the Bronze plans with the highest out-of-pocket deductibles. Typically, officials reported, about one in five new enrollees go with the Bronze option, but for 2026 that number has soared to more than one-third. It’s a similar story in Idaho, where officials told NBC that Bronze enrollments are running 5% higher than normal, with most moving from Silver plans.

“There’s a lot yet to be seen, but there are definitely some early warning signs in terms of the decisions consumers are having to make in reaction to the changing federal policy,” Jessica Altman, executive director of Covered California, told the network.

Even more worrisome, however, is the number of Americans who are cancelling their ACA marketplace coverage altogether, because – all evidence suggests – they can no longer afford the premiums for any level of plan. In Pennsylvania, after families began receiving notices that – in many cases – their premiums had doubled, officials reported that about 40,000 people dropped their coverage, which is double the total from the 2024 enrollment period. What’s more, new enrollments in the Keystone State are also running about 20% lower than this time last year.

This is on top of a growing number of people – especially in the younger age brackets – who are switching to other low-cost alternatives that also are essentially a big gamble. These include so-called short-term plans, which are not compliant with ACA coverage requirements and that often come with annual or lifetime caps on coverage, don’t cover certain critical expenses like prescription drugs or paternity care and can penalize patients with preexisting conditions. There are also so-called catastrophic plans, which usually carry the maximum allowable deductible and which – in recognition of the worsening health insurance climate in the U.S. – have been expanded as an option to consumers over age 30. You may have even heard ads for faith-based sharing plans, whose members pool their expenses. People who sign up for those plans often find out they are not covered for a serious illness.

No wonder growing numbers of us are more anxious about the cost of health care than any time since the ACA was enacted in 2010 – perhaps ever. In November, a West Health-Gallup survey found that 47% of U.S. adults are worried they can’t afford health care next year – the highest number since the survey began in 2021. Those surveyed cited the rising cost of out-of-pocket requirements for prescription drugs in particular. And the number of Americans who say the cost of health care is causing “a lot of stress” in their daily lives has nearly doubled since the survey began, to 15%.

Georgetown’s Keith noted that – with patients and their families getting hit with higher costs on all sides – both the federal government and individual states have shown there are legislative actions that can reduce out-of-pocket costs for these anxious consumers. These include the federal No Surprises Act, which was signed into law by President Donald Trump in 2020 to address surprise medical bills, and a $2,000 annual cap on prescription drug costs for Medicare beneficiaries that went into effect in 2025 (it will rise to $2,100 this year), as well as various state efforts to curb tack-on facility fees or impose limits on insulin charges.

“There are many different flavors – ways that patients are getting charged,” Keith said. Indeed, that’s the bad news, since many of the fixes that lawmakers have been working on feel like bail-out buckets of water against a tsunami of rising medical expenses that in 2026 threaten the broader American economy, not to mention the national psyche.

Rising out-of-pocket expenses might be the looming health crisis that no one is talking about, but the lack of media coverage is likely to change over the course of 2026 as horror stories trickle in from those who gambled on not getting sick over the next 12 months – and lost that wager.


Why health insurance is getting more expensive

There’s a good chance your health insurance premiums are going up next year, regardless of where you get coverage.

Why it matters: 

The spike in what millions of Affordable Care Act plan enrollees pay will be acute, but workplace insurance is getting more expensive, too — and all at a time when affordability is prominently on Americans’ minds.

ACA premiums have dominated the political discourse in Congress for weeks, but there’s no real sign that any relief is coming from Washington.

  • Even extending the Biden-era enhanced ACA subsidies — which most Republicans don’t want to do — would do nothing to address what’s driving the surging cost of care or employer insurance affordability issues.
  • And all signs point to Democrats hammering Republicans for high costs in all forms of health insurance leading up to next year’s midterm elections.

The big picture: 

Health insurance gets more expensive almost every year, keeping up with increases in the costs of procedures, tests, drugs and more. But some years see bigger jumps than others, and 2026 is looking like one of those years.

  • That means tough choices for families, employers and workers all faced with shouldering higher premiums or out-of-pocket spending. Some will conclude it’s prohibitively expensive and go uninsured.
  • Another thing that’s different about this year is that the white-hot political rancor around ACA premiums is putting health insurance back centerstage politically.

By the numbers: 

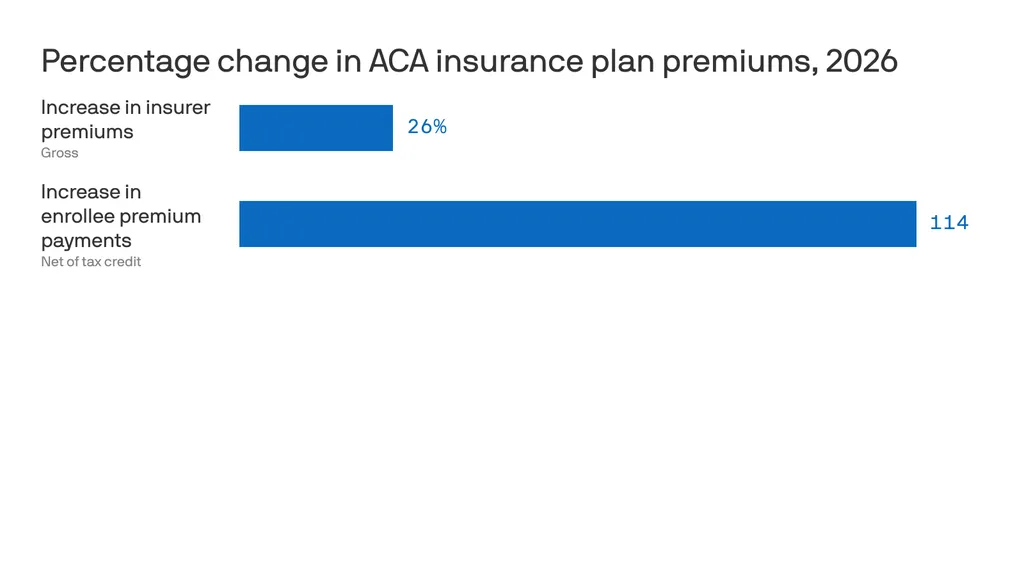
ACA insurers themselves are raising premiums by an estimated 26%, in part due to rising hospital costs, higher demand for pricey GLP-1 drugs like Ozempic, and the threat of tariffs.

  • But add in the loss of federal subsidies, and the increase is 114% — or more than double what they currently pay, according to KFF. 22 million out of 24 million marketplace enrollees now receive subsidies.
  • Premiums in the small group employer market will go up by a median of 11%, also per KFF, due to some of the same reasons insurers cite in ACA markets.

For employer health insurance, there’s no comprehensive data yet for 2026, but estimates from earlier this year put the increases in the high single digits.

When Drug Price Transparency Isn’t Enough

Policymakers and advocates often promote drug price transparency to lower costs and improve equity. While transparency is an important first step toward accountability and informed public budgeting, it does not guarantee affordable prices or fair access to medicines.

Transparency Has Some Benefits

Drug price transparency helps show how and why medicines cost what they do along the supply chain (i.e., from the manufacturer to the pharmacy), which makes it easier to identify where costs can be reduced or better regulated. By making this information public, transparency allows patients, payers, and policymakers to make more informed decisions and encourage manufacturers to prices drugs more fairly. Ultimately, it supports a fairer system where patients can better afford and obtain the treatments they need, improving access to care.

States with Drug Transparency Laws

While federal policy to improve price transparency is lacking, the states have moved to make things clearer for patients and payers. Vermont was the first U.S. state to enact a drug price transparency law in 2016. Since then, many others have followed suit. At least 14 states have passed some version of transparency legislation, though the details and their enforcement of these laws differ widely.

For example, only Vermont and Maine require drug companies or insurers to disclose the actual prices paid after discounts (called the “net price”). Alternately, Oregon and Nevada require drug manufacturers to publicly report their profit to state government agencies. And Connecticut, Louisiana, and Nevada mandate pharmacy benefit managers (PBMs) to report the total rebates they receive, but not the amounts for each specific drug. Despite these efforts, no state has yet achieved full transparency across the entire drug supply chain.

Transparency is Not Enough

Even with clear pricing, Americans still pay about 2.6 times more for prescription drugs than people in other wealthy countries. Early evidence suggests that these laws have done little to curb drug prices. To date, only four states – California, Maine, Minnesota, and Oregon – have published analyses of their own laws. These reports share common concerns: difficulty tracking pricing across the supply chain and uncertainty about whether state agencies have the authority (or the will) to act when data is incomplete or unreliable. 

Most transparency laws fall short on requiring detailed cost or profit data, focusing instead on broad price trends. As a result, this narrow scope makes it difficult to identify the exact drivers of high drug prices. Even when transparency discourages manufacturers from raising prices, these policies do not directly control pricing or define what constitutes an ‘unjustified’ price increase. Manufacturers can simply adjust by setting higher launch prices or implementing smaller, more frequent increases to stay below reporting thresholds. Still, the result is a system where drug costs can vary by as much as $719 for the same 30-day prescription even when prices are publicly listed.

What can also be done?

Creating a consistent national framework could replace the current patchwork of state laws and improve oversight of how drugs are priced. For example, the Drug Price Transparency in Medicaid Act (H.R. 2450) could do just that: it would standardize reporting requirements and reveal how drug prices are set, rebated, and reimbursed. But transparency alone can’t lower costs—it only shows the problem.

To make transparency meaningful, policymakers must address the underlying contracts and incentives that drive high prices.

Hidden rebate deals and opaque pricing structures between PBMs and drugmakers often inflate costs and limit patients from seeing savings. Transparency legislation should also be paired with value-based pricing that links payments to clinical benefits. Federal programs like the Medicare Drug Negotiation Program provide additional leverage, but broader reforms are needed to reach the commercial market (i.e., where most Americans get their prescription drugs and still face high prices).

Still, transparency can have downsides, especially globally. Fully public drug prices could push companies to stop offering lower prices in low- and middle-income countries. To avoid cross-country comparisons, they could raise prices across the board, making medicines less affordable where they’re needed most. To make transparency more equitable, policymakers should combine disclosure with protections that preserve affordability worldwide.

Conclusion

In short, transparency is necessary but an incomplete fix for America’s drug pricing system. Simply shining a light on how prices are set isn’t enough. Policymakers need to be paired with other reforms, such as removing the incentives that encourage high prices, holding PBMs and manufacturers accountable, extending the negotiating power beyond Medicare, and protecting prescription drug access both at home and abroad. Without these other steps, transparency laws risk highlighting unfairness without actually improving it.

The Double Whammy Behind the 2026 ACA Premium Shock

Millions of ACA enrollees will face steep premium hikes in 2026 as insurer rate increases collide with the expiration of enhanced federal subsidies.

As health insurance premium costs have taken center stage this fall, you may have seen seemingly conflicting reports about how much premiums are increasing, especially for ACA marketplace plans. This isn’t a reporting error. Instead, it reflects a double whammy of increases that more than 20 million ACA enrollees are poised to face in 2026.

To understand what’s happening, it helps to think of ACA premium increases as a one-two punch.

The first hit comes from the overall increase in health insurance premiums for 2026. On average, insurers raised premiums for ACA marketplace plans by roughly 26 percent from 2025 to 2026. This increase reflects a rise in the total cost of coverage, the full premium paid jointly by enrollees and the federal government through subsidies, not just what individuals pay out of pocket.

Premium increases are not new. Insurers raise rates every year. But the 2026 hike is striking: more than three times the 7 percent increase in 2025 and the 6 percent increase in 2024. Insurers have attributed roughly four percentage points of this increase to the anticipated expiration of the enhanced premium tax credits, arguing that enrollment will decline and that sicker, higher-cost enrollees will make up a larger share of the risk pool. Insurers also cite provider consolidation and high pharmaceutical prices as drivers of higher premiums.

These explanations deserve scrutiny. As Wendell Potter recently documented, the seven largest private insurance corporations have collectively taken in more than $10 trillion in revenue since 2014 with revenues steadily increasing each year. Against that backdrop, claims that today’s premium spikes are unavoidable or purely defensive ring hollow.

The second hit falls directly on consumers who currently rely on enhanced premium subsidies (in the form of tax credits) to make coverage affordable. Those enhanced subsidies, first made available during the pandemic, are set to expire at the end of 2025, and Congress appears poised to let them lapse without an extension. If that happens, many enrollees will see the tax credits that lower their monthly premiums shrink dramatically or disappear altogether. Taking this into account, the amount people pay out of pocket for ACA premiums is expected to increase by an estimated 114 percent in 2026. And that is just for the premiums. People enrolled in ACA plans will also have to spend hundreds if not thousands of dollars out of their own pockets in deductibles and copays before their coverage kicks in.

This double whammy will have drastic, and potentially deadly, consequences for millions of Americans. I am already seeing panic from people in my own community and across the country, echoed daily on social media. Yet Congress has taken no action to cushion the blow. The Republicans leading both the House and the Senate are leaving Washington without extending the enhanced tax credits, even as the clock runs out.

This is an abdication of Congress’s responsibility to represent the people it serves, people who have been clear about what they want and need: health insurance they can actually afford. Rather than getting bogged down in partisan gridlock or abstract market ideology, Congress must act now to extend the enhanced premium tax credits. That extension should be treated as an urgent bridge to a real fix to our health care system; one that reduces dependence on Big Insurance, lowers costs for patients, and ensures that no one is forced to go without care.