Is AHA Right to be Concerned?

Last week, the American Hospital Association released a study by Kaufman Hall, its preferred data vendor, that took issue with methodologies used by critics of hospital consolidation:

“These findings suggest that a more comprehensive analysis of hospital M&A transactions, one that considers impacts on all patients served, broadens the focus to impacts beyond pricing, and considers the consequences if an M&A transaction is not permitted to proceed, would ensure not only competitive but also healthy hospital markets that can continue to provide the fullest possible range of services.”

The report discusses how hospital merger reviews should look beyond the potential impact on commercial insurance prices and consider what proposed transactions mean for all patients, particularly the nearly 60% of hospital patient days attributable to Medicare, Medicaid and Medicare Advantage beneficiaries whose payment rates are largely set by government programs.” Drawing on analyses of challenged and canceled transactions, the report also finds that hospitals seeking partners often serve more vulnerable communities and face greater financial pressures, and that when proposed deals do not move forward, struggling hospitals can experience significant financial deterioration that threatens services, workforce stability and access to care.”

Kaufman Hall added this disclaimer: “The findings contained in this document may contain predictions based on current data and historical trends. Any such predictions are subject to inherent risks and uncertainties. Past performance is not necessarily indicative of future results. Kaufman Hall accepts no responsibility for actual results or future events.

Also last week, a Health Affairs commentary “In 2026, States Are Leading On Health Care Affordability” noted that “Research has consistently shown that hospital prices are the largest driver of commercial health care spending growth. Hospital markets are dominated by monopolies, which enable hospitals to charge higher prices without improving quality or outcomes. State policymakers are increasingly looking for options to limit excessive hospital prices. Our research shows that capping the highest, most egregious prices charged by hospitals can meaningfully improve health care affordability while still allowing hospitals to generate a healthy margin…

A key driver of rising health care prices is consolidation in health care systems, including through hospital acquisitions of physician practices. These acquisitions, which are a form of vertical integration, increase hospital prices by 3 to 5%. This can be attributed to greater bargaining power, more intensive coding practices, and hospitals charging facility fees at what were previously independent physician practices but are now treated as “hospital outpatient departments.” To address these issues, states are increasingly considering facility fee bans or “site-neutral” policies that would cap prices for certain routine hospital outpatient services that could be provided safely in an office setting.”

Both positions are defensible.

Not for profit and public hospitals are at a disadvantage in managing their finances because they’re obligated to serve entire communities without regard to local economies or population health. Investor-owned hospitals and insurance companies have fewer restrictions and can exit markets at will.

And almost every hospital is dependent on reimbursement from commercially insured patients to offset what is the widely-accepted calculus that Medicare and Medicaid reimbursement doesn’t cover the total cost of care provided enrollees. Thus, across the hospital industry, the playbook has been straightforward: to optimize hospital finances….

  • Maximize the attractiveness of hospital services that attract privately insured patients via contracting with private insurers.
  • Negotiate favorable rates with private insurers to enhance cost-shifting to Medicare and Medicaid by private plans.
  • Optimize leverage (scale) over insurers by consolidating hospitals, acquiring physician practices, expanding ancillary activities and deploying capital to potentially profitable ventures.
  • Advocate for state and federal laws that dissuade hospital price caps, 340B cuts, site-neutral payments, unreasonable price transparency requirements and limits on private-equity partnerships.
  • Assert that hospitals are efficient stewards of the public’s trust but disadvantaged by corporate insurers and drug companies that are allowed to enter and exit markets at will, price at “what the market will bear” and put shareholder profit above all else.

This scheme has worked for 40 years to enable hospitals to control at least 50% of total health spending: 31% for traditional hospital services, 12% of total physician services, and ventures, partnerships, ancillary services and post-acute services in addition. In the aggregate, hospitals are the most important cog in the healthcare wheel. They’re labor intense, capital intense, complicated businesses that enjoy public trust that’s slipping away, especially among the 25 million who work in the industry.  Complicating matters, distinctions between rural and government safety net hospitals and highly profitable investor-owned and not-for-profit systems are attracting unwanted scrutiny from regulators and in media coverage.

While Kaufman Hall raises legitimate questions about current methodologies used by state and federal regulators to assess consolidation, it does not answer the bigger question: what role should hospitals play in the U.S. system as AI-derived clinical innovation proliferates, labor and supply costs accelerate and fewer people can afford services?

It’s not clear.

  • Should “hospital services” be redefined bifurcating facility-dependent inpatient services (Part A) and an expanded set of services inclusive of self-care provided in homes, schools, workplaces and virtually?
  • Should “community-benefits” and “charity care” be redefined so that methodologies are consistent and gaming to receive tax benefits eliminated?
  • Should hospital clinical performance be linked to improved outcomes and lower costs (affordability)?
  • Should local primary care and preventive health services (inclusive of nutrition, physical and mental health, prophylactic dentistry) be integrated with hospital services to improve population health and control demand for hospital services?
  • Should specialized tertiary and quaternary hospital programs be rationalized to optimize outcomes and improve efficiency?
  • Should consolidated hospital systems disclose administrative costs, functions and allocation methodologies publicly?
  • Should hospital boards be required to conduct scenario planning that’s comprehensive?
  • Should hospital administrative services and costs be standardized to facilitate caps on spending and management performance comparisons?
  • Should physician ownership of hospitals be enabled to increase competition?

And many others.

The American Hospital Association is right to be concerned about how regulators are addressing hospital consolidation and its impact on prices. And they’re right to challenge methodologies applied to questions about hospital prices and competition. But they fall short in offering a vision for the future of the health system that’s plausible, affordable and compelling. Rather, they offer a hospital-centric vision based on suspect assumptions and inadequate sensitivity to market trends not directly associated with traditional health services.

Every stakeholder in the health system—including hospitals and physicians—face heightened pressure to eliminate unnecessary utilization and costs due to willful or unknowing fraud. Just as insurer prior authorization practices have been frustrating to providers, unnecessary care is confounding to regulators and employers. The use of agentic AI tools to examine appropriateness of tests, procedures, medications and visits will exponentially change how “quality of care” is defined and regulated, and how its delivered. It’s a big deal everywhere, especially in Medicaid programs.


The Biggest Health Care Companies in America Don’t Treat Anyone

It started as a simple question. Who are the biggest health care companies in the United States?

If you rank the ten largest health care companies in America by revenue, you will not find a single hospital system or drugmaker. Not Pfizer, not Eli Lilly, not the Mayo Clinic or HCA. Every company in the top ten is a middleman, and together they take in about $2.6 trillion a year.

Above is a list showing how much of every dollar of revenue each company keeps as net income. Then read about what these companies actually do.

Three of these companies are insurers that swallowed pharmacy benefit managers: UnitedHealth owns Optum Rx; CVS owns Caremark and Aetna; and Cigna owns Express Scripts. Three are drug distributors that move pills from the factory to the pharmacy and touch almost none of them. Three more are built on Medicare and Medicaid managed care. Every one of them sits between the people who deliver care and the money that pays for it.

McKesson, Cencora and Cardinal Health each keep somewhere between half a cent and a penny of profit on every dollar of revenue. Cencora reported $294 billion in sales in fiscal 2024 and $1.5 billion in profit. That is a rounding error as a margin. And yet all three rank among the thirty largest companies in the world.

No other rich country works this way

The sheer size of these companies is another distinctly American feature of the system. On the 2026 Fortune Global 500, UnitedHealth ranks fourth in the world, ahead of Apple; McKesson is seventh; CVS is ninth; and Cigna, where I worked for 15 years, ranks 14th in the U.S. and 21st in the world. Every health care company near the top of the global list is an American intermediary in one way or another. There is no foreign health care business of any nature that comes close.

The closest thing another country has to one of our giants is Allianz, in Germany. Allianz is the largest insurance company in Europe. But it is a general insurer built on property, life and asset management, and health is a minor line. Even at home, Allianz is only the third largest health insurer in Germany. There, roughly nine in ten people are covered by nonprofit sickness funds, which are barred by law from operating as for profit and must send any surplus in funds back into the system.

And then there are Britain’s National Health Service (NHS), which is funded by taxes; Canada’s single-payer system financed through the provinces; and Japan’s nonprofit insurance system based on a standardized national fee schedule.

None of these countries built the kind of for-profit middleman layer that exists in the U.S., where some of those companies have grown into the largest corporations in the world. Pharmacy benefit managers are also a uniquely American creation, which helps explain why that entire category of health care giant does not exist elsewhere.

What the middleman layer costs

The United States spent $5.3 trillion on health care in 2024. That was the first year the country ever crossed $5 trillion, and it is the most recent year with actual figures rather than projections. (The Centers for Medicare and Medicaid Services estimates total U.S. health spending will reach $6 trillion this year.)

A large share of that money never reaches care and instead is consumed by the U.S. health care system’s complicated administration and payment systems.

In 2021, the United States spent $925 per person on health administration, meaning the overhead of insurers and government programs. The average wealthy country spent $245. That gap of $680 a person accounts for about 12% of the entire difference between what America spends on health and what its peers spend. As a share of the total, administration eats about 7.6% of U.S. health spending against 3.8% across comparable nations. We devote twice the share of every health dollar to running our absurd machinery.

The $925 figure counts insurer and government overhead and does not include what hospitals and doctors spend on billing, coding and prior authorization just to get paid. When those costs are included, estimates put total administrative spending between 15% and 25% of all U.S. health care spending — or, based on 2024 spending, roughly $800 billion to $1.3 trillion a year.

The countries with the leanest administrative spending tend to be those (you guessed it!) with the fewest middlemen.

Middlemen spend to keep the status quo

I know how a system this profitable defends itself because I used to help do it. Back at my old gig at Cigna, my team and I wrote talking points for lobbyists to use with lawmakers, and we doled out campaign cash to candidates we liked.

The health sector spent $743.9 million lobbying the federal government in 2024, more than any other sector of the economy and the only one to clear $700 million. UnitedHealth alone spent $16.6 million in the 2024 election cycle. The insurance industry’s trade group, AHIP, and the biggest insurance conglomerates pour tens of millions more into the same effort year after year, and the pharmacy benefit managers keep their own operation running through another insurance industry funded trade group called the Pharmaceutical Care Management Association (PCMA), whose spending has roughly doubled since 2022.

That spending helps protect Medicare Advantage payments, fight efforts to rein in pharmacy benefit managers and oppose proposals that would move the country toward universal coverage. Compared with the $70 billion in combined profit of the seven biggest for-profit insurers last year, the lobbying bill is relatively small.

The price of “choice”

The industry says all of this is the price of “choice,” which they want folks to believe is sacred. It is the argument insurers and their allies reach for every time Congress looks at a single-payer bill or public option or any other approach, for that matter, that could move us closer to reining in the worst abuses of the industry.

Americans say they want to choose their own doctor and their own hospital, but that is exactly the kind of choice the middleman system can take away through narrow networks and prior authorization. What the industry defends instead is the choice among insurers. And for most working people, even that choice is made by an employer. We pay hundreds of billions of dollars a year to run a marketplace of middlemen, and in return we get narrower networks and more denials than patients face in the countries that never built the marketplace at all.

Depending on the results of the next two election cycles, Congress will almost certainly debate how to restructure health care again, with the familiar goals of lowering costs, expanding coverage and improving care. But any serious attempt to do that will have to confront the enormous middleman industry the current system has created and allowed to flourish.

The Health Care Scare Is Back

As voters sour on private insurers and health care reform gains political momentum, decades-old warnings about “choice,” “wait times” and “slippery slopes” are resurfacing.

If you want a sense of where the health care debate is headed as we enter the final stretch before the midterm elections, take a look at what has been published over just the past week.

Last Wednesday, the New York Post published an op-ed by Pacific Research Institute President Sally Pipes warning that Medicare for All would be a “real-life nightmare.” That same day, another Pipes column, this one in Newsmax, warned that a public option would be the first step toward a “complete government takeover of health insurance.” And also last Wednesday, Reason published a piece warning that universal health care means “long waits, rationed care, and unmet medical needs.”

These old tropes are familiar to me, as I am sure they are to many readers. And there is a reason they are back getting airtime.

Health care costs have become a major vulnerability for politicians heading into November. A KFF poll this summer found that 51% of voters considered health care costs an “extremely important” issue for candidates to address. Earlier KFF polling found that 61% said health care costs would have a major impact on which party’s candidates they support. And it is Americans’ sentiments about health care costs that have pushed many Medicare for All candidates over the finish line and lit a fire under current members of Congress who are now seeking a way to increase competition in the health insurance space by creating a nonprofit health plan that would be operated by the federal government.

Americans are increasingly fed up with private health insurers. Complaints about denied care, prior authorization, rising premiums and exorbitant out-of-pocket requirements have put insurers under a level of scrutiny I haven’t seen in years. It’s not just Abdul El Sayed. It’s Marjorie Taylor Green, too.

And it’s because of this political storm brewing that the health insurance industry’s longtime defenders are coming out swinging.

I know Sally Pipes’ work especially well. Pipes, who grew up in Canada but has lived in the U.S. for years, has spent decades warning Americans about reforms that might move the United States closer to a system like our neighbors to the north have. When I was an insurance executive, she was always useful to us.

During the industry’s campaign against Michael Moore’s Sicko, for example, we drew on Pipes’ work to portray Canada’s health care system as a cautionary tale. I wrote about that in the Washington Post. And during the debate over what became the Affordable Care Act, she was a forceful critic of the public insurance option insurers desperately wanted to keep out of the final bill.

She was a reliable ally of the health insurance industry then, and she clearly is returning to that role once again.

In her New York Post column last week, Pipes reaches for one of the oldest and most effective arguments against health care reform: “choice.” Pipes says that (currently) employers can switch insurance companies, people buying their own coverage can shop among plans and Medicare beneficiaries can choose between traditional Medicare and privately run Medicare Advantage plans. Medicare for All, she warns, would take that “choice” away.

It’s an argument that has worked before because “choice” sounds pretty good. Who wants fewer “choices” when it comes to their health care? (That’s a rhetorical question. But one answer is the insurance industry, which has been eliminating “choice” and competition for decades now.)

The trick is that much of the “choice” Pipes is talking about is an illusion. Americans with employer-sponsored coverage most certainly do not get to choose their insurance company. Their employer does. And even if you can choose among a handful of health plans at work, all of them at most U.S. businesses that can still afford to offer coverage are operated by the insurance company your employer chose. That’s not the same as being able to choose your doctors or hospitals, which is the “choice” Americans really want. Your health insurer decides which doctors and hospitals are in your network and can require prior authorization before it will pay for care your doctor recommends.

In other words, Americans may have (some) “choice” of plans – with varying levels of deductibles and copayments – but that doesn’t necessarily mean they have a meaningful “choice” when it comes to their health care.

Pipes’ second column last week reveals something else about the “choice” argument. She warns in Newsmax that a public option would have advantages private insurers couldn’t match, eventually drive them from the market and put the country on a “slippery slope” toward single-payer health care. (I can’t tell you how many times I warned about that so-called “slippery slope” when I ran communications at Cigna.) So Pipes essentially is arguing that private insurers must continue to be protected from additional competition in the name of giving Americans “choices.” But give Americans the “choice” of a public plan—and the possibility that millions might prefer it to what private insurers are selling—and suddenly “choice” itself becomes the problem. She ignores the fact that seniors have long been able to choose a public option – traditional Medicare – or one operated by a private insurer – Medicare Advantage. I can assure you that Medicare Advantage is extraordinarily profitable for private insurers. No one should worry that insurance companies won’t continue to make money if people younger than 65 can also at long last be able to choose a public option.

Reason, the libertarian magazine that has been a persistent critic of the Affordable Care Act, Medicare for All and any concept that would allow the government to pass legislation that would interfere with insurance companies’ business practices, published its own warning last week under the headline: “Universal Healthcare Sounds Great. Here’s What’s Happening in Countries That Have It.”

The piece focuses heavily on Canada and Britain, arguing that people in those countries face long waits for care in overcrowded hospitals, and it cites examples of patients who received inadequate care. Those problems are real and shouldn’t be dismissed. Neither Canada nor Britain has a perfect health care system. But the United States sure as hell doesn’t either. Millions of Americans never get the care they need because they can’t afford to buy health insurance. Millions more with insurance can’t use it because of unaffordable out-of-pockets costs and have no “choice” but to go without the care they need.

Reason leans heavily on one of the most familiar scare tactics used against universal health care: the wait times. In Canada, you might wait a few months for an elective procedure like a knee replacement, and in the U.K. see a specialist or get a procedure. In Britain, you might find yourself in an NHS queue. But in either country, unlike in the U.S., you will not have to wait long at all to see your primary care doctor or be admitted to a hospital for medically urgent care.

To be sure, waiting for an elective procedure or imaging annoys many Canadians and Brits. They are real problems. But in this country, we ration care in a way that creates far more harm than waiting in a queue for a few weeks or months for non-urgent care. In the United States, if you can’t afford care, you don’t wait a few months or get thrown on a waiting list – you all too often never get the care. Because in the U.S. of A, if you’re one of the nearly 30 million Americans who are uninsured, or who can’t cover their deductibles, you don’t get it until you get so sick you have to go to the ER. And then you get saddled with hundreds or thousands of dollars in medical debt.

So comparatively, Americans put off the procedures, scans and medications they need. Americans live with pain and hope whatever is wrong doesn’t get worse. In the worst cases, folks in this country die prematurely with conditions that could have been treated because they couldn’t afford to get the care that could have saved their lives.

Reason has been making versions of this argument for years. The magazine has previously published pieces with headlines including “Medicare for All Is Bad Medicine,” “Why Bernie Sanders’ Medicare for All Is a Bad Idea,” and “Medicare for All Would Actually Be a Government Takeover of Health Care.” (“Government takeover” ranked right up there with “slippery slope” when I was an insurance industry propagandist. Get ready to hear both lies again and again and again between now and November.)

Not only did I find propaganda like this effective in my old job, I’ve also seen it effective in real life.

Obviously, the only way we are going to fix our health care system is by debating the difficult things. We can debate Medicare for All. We can debate a public option. Both proposals deserve serious scrutiny if we want to get the next version of our health care system right.

But the attacks against these reforms deserve scrutiny, too — especially when they come from the same people and organizations that have been making them for decades, and when those arguments have historically served the interests of a health insurance system with an enormous financial stake in preventing reform.

Medicare Advantage enrollees more likely to leave after new complex diagnosis

Medicare Advantage enrollees who developed a new complex condition, such as congestive heart failure or Alzheimer’s disease, were more likely to leave their plan for traditional Medicare the next year, according to a study published Aug. 21 in JAMA Health Forum.

Medicare Advantage (MA), the private alternative to traditional Medicare, covered 54% of Medicare beneficiaries in 2025, the study noted. MA plans offer perks traditional Medicare doesn’t guarantee, such as spending caps and built-in drug coverage, but they also use prior authorization and limited networks that can slow down care. Folks with bigger health needs have left MA at higher rates than healthier enrollees.

However, leaving isn’t simple. In most states, insurers don’t have to sell Medigap, the supplemental coverage that fills traditional Medicare’s gaps, to someone who skipped it when they first signed up. That can leave beneficiaries who get sick later stuck without that backup option.

The study was led by Mark K. Meiselbach, Ph.D., of the Department of Health Policy and Management at Johns Hopkins Bloomberg School of Public Health, and his team, who said past studies treated a new diagnosis as simply yes-or-no and mostly tracked switches to traditional Medicare. The researchers wanted to see whether leaving MA increases with the number of new conditions a person develops and to separate switches to traditional Medicare from switches to a different MA plan, something earlier research hadn’t done.

JAMA Health Forum finds Medicare Advantage members with new complex diagnoses increasingly switch to traditional Medicare, highlighting MediGap barriers, state protections, and plan limits.

The retrospective cohort study used Medicare enrollment and claims data from 2016 through 2021, analyzed in late 2025 and early 2026. Researchers tracked beneficiaries who stayed in an MA plan all of 2016 and had no complex condition through 2018. Using a standard federal algorithm, they flagged eight conditions: heart attack, Alzheimer disease, atrial fibrillation, chronic kidney disease, chronic obstructive pulmonary disease (COPD), depression, congestive heart failure and stroke.

A treatment group of 219,942 beneficiaries developed one of those conditions in 2019; a comparison group of 834,984 did not develop one through 2021. Using a difference-in-differences design, researchers compared how disenrollment changed for each group before and after 2019, then checked whether that change depended on how many new conditions someone developed, their state’s Medigap rules, and whether their MA plan was a health maintenance organization (HMO).

Developing any new complex condition raised MA disenrollment by 3.3 percentage points. Almost all of that increase came from people leaving for traditional Medicare rather than switching to a different MA plan. The more conditions someone developed, the more likely they were to leave: 1.4 percentage points with one new condition, up to 12.8 points among the 1,010 people with four or more. A new Alzheimer’s disease diagnosis had the single biggest effect, an 8.6 percentage point increase, while the rest ranged from 2.9 to 5.0 points.

Beneficiaries in the four states with Medigap guaranteed-issue and community-rating rules, Connecticut, Maine, Massachusetts and New York, were 1.5 percentage points more likely to leave for traditional Medicare than beneficiaries elsewhere. Those enrolled in HMO plans were less likely to leave for traditional Medicare but more likely to switch to a different MA plan.

Dual-eligible beneficiaries, who qualify for both Medicare and Medicaid, left for traditional Medicare at higher rates and switched MA plans less often, which the authors said tracks with Medicaid reducing their need for Medigap. Plan star ratings didn’t matter much: those in 4- or 5-star plans left at about the same rate as those in 3-star plans after a new diagnosis, suggesting star ratings don’t capture how well a plan serves sicker members.

“These findings underscore the difficulty of making an initial enrollment decision in Medicare,” the study’s authors wrote in the discussion. “Beneficiaries cannot foresee all of their future health needs when they first enroll in MA, but the consequences of that decision may depend on health events that occur years later.”

Strengths in this study include the tracked disenrollment trends before 2019, not just a single before-and-after comparison, and the study found no sign the groups were already diverging. The results also held up after adjusting for other chronic conditions people developed.

However, there are limits. Since new conditions were identified from claims, which usually show up after a diagnosis, the authors said their numbers likely undercount the true effect rather than overstate it. Counting conditions is also an imperfect stand-in for true complexity, and the group with four or more new conditions was small, just 1,010 people, so those figures carry more uncertainty. The data ends in 2021 and doesn’t reflect newer MA plan designs.

The authors confirmed that state Medigap protections make it easier for more ill beneficiaries to switch to traditional Medicare, but expanding those protections more broadly could push Medigap premiums up for everyone. And MA star ratings, as they currently work, may not reflect how well a plan actually serves members whose health needs have grown more complex.

Where Do Our Health Insurance Premiums Go?

Big Insurance has hauled in $500B in profits since 2014— enough to cover extending the enhanced ACA subsidies and leave $150B — yet it’s gone to shareholders and executive bonuses instead of patients.

As open enrollment begins and Congress remains deadlocked on whether to extend the ACA’s enhanced premium subsidies, one question looms large: Where does all the money we pay for health coverage actually go?

It’s a fair question. Premiums and out-of-pocket costs have risen relentlessly over the past decade. Since the Affordable Care Act was fully implemented, the average premium for an ACA marketplace plan has doubled, and the average deductible for a Silver plan has increased by 92%. Every year, families pay more, yet the coverage often feels thinner.

What the Insurers Say

Health insurance companies routinely claim these increases simply reflect rising medical costs and higher utilization. For example, when justifying rate hikes in 2024, Cigna of Texas wrote:

“The increasing cost of medical and pharmacy services and supplies accounts for a sizable portion of the premium rate increases.”

But the financial filings of these same companies tell a different story.

What the Numbers Show

As Wendell Potter recently wrote, from 2014 to 2024 the seven largest publicly traded health insurance companies, UnitedHealth Group, CVS/Aetna, Cigna, Elevance (formerly Anthem), Humana, Centene, and Molina, reported that they collectively made more than half a trillion dollars in profits.

That’s money collected from individuals, employers and taxpayers for health coverage — dollars that didn’t go to medical care but instead flowed to corporate shareholders and executive bonuses. To put this in perspective, those profits alone could fund the enhanced ACA premium subsidies for another ten years, at an estimated cost of $350 billion.

Stock Buybacks: Enrollees’ Money, Executives’ Reward

Over the same period, these seven companies spent $146 billion buying back their own stock or, in other words, using premium dollars from patients and employers to boost share prices and executive compensation (the CEOs and many other top executives of big insurers are compensated primarily through stock grants and options).

Stock buybacks don’t lower premiums, expand networks, or improve care. They simply make investors and executives richer. If that same money had been reinvested in enrollees, it could have provided premium-free health coverage to more than 5 million families for an entire year, based on the average employer-sponsored plan cost of $27,000 in 2026.

Lobbying With Our Premium Dollars

Insurers aren’t just rewarding shareholders, they’re also shaping the political system that protects their profits. Since 2014, the seven largest insurers and their trade association, AHIP, have spent $618 million on lobbying.

That’s money that could have been used to lower out-of-pocket costs or improve patient care, but instead it’s spent to influence Congress and federal agencies to maintain the status quo.

The Real Problem — and the Real Solution

As the cost of health insurance continues to climb, politicians debate how to control those costs and expand coverage. But the truth is, there’s already enough money in the system to cover everyone. It’s just being siphoned off by insurance corporations for profits, lobbying, and stock buybacks.

Though some have been calling for less regulation of Big Insurance, that is not the answer and is partly how we ended up in this situation. Right now, Big Insurance is allowed to use premium dollars and tax dollars on things that do nothing to improve anyone’s health – such as stock buybacks and lobbying – instead of on medical care.

Rather than asking families and taxpayers to pay more, it’s time to demand accountability from insurers. At a minimum, they should not be allowed to use premium dollars, or taxpayer dollars, to enrich shareholders through stock buybacks (which wasn’t even legal until the 1980s) or lobby for policies that drive up costs.

If we want to contain health care costs, the first step is simple: Stop the profiteering by Big Insurance.

Insurers Are Rejecting More Prescriptions Than Ever, New Study Finds

First-time prescription rejections rose 67% between 2018 and 2024, with nearly half of denied patients receiving no comparable medication within 90 days.

A new study published in JAMA puts hard numbers behind something patients and doctors have been telling me for years: getting a prescription filled increasingly means running an obstacle course of denials, prior authorization forms, and step therapy requirements — and a lot of people never make it through.

Researchers from Johns Hopkins Bloomberg School of Public Health and the American Enterprise Institute analyzed more than 2 million first-time attempts to fill prescriptions for brand-name drugs that have no generic alternative, using pharmacy claims data covering nearly every major insurance market in the country: commercial plans, Medicare, Medicare Advantage, Medicaid, and ACA marketplace plans. The data ran from January 2018 through September 2024.

Here’s what they found:

  • Rejections are way up. In 2018, insurers turned down 24.3% of first-time fill attempts for these drugs. By 2024, that had jumped to 40.7% — a 67% increase.
  • Coverage rules are the driver. Overall, 32% of initial attempts were rejected: 14.8% because the drug was excluded from the formulary outright, and 17.2% because it required prior authorization or step therapy — insurer-speak for “try something cheaper first.”
  • Nearly half of rejected patients got nothing. Of everyone who was turned down, only 38.6% eventually got the original drug within 90 days, and 13% got a different drug in the same class. But 48.4% — essentially half — received no medication in that class at all within three months.
  • Delays add up. Even patients who eventually got their medicine waited an average of 12.2 days after the initial rejection.
  • Where you get your coverage matters enormously. Rejection rates were highest in ACA marketplace plans (48.7%) and Medicaid managed care (49.8%) — nearly one in two prescriptions. Traditional Medicare drug plans (24.0%) and Medicare Advantage (19.8%) had noticeably lower rejection rates.

Why this matters

The insurance industry has a ready answer for all of this: prior authorization and step therapy exist to control costs and steer patients toward drugs with the best evidence behind them, not just the most expensive ones. There’s some truth in that — utilization management can reduce unnecessary spending and has, in some cases, nudged prescribing toward cheaper, equally effective alternatives.

But this study makes clear that the tradeoff is not small or hypothetical. When nearly half the people who get turned down simply never receive treatment in that drug class — not “later,” not “with a substitute,” but never, at least within 90 days — that’s not utilization management working as intended but as a barrier that outright blocks care for a huge share of patients, many of whom presumably still need what their doctor originally prescribed.

The study lands in the middle of a real fight over these practices. Federal regulators have been pushing to speed up and standardize prior authorization. Several states have passed laws limiting insurer review times, exempting doctors with track records of low rejection rates from prior authorization requirements altogether, or requiring plans to honor authorizations a patient already has when they switch coverage.

Insurers will point out that some of the increase in rejections reflects more brand-name drugs entering the market during the study period. But that doesn’t explain away the core finding: patients across every type of coverage are hitting more roadblocks, and for close to half of them, the medicine their doctor decided they needed simply never arrives.

Average Medicare vs Medicaid Reimbursement to Hospitals as a Percentage of Cost

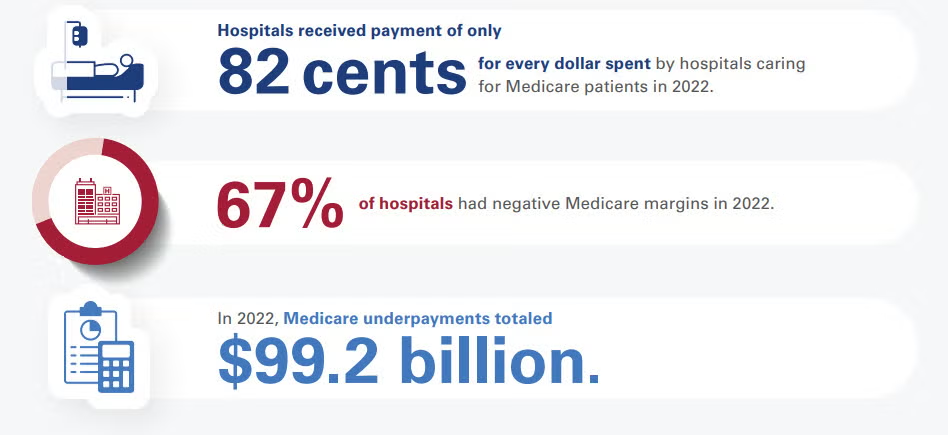
Medicare reimburses hospitals at an average of 82% to 87% of the actual cost of providing patient care. According to long-term data from the American Hospital Association (AHA) and the Congressional Budget Office (CBO), this means hospitals face a shortfall, receiving roughly 82 to 87 cents for every dollar they spend caring for Medicare beneficiaries.

Financial Impact and Hospital Margins

Because Medicare reimbursement rates are fixed by the federal government, they often fail to keep pace with the rising costs of labor, drugs, and supplies:

  • Negative Profit Margins: The Medicare Payment Advisory Commission (MedPAC) reported that hospitals experienced an average -12% margin on fee-for-service Medicare services, with projections remaining deeply negative at -10%. [1]
  • Widespread Losses: Approximately 67% of all U.S. hospitals operate at a net financial loss specifically on their Medicare patient population. [1]
  • Aggregate Underpayments: This payment-to-cost deficit translates to roughly $99.2 billion in annual underpayments that hospitals must absorb or offset through other revenue streams.

How Hospitals Balance the Deficit

To remain financially viable while absorbing underpayments from Medicare and Medicaid, hospitals rely on cost-shifting to the private sector:

  • Commercial Insurance Rates: Private, employer-sponsored health plans pay hospitals significantly more to subsidize public program shortfalls. On average, commercial insurers reimburse hospitals at 196% to 199% of Medicare rates.
  • Payer Mix Vulnerability: Hospitals located in regions with high concentrations of elderly or low-income residents are at higher financial risk. At 96% of U.S. hospitals, government programs (Medicare and Medicaid) account for more than half of all inpatient days.

If you are tracking hospital financials or healthcare policy, would you like to see how Medicaid reimbursement rates compare, or look closer at the differences between inpatient and outpatient Medicare payment structures?

Medicaid reimburses hospitals at an average of 88% to 90% of the actual cost of care, but this figure heavily relies on supplemental government funding. Without these extra state and federal payments, standard Medicaid base rates only cover roughly 58% to 65% of hospital costs.

Because Medicaid is jointly funded by federal and state governments, the exact payment-to-cost ratio varies wildly by state, fluctuating between 49% and 169% of Medicare benchmarks.

The Core Components of Medicaid Payments

Medicaid hospital payment structures are highly complex and divided into two primary tiers:

  • Base Rates (Severe Shortfalls): Standard Fee-For-Service (FFS) base rates and Managed Care Organization (MCO) plans pay well below actual expenditures. According to industry data published by the American Hospital Association (AHA), standard MCO plans cover just 65 cents on the dollar, while FFS base payments plummet to 58 cents on the dollar.
  • Supplemental Payments (The Lifeline): To minimize this gap, states issue extra payments to hospitals. These account for over 52% of total Medicaid hospital spending nationwide and are broken down into:
    • Disproportionate Share Hospital (DSH) Payments: Extra funds legally required for safety-net hospitals serving high volumes of low-income or uninsured patients.
    • Non-DSH Supplemental Payments: Upper Payment Limit (UPL) adjustments and state-directed payments meant to artificially boost base rates closer to commercial or Medicare levels.

Operational Impacts on Hospitals

The gap between Medicaid base reimbursement and actual cost strains hospital systems in several distinct ways:

  • Widespread Financial Loss: Even after accounting for all safety-net supplemental payments, roughly 62% of U.S. hospitals operate at a net loss on their Medicaid patient populations.
  • Aggregate Underfunding: The total nationwide Medicaid underpayment deficit adds up to approximately $24.8 billion annually that hospitals must absorb.
  • The Commercial Subsidy: Because public programs underpay, hospitals shift costs onto employer-sponsored health plans. As a result, private insurers are charged nearly double (up to 200%) what Medicare and Medicaid pay for the exact same medical services.

UnitedHealth Has a Bank. Now Washington Wants More Insurers to Act Like One.

The administrations new ACA rules encourage health insurers to offer loans for medical bills instead of addressing the soaring out-of-pocket costs driving Americans into debt.

Most Americans are familiar with UnitedHealth, the largest private health insurer in America – if not because the corporate giant provides their medical coverage, then because of the massive publicity when the CEO of its key subsidiary was assassinated on a Manhattan street in December 2024.

The shooting of Brian Thompson also sparked a nationwide debate over Big Insurance practices, after many came forward with horror stories about their denied claims for urgent medical care or other bad health insurance experiences. Yet there is one thing most Americans do not know about UnitedHealth: It also has a bank.

But a number of physicians did know about Optum Financial by the spring of 2025, and they were not happy. Some doctors said their practices had been forced to borrow money from Optum to deal with a crippling cyberattack on the medical payments system, and Optum then pressured them to quickly repay the money. One New Jersey specialist in pediatric neurology and neurosurgery told The New York Times: “Optum, in my opinion, is acting like a loan shark trying to rapidly collect.”

Now, financially pressed U.S. families might learn what it’s like to owe money to Optum, under a new plan from the Trump administration.

With out-of-pocket medical costs for Americans skyrocketing, new guidelines for the Affordable Care Act marketplace suggest that insurers begin offering loans to patients with sky-high deductibles and unexpected large medical bills, a loan that presumably would be repaid with interest.

The Trump administration’s plan would worsen an existing crisis. In the world’s only developed nation where families experience medical bankruptcy, and with about one-third of families already in debt because of their medical bills, the government’s proposed solution is even more debt.

“We note that multiyear and 1-year catastrophic plans may be able to offer relief from the high deductible and maximum annual limitation on cost sharing through other mechanisms,” reads the final rule. “For example, issuers of catastrophic plans could consider financing the deductible by providing enrollees a loan.”

Experts say the ACA rules for 2027 and 2028 from the Centers for Medicare & Medicaid Services reveal the administration’s focus on expanding consumer choice and reducing federal outlays while ignoring the core issue: higher out-of-pocket costs.

“They’re putting a lot of stock into the idea that people really want these extremely, extremely high deductibles and out-of-pocket costs,” said Katie Keith, director of the Center for Health Policy and the Law at the Georgetown University Law Center. “And so they’re coming up with all these attempts at workarounds, including things like making your insurance company your bank.”

The New York Times noted that UnitedHealth, with its Optum financial unit, is the one large insurer that’s already equipped to offer loan packages to patients who can’t afford their bills. In addition to its controversial program of loans to physician practices, Optum’s bank currently offers government-approved Health Savings Accounts, or HSAs, which allow patients to set aside pre-tax earnings for future medical bills. A UnitedHealth spokesperson wouldn’t comment to the Times on the new ACA rules.

It’s understandable why the Big Insurance icon wouldn’t be eager to weigh in on a concept that will only fuel consumer anger over the increasing unaffordability of health care. U.S. Rep. Shontel Brown, an Ohio Democrat, weighed in on the Trump administration scheme on the social media platform X by noting this would “supercharge medical debt.” She added: “This could ruin people’s finances, while creating a financial incentive for insurers to deny coverage.”

Indeed, a 2025 report from the health-policy organization KFF found that UnitedHealth had – along with two Blue Cross Blue Shield affiliates – one of the nation’s three highest rates of claims denials for its ACA Marketplace policies. Its reported denial rate of 33% was nearly double the overall national rate of 19%. Now UnitedHealth – which posted more than $12 billion in profits in 2025, the highest of the nation’s insurers – could make even more money from denying claims or raising deductibles and offering loans.

The crisis of high out-of-pocket medical costs in America has been spiraling rapidly since the Trump administration and the Republican-controlled Congress rejected extending enhanced federal subsidies that had made coverage under the ACA, or Obamacare, reasonably affordable.

For millions of Americans, the end of those subsidies – with some consumers getting 2026 monthly premium bills that have more than doubled – has meant shifting to the lowest level of Bronze ACA plans, which come with high annual deductibles. This will mean thousands of dollars in bills for an unexpected major illness.

The soaring premiums have also seen many families joining the growing ranks of the uninsured. One early analysis from KFF predicted that as many as 5.5 million Americans – or about 25% of the peak enrollment – will have dropped their ACA insurance by the end of 2026, The new negative aura around health insurance – higher premiums, higher-out-of-pocket costs for those choosing inferior plans, or those without any coverage at all – is behind a recent report that about one-third of all Americans are cutting routine expenditures or even skipping meals to deal with their rising doctor bills and drug costs.

Instead of continuing the subsidies that had brought a steep rise in ACA enrollment earlier in the decade, the Republican-led government insists it is addressing the growing affordability crisis with new options that dangle lower premiums with the much greater risk of painful out-of-pocket costs in an emergency.

The government’s new ACA rules for 2027 increase the number of people who’d be eligible to buy so-called catastrophic plans that might defray costs for an extreme medical emergency but put consumers on the hook for the costs of most doctor visits or prescriptions. This is on top of new rules that will allow insurers to raise deductibles for the third-tier Bronze plans to $15,600 for individual coverage or $31,200 per family.

The Trump administration hoped to boost catastrophic plans to spike their enrollment as high as 3 million Americans, but Louise Norris, the longtime expert who writes for Healthinsurance.org, noted that a variety of factors have prevented any surge in customers for these high-deductible plans. In some states, she noted, premiums are actually lower for the Bronze plans, and this year, only about 67,000 people have signed up for the catastrophic plans.

Norris said the Trump administration’s idea for insurance-company loans is “that you can pay back that deductible over time, [but] I’m not sure that would really offset those other factors in terms of making those plans appealing.” She added that, “if you don’t qualify for subsidies, and you’re looking for the cheapest plan you can get in a lot of areas, that’s actually going to be a Bronze plan.”

So the government seems determined to make catastrophic insurance popular when American consumers don’t really want it.

Instead, the various schemes in the new ACA rules for 2027 and beyond – pitched with a notion of offering consumers more choices instead of the cost relief that Americans need – are projected to cost a whopping $1.3 billion annually, while it’s projected that two million more people will likely drop their ACA coverage because of the expense.

While the Trump administration and its GOP allies on Capitol Hill own this current crisis, Democrats need to acknowledge their own complicity in the situation.

Democrats in the past have bent to insurers’ demands to make sure all the health plans offered in the ACA marketplace have cost-sharing requirements of some amount and also to allow the out-of-pocket maximum to be unaffordably high for most Americans – especially for people with chronic conditions and those with low incomes.

This year’s midterm election is an opportunity for candidates to promise that health care affordability will be a priority. The centerpiece of such an agenda should be lowering the outrageous out–of-pocket maximums. The Lower Out of Pockets NOW coalition, which I founded, supports a bill sponsored by Massachusetts Democratic U.S. Rep. Jake Auchincloss to extend the Biden-era Medicare prescription drug yearly out-of-pocket maximum of $2,000 (rising to $2,100 this year) to people enrolled in ACA marketplace plans.

Some states already offer innovative cost-control plans. For example, Massachusetts now requires issuers of individual coverage and fully insured group coverage to limit increases in the enrollees’ out-of-pocket costs to the Consumer Price Index inflation rate for the Boston area. For 2027, the cap will be 3.6%. The covered expenses include plan deductibles, copayments and coinsurance bills.

When the idea of loans from insurers like UnitedHealth was reported in The New York Times, an attorney commented on social media that “it’s hard to top this level of dystopia.” This is a wake-up call to focus on the real pathways to affordable health care.

Health Brief: Watchdog flags Medicare Advantage denials

https://links.washingtonpost.com/s/vb/-EUvaxFcJplQEX3qaZfdNRAnp0MGOWYaCYHvLqShmKIDlV07Oyi-FlxsNBiavJoMcz3PNclaOcdrmMRGzSHoZfnJ_UcAvJ3UnkmhzjgzOMcVAUM05xj_Se6_iBuNe_Ngi8c_7CjEdxEdF3oWeQ92VLHsXdirR7A0aRXq8Q/Sumw3cirsVT0csIf-v1IYk2xkO4EJnfD/21

In today’s issue:

A federal watchdog is renewing the debate over whether private insurers are overutilizing prior authorization to delay patient careNew polling shows how the Trump administration’s approach to health policy could impact the midterm electionsDrugmakers are tweaking GLP-1 formulations, showing that industry still views the drug category as a revenue winner It’s a sweltering day in Washington, and yet Health Brief persists. 
Medicare Advantage, operated by private insurance plans, has come under scrutiny. (Jenny Kane/AP)
The Lead Brief:

A new report from a federal watchdog found that three of the nation’s largest Medicare Advantage insurers routinely denied requests for post-acute care services, which could intensify scrutiny of prior authorization practices in the rapidly growing program.The Office of Inspector General for the Department of Health and Human Services examined more than 2,000 prior authorization decisions made in June 2024 by Aetna, UnitedHealthcare and Humana.→ That’s the subject of the latest report from The Post’s Christopher Rowland.The OIG focused on services often needed after a hospital stay, including long-term acute care hospitals and inpatient rehabilitation facilities. Delays or denials can leave patients stuck in hospitals longer than necessary or without access to specialized recovery services.The report found denial rates for long-term acute care hospitals ranged from 70 percent to 80 percent, while denials for inpatient rehabilitation services exceeded 50 percent across all three insurers.

Why it matters: 

More than half of Medicare beneficiaries — roughly 35 million people — are now enrolled in Medicare Advantage plans, giving a handful of insurers enormous influence over access to care.“As enrollment in Medicare Advantage continues to grow, so does the urgency and importance of ensuring that [insurance companies] are delivering on the value that the federal government pays them to provide,” the OIG report said.Complaints about Medicare Advantage coverage denials are nothing new, but the report underscores the potential impact they can have.The Centers for Medicare and Medicaid Services, which oversees the Medicare Advantage program,has been working with insurers over the last year to scale back their use of prior authorization.

What to watch: 

The report could add fuel to several legislative proposals on Capitol Hill that would require insurers to submit more information about claim denial rates and, for Medicare Advantage plans specifically, additional encounter data related to patient care. The OIG report found for-profit Medicare Advantage organizations denied coverage more frequently than nonprofit plans, a pattern investigators said suggests financial incentives may play a role in utilization management decisions.→ But the report’s data predates pledges that private insurers have made to decrease use of the practice for all consumers. Companies have reported early progress in reducing prior authorization for many services.“This report reflects data from 2024. Since then, health plans have voluntarily eliminated roughly 6.5 million prior authorizations across markets — including more than 15 percent in Medicare Advantage,” said Mary Beth Donahue, president and CEO of the Better Medicare Alliance.Insurers also pointed to previous findings, including ones from the HHS watchdog in 2018, that raised concerns about whether many inpatient rehab facilities met Medicare’s standards or were providing unnecessary care that ultimately harmed patients.“The reports ignore serious, well-documented concerns about wide variations in the cost and quality of post-acute care and skilled nursing facilities,” said Chris Bond, a spokesperson for insurance industry group AHIP.BUT WAIT, THERE’S MORE→

A companion report issued by the OIG also renews scrutiny of insurers’ use of contractors to conduct prior authorization reviews. Investigators found a UnitedHealth Group subsidiary, formerly known as NaviHealth, denied nursing home care more frequently than insurers themselves or other vendors. The subsidiary, which rebranded to Home & Community Care in 2024, has allegedly used an algorithm to determine care needs. The OIG report doesn’t mention the reported algorithm usage. UnitedHealth Group has maintained that coverage decisions are always made by a human, thereby rejecting claims that the algorithms led to improperly denied care. However, the claims are at the center of an ongoing lawsuit filed by the families of deceased Medicare Advantage patients. The inspector general is urging CMS to take action to ensure plans are not improperly denying care. CMS officials told Christopher the agency is examining insurance denials by collecting data through a pilot program and conducting audits. The agency added that it “will continue using its full range of oversight and enforcement tools to identify potential issues, hold plans accountable and strengthen program integrity while protecting beneficiary access to care.

”Read the full story: “Seniors needed long-term care and rehab. Their private Medicare plans said no.”

Trump Plans – I Mean – Junk Plans Are Back

The Trump administration has announced that it will significantly expand access to so-called catastrophic health insurance plans, which are policies with comparatively low monthly premiums but deductibles so high they often leave families effectively uninsured until a medical crisis strikes. CMS described the move as giving Americans “flexibility” and improving access to “affordable healthcare coverage.” But what I call them are “junk plans”.

Back in October, I warned that these plans (often called short-term, limited-duration insurance plans, or STLDIs) were poised for a comeback as enhanced Affordable Care Act subsidies expired and millions of Americans faced sharp premium increases. Well, now these plans are, in fact, a reality.

The Affordable Care Act outlawed most of these junk-style plans because the law requires insurers to cover health care services people need, including prescription drugs, hospitalization, mental health care and maternity care. The ACA also forced insurers to spend most premium dollars on medical care instead of executive compensation, advertising and shareholder returns.

But the ACA never fully solved the deeper affordability crisis in American health care. Premiums have steadily become much too high. Deductibles and other out-of-pocket requirements have put care out of reach for millions as insurers have continued to shift more costs onto patients while simultaneously becoming larger, more powerful and more profitable. The shortcomings of the ACA and the decisions by the President and congressional Republicans have created the perfect opening for catastrophic plans to return.

ACA Rule Foreshadows New Plan Model in 2028

Affordability’s all the buzz, but Trump’s sweeping payment rule emphasizes consumer choice over cost control.

When families are staring at monthly premiums they can no longer afford, a cheaper option — even one loaded with massive deductibles and coverage gaps — starts looking attractive. That is exactly what insurers are counting on.

In my old job at Cigna, I helped market plans like these. In my book Deadly Spin, I called them what they often really are: “the illusion of coverage.” These policies were designed to look like insurance while minimizing the likelihood insurers would actually have to pay significant claims. Companies like UnitedHealth Group and other insurance and health care conglomerates make enormous profits on catastrophic-style plans because the deductibles are so high and the restrictions so extensive that relatively few claims ever get paid.

Supporters of these plans frame them as “consumer choice.” But choice is a misleading word when many Americans are being financially cornered into skimpier coverage because comprehensive insurance has become unaffordable. People do not think they will get cancer before it happens. No one expects a devasting car crash or for their kid to come down with a confusing illness. The danger with junk plans is that people undoubtedly only discover how weak their coverage is after their lives have already been turned upside down.

And so, both parties in Washington deserve criticism. Republicans are now openly expanding access to catastrophic-style plans. But Democrats also bear responsibility for defending a post-ACA system that still leaves millions of Americans underinsured and financially exposed. Expanding coverage was enormously important. But coverage alone is not enough if using that coverage can still bankrupt you. We need a comprehensive update to the consumer protections in the ACA – expanding junk insurance is not that – and Republicans know better.

The real danger now is that America slowly normalizes a health care system where people are expected to carry insurance cards that offer little meaningful protection until disaster strikes. Once that becomes acceptable, legitimate insurance and junk insurance become indistinguishable.