Medicare Beneficiaries Feel The Pinch When They Can’t Use Drug Coupons

https://khn.org/news/medicare-beneficiaries-feel-the-pinch-when-they-cant-use-drug-coupons/

This week, I answered a grab bag of questions about drug copay coupons and primary care coverage on the health insurance marketplace.

Q: My doctor wants me to take Repatha for my high cholesterol, but my Medicare drug plan copayment for it is $618 a month. Why can’t I use a $5 drug copay coupon from the manufacturer? If I had commercial insurance, I could. I’m on a fixed income. How is this fair?

The explanation may offer you little comfort. Under the federal anti-kickback law, it’s illegal for drug manufacturers to offer people any type of payment that might persuade them to purchase something that federal health care programs like Medicare and Medicaid might pay for. The coupons can lead to unnecessary Medicare spending by inducing beneficiaries to choose drugs that are expensive.

“The law was intended to prevent fraud, but in this case it also has the effect of prohibiting Part D enrollees from using manufacturer copay coupons … because using the coupon would be steering Medicare’s business toward a particular entity,” said Juliette Cubanski, associate director of the Program on Medicare Policy at the Kaiser Family Foundation. (Kaiser Health News is an editorially independent program of the foundation.)

The coupons typically offer patients with commercial insurance a break on their copayment for brand-name drugs, often reducing their out-of-pocket costs to what they would pay for inexpensive generic drugs. The coupons help make expensive specialty drugs more affordable for patients. They can also increase demand for the drugmaker’s products. If patients choose to use the coupons to buy a higher-cost drug over a generic, the insurer’s cost is likely to be more than what it would otherwise pay.

In addition, consumers should note that the copay cards often have annual maximums that leave patients on the hook for the entire copayment after a certain number of months, said Dr. Joseph Ross, associate professor of medicine and public health at Yale University who has studied copay coupons.

The coupons may discourage patients from considering appropriate lower-cost alternatives, including generics, said Leslie Fried, a senior director at the National Council on Aging.

According to a 2013 analysis co-authored by Ross and published in the New England Journal of Medicine, 62 percent of 374 drug coupons were for brand-name drugs for which there were lower-cost alternatives available.

Q: Last year, my marketplace plan covered five primary care visits at no charge before I paid down my $2,200 deductible. This year, it doesn’t cover any appointments before the deductible, and I had to pay $80 out-of-pocket when I went to the doctor. Is that typical now? It makes me think twice about going.

Under the Affordable Care Act, marketplace plans are required to cover many preventive services, including an annual checkup, without charging consumers anything out-of-pocket. Beyond that, many marketplace plans cover services such as some primary care visits or generic drugs before you reach your deductible.

The likelihood of having a plan that offers some cost sharing for primary care before you reach your deductible (rather than requiring you to pay 100 percent of the cost until you hit that amount) varies significantly depending on whether you’re in a bronze, silver or gold plan, according to a recent analysis by the Robert Wood Johnson Foundation.

In 2018, 77 percent of silver-level plans offered some cost sharing for primary care visits before enrollees had paid off their typical deductible of $3,800, the analysis found. In most cases, that means people owe a copayment or coinsurance charge for each visit until they reach their deductible. A small number of plans offered a limited number of no-cost or low-cost visits first, and then people using more services either had to pay the full charge for each visit or owed cost sharing until the deductible was met.

Bronze plans were much stingier in what they offered for primary care before people reached their deductible, which was $6,400 or higher in half of plans. Only 38 percent of bronze plans offered any primary care coverage before the deductible, and generally patients still had to pay a copayment or coinsurace. A smaller percentage of bronze plans offered limited visits at no cost or low cost before the deductible.

The share of people who chose bronze plans grew from 23 percent in 2017 to 29 percent this year, said Katherine Hempstead, a senior policy adviser at the Robert Wood Johnson Foundation. While premiums are typically significantly lower in bronze plans than other “metal”-level plans, it can be worthwhile to check out how plans handle primary care services before the deductible, she said.




How The Farm Bill Could Erode Part Of The ACA

https://khn.org/news/how-the-farm-bill-could-erode-part-of-the-aca/

Some Republican lawmakers continue to try to work around the federal health law’s requirements. That strategy can crop up in surprising places. Like the farm bill.

Tucked deep in the House version of the massive bill — amid crop subsidies and food assistance programs — is a provision that supporters say could help provide farmers with cheaper, but likely less comprehensive, health insurance than plans offered through the Affordable Care Act.

It calls for $65 million in loans and grants administered by the Department of Agriculture to help organizations establish agricultural-related “association” type health plans.

But the idea is not without skeptics.

“I don’t know that anyone at the Department of Agriculture, with all due respect, knows a darn thing about starting and maintaining a successful insurance company,” said Sabrina Corlette, a professor and project director at the Georgetown University Health Policy Institute.

Association health plans are offered through organizations whose members usually share a professional, employment, trade or other relationship, although the Trump administration is soon to finalize new rules widely expected to broaden eligibility while loosening the rules on benefits these plans must include.

Under that proposal, association plans would not have to offer coverage across 10 broad “essential” categories of care, including hospitalization, prescription drugs and emergency care. They could also spend less premium revenue on medical care.

Under the farm bill, the secretary of Agriculture could grant up to 10 loans of no more than $15 million each, starting next year, to existing associations whose members are ranchers, farmers or other agribusinesses.

The language is strikingly similar to a bill introduced April 12 by Rep. Jeff Fortenberry (R-Neb.), a supporter of association health plans. He did not respond to calls for comment.

Although the farm bill is usually considered “must-pass” by many lawmakers, it is currently facing pushback because of controversy surrounding other parts of the measure, mainly language that would add additional work requirements to the food stamp program.

Still, the focus on association health plans won’t go away.

The plans — coupled with another Trump administration move to make short-term insurance more widely available — could draw healthier people out of the ACA markets, leaving the pool of beneficiaries with higher percentages of people who need medical care. And that, some say, could drive up premiums for those who remain.

The National Association of Insurance Commissioners, for example, has warned that association plans “threaten the stability of the small group market” and “provide inadequate benefits and insufficient protection to consumers.”

Actuaries have made similar arguments.

Others are concerned about the idea of the government providing funding for such plans.

“We have reams of experience with AHPs that have gone belly up … and the notion that we should put taxpayer money into them is irresponsible,” said Georgetown University’s Corlette.

She was referring to the industry’s mixed track record with plans. Some have served members well, but other plans have been marked by solvency problems that left consumers on the hook with unpaid medical bills or were investigated for providing little or no coverage for such things as chemotherapy or doctor office visits.

It’s not fair to simply focus on the failures, countered attorney Christopher Condeluci, who served as tax and benefits counsel to the Senate Finance Committee and now advises private clients, some of whom are interested in association plans.

“Some AHPs were not successful,” he agreed. “But there’s arguably more examples of AHPs that work. The trouble is everyone focuses on the negative.”

Although the GOP generally supports association plans, using taxpayer funds to help start them could prove problematic for some conservatives in Congress.

Many Republican lawmakers expressed concerns about the use of tens of millions of taxpayer dollars to start insurance co-ops that were part of the ACA, most of which failed.

“The hard-earned tax dollars collected from working Americans, sitting at Treasury right now, are not venture capital, said Rep. Kevin Brady (R-Texas) at a subcommittee hearing in November 2015. Currently, Brady is chairman of the powerful House Ways and Means Committee.

The provision could also be popular in rural areas.

“We think it’s a good idea,” said Rob Robertson, chief administrator for the Nebraska Farm Bureau Federation, whose group is considering sponsoring one.

About half of his members, Robertson said, have a spouse working a non-farm job, mainly for insurance coverage. Of those who buy their own plan, some are facing astronomical premiums and are looking for relief.

“I can’t think of any sector that is affected more by the huge premium increases under Obamacare than farmers and ranchers,” he said.

The farm bill — including the AHP provision — was approved by the House Committee on Agriculture in mid-April, and is currently awaiting floor consideration. Meanwhile, a final rule on the Trump AHP rule, which has drawn more than 900 comments from supporters and opponents, could be issued as early as this summer.


Health Insurers Had Their Best Quarter in Years, Despite the Flu

https://www.bloomberg.com/news/articles/2018-05-03/health-insurers-had-their-best-quarter-in-years-despite-the-flu

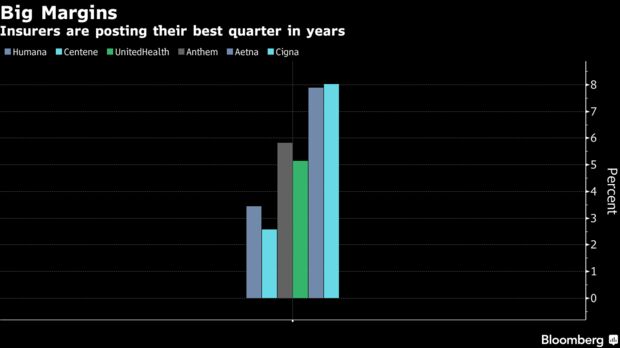
Here’s a look at how the margins of the largest in the quarter, based on data compiled by Bloomberg:

U.S. health insurers just posted their best financial results in years, shrugging off worries that the worst flu season in recent history would hurt profits.

Aetna Inc., for instance, posted its widest profit margin since 2004. Centene Corp. had its most profitable quarter since 2008. And Cigna Corp., which reported on Thursday, had its biggest margin in about seven years.

Analysts at Morgan Stanley, in a research note, said insurers are in the midst of a “hot streak.”

One big reason for the windfall is the tax cuts passed by Congress last year, which in some cases more than halved what the insurers owe the government. Aetna said its effective tax rate fell to 16.8 percent from 39.6 percent, for example. Many insurers also spent less on medical care than analysts had expected, even taking into account increased spending on flu treatments.


Building the bench: Hospitals and health systems prepare for boomer retirement wave

http://www.modernhealthcare.com/article/20180505/NEWS/180509944


TriHealth asked its vice president of finance to shadow executives at an affiliated health system.

Sending a senior executive off-site to expand his perspective was part of the Cincinnati-based health system’s leadership institute, which aims to develop the skills of some 1,000 administrative and physician executives and prepare them for new roles.

While many executives move around within their organization’s network, the approach aimed to expose the employee—who had spent much of his career at TriHealth—to another corporate culture and operations.

“We obsess about spending $2 million on a CT scanner, but we can’t find a way to spend $10,000 on investing in our leaders,” said TriHealth CEO Mark Clement, who launched the system’s leadership institute about ½ years ago. “I would argue that investments on improving talent within our organization produce dividends far greater than a piece of equipment.”

For many providers, it’s the end of an era. Hospital, health system and physician group executives are seeking new leaders. They are prompted by an exodus of top healthcare executives, a generational transfer of power highlighted by the departures of senior managers like Dr. Toby Cosgrove, former Cleveland Clinic CEO; Michael Murphy, CEO of Sharp HealthCare who is retiring in 2019; and outgoing Mayo Clinic CEO Dr. John Noseworthy.

Millennials have claimed the largest share of the U.S. workforce, with 35% of workers in 2017, according to the Pew Research Center. As more boomers eye retirement, providers will look to fill a void of institutional knowledge.

Organizations are actively searching for what’s next and who will take them there. Industry consolidation is accelerating that conversation. But there is wide variation on their approach and level of preparation.

There’s a lot at stake, both from a cultural and financial perspective, said Mark Armstrong, vice president of consulting operations at Quorum Health Resources. Good managers translate to engaged employees, he said.

But only about 33% of U.S. workers are actively engaged in their jobs, and a mere 15% of employees strongly agree the leadership of their organization makes them enthusiastic about the future, according to a 2016 poll by Gallup. The firm estimates that disengaged employees cost the U.S. $483 billion to $605 billion each year in lost productivity.

“Even when systems know someone is retiring, it is interesting how few of them still don’t have an assertive plan in place,” Armstrong said. “Any kind of turnover can be disruptive, especially if there has been a trend of declining performance. It’s not unusual for a ratings agency to have heightened concerned when a CEO leaves.”

Almost every system grapples with a huge retention problem, which can make it difficult to plan ahead, said Alan Rolnick, CEO of Employee Engagement and Retention Advisors. The most costly departures are often experienced nurses, he said.

“It’s not just the cost of replacement but the loss of institutional knowledge,” Rolnick said.

TriHealth’s leadership program highlights potential candidates within the system who could fill upcoming vacancies. It puts executives on a multiyear track that assesses potential areas for improvement and exposes them to systemwide quarterly leadership training sessions and other development opportunities. The company’s vice president of finance, Brian Krause, spent a week at BJC HealthCare in St. Louis, relying on connections TriHealth had with the organization. Krause is also planning on spending some time at the University of Pennsylvania Health System, as well as a few other systems.

Since launching the institute—which is conducted with the help of the consultancy Studer Group—TriHealth’s employee engagement improved from the 26th to the 74th percentile, which has helped the organization generate a 3.5% operating margin—one of its highest margins in recent history, Clement said. Its patient experience scores are also up from the 50th percentile to the 75th, helping to drive an increase in admissions, bucking the national trend.

Ideally, promoting from within will ensure cultural and operational continuity and motivate executives, Clement said. “When you bring new senior executives in from other organizations, it can be a threat to the culture,” he said. “For an organization like ours that has invested a lot of money in building a culture based on value, engaging team members and flattening the organization, it’s often best to promote from within.”

Outside perspectives

Ascension has development programs similar to TriHealth, including quarterly leadership meetings and a series of classes. The St. Louis-based health system pairs its administrators with clinician executives in each of its markets. It shuffles executives within its vast hospital network to provide new perspectives and fill roles in regions where it can be hard to recruit qualified employees.

Ascension also recently launched a diversity inclusion campaign that seeks to cultivate minority leaders.

“The types of leaders are changing,” Ascension CEO Anthony Tersigni said at the American College of Healthcare Executives’ 2018 Congress on Healthcare Leadership in March. “The time for guys like me who started as a hospital operator is passing.”

The CEO of a Fortune 100 company told Tersigni several years ago that he spends about 30% of his time on leadership development. Tersigni, who at the time only spent a fraction of that on cultivating executives, said that interaction completely changed his perspective. Ascension has since partnered with a number of universities to build a better leadership curriculum and management pipeline.

“Disruption in the healthcare industry is not going to come from the hospital across the street, it has been coming from outside the industry,” Tersigni said. “We need to understand how they think, how they act, how they make decisions, because it is a lot faster than healthcare can dream of.”

Renton, Wash.-based Providence St. Joseph in 2017 partnered with the University of Great Falls in Montana, in part, to create a stable pipeline of managers to feed into the integrated health system. The university, which was renamed University of Providence, will include professional and certificate programs for Providence St. Joseph’s more than 111,000 employees.

The health system has also implemented mentoring and leadership development programs that have increased its women executive cohort by 50% over a three-year period.

“Diversity begets diversity,” said Dr. Rod Hochman, CEO of Providence St. Joseph, adding that women and minority leaders will help the system better understand its most vulnerable populations. “We are looking for folks with different perspectives who can help lead us through this time of change.”

Whether the successors are internal or external, establishing a strong executive pipeline requires a proactive and standardized approach, and the board should take the lead, industry analysts said.

A health system should identify the competencies it needs to lead the team going forward and where the gaps are, said Craig Deao, a senior leader at Studer Group. “The three keys leaders of tomorrow need to have are getting people to do things better—performance improvement; getting them to do new things—innovation; and helping people do those things—engagement,” he said.

Managing the process rather than the people will translate to more innovative and engaged employees, according to Rolnick. It starts with communication, he said.

“Today, the average employee of a hospital has no idea of the strategic direction of their organization and what their role is,” Rolnick said. “You have to tell them as much as you can, and be open and honest.”

Beyond employee engagement, executives need to understand how to interact with patients. As the industry adapts to thinking of patients as consumers, that requires a different lens, Deao said.

“People need to understand how to shape behavior and apply concepts of psychology to running the business,” he said.

Help from outsiders

While many systems have traditionally preferred to promote from within, that dynamic is changing as providers place more value on the skills industry outsiders offer. Notably, an executive from a major technology company will join Ascension later this year as its new chief digital officer.

Healthcare is becoming more consumer- and technology-oriented. Health systems are also focusing more on nutrition, transportation, education, fitness and other social factors that influence an individual’s health.

Novant Health, for instance, is launching a new leadership program that looks to train untapped community leaders in Charlotte-Mecklenburg, N.C. The program involves a combination of teaching sessions and mentoring that aims to reach individuals who otherwise wouldn’t have access to programs that hone their leadership skills, said Tanya Blackmon, executive vice president and chief diversity and inclusion officer at Novant.

While there is a significant learning curve, experience in consumer insight, marketing or technology can better equip individuals to tackle healthcare’s current challenges, said David Schmahl, executive vice president of consultancy SmithBucklin and chief executive of its healthcare and scientific industry practice.

“The experience people are obtaining in leadership roles outside the healthcare field is critical,” he said.

The role of healthcare leadership has evolved into a platform used to convey a moral foundation, spanning conversations from racism to gun control. They have to balance their role as an influencer while dealing with budgets, managing their boardrooms, implementing both long-term visions and short-term goals, and maintaining an engaged workforce.

The average tenure of healthcare executives and managers is also decreasing, particularly among CEOs, nurses and physicians, which exacerbates labor shortages. A C-suite executive’s pay is still tied to financial metrics, but quality, safety and patient satisfaction are becoming a more prominent determinant.

While Novant’s initiative isn’t necessarily geared to develop successors, it signifies how the definition of a leader is evolving.

“We are looking at trying to tap talent across all spectrums,” Blackmon said. “We’re not leaving any area untapped.”


Caught in the Theranos Wreckage

The high-profile investors, including Ms. DeVos and Mr. Murdoch, collectively invested about $600 million in the company Theranos

Even some of the world’s richest people may get duped, according to newly unsealed documents in a lawsuit filed on behalf of investors in the failing blood-testing company Theranos.

High-profile investors who collectively lost hundreds of millions of dollars included Walmart’s Walton family, the media mogul Rupert Murdoch, as well as Betsy DeVos, the secretary of education and her relatives.

The list of investors, which was first reported by The Wall Street Journal, came to light as part of a class-action lawsuit brought in 2016 by Robert Colman, a retired Silicon Valley investment banker, who claims that Theranos misled investors about its business and technology.

Theranos, founded by Elizabeth Holmes when she was a 19-year-old Stanford University dropout, promised to revolutionize the lab industry using a few drops of blood from a simple finger-prick to look for everything from diabetes to cancer, at a fraction of the cost of a traditional blood test.

The company became a Silicon Valley fairy tale, with investors awarding the privately held company a valuation of around $9 billion. But the story began to unravel in October 2015 after The Wall Street Journal, owned by Mr. Murdoch’s News Corp., began questioning whether the tests worked. Theranos became the subject of federal investigations into its testing and claims of proprietary technology, which were called “nanotainers.” Much of the time the company had to resort to using conventional blood testing methods, unable to get federal approval for any test but one for Herpes.

Theranos and its founder also became embroiled in a series of lawsuits, involving investors as well as one of its key partners, Walgreens, a large drugstore chain, where it offered its tests. The company reached a settlement with Walgreens last August.

In March, the Securities and Exchange Commission charged Ms. Holmes with fraud, accusing her of exaggerating and lying about her technology to attract investors. As part of the S.E.C. action, Ms. Holmes agreed to pay $500,000, give up control of her company, and is barred from serving as an officer or director of any public company for 10 years. She and Theranos did not admit nor deny the allegations.

Theranos still faces the class-action lawsuit, and may still be subject to a criminal investigation by the United States attorney in San Francisco. The company’s future is unclear. The company did not respond to requests for comment.

Theranos had always boasted a star-studded list of investors and directors — its board included the former secretaries of state George P. Shultz and Henry A. Kissinger, two former United States senators, and Gen. Jim Mattis, the current secretary of defense. But while some high-profile investors’ links to Theranos had been previously known, the new documents provide a detailed list of financial amounts.

The Walton family invested about $150 million in 2014 through two separate entities, according to the investor list. Mr. Murdoch put in about $125 million, and the extended family of Ms. DeVos invested about $100 million.

“It’s obvious that they are highly disappointed in them as a company and as an investment,” said Greg McNeilly, the chief operating officer of The Windquest Group, the holding company of Ms. DeVos and her husband. Mr. McNeilly said the $100 million was a joint investment across multiple generations and branches of her family, and described the share held by Ms. DeVos and her husband as “minor.”

Other prominent investors, according to the list, included the Cox family; the Atlanta billionaires who own the media conglomerate Cox Enterprises and who invested $100 million; and a company affiliated with Mexican billionaire Carlos Slim that put in about $30 million. Robert K. Kraft, the owner of the New England Patriots, invested $1 million.

Representatives for Mr. Kraft, the Walton family, Cox Enterprises and News Corp. declined to comment.