


Cartoon – Moving to a Shared Leadership Model


Starting last March, retail giant Walmart now requires that its employees use a select network of 800 diagnostic imaging providers, or face additional out-of-pocket costs, according to an article this week from Kaiser Health News. Lisa Woods, Walmart’s senior director of benefits design, said high error rates in imaging studies were the driver for establishing the program, with the perspective that “a quality MRI or CT scan can improve the accuracy of diagnoses early in the care journey.”
The network was created in partnership with New York-based Covera Health, a technology company that has amassed information on thousands of imaging facilities nationwide, and uses independent radiologists to evaluate a sample of studies to determine facility and radiologist error rates. According to the article, while many employers have steered employees to lower-cost imaging networks, Walmart is the first to do so based on quality of the studies.
Whether this network will be effective in achieving its stated goal—reducing misdiagnoses that lead to unnecessary care and surgery—remains an open question. Poor-quality imaging undoubtedly leads to repeat studies, which carry significant costs. But many other factors (clinical judgement, incentives, patient preferences) contribute to the decision to perform surgery. Defining imaging “quality” beyond the blunt measures of repeat rates, technical adequacy and radiologist sub-specialization is highly complex, and requires correlation with pathology and clinical outcomes data—a high bar for an outsourced analytics provider.
Despite Walmart’s goals, it will be difficult for imaging providers to differentiate their services solely on quality. The high variability in imaging prices is well-documented, and choice of provider is largely made by consumers, for whom imaging is a commodity service.
Without an activist employer or payer to steer them, consumers will likely continue to choose their imaging providers based on their doctor’s recommendation and out-of-pocket costs.

At the end of my meeting last week with a health system executive team, the system’s COO asked me a question: “Your concept of Member Health describes exactly how we want to relate to our patients, but we’re not sure about the timing. Could you give us a list of the ‘no regrets’ investments you’d recommend for health systems looking to do this?”
We frequently get asked about “no regrets” strategies: decisions or investments that will be accretive in both the current fee-for-service system as well as a future payment and operational model oriented around consumer value. The idea is understandably appealing for systems concerned about changing their delivery model too quickly in advance of payment change. And there is a long list of strategies that would make a system stronger in both fee-for-service and value: cost reduction, value-driven referral management, and online scheduling, just to name a few.
But as I pointed out, the decision to pursue only the no-regrets moves is a clear signal that the organization’s strategy is still tied to the current payment model. If the system is really ready to change, strategy development should start with identifying the most important investments for delivering consumer value.
It’s fine to acknowledge that a health system is not yet ready, but I cautioned the team that they should not rely on the external market to provide signals for when they should make real change. External signals—from payers, competitors, or disruptors—will come too slow, or perhaps never.
At some point, the health system should be prepared to lead innovation, introduce a new model of value to the market and define and promote the incentives to support it. Real change will require disruption of parts of the current business and cannot be accomplished with “no-regrets investments” alone.

In perusing the excellent work of the Peterson-Kaiser Health System Tracker project, we recently came across an analysis (depicted on the left, below) of Medicare spending patterns broken down by age of beneficiary. Based on 2014 data, the analysis shows how much was spent per capita in traditional Medicare fee-for-service on beneficiaries of each age. (The analysis excludes Medicare Advantage data, and also doesn’t include beneficiaries aged 65, for whom a full year of spending data wasn’t available.)
What’s interesting is how spending patterns differ across age cohorts—inpatient spending peaks at age 92 and then declines, spending on physician services peaks at age 85, skilled nursing and hospice spending ramp up quickly for much older beneficiaries. To see how these patterns might play out if applied to the Baby Boom generation, we combined the Peterson-Kaiser analysis with our earlier look at generational aging. The result is the chart on the right, below, which shows how each bucket of spending will increase over the coming 25 years given aging of the population.
A couple of interesting observations from this (admittedly imperfect) analysis.
First, the sheer size of the baby boom generation will drive a huge increase in Medicare spending over the next 25 years. And a full third or more of the total Medicare spend on Baby Boomers isn’t even captured here—that will come via payments to Medicare Advantage plans.
Second, inpatient care drives a huge amount of the total spend. It’s clear that an urgent priority is finding ways to shift spending from the light grey bars (inpatient) to the other segments—we need to pull forward the shift from inpatient to other settings from where it was in 2014’s population. Recall that this is traditional Medicare—strategies like accountable care organizations (ACOs) and other care management/population health reforms will be critical here.
Finally, in addition to changing the trend with innovations in care delivery models, we should expect technology and pharmaceuticals to play a role in inflecting the shape of this graph. Whether that impact will produce a net savings or a net increase in spending remains to be seen.

In other healthcare news from the Evergreen State, Gov. Inslee also signed a law this week that will provide a new long-term care benefit for state residents starting in 2025. In the furthest-reaching legislation of its type nationally, the new Washington law puts in place a payroll tax of 0.58 percent starting in 2022, and creates a year-long, $100/day allowance for state residents that can be used to pay for nursing home fees, at-home caregivers, and other long-term care needs.
Family members who are full-time caregivers can also receive compensation. Like other states, Washington spends a growing portion of its state budget on paying for long-term care for aging residents, putting a heavy burden on the finances of its Medicaid program that’s expected to worsen as the Baby Boom generation ages. In addition to nursing and caregiver services, the new benefit can also be used for in-home meals, housing repairs, and other services that impact health status.
As with its “public option” plan, Washington has taken the lead on another healthcare coverage issue that will eventually need to be addressed nationwide: the fact that seniors are entering retirement entirely unprepared for the amount they’ll need to spend on long-term care.
Medicaid currently pays for two-thirds of nursing home care and 60 percent of all long-term care costs, and no state is currently prepared for the amount of spending that will be required over the next 25 years. Almost no one buys long-term care insurance, which is unaffordable for most. Any serious attempt to expand coverage over the next few years must take on this critical issue.

On Monday, Washington Gov. Jay Inslee signed into law the nation’s first “public option” health plan, to be sold on the state’s individual health insurance exchange, starting during next year’s open enrollment period. Inslee, who is also a candidate for the Democratic Presidential nomination, characterized the new plan as a “way for our state to push back” on the Trump administration’s efforts to roll back the Affordable Care Act (ACA).
The plan, called Cascade Care, is not quite the same as a true, government-run plan of the type proposed by some during the drafting of the ACA; rather, it creates a category of private insurance plans that will cap provider and facility rates at 160 percent of Medicare reimbursement, with the goal of lowering premiums for consumers who shop on Washington’s insurance marketplace.
The public option plan is meant to exert competitive pressure on other plans in the market in an attempt to drive premiums down, but experts expect the new plan to produce only a modest 5-10 percent savings for consumers. In 2018, average premiums on Washington’s exchange rose 38 percent, resulting in lower overall enrollment levels. Other states, including Colorado and Connecticut, are considering similar “public option” plans.
It’s notable that Washington’s approach is explicitly built around reducing payment to hospitals and doctors—any serious efforts to lower premiums will almost certainly have the same impact.
As the politics of healthcare continue to heat up, we’d expect more such proposals to gain traction across the country.
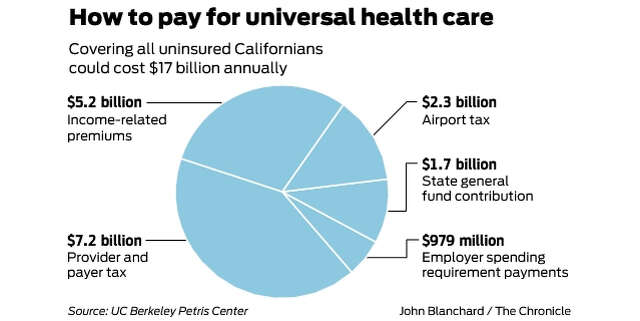
Universal health care in California could cost $17.3 billion a year, under one plan proposed Friday by UC Berkeley health policy researchers.
The paper offers one path for getting about 3 million uninsured Californians health coverage. It is one of several recent estimates from researchers and legislators who have devised various ways to work toward universal coverage in the state. It is not a plan for a single-payer system.
The figure is significantly higher than other analyses, which found that working toward universal coverage by expanding Medi-Cal insurance for the poor would cost less than half of that. That is because the paper builds in the assumption that the uninsured would get on private health insurance plans, whereas other estimates factor in federal funding for getting more people on Medi-Cal, which is jointly paid for by the federal and state governments.
The paper, by Richard Scheffler and Stephen Shortell of Berkeley’s School of Public Health, proposes a mix of new taxes on the health care industry, California employers and airline travelers, paired with contributions from the state’s general fund and premium payments from individuals who are now uninsured.
The ideas, presented Friday to a group of California health policy researchers and advocates, are considered one early stab at financing universal coverage and are not included in legislative proposals.
The largest source of financing, 41 percent, would come from a 3 percent tax on the revenue of hospitals, nursing homes, drug companies, home care providers and insurance companies, which would generate an estimated $7.2 billion a year. The tax would not apply to public hospitals.
The next largest source of funding, 31 percent or $5.2 billion, would come from currently uninsured residents who would pay a monthly premium for a health plan — envisioned as a plan bought through the insurance marketplace Covered California. The premium would be paid by those who earn too much to qualify for Medi-Cal, the insurance program for the poor, and would average out to $123 a month per person. The authors do not specify how many people would pay this premium, or address how to incentivize this population — many of whom are undocumented and hesitant to participate in government programs — to buy into the system.
The paper also proposes a tax on international and business class travelers who fly into and out of California’s five largest airports: Los Angeles International Airport, San Francisco International Airport, San Diego International Airport, Oakland International Airport and San Jose International Airport. The taxes would be $50 per ticket for domestic business class passengers, $60 per ticket for for economy international passengers and $250 per ticket for international business passengers. These five airports see a collective 188 million passengers each year, according to the authors’ analysis of California Department of Transportation air passenger traffic data. The tax would generate $2.3 billion a year.
The remaining funding would come from the state’s general fund in the amount of $1.7 billion, and a tax on employers that would generate $979 million. The employer tax would be modeled after Healthy San Francisco, a program started in 2007 to cover the city’s 14,000 uninsured residents. It would require employers that don’t provide insurance to their workers to pay into a fund by levying a 4 percent surcharge on customers. It would apply to for-profit employers with more than 20 workers and nonprofit employers with more than 50 workers.
Under the plan, the revenue generated through these proposed new taxes would go toward what’s known as integrated care systems to expand their geographic reach and offer more insurance plans on Covered California. The biggest and most well-known integrated system is Kaiser, which provides both the insurance coverage and health care services to its patients, but others have started forming their own integrated care systems in recent years including Sutter Health’s HMO plan, Sharp Health Care in San Diego and HealthCare Partners in Los Angeles. Those integrated care plans would be offered on Covered California.
Scheffler and Shortell say they hope their ideas are a starting point for debate and will inspire action by state legislators.
“We’re hoping for some interest from Sacramento,” Scheffler said.
Some policy experts who reviewed the paper raised questions about some of the proposed taxes and the cost estimate. Ken Jacobs, chair of the UC Berkeley Labor Center, said $17 billion is much too high for achieving universal coverage because it doesn’t take into account the federal dollars that would be available if the state were to expand Medi-Cal to more uninsured people.
A state-level employer mandate could face legal challenges, as Healthy San Francisco did, because of federal preemption issues under the Employee Retirement Income Security Act, or ERISA, Jacobs said. Similarly, the airline tax might run afoul of federal laws regulating interstate commerce and airlines. And the tax on hospitals would need a two-thirds vote in the Legislature and buy-in from health care providers.
“I look at the (financing) as throwing some ideas on the table to start a discussion,” Jacobs said.
Other proposed measures and analyses put different cost estimates for getting California closer to universal coverage. A report released this month by Covered California found that providing more financial assistance to consumers to buy plans would cost between $2.1 billion and $2.7 billion a year.
One bill, AB-4, proposes expanding Medi-Cal to all undocumented adults — a move the Legislative Analyst’s Office has estimated would cost $3 billion annually. Another bill, AB-174, aims to provide financial assistance to those making between $48,000 and $72,000 to buy insurance. It would cost $40 million to $75 million a year, according to estimates included in a previous bill.
Gov. Gavin Newsom’s proposed budget included expanding Medi-Cal coverage to undocumented young adults between ages 19 and 25, and providing state-funded financial assistance to help Californians buy insurance — both of which would be steps toward universal coverage in the state. It is unclear how much the initiatives would cost.


