Clinical Documentation and Coding Top Revenue Cycle Vulnerability

https://revcycleintelligence.com/news/clinical-documentation-and-coding-top-revenue-cycle-vulnerability?eid=CXTEL000000093912&elqCampaignId=8479&elqTrackId=0bbef7eb6fb747b58d9ba9db66b25519&elq=c0883462d36f46f1919e194284b0fcd0&elqaid=8937&elqat=1&elqCampaignId=8479

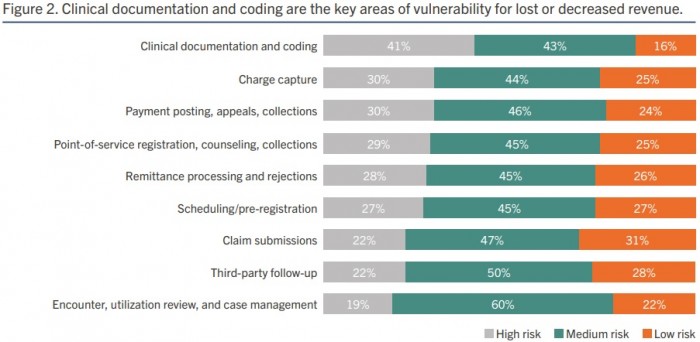
Image shows clinical documentation and coding is the top area at risk of lost or decreased revenue, according to most hospital leaders.

Hospitals are concerned their clinical documentation and coding processes are resulting in lost or decreased revenue, a new survey shows.

Hospital leaders are concerned that their organization’s clinical documentation and coding processes are vulnerable to errors that could result in lost or decreased revenue, according to a recent survey.

Consulting firm and technology vendor BESLER recently partnered with HIMSS Media to identify the greatest industry challenges and potential opportunities for revenue cycle improvement. They surveyed over 100 leaders within finance, revenue cycle, reimbursement, and health information management (HIM) departments at hospitals and acute-care facilities in October 2018.

The recently released survey results showed that 84 percent of respondents believe clinical documentation and coding are high or medium revenue cycle risk.

Hospital finance leaders were the most adamant that clinical documentation and coding presented significant revenue cycle challenges. Almost one-half of finance leaders chose clinical documentation and coding as their greatest revenue cycle vulnerability.

Although, the area was considered high or medium risk by over one-third of revenue cycle, reimbursement, and HIM leaders as well.

Clinical documentation and coding are creating revenue cycle vulnerabilities because solutions are not optimized for the diagnosis-related group (DRG) payment system, respondents shared. Only about one-third of hospital leaders said DRG optimization is a solved problem. In other words, the majority of hospital leaders (68 percent) do not think their solutions are equipped to manage DRG coding.

The DRG payment system has been around for over three decades. And major payers, including Medicare, use the payment system to determine lump-sum payments for hospitals that treat specific diagnoses.

While the payment system is not new, it is constantly evolving. Payers are attempting to get more specific about diagnoses to ensure hospitals are paid accurately for treating patients with certain conditions. The introduction of ICD-10 in 2015 is a prime example of how the industry has changed the DRG payment system.

But DRG changes are not ideal for providers. Hospitals find it difficult to follow and comply with constant DRG changes, and as a result, DRG coding accuracy has decreased. The report stated that the national benchmark for DRG assignment fell from 95 percent under ICD-9 to 72 percent in 2018.

Revenue cycle solutions, however, are optimized for inpatient coding and audits. Approximately 72 percent of respondents felt their technology is optimized for inpatient coding.

The survey also uncovered that respondents thought the accuracy of inpatient coding at their organizations was about the same as the industry benchmark.

Additionally, the majority of respondents (72 percent) agreed that their revenue cycle solutions are optimized for outpatient coding.

Opportunities to improve revenue cycle management technology remain. And poor coding integrity could result in the top two challenges hospitals face: claim denials (49 percent of respondents) and inaccurate reimbursements (47 percent of respondents).
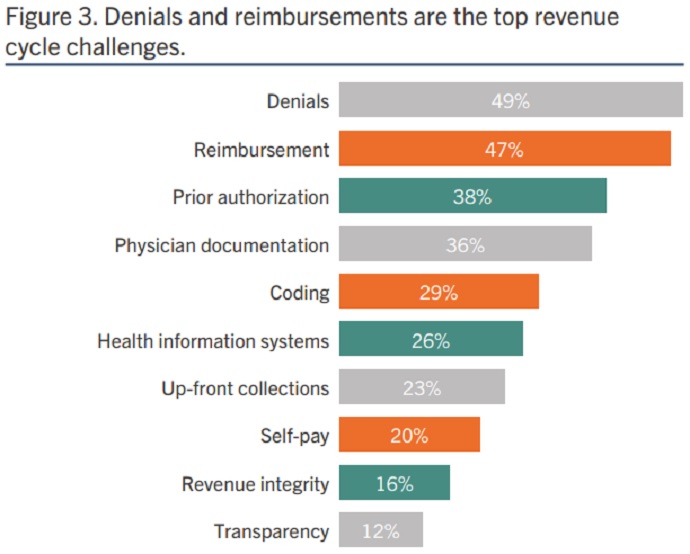
Image shows claim denials and inaccurate reimbursements are the top two revenue cycle challenges, according to most hospital leaders.

Source: BESLER and HIMSS Media

However, hospitals and health systems face significant obstacles with improving their mid-revenue cycle processes, including DRG coding and documentation. Chief among the challenges is a lack of budget. Nearly one-half of hospital leaders (49 percent) said budget constraints prevented their organization from improving DRG coding and documentation.

Nearly the same percentage of leaders also felt return on investment (ROI) was an obstacle. Forty-eight percent of respondents said difficulty proving ROI from investment stopped their organization from executing DRG optimization efforts.

Other obstacles to improving the mid-revenue cycle included:

  • Competing projects (45 percent)
  • Lack of staff/headcount to manage improvement efforts (38 percent)
  • Lack of familiarly with solutions to address challenges (34 percent)
  • Existing solutions already widely entrenched or accepted (32 percent)
  • Overcoming internal perceptions that there is no need for improvement (30 percent)

Respondents identified a variety of challenges, but the survey also found a potential solution for hospitals and acute-care facilities. The survey showed that nearly half of respondents (47 percent) have created a revenue integrity program, which ensures organizations are being fully compliant with coding and billing practices while also achieving operational efficiency and legitimate reimbursement.

That means about 53 percent of hospitals still haven’t implemented a revenue integrity program.

About three-quarters of hospitals with revenue integrity programs reported improvements in net collections, increases in gross revenue capture, and/or reduction in compliance risk.


Cybersecurity for revenue cycle should be a KPI

https://www.healthcarefinancenews.com/news/intermountain-ciso-west-cybersecurity-revenue-cycle-should-be-kpi?mkt_tok=eyJpIjoiTmpCbE5tWmtNak5qTkdOayIsInQiOiJjMUJtNEJkTGxjbTNFWHl0Tmg4YUdrSjhQc0RpQWdid1VDQm5KQjBBeXRTaUluTjdwbnFnVEJ1aDhLcTNVdTl0Z2ZNM2RlbHRNRmJheDNsSVwvVU5qdHlFSkxIWHpBVHFQaVFDbnpPYkpGaU5oU1I5U0JvWEI2bFwveGRvRUpwMEZjIn0%3D

Image result for cybersecurity in revenue cycle

The revenue cycle is an important target for cybercriminals because of the information that flows through it.

Intermountain Healthcare’s chief information security officer Karl West kicked off the HIMSS19 Revenue Cycle Solutions Summit with a strong message for his captive audience. If you’re a revenue cycle leader, you need to understand a fundamental reality: There’s a whole host of data available for hackers in your rev cycle. Not only is there payment information, there is also member information and all of your PHI. All of those are sources of cyber risk.

For example, patient portal credentials are highly valuable for hackers at around $1,500 or more according to one study, West said.

As such, there needs to be a strong partnership between your cyber organization/operation and your revenue cycle. You also need to understand what are the threats and sources of loss. First, there’s phishing. It’s common and proven to be effective. At Intermountain, they phish their employees four times a year to test their proclivity to fall victim. Even though some find the measure frustrating, it’s essential to flushing out vulnerability.

Malware is also a significant security threat. To thwart such threats, it’s important to keep your systems patched. In your system, you need to have someone watching for vulnerability and patching.

“That’s the basic blocking and tackling,” West said.

Another source of loss is the misconfiguration of public-facing systems, which occurs when at build time, the proper protections are not built in.

And then there are nation-state actors, which are harder to protect against because smaller organizations do not have the resources to spend a lot on cybersecurity. Intermountain has a 24/7 security station/operation with eyes on such threats.

Finally, there are theft or loss/inadvertent accidents that involve employee error or bad action.

“If you aren’t, those are things you should be considering,” West said.

As consumerism continues to drive healthcare, the revenue cycle must move with that trend, and in a consumer-driven revenue cycle organization, fraud, breach, patient card information, PHI, personally identifiable information and the cloud are both assets and areas of risk.

As such, vulnerability management in the revenue cycle should be a big part of your operation and claims processing.

“When a caregiver gives care, they must be current on flu shots and vaccines,” West said. “It’s not an option. It’s a condition of employment. It means that the caregiver is protected to the best ability that we can. In the cyber world, it’s the same. Your networks, laptops and servers, how are you protecting them?”

While updates are annoying, vulnerabilities do need to be patched. Most healthcare organizations patch on an annual basis. At Intermountain, however, it is on a weekly or monthly basis. It’s a different mindset, West said. That is because not only did healthcare cyber attacks increase 320 percent between 2015 and 2016, but the attacks are also growing in sophistication. They don’t just slow systems down – they can cripple them for days, weeks or even months.

So, it is important to know that your patches are in place and your action plans are in place, he said. Have arrangements with vendors and partners. And for the many who have migrated to the cloud to streamline and cut costs, develop a strategy that isn’t just focused on one cloud but the whole cloud and know the controls required to protect you. West asked, does your cloud partner have a vulnerability and what are their safety practices?

“Have an inventory of your partnerships and manage them. Establish governance. As the primary organization, you are the one accountable to your patients,” he said.

Have an inventory of your data – where it is stored, where will it move to, and how it will move safely and securely. This should be a key performance indicator (KPI). Classify your data as public, restricted, private, classified or confidential, such that it is properly protected, and have data loss protection tools.

“When you wonder how did one system get taken down and not another, it’s your patching and practices,” West said.


Spending money on the social determinants is an investment

https://www.healthcarefinancenews.com/news/spending-money-social-determinants-investment?mkt_tok=eyJpIjoiTmpCbE5tWmtNak5qTkdOayIsInQiOiJjMUJtNEJkTGxjbTNFWHl0Tmg4YUdrSjhQc0RpQWdid1VDQm5KQjBBeXRTaUluTjdwbnFnVEJ1aDhLcTNVdTl0Z2ZNM2RlbHRNRmJheDNsSVwvVU5qdHlFSkxIWHpBVHFQaVFDbnpPYkpGaU5oU1I5U0JvWEI2bFwveGRvRUpwMEZjIn0%3D

Dr. Claire Pomeroy addresses the social determinants at HIMSS19.

Value-based care demands the switch to wellcare to raise outcomes and decrease costs, Claire Pomeroy says.

Claire Pomeroy, CEO and president of the Albert and Mary Lasker Foundation, an expert in infectious diseases and a long-time advocate for patients, drove home the point of the importance of the social determinants of health by relating a story of a young woman who needed asthma medication but was unable to afford it.

She got a prescription for an inhaler she couldn’t afford, Pomeroy told a full room at HIMSS19. She knew the story because she was that woman. She needed a ride, food and money for a few days and had no way to get any of that, let alone buy a drug she couldn’t afford.

The clinicians followed all of the right clinical protocols for her condition. But, she said, “They didn’t have the information they truly needed to make me better.”

What was needed was for her clinicians to pay attention to the social determinants of health, an issue that providers are increasingly realizing need to be addressed if their population of patients is to remain healthy.

Without this attention being paid to housing, food, transportation and other socio-economic needs, costs will never be brought inline, as hospitals see patients returning to be admitted or get care through the emergency room.

“Our cost and our outcomes demand change,” Pomeroy said.

The statistics show the need. Black mothers die at truly unacceptable rates in this country, she said and all blacks in the United States have a life expectancy that is on average, 10 years less than whites.

All people in the United States who have a college degree live longer than those with a high school diploma. Stress on the job plays a part. And the opioid crisis has led to overdose deaths surpassing the odds of dying than from a car accident.

“We must redesign the U.S. healthcare system from one of sick care to wellcare,” Pomeroy said.

Healthcare makes up only 10 percent of what goes into the social determinants of health. The biggest percentage goes to behavioral patterns, genetic predisposition and social circumstances.

“We work all day and are only impacting 10-15 percent of the social determinants of health,” Pomeroy said. “Spending on social determinants make sense. We need to move beyond pilot programs and start scaling some of these things.”

Hospitals that spend money on housing to take care of their homeless population see a a 93 percent reduction in costs. For every $25 increase in delivered meals for older adults, there’s a 1 percent decline in nursing home admissions.

“Addressing the social determinants is an investment,” she said.

The biggest challenge is lack of funds for hospitals struggling to stay in the black, lack of data and siloed proprietary care information.

Information connectivity allowed one health system to learn that 31 percent of the Medicaid moms in its area were not enrolled in WIC, and therefore not getting access to food and supplies for their babies.

Technology is needed, as are more health policies for reimbursement that address risk adjustment. State innovation models help, as does the Centers for Medicare and Medicaid Services accountable health communities model, a five-year pilot looking at the connection between social assistance, health and costs.

EHRs should include information on housing, food, transportation and other needs. Systems must transform their thinking, create a new strategy, empower multidisciplinary teams, educate health professionals, invest in research and “raise our voices to drive change,” Pomeroy said.


14 hospitals with strong finances

https://www.beckershospitalreview.com/finance/14-hospitals-with-strong-finances-021219.html?origin=rcme&utm_source=rcme

Here are 14 hospitals and health systems with strong operational metrics and solid financial positions, according to recent reports from Moody’s Investors Service, Fitch Ratings and S&P Global Ratings.

Note: This is not an exhaustive list. Hospital and health system names were compiled from recent credit rating reports and are listed in alphabetical order.

1. Dallas-based Baylor Scott & White Health has an “Aa3” rating and stable outlook with Moody’s. The health system has strong cash flow margins, and its favorable demographics will contribute to volume and revenue growth, according to Moody’s.

2. Los Angeles-based Cedars-Sinai Medical Center has an “Aa3” rating and stable outlook with Moody’s. The hospital has strong margins, excellent balance sheet metrics and a strong reputation locally and nationally for patient care and research, according to Moody’s.

3. Orange, Calif.-based Children’s Hospital of Orange County has an “AA-” rating and stable outlook with Fitch. The hospital has a strong financial profile, and Fitch expects its capital-related ratios to improve.

4. Newark, Del.-based Christiana Care has an “Aa2” rating and stable outlook with Moody’s. The health system has solid margins and a robust balance sheet, according to Moody’s.

5. Fort Worth, Texas-based Cook Children’s Medical Center has an “Aa2” rating and stable outlook with Moody’s. The hospital has a strong market position and solid operating performance, according to Moody’s.

6. Durham, N.C.-based Duke University Health System has an “Aa2” rating and stable outlook with Moody’s. The health system is a leading provider of tertiary and quaternary services and has solid margins and cash levels, according to Moody’s.

7. Midland County (Texas) Hospital District has an “Aa3” rating and stable outlook with Moody’s. The district, which was created to operate a hospital in the county, has a manageable debt load, a modest pension liability and the ability to produce strong operating margins, according to Moody’s.

8. Chicago-based Northwestern Memorial HealthCare has an “Aa2” rating and stable outlook with Moody’s. Moody’s expects that the health system’s operating model and comprehensive IT systems will enable it to execute growth strategies while maintaining strong margins.

9. Winston-Salem, N.C.-based Novant Health has an “Aa3” rating and stable outlook with Moody’s. The credit rating agency expects Novant to continue generating strong cash flow margins in favorable markets.

10. Boston-based Partners HealthCare has an “Aa3” rating and stable outlook with Moody’s and an “AA-” rating and stable outlook with S&P. The health system has an excellent reputation in the clinical and research spaces, a long track record of fundraising, and adequate balance sheet measures, according to Moody’s.

11. St. Louis-based SSM Health Care has an “AA-” rating and stable outlook with Fitch. SSM has a strong financial profile, and Fitch expects the system to continue growing unrestricted liquidity and to maintain improved operational performance.

12. Appleton, Wis.-based ThedaCare has an “AA-” rating and stable outlook with Fitch. The health system has a leading market share in a stable service area and strong operating performance, according to Fitch.

13. Cincinnati-based TriHealth has an “AA-” rating and stable outlook with Fitch. Fitch expects the health system to maintain good operating ratios, leading to liquidity growth.

14. Yale New Haven (Conn.) Health has an “Aa3” rating and stable outlook with Moody’s. The health system has a leading market position in Connecticut, with a broad reach for tertiary and quaternary patients from throughout the state, and strong brand recognition, according to Moody’s.


Here’s How Microsoft Plans To Modernize Healthcare

http://fortune.com/2019/02/07/microsoft-healthcare-artificial-intelligence/

Image result for microsoft healthcare bot service

Microsoft announced its new service to help healthcare companies store patient data in the cloud and a Healthcare Bot service that will be integrated with Electronic Health Records.

The tool will be based on Microsoft’s Azure cloud platform, which it describes as a secure end-to-end platform that organizations can use to store and analyze sensitive data.

“Healthcare leaders are thinking about how they bring their data into the cloud while increasing opportunities to use and learn from that data,” Microsoft wrote in a blog.

With its new healthcare push, Microsoft aims to create a system that makes health records more easily accessible and sharable between clinicians, researchers, and patients, Bloomberg reports.The corporation also sees its integrated healthcare storage as a way to attract companies to Microsoft, over its competitor Amazon Web Services.

