Sniffles? Cancer? Under Medicare Plan, Payments for Office Visits Would Be Same for Both


Image result for Sniffles? Cancer? Under Medicare Plan, Payments for Office Visits Would Be Same for Both

The Trump administration is proposing huge changes in the way Medicare pays doctors for the most common of all medical services, the office visit, offering physicians basically the same amount, regardless of a patient’s condition or the complexity of the services provided.

Administration officials said the proposal would radically reduce paperwork burdens, freeing doctors to spend more time with patients. The government would pay one rate for new patients and another, lower rate for visits with established patients.

“Time spent on paperwork is time away from patients,” said Seema Verma, the administrator of the Centers for Medicare and Medicaid Services. She estimated that the change would save 51 hours of clinic time per doctor per year.

But critics say the proposal would underpay doctors who care for patients with the greatest medical needs and the most complicated ailments — and could discourage some physicians from taking Medicare patients. They also say it would increase the risk of erroneous and fraudulent payments because doctors would submit less information to document the services provided.

Medicare would pay the same amount for evaluating a patient with sniffles and a head cold and a patient with complicated Stage 4 metastatic breast cancer, said Ted Okon, the executive director of the Community Oncology Alliance, an advocacy group for cancer doctors and patients. He called that “simply crazy.”

Dr. Angus B. Worthing, a rheumatologist, said he understood the administration’s objective. “Doctors did not go to medical school to type on a computer all day,” he said.

But, he added: “This proposal is setting up a potential disaster. Doctors will be less likely to see Medicare patients and to go into our specialty. Patients with arthritis and osteoporosis may have to wait longer to see the right specialists.”

Private insurers often follow Medicare’s lead, so the proposed change has implications that go far beyond the Medicare program.

The proposal, part of Medicare’s physician fee schedule for 2019, is to be published Friday in the Federal Register, with an opportunity for public comment until Sept. 10. The new policies would apply to services provided to Medicare patients starting in January.

“We anticipate this to be a very, very significant and massive change, a welcome relief for providers across the nation,” Ms. Verma said, adding that it fulfills President Trump’s promise to “cut the red tape of regulation.”

“Evaluation and management services” are the foundation of an office visit. Medicare now recognizes five levels of office visits, with Level 5 involving the most comprehensive medical history and physical examination of a patient, and the most complex decision making by the doctor.

Level 1 is mostly for nonphysician services: for example, a five-minute visit with a nurse to check the blood pressure of a patient recently placed on a new medication.

A Level 5 visit could include a thorough hourlong evaluation of a patient with heart failure, chronic obstructive pulmonary disease, high blood pressure and diabetes with blood sugar out of control.

“The differences between Levels 2 to 5 are often really difficult to discern and time-consuming to document,” said Dr. Kate Goodrich, Medicare’s chief medical officer.

Medicare payment rates for new patients now range from $76 for a Level 2 office visit to $211 for a Level 5 visit. The Trump administration proposal would establish a single new rate of about $135. That could mean gains for doctors who specialize in routine care, but a huge hit for those who deal mainly with complicated patients, such as rheumatologists and oncologists.

For established patients, the proposal calls for a payment rate of about $93, in place of current rates ranging from $45 to $148 for the four different levels of office visits.

“This proposal is likely to penalize physicians who treat sicker patients, even though they spend more time and effort and more resources managing those patients,” said Deborah J. Grider, who has audited tens of thousands of medical records and written a book on the subject.

Dr. Atul Grover, the executive vice president of the Association of American Medical Colleges, said, “The single payment rate may not reflect the resources needed to treat patients we see at academic medical centers — the most vulnerable patients, those who have complex medical needs.”

While the proposal would redistribute money among doctors, it is not intended to cut spending under Medicare’s physician fee schedule, which totals roughly $70 billion a year.

If the new rules really do simplify their work, doctors say, they will be elated.

“We can focus more on patient care and less on the administrative burden of documentation and billing,” said Dr. David B. Glasser, an assistant professor of ophthalmology at the Johns Hopkins University School of Medicine. “We sometimes joke that it can be more complicated trying to get the coding level right than it is to figure out what’s wrong with the patient.”

But, Dr. Glasser said, the financial impact of the proposal on eye doctors is not yet clear.

Documentation requirements have increased in response to growing concerns about health care fraud and improper payments that cost Medicare billions of dollars a year.

In many cases, federal auditors could not determine whether services were actually provided or were medically necessary. In some cases, they found that doctors had billed Medicare — and patients — for more costly services than they actually performed.

In a report required by federal law, officials estimated early this year that 18 percent of Medicare payments for office visits with new patients were incorrect or improper, about three times the error rate for established patients.

To prevent fraud and abuse, Medicare officials have repeatedly told doctors to document their claims. “If it is not documented, it has not been done” — that is the principle set forth in Medicare’s billing manual for doctors.

The Trump administration is moving away from that policy.

“We have proposed to move to a system with minimal documentation requirements for Levels 2 to 5 and one single payment rate,” Dr. Goodrich said.

Doctors now must provide more documentation for higher levels of care. Under the proposal, “practitioners would only need to meet documentation requirements currently associated with a Level 2 visit.” That would reduce the need for audits to verify the level of office visits.

Medicare officials acknowledged that doctors who typically bill at Levels 4 and 5 could see financial losses under the proposal. But they said some of the losses could potentially be offset by “add-on payments” for primary care doctors and certain other medical specialists.

With such adjustments, Medicare officials said, the impact on most doctors would be relatively modest. A table included in the proposed rule indicates that obstetricians and gynecologists would gain the most, while dermatologists, rheumatologists and podiatrists would lose the most.


Private equity’s next health care target

https://www.axios.com/private-equity-firm-apollo-buying-lifepoint-health-1532121720-9e9a07eb-3090-4da3-9183-48144da93695.html?utm_source=newsletter&utm_medium=email&utm_campaign=newsletter_axiosvitals&stream=top

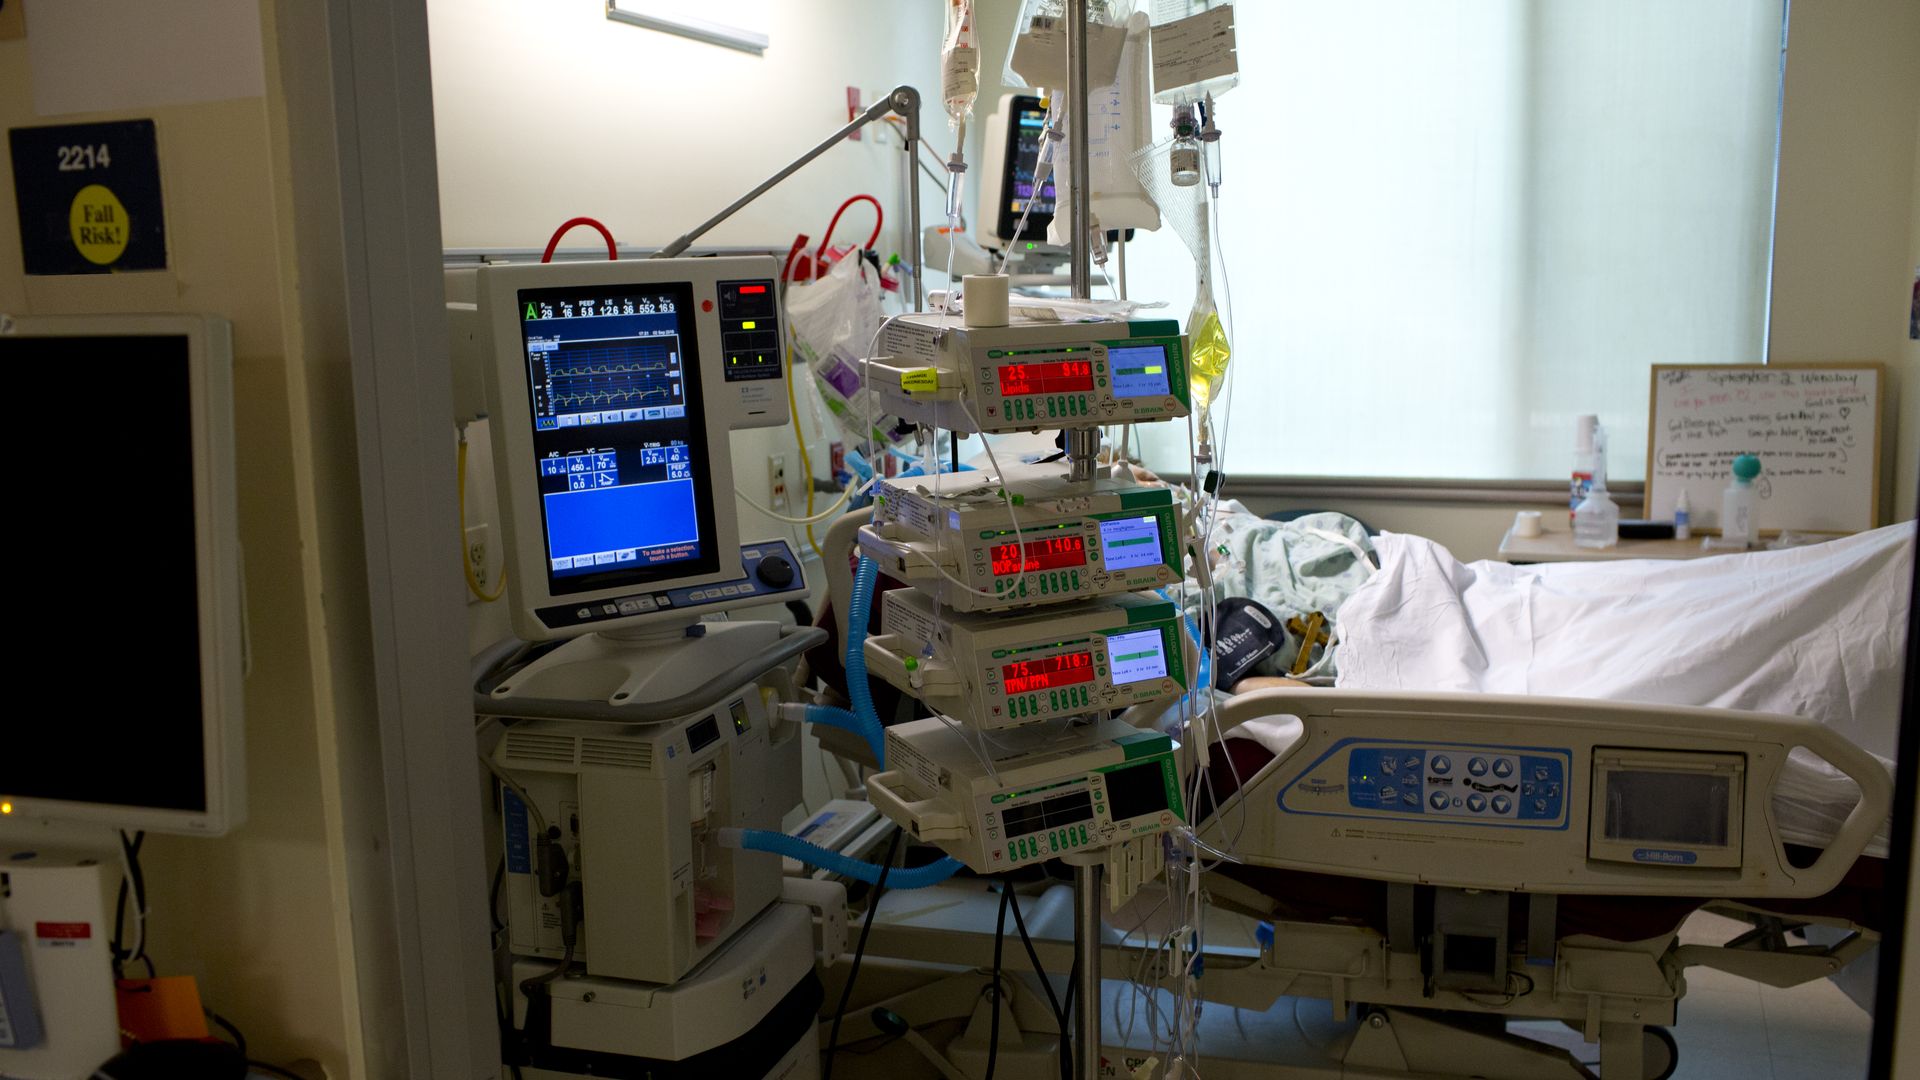
A patient sits in a hospital bed with machines nearby.

LifePoint Health owns hospitals in mostly rural areas.

For-profit hospital system LifePoint Health is nearing a deal to sell itself to private equity firm Apollo Global Management for $6 billion, including debt, Reuters reports. Apollo acquired a separate hospital chain — RegionalCare Hospital Partners, which is now known as RCCH HealthCare Partners — in 2015.

Why it matters: Private equity is craving health care deals right now, and this buyout would further consolidate the hospital industry, which is attempting to turn around a pattern of stagnant admissions.

Reuters reported Friday that private equity firm Apollo Global Management was considering buying LifePoint Health in a deal valued at $6 billion, which included debt. Axios’ Bob Herman breaks down the proposed deal…

Thought bubble, per Bob: Private equity has its hands all over the health care industry these days. But it’s a little surprising to hear such a large price tag for a company that owns mostly rural hospitals, which have struggled with fewer admissions and have relied more on the lower-paying Medicare and Medicaid programs.

The bottom line: Gary Taylor, an analyst with J.P. Morgan Securities, wrote this to hospital investors over the weekend, “We certainly do not expect another superior offer for a low-growth, challenged rural hospital company.”

Medicare option is popular but vague among Democrats

https://www.axios.com/democrats-single-payer-public-option-health-care-1532047129-3b97bb26-f2ff-407a-af5b-6821981b6e45.html

A public health care plan — once deemed too liberal to make it into the Affordable Care Act — is now the more moderate position for many Democrats who are uncomfortable with the party’s rapid embrace of “Medicare for All.”

Yes, but: Democrats haven’t decided yet what a public option should look like.

Show less
“In some ways, a public option or buy in to Medicare or Medicaid has become a place for Democrats uncomfortable with single payer to land.”
— Larry Levitt, Kaiser Family Foundation

Driving the news: Members of Congress have now introduced as many as five bills expanding government involvement in health care, as Vox has reported. A public option is also coming up frequently on the campaign trail, either as a step toward “Medicare for All” or as a policy goal in and of itself.

  • In Iowa’s third district, which is rated as a toss-up, Democrat Cindy Axne is running on a public option “that allows Americans to choose between Medicare or Medicaid.”
  • In New Jersey’s third district, another toss-up, Democrat Tom Malinowski supports creating a universal Medicare option that people could buy into.
  • “I think the much more plausible path to a single payer health care system is through a public option. I just don’t know that the country is ready to support a bill that outlaws private insurance,” said Sen. Chris Murphy, a sponsor of one of the public option plans.

Flashback: A public option for the individual market was almost included in the Affordable Care Act, but former Sen. Joe Lieberman blocked it.

  • “It was too liberal for Joe Lieberman” — not for the entire party — back in 2009, Democratic Minority Whip Dick Durbin told me. “We had 60 votes and he said he wouldn’t vote for it. That was the end of that.”
  • “You may have more people today supporting single payer, Medicare for All than 10 years ago, but I’m not sure that the floor has moved as much as the ceiling has,” Murphy said.

The big question: Some Democrats want a public option to be offered in the employer market in addition to the individual market.

  • “Now, a public option for just the individual market would likely be unsatisfying to single payer supporters, providing no relief from health care costs for the much larger number of people with employer coverage,” Levitt said.

The details: A central tenet of adopting a public option is using the government’s purchasing power to bring down underlying health care prices.

  • “The common denominator of all Democrats is that they want more affordable options for people, and how broadly you apply to tool depends on how broadly you define the problem right now,” said Chris Jennings, a Democratic health care consultant.
  • “Lurking behind the public option discussion is really the issue of health care prices. A public option of any kind would use the leverage and regulatory power of the government to get lower prices for health care,” Levitt said.
  • But determining how far to go would be tricky and comes with risk.
  • “There is some room to put some downward pressure on provider prices without having significant adverse consequences on access to care or quality of care, but the big question is how much,” said Aviva Aron-Dine of the left-leaning Center on Budget and Policy Priorities.


“The Inevitable Math behind Entitlement Reform”

“The Inevitable Math behind Entitlement Reform”

Image result for Entitlement Reform


That’s the title of a new NEJM Perspective by Michael Chernew and me. After crunching the numbers, our argument is that for long term cost control we will probably need to address growth in per capita health care utilization. The easy “solutions” won’t be enough.

Much of the projected increase in inflation-adjusted spending on health care entitlements, particularly for Medicare, stems from assumed increases in utilization (e.g., 2.75 percentage points of the 5.33% annual projected growth for Medicare spending). Strategies for holding utilization growth below projections (and more in line with very recent historical growth) will thus be central to the success of any attempt at cost containment.

[One approach] is to dissuade patients from seeking care by charging them more at the point of service. About 85% of Medicare beneficiaries have supplemental plans (e.g., Medigap) that reduce their out-of-pocket costs. Policies that limit the generosity of such plans could reduce Medicare spending considerably. However, such strategies would increase beneficiaries’ financial risks, reduce access to care, and probably exacerbate health disparities.

A second strategy is to help beneficiaries improve their health by enhancing long-term care management and preventive services with the goal of avoiding more expensive services. Evidence suggests that although this type of approach is probably beneficial to patients and may be cost-effective, it is generally not cost saving.

The piece continues with some more promising approaches, in our view. Click to read it in full (unfortunately pay-walled though).
