The Democrats Already Have a Healthcare Playbook for 2029

As the midterm elections approach, politicians are debating healthcare within the broader context of “affordability,” or, more precisely, the challenge voters say they are facing in paying their regular bills. An interesting battle within the Democratic Party is underway over the appropriate response to this concern, with some favoring Medicare for All and others voicing skepticism about that approach.

Leading congressional Democrats, including Sen. Ron Wyden of the Finance Committee, are hedging their bets, but the most likely scenario is still one of incrementalism rather than sweeping reform.

Medicare for All has always been more effective as a rallying cry for the Democratic Party than as a roadmap for getting a bill through Congress. Although many voters are exasperated with the state of American healthcare, support for Medicare for All falls when its costs, which are considerable, are made clear to survey respondents. There is also a broad lack of confidence in the government’s ability to competently manage healthcare insurance for the entire country.

A potential guide for what Democrats might do in lieu of Medicare for All can be found in a document posted in July by Wyden on behalf of many of his Senate colleagues. It lists scores of ideas for reforming healthcare insurance and care delivery, including through the possible adoption of Medicare for All, although the balance of the paper points toward more public control and regulation than a major push for a monolithic public plan.

Wyden is following the playbook Democrats used to successfully advance the Affordable Care Act (ACA) from 2008 to 2010. In the months leading up to the 2008 election, then-Senate Finance Committee Chairman Max Baucus had worked with outside experts and fellow Democrats to draft a white paper on healthcare, which he released just days after then-Sen. Barack Obama won the presidency. That document would serve as the blueprint for the bill Baucus would draft and pass in the Senate in 2009, which later became the foundational ACA law.

Many healthcare concepts that are now familiar because of their inclusion in the ACA were promoted in the Baucus white paper, including the individual mandate, new premium subsidies for non-employer coverage for individuals with incomes below 400 percent of the federal poverty line, a large Medicaid expansion, and accountable care organizations, which are provider-led—as opposed to insurer-owned—managed care plans.

Wyden is explicit in his July release that he views the development work conducted by Baucus before 2009 as a model for what he hopes to accomplish in the run-up to 2029. However, he framed the ideas presented in the July release not as proposals he supports but as ideas for which he is soliciting feedback (responses to his “request for information” are due by October 2). It is possible, depending on what occurs in November 2028, that Wyden will publish a more prescriptive plan after the election to signal more clearly his intentions for 2029.

Wyden’s document zeroes in on consumer dissatisfaction with aspects of private insurance and divides the ideas under review into three categories: lowering costs for consumers and making enrolling in insurance easier, removing barriers to accessing care and lowering administrative costs, and regulating the for-profit companies providing insurance and care to patients.

Some of the more noteworthy concepts included in the document include:

  • reversing most of the budget cuts and regulatory changes implemented during the second Trump administration
  • developing transition plans that might allow Medicare for All to be approved with less immediate disruption to the current coverage of many Americans
  • creating an option for states to offer single-payer coverage
  • creating a nationwide “public option,” sponsored and run by the federal government, that would be offered to consumers buying individual coverage through the exchanges established by ACA and which might use Medicare’s regulations to set reimbursement rates for services or allow the government to negotiate rates with the providers of services in each market
  • developing new Medicare or Medicaid “buy-in” options that could be offered to all Americans regardless of their employment status and incomes
  • creating a single online entry point for enrolling in coverage that both those getting employer-sponsored and non-group coverage could use
  • allowing states to add to essential health benefits based on emerging evidence of effective services
  • stricter state oversight over premium increases requested by insurance plans, potentially including caps
  • eliminating deductibles and coinsurance for some “non-shoppable” services, and applying lower limits on total annual out-of-pocket costs based on a person’s income
  • reinstating the enhanced premium credits in place from 2021 to 2025 that the GOP Congress allowed to expire
  • allowing the ACA premium credits to go to lower-income workers enrolled in employer coverage, which the current “firewall” prohibits and which might be provided irrespective of the share of the premium paid by workers, and
  • restricting the business practices of for-profit companies participating in the healthcare industry, including insurance companies, private equity investors, and other “middlemen”

The connecting theme behind these ideas is a publicly regulated system, with the government taking on the responsibility of providing affordable coverage options for all Americans, with cost-sharing that is capped relative to household income. Wyden and other Democrats are willing to consider all manner of new controls and subsidies to ensure these objectives are achieved, but it is of course easier to promise these outcomes than to deliver them. An especially formidable obstacle is likely to be the service providers who believe Medicare and Medicaid’s payment rates are too low to serve as guides for private coverage too. Cutting payments to all providers is easier than designing reforms that more precisely target waste and inefficiency, but the ability of Democrats to overcome industry opposition to payment reductions in 2029, as they did when writing the ACA, is not assured.

In addition, even with some provider cuts, the aggregate federal cost of a plan that includes some of the more prominent ideas in the Wyden plan (not including Medicare for All), could be significant. For instance, the Congressional Budget Office has estimated that rolling back policies that tightened administration of the ACA credits, along with reinstating on a permanent basis the enhancement of the credits originally approved in 2021, would increase projected federal budget deficits by $662 billion over 10 years. Democrats are certain to favor tax hikes on well-to-do Americans in 2028, but it is not yet clear that those potential sources of new revenue would be sufficient to fully offset the most expensive ideas the Wyden document teases.

The heavy investment Senate Democrats are making in the development of their 2029 agenda for healthcare contrasts with the GOP’s approach, which is less focused. The Trump administration released a one-page framework earlier this year (“The Great Healthcare Plan”), but there has been little follow-up and no visible movement among congressional Republicans to approve new legislation.

Republicans should take the Wyden document seriously. If voters opt once again for change in 2028 rather than continuity, it is near certain Democrats will use the power voters granted them to prioritize passage of a major healthcare bill. The GOP could make that scenario less likely to occur if it developed, promoted, and tried to advance an alternative approach. There are multiple sound ideas they could embrace to make healthcare more affordable without excessive reliance on public regulation, such as by allowing consumers to keep the savings when they choose lower-cost insurance and care providers. Refining those ideas and putting them into legislation would put the party in a better position to compete with what is coming from their opponents in both 2026 and 2028.


Rising Employer-Sponsored Insurance Premiums Will Add to the Pressure for Reform

The consultants agree: Healthcare premiums in 2027 for employer-sponsored insurance (ESI) are going up once again at an exceptionally elevated rate. As has been the case in all the years since the COVID-19 pandemic ended, the forces driving costs higher are overwhelming those working in the other direction. The added pressure from yet another year of significant premium hikes is likely to further intensify voter interest in a political response.

As employers get set to administer their open enrollment seasons for 2027 workplace benefit programs, a consensus has emerged among the outside firms monitoring trends in this sector that ESI is going through a sustained period of unusually rapid cost growth.

  • WTW (rebranded from Willis Towers Watson) projects that total costs for ESI will rise by 11.1 percent in 2027, which the firm says is the highest annual rate increase it has observed in two decades.
  • Aon forecasts a 9.5 percent increase for 2027, which would come on top of an 8.3 percent jump in 2026.
  • Marsh (previously Mercer) expects a modestly slower growth rate in 2027 of 8.2 percent after taking into account coverage adjustments, such as higher deductibles. The firm says the 2027 increase comes after a 6.7 percent rise in 2026 and 6.0 percent in 2025.
  • PricewaterhouseCoopers (PwC) predicts a 9.0 percent increase in covered medical expenses, on average, for ESI plans in 2027, which is the same rate it found for 2026 and slightly above the 8.5 percent rate it observed in 2025.

The PwC report points to multiple sources for ESI cost growth above general consumer inflation:

  • New AI Tools. Hospitals and physician groups are using artificial intelligence (AI) to maximize what they get paid for every interaction they have with patients. Insurers also have new AI platforms to better identify opportunities for cutting costs, but, to date, the provider-focused products are having more of an effect on total costs.
  • Provider Consolidation. Employers continue to struggle to hold down payment demands made by dominant health systems. With the industry already heavily consolidated, insurers have limited options to work around the major players.
  • Pharmaceutical Spending. Price increases for specialty therapies and expanded use of GLP-1s are pushing up drug costs.
  • Behavioral Health. Utilization of covered mental health services remains on a steep upward trajectory, with cumulative growth of 62 percent over the six-year period 2018 to 2024.
  • The Unintended Fallout from the No Surprises Act (NSA). Congress approved the NSA assuming it would lower overall costs for consumers, but it has had the opposite effect because physicians keep winning in arbitration. The added costs have grown to the point that they are noticeable in ESI premiums.

With cost pressures building, one might expect big employers to become more assertive in pushing for lower costs, yet WTW found continued reluctance among employers to take on the healthcare sector. In its survey, only 15 percent of the firms responding said they would be willing to back disruptive changes to secure a 5 percentage point drop in premiums. Further, 61 percent said they preferred to avoid upsetting their employees to securing meaningful cost reductions from disruptive ESI changes.

These findings confirm that the ESI market suffers from a collective action problem. Firms offering healthcare coverage want to attract the best workers possible within the budgets they allocate to labor costs. They do not want to develop reputations for offering less generous ESI than their competitors. Moreover, individual firms generally do not wield sufficient market power to change the business practices of major health systems.

The inability of employers to solve this problem on their own is certain to increase the pressure on Congress to provide a fix through legislation. In the coming years, many policymakers could get behind some version of additional rate setting in the ESI market to put a lid on premium growth.

Elected officials who might be wary of such remedies need to consider what they would offer as an alternative.

One option would be to force firms with ESI to run something like a premium support plan. Workers would get fixed levels of subsidization from their employers, which they would then apply to the plans they prefer rather than to the plans their companies choose on their behalf. The offered plans would need to be standardized (to a degree) to allow for apples-to-apples premium comparisons. This design would move responsibility from the firms to the workers to make economizing choices, with a strong likelihood of producing better results. Many employees might gladly accept coverage with market-disrupting changes if doing so would increase their take-home pay.

340B Rebate Fight Puts Hospital Cash Flow on the Line

https://www.healthleadersmedia.com/cfo/340b-rebate-fight-puts-hospital-cash-flow-line

A new lawsuit from the American Hospital Association and four safety-net hospitals challenges a proposed federal drug rebate model, raising fresh concerns about liquidity, administrative spending and the financial stability of providers.


KEY TAKEAWAYS

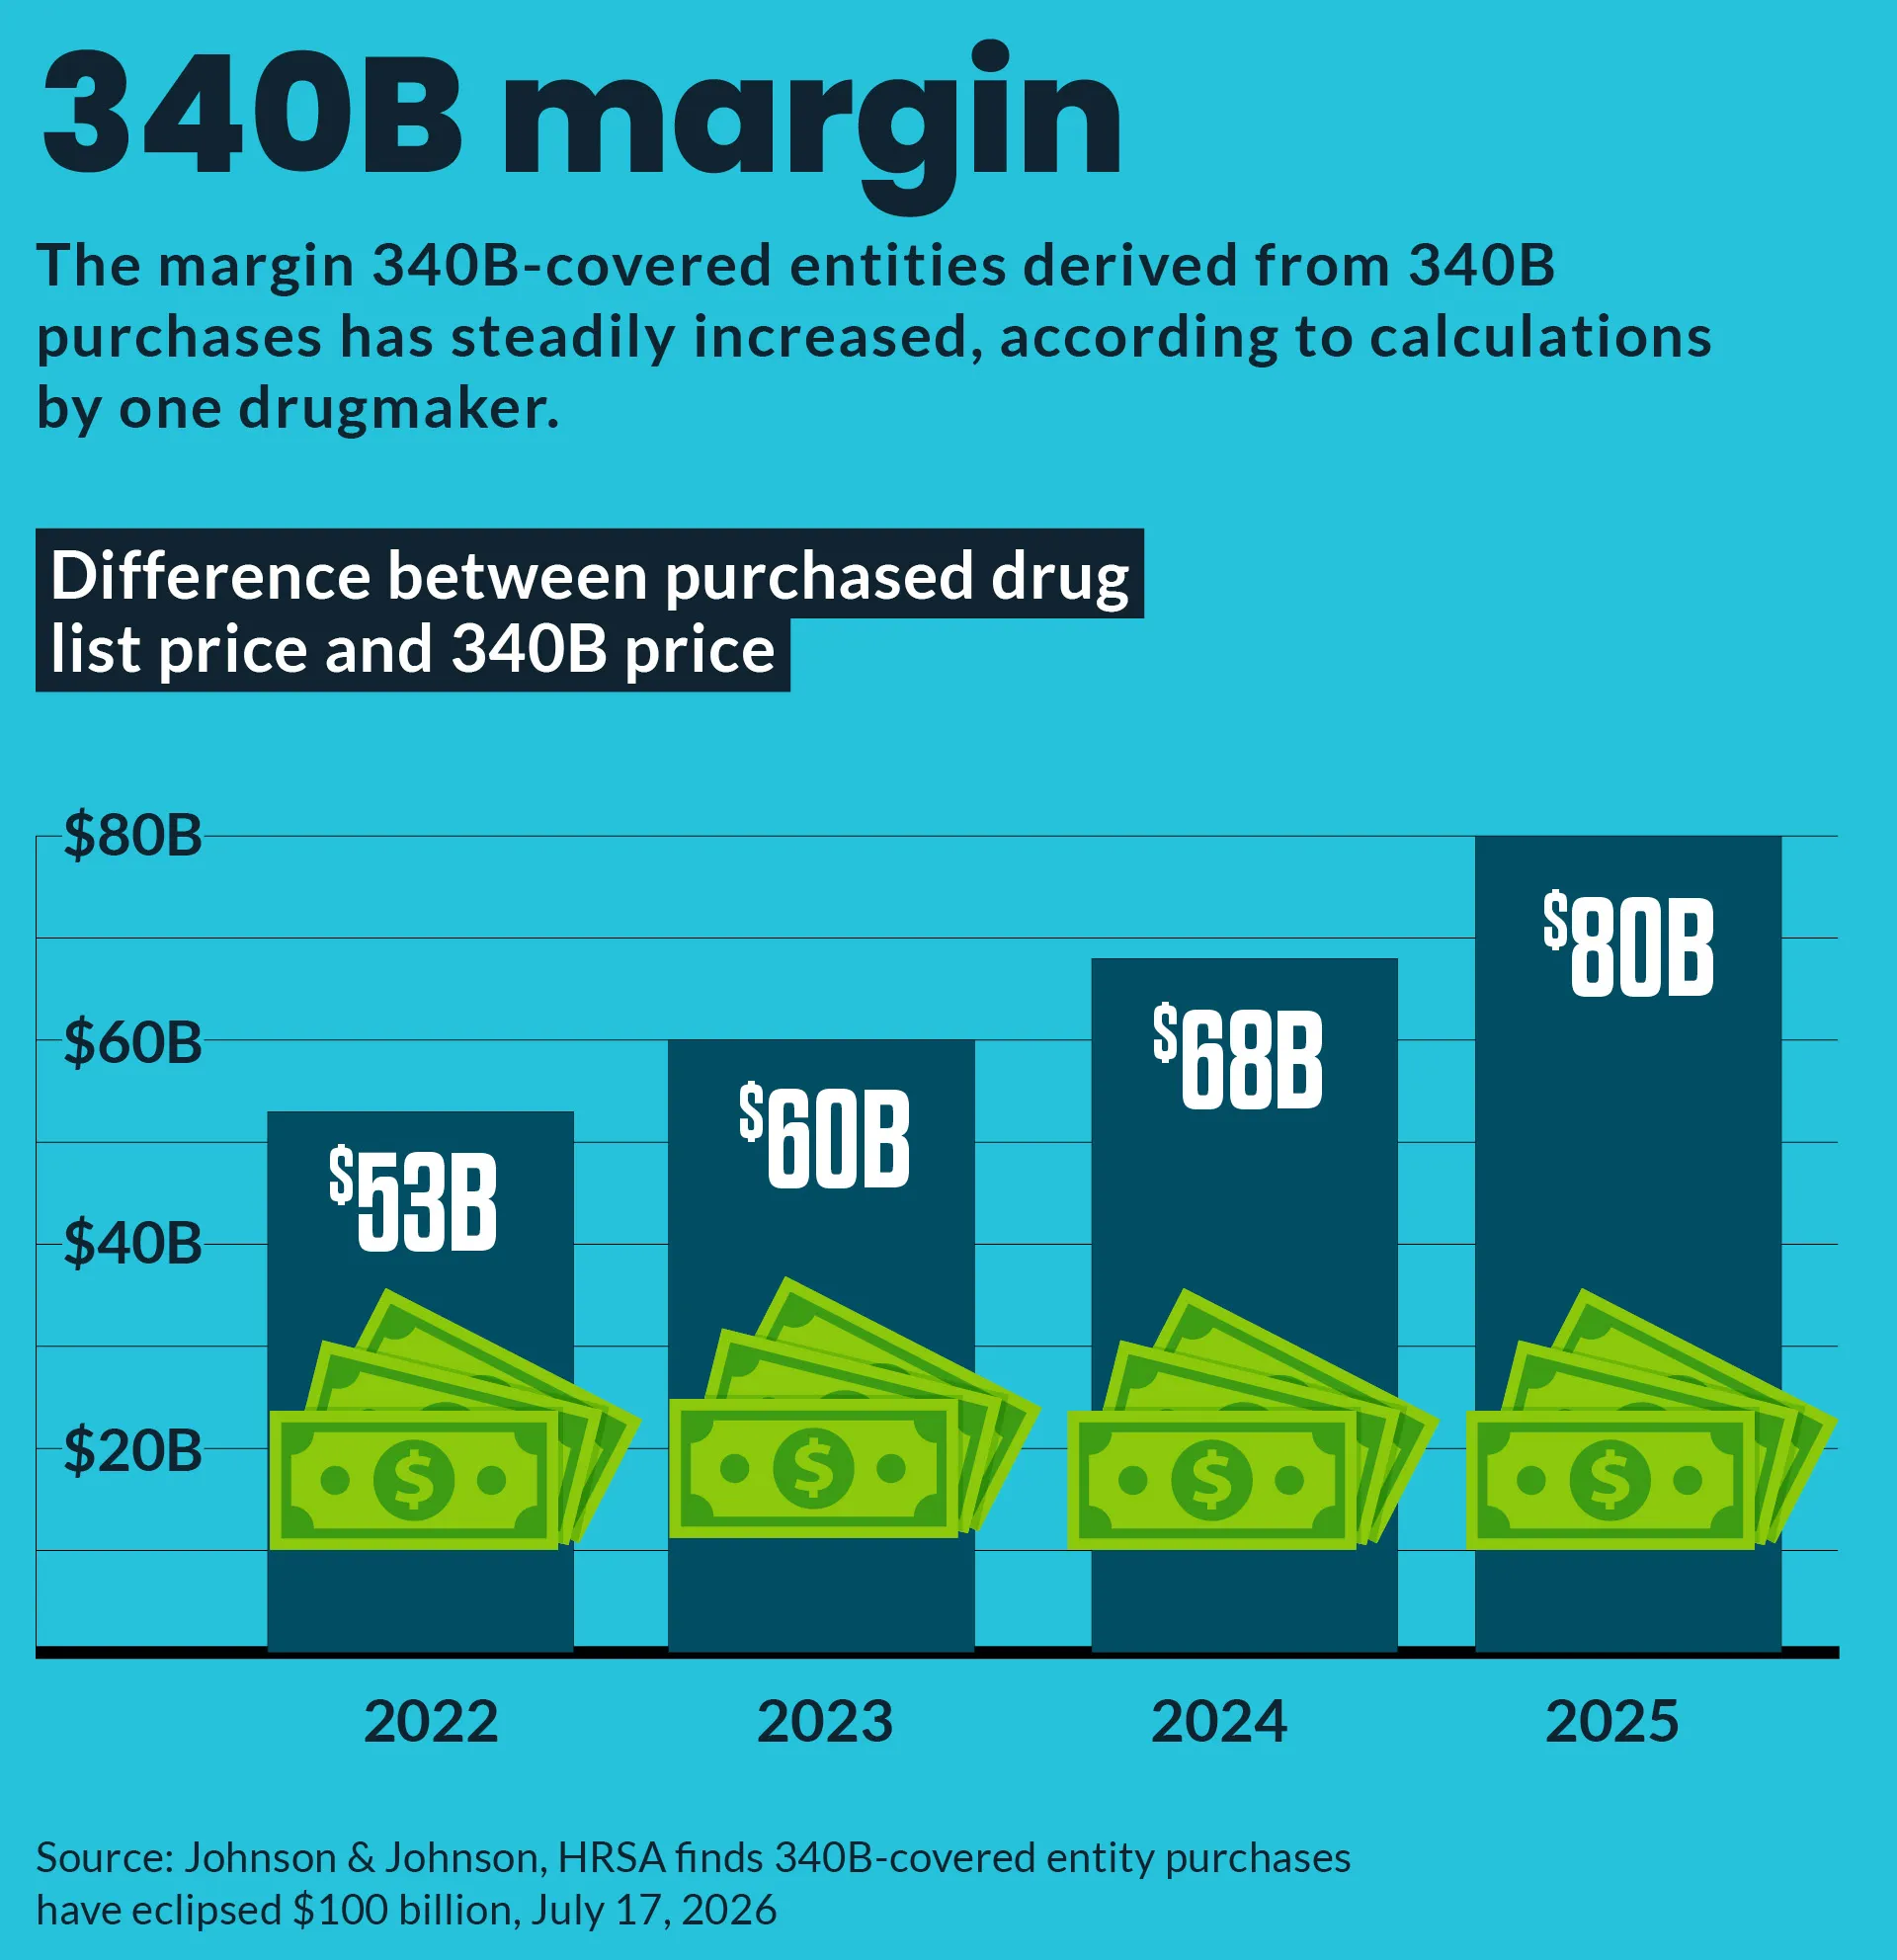
Hospitals would pay wholesale prices for certain drugs upfront and seek 340B discounts through rebates.

Hospital groups estimate annual administrative expenses could exceed $1 billion, nearly double the federal government’s estimate of approximately $537 million.

The revised pilot is scheduled to begin January 1, 2027, but a new legal challenge could disrupt implementation.

The financial stakes of the federal 340B Drug Pricing Program are back in court. The American Hospital Association (AHA), the Maine Hospital Association and four safety-net hospitals filed a federal lawsuit October 9 seeking to block a revised rebate pilot that could change how participating providers obtain discounts on certain outpatient drugs.

The plaintiffs also requested a temporary restraining order to prevent the program from taking effect January 1, 2027. They argue that the Department of Health and Human Services (HHS) and the Health Resources and Services Administration (HRSA) failed to adequately assess the program’s financial consequences and consider less burdensome alternatives.


Under the current 340B model, eligible hospitals generally purchase covered outpatient medications at discounted prices. The revised pilot would instead require providers to buy participating drugs at wholesale acquisition cost, submit claims data and receive rebates for the difference between that price and the 340B ceiling price.

That change could create a significant working-capital challenge. Hospitals would have to front more money for medications and wait for rebates, while also managing claims submissions, payment reconciliation, potential denials and additional compliance work.

The cost estimates are the real disagreement. Hospital analyses cited by the AHA put annual administrative expenses above $1 billion, compared with the federal government’s estimate of roughly $537 million. The hospital groups contend that the government failed to fully account for startup costs, staff training, vendor expenses and the financial burden of advancing funds for drug purchases.

For hospitals operating on narrow margins, those expenses could have consequences well beyond the pharmacy department. Maine Hospital Association President Jeff Austin has said hospitals in the state average less than two weeks of cash on hand, underscoring how quickly additional working-capital demands could become a liquidity concern.

The HRSA, meanwhile, says the rebate model would improve transparency and program integrity by allowing individual transactions to be verified before rebates are paid. The agency also says the approach would help prevent overlapping discounts under 340B and the Medicare Drug Price Negotiation Program. The pilot is voluntary for manufacturers, and HRSA has approved plans from 10 manufacturers covering 18 drugs for the planned January launch, according to the lawsuit.

What CFOs should be watching

A shift from upfront discounts to retrospective rebates could increase cash-conversion-cycle pressure, require new investments in revenue-cycle and pharmacy systems, and expose hospitals to reconciliation delays. CFOs should therefore model potential cash requirements, assess vendor and staffing needs, and coordinate with pharmacy, compliance and legal teams rather than waiting for the litigation to conclude.

If the plaintiffs’ cost projections prove accurate, hospitals may have to redirect funds from patient assistance, specialty services and other community programs to cover administrative overhead and drug purchases. Smaller rural providers could be especially vulnerable because they have fewer reserves to absorb delays.

This is not the first legal challenge to the rebate approach. A federal judge temporarily blocked the original pilot in December 2025, and HHS later withdrew that version. HRSA announced the revised program in August 2026, but the latest lawsuit puts its planned launch back in question.

For now, CFOs should treat January 2027 as a planning deadline, not a settled outcome. The ultimate decision could shape how hospitals manage drug costs, liquidity and 340B-funded services for years to come.

Hospital Finance: Things to Know

Hospital and health system margins are beginning to reveal two different realities as a growing number of hospitals lose money and cut costs while the strongest add services, shed what doesn’t fit and post gains.

The gap shows struggling facilities like Watsonville (Calif.) Community Hospital that are down to just eight days of cash on hand, while systems like Durham, N.C.-based Duke University Health System reported an operating income of $453.1 million (5.4% margin) in fiscal year 2026, up from an operating income of $179 million (2.5% margin) in fiscal 2025.

Here are the numbers and moves defining the hospital finance divide as hospitals head into 2027.

THE NATIONAL PICTURE

1. More hospitals are losing money. A Kaufman Hall “National Hospital Flash Report” from Oct. 13 found that 43% of hospitals are operating in the red, up from 33% prior to the COVID-19 pandemic. The report pulled from August 2026 financial performance data from 1,300 hospitals.

2. Margins slid through the summer. The average hospital margin fell to 1.8% in August, down from 3.8% in July and 5.6% in June.

3. Geography matters. In August, hospital margins were down 2 percentage points compared with the same month in 2025. Margins rose 5% year over year in the Northeast/Mid-Atlantic but fell 18% in the Great Plains.

4. Revenue is up, but costs and bad debt are increasing faster. Operating revenue per day increased 6% year over year in August. Total expenses have increased 21% over the last three years, with drug expenses up 29%, supply expenses up 25% and labor expenses up 16%. Bad debt and charity care per calendar day increased 13% year over year and 49% over the last three years.

SYSTEMS PULLING AHEARD

5. For-profits remain ahead. Nashville, Tenn.-based HCA Healthcare, which is scheduled to report its third-quarter results Oct. 27, reported a net income of $1.7 billion (8.4% margin) in the second quarter of 2026, roughly flat compared with $1.7 billion (8.9% margin) in the second quarter last year. HCA, Dallas-based Tenet Healthcare and King of Prussia, Pa.-based Universal Health Services have also outpaced the broader market since June 30, even as they split their outlooks for the rest of the year.

6. Certain nonprofits are posting big margin gains. Duke Health’s operating margin for fiscal 2026 was 5.4%, compared with an operating margin of 2.5% for fiscal 2025. Livonia, Mich.-based Trinity Health also saw $281 million in operating income (1.1% margin) in fiscal 2026, up from a $12.2 million operating loss (0% margin) in fiscal 2025.

7. Turnarounds are working. West Reading, Pa.-based Tower Health achieved a positive operating income for the first time in nearly a decade. President and CEO Michael Stern told Becker’s the system is shifting from stabilization toward strategic investment and sustainable growth. St. Louis-based Ascension also completed a $3 billion turnaround in three years, with the system reporting a $120 million operating loss (-0.2% margin) in fiscal 2026, a $371 million improvement from the prior year.

8. System investments reach beyond hospitals. Phoenix-based Banner Health has bet on ASCs and insurance to grow. In 2018, the system entered a joint venture partnership with Phoenix-based Atlas Healthcare Partners to build and operate a network of ASCs in Arizona, Colorado and Wyoming. Additionally, just under 20% of Banner’s total revenue comes from insurance premiums, with its long-term financial strategy including an increase in that share. Ascension also just wrapped its $3.9 billion acquisition of AmSurg in June, growing its ASC footprint from 58 centers to more than 300 across 34 states.

THE HOSPITALS FALLING BEHIND

9. Cash is the strongest divider. An Aug. 13 Moody’s Ratings report found that median days cash on hand was 280 for Aa-rated nonprofit systems, 191 for A-rated systems, 117 for Baa-rated systems and 71 for systems rated below Baa.

10. Some hospitals are down to days, not months, of cash. Watsonville Community Hospital faces “a serious financial gap” with just eight days of cash on hand. Its interim CEO Tim Moran warned the hospital could close within six to 12 months without action.

11. Downgrades are piling up. Becker’s has tracked 19 health system rating downgrades in its latest roundup. Most recently, Ashtabula, Ohio-based ACMC Healthcare System’s credit rating was downgraded to “BBB” from “BBB+” by Fitch. The downgrade reflected deterioration in the system’s liquidity since fiscal 2023.

12. Federal scrutiny has added pressure. An Oct. 8 inspection report obtained by Becker’s found Central Maine Medical Center in Lewiston is at risk of losing Medicare funding after CMS found it out of compliance with three of the program’s conditions of participation.

13. Rural hospital exposure remains high. More than 40% of rural hospitals operate at a loss, according to an Oct. 13 AHA report. Becker’s has reported on just six planned hospital and emergency department closures in 2026, but at this point in 2025, Becker’s had already reported on 22. While this may be viewed positively, many healthcare leaders feel the financial strain hasn’t eased and is showing up in areas like service line cuts and rural emergency hospital conversions and consolidations.

HOW SYSTEMS ARE RESPONDING

14. Workforce cuts aren’t slowing down. Becker’s has reported on 68 hospitals and health systems that have announced job cuts in 2026. In recent months, four systems have also cut corporate and administrative support roles while protecting positions focused on patient care.

15. Portfolios are being reshaped. Many large systems are divesting assets, exiting joint ventures and calling off deals. At the same time, hospital and health system mergers and acquisitions in 2026 have already surpassed 2025 numbers, and are set to see their busiest year since the pandemic. Since 2020, at least 23 health systems have formed or taken new identities through mergers, new launches or rebrands.