





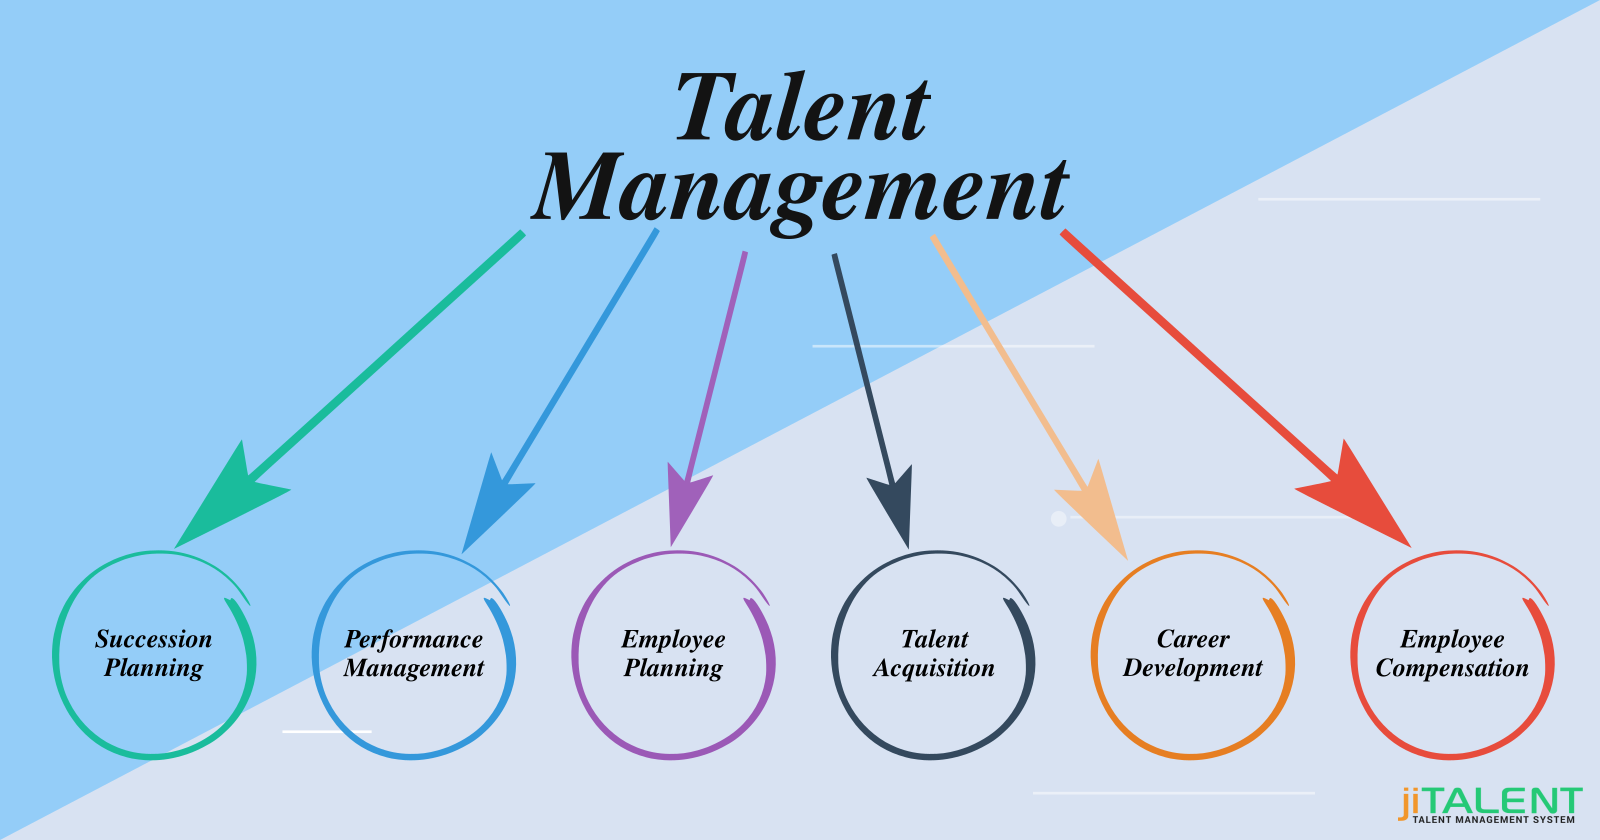
“Talent management deserves as much focus as financial capital management in corporations.”
~ Jack Welch
One of the best ways to strengthen your company as a whole is to devote attention to developing your employee talent. If your staff isn’t given the proper encouragement or assistance needed to help them move forward within your company, it can be more challenging for the company itself to continue growing in its capabilities. There are several ways that you, as a leader, can help to develop the talent at your company. Talent identification and management begin with The Four P’s.
For instance, if one of their goals is to expand their understanding of the daily responsibilities of your company’s executive team, create an opportunity for them to shadow you or another company leader so they can gain insight into whether an executive career path could be a good fit for them. The more your employees are able to broaden their comprehension of your company’s functionality beyond their own duties, the greater the likelihood that they’ll be able to develop into well-informed and well-rounded contributors.
https://apnews.com/1c5c5dc43950421a9ab4ff7edb9fe678?omnicid=CFC1688174&mid=henrykotula@yahoo.com

Major legislation to reduce prescription drug costs for millions of people may get sidelined now that House Democrats have begun an impeachment inquiry of President Donald Trump. Proposals had been moving in Congress, but there are more ways for the process to break down than to succeed. Still, nobody says they’re giving up.
Some questions and answers about the legislation and its uncertain prospects:
Q: Why, now, is there a big push to lower drug prices?
A: Some would say it’s overdue. Drug prices emerged as the public’s top health care concern near the end of the Obama administration as people with health insurance got increasingly worried about their costs.
In the 2016 campaign, Trump and Democrat Hillary Clinton called for authorizing Medicare to negotiate prices. But after Trump won the White House, his focus shifted to the failed Republican drive to repeal the Affordable Care Act. A year went by before the administration reengaged on prescription drugs .
Now, facing the 2020 election, Trump and lawmakers of both parties in Congress have little to show for all their rhetoric about high drug prices. For there to be a deal , enough Democrats and Republicans have to decide they’re better off delivering results instead of election-year talking points.
Q: What are the major plans on the table?
A: On the political left is House Speaker Nancy Pelosi’s plan authorizing Medicare to negotiate prices for the costliest drugs. In the middle is bipartisan legislation from Sens. Chuck Grassley, R-Iowa, and Ron Wyden, D-Ore., to restrain drug price increases. The wild card is Trump. He doesn’t share the traditional Republican aversion to government as price negotiator and keeps complaining that it’s unfair for Americans to pay more than patients in other countries.
There’s significant overlap among the major approaches.
Trump, the Senate bill, and Pelosi would all limit what Medicare enrollees pay annually in prescription copays. That would be a major change benefiting more than 1 million seniors with high costs.
Pelosi and the Senate bill would require drugmakers to pay rebates if they raise their prices to Medicare beyond the inflation rate. Long-available medicines like insulin have seen steep price hikes.
Pelosi and the administration would use lower international prices to determine what Medicare pays for at least some drugs. Pelosi is echoing Trump’s complaint that prices are unfair for Americans.
“If they wanted to do a deal, it’s sitting right there in front of them,” said John Rother, president of the National Coalition on Health Care, an umbrella group representing a cross-section of organizations.
Q: How would any of these plans reduce what I pay for prescription drugs?
A: Under Pelosi’s bill, private purchasers such as health insurers and employer-sponsored plans would be able to get the same price that Medicare negotiates. Medicare would focus on the costliest medications for individual patients and the health care system as whole.
People on Medicare could be the biggest winners. There’s consensus that seniors should get an annual limit on out-of-pocket costs for medications — $2,000 in the Pelosi bill or $3,100 in the Senate bill. Older people are the main consumers of prescription medicines.
Q: What would “Medicare for All” do about drug prices?
A: Under Medicare for All, the government would negotiate prices for prescription drugs.
Whether or not they support Medicare for All, Democratic presidential candidates are calling for Medicare to negotiate prices.
Q: Why are drug prices so much higher in the U.S. than in other countries?
A: It’s not the case for all drugs. U.S. generics are affordable for the most part.
The biggest concern is over cutting-edge brand-name drugs that can effectively manage life-changing diseases, or even cure them. Drugs with a $100,000 cost are not unusual any more. In other countries, governments take a leading role in setting prices.
In the U.S., some government programs such as Medicaid and the veterans’ health system get special discounts. But insurers and pharmacy benefit managers negotiate on behalf of Medicare and private health plans. Federal law protects the makers of a new drug from generic competition, which gives the manufacturer a lot of leverage.
Pharmaceutical companies say high initial prices are justified to recoup the costs of research and development.
However, a major case study — the 2015 Senate investigation of costly breakthrough drugs for hepatitis C infection — found that drugmaker Gilead Sciences priced the medication to maximize profits, not to foster access.
Q: What’s the outlook for drug pricing legislation?
A: Impeachment could suck the air out of the room.
“It is extremely difficult to get things done in that type of environment, and certainly for a president who is largely incapable of compartmentalizing,” said longtime Democratic health care adviser Chris Jennings. “Having said that, the work of policymakers in power must include being responsive to here-and-now domestic problems.”
Trump has pointedly refrained from criticizing Pelosi’s bill even as other Republicans called it “socialist.”
Pelosi’s legislation had its first committee consideration last week, and the leading Democrat on that committee promoted it using Trump-like rhetoric that it’s unfair for Americans to pay more. The bill will get a floor vote, and it could gain political momentum if a pending budget analysis finds big savings.
Democrats would be hard-pressed to drop their demand for Medicare negotiations. But could Trump agree to a more limited form of negotiations than what’s now in Pelosi’s bill? Could he sell that to Senate Republicans?
“It boils down to the crude political calculus of whether in the end this will help my side,” said health economist Joe Antos of the business-oriented American Enterprise Institute. “Will Democrats be able to stomach Donald Trump taking credit for all of this? On the Trump side, it is going to be more of a legacy issue for him.”

Americans need to know more before they can make up their minds about proposed overhauls to the nation’s health care system, according to a survey released Thursday.
When asked if they wanted to wipe out private health insurance for a so-called Medicare for All public insurance program, 40 percent of U.S. adults between the ages of 19 to 64 said they did not know enough to offer an opinion.
A few Democratic presidential candidates have put forward their proposed health care plans, including Medicare for All. Sen. Bernie Sanders, I-Vt. and Sen. Elizabeth Warren, D-Mass. have advocated for Medicare for All models that replace private insurance with a national health insurance plan. And Sen. Kamala Harris, D-Calif., released a health care proposal that covered 330 million Americans under one government health care plan. According to the candidates, these plans would make health care affordable for more Americans. It could help reduce the number of uninsured Americans, which currently amounted to 27.5 million people nationwide in 2018, according to the Census Bureau, marking a rise of 1.9 million people over the previous year.
According to a July 22 poll from the PBS NewsHour, NPR and Marist, 70 percent of U.S. adults said they supported Medicare for All proposals as long as they maintain an option to keep private health insurance. A system like this has been proposed by Pete Buttigieg. By comparison, when asked in a separate question, only 41 percent of survey respondents said they wanted to scrap private health insurance for a government-run plan.
In this latest poll from the Commonwealth Fund, another 32 percent of Americans said they opposed the idea, while 27 percent of Americans favored such a plan, according to the survey results published by the Commonwealth Fund, which researches health policy. The survey polled 4,914 U.S. adults ages 19 to 64 from March 19 to June 9.
“People are confused about what this might mean for them, and what it might mean for the health system and what it might mean in terms of trade-offs,” said Sara Collins, vice president of Health Care Coverage and Access at the Commonwealth Fund, during a call with reporters Wednesday.
Americans are largely satisfied with their health insurance, but lacked confidence that their health care coverage could protect them financially if they fell seriously ill and required medical care.
“These satisfaction rates reflect the fact that most people don’t use their insurance a ton,” said Sabrina Corlette, a research professor and co-founder of the Center on Health Insurance Reforms at Georgetown University. “It’s sporadic interactions.”
Eighty-five percent of working-age Americans said they were satisfied with their health insurance. That included private health insurance, Medicaid, and coverage purchased on the individual marketplace established under the Affordable Care Act. Another 14 percent said they were dissatisfied with their current health insurance.
In contrast, 61 percent of U.S. adults age 16 to 64 said they were confident that they would be able to afford the cost of care if they became seriously ill, while 38 percent of Americans said they were not confident.
These survey results come as Democratic presidential candidates promote their health care plans going into the 2020 election. Meanwhile, Republicans in Congress and the Trump administration have promised to replace the Affordable Care Act, known as Obamacare, with “something better,” although it is unclear what that would be. To date, they have eliminated some policies put into place under Obamacare, including dismantling the individual mandate.
Health care will be one of the most important issues among voters going into the next presidential election. Health care costs for Americans are the highest among industrialized nations. Meanwhile, life expectancy has dropped nationwide in recent years, in part due to the rise in drug overdose deaths, many of which are tied to the opioid crisis. Among developed nations the OECD ranked for infant mortality, the U.S. was among the bottom 11, after Russia.
This survey suggests that all the campaigns have their work cut out for them if they want to ramp up public awareness of proposals on the table to fix health care, Corlette said. She said the public needs more education and discussion about possible solutions aimed at problems in the U.S. health care system.
“It strikes me as a really good opportunity for people on both sides of the debate,” Corlette said. “There’s clearly a lot of people who have just not made up their mind.”
But she said the lack of confidence in how much protection health coverage affords people tugs at the reality that “the system doesn’t work really well for people who are very sick.”
New analysis from the Kaiser Family Foundation supports that notion. Annual family premiums for employer-based health insurance rose 5 percent to $20,576 on average, faster than wage growth, which increased by 3.4 percent, according to the study, published in Health Affairs. And since 2009, those premiums jumped 54 percent.
Health insurance costs and coverage only provide part of the picture of what troubles Americans, said Thomas Miller, a resident fellow with the conservative American Enterprise Institute.
Policymakers need to think about more than tinkering with “incremental expansions of coverage on the margins beyond where we already are,” Miller said. “It’s important to remember that people need most of all economic growth, job security and reasons to be optimistic about managing their lives.”

The defendants ordered unnecessary tests that were reimbursed by Medicare, with laboratories sharing the profit, DOJ says.
The U.S. Department of Justice has charged 35 people with unlawfully charging Medicare $2.1 billion in what it said is one of the largest healthcare fraud schemes in history.
The 35 alleged offenders were charged in five separate federal districts, and were linked to dozens of telemedicine firms and laboratories focused on genetic testing for cancer. The people charged, including nine doctors and one other medical professional, cumulatively billed Medicare billions for cancer genetic tests, the DOJ said in a press release.
The charges were a culmination of coordinated law enforcement activities over the past month that were led by the Criminal Division’s Health Care Fraud Unit, resulting in charges against more than 380 individuals who allegedly billed federal healthcare programs for more than $3 billion, and allegedly prescribed and dispensed approximately 50 million controlled substance pills in Houston, across Texas, the West Coast, the Gulf Coast, the Northeast, Florida and Georgia, and the Midwest.
These include charges against 105 defendants for opioid-related offenses, and charges against 178 medical professionals.
The investigation targeted an alleged scheme involving the payment of illegal kickbacks and bribes by CGx laboratories in exchange for the referral of Medicare beneficiaries by medical professionals working with fraudulent telemedicine companies for expensive, and medically unnecessary, cancer genetic tests.
According to the DOJ, the targets of the scheme were primarily seniors, who were approached at health fairs, at their homes during door-to-door visits, or through telemarketing calls. The “recruiters,” as they were called, would approach seniors about supposedly free cancer screenings or generic cheek swab tests, and the recruiters would then obtain the seniors’ Medicare information for the purposes of fraudulent billing or identify theft.
The recruiter would then get a doctor to sign off on a genetic so a lab would process it, and then pay a kickback in exchange for ordering the test. The lab would process the test and bill Medicare, and once it was reimbursed, would share the proceeds with the recruiter, according to the charges.
Often, the test results were not provided to the beneficiaries, or were worthless to their actual doctors. Some of the defendants allegedly controlled a telemarketing network that lured hundreds of thousands of elderly and/or disabled patients into a criminal scheme that affected victims across the U.S.
The defendants allegedly paid doctors to prescribe CGx testing, either without any patient interaction or with only a brief phone conversation with patients they had never met or seen.
WHAT’S THE IMPACT
In addition to the DOJ charges, the Centers for Medicare and Medicaid Services, Center for Program Integrity said it took adverse administrative action against cancer genetic testing companies and medical professionals who submitted more than $1.7 billion in claims to the Medicare program.
The DOJ Criminal Division, along with the U.S. Department of Health and Human Services Office of Inspector General and the FBI, spearheaded the investigation.
The DOJ calls the scheme one of the largest it has ever handled.
THE LARGER TREND
Since its inception in March 2007, the Medicare Fraud Strike Force, which maintains 15 strike forces operating in 24 districts, has charged nearly 4,000 defendants who have collectively billed the Medicare program for more than $16 billion.
In addition, CMS, working in conjunction with the Health and Human Services Office of the Inspector General, are taking steps to increase accountability and decrease the presence of fraudulent providers.
The newest Medicare fraud scheme is the second to be uncovered in the last month. Earlier in September, a telemedicine CEO pleaded guilty to one count of conspiracy to defraud the United States and pay and receive healthcare kickbacks and one count of conspiracy to commit money laundering in a scheme estimated at $424 million.
ON THE RECORD
“Unfortunately, audacious schemes such as those alleged in the indictments are pervasive and exploit the promise of new medical technologies such as genetic testing and telemedicine for financial gain, not patient care,” said Deputy Inspector General for Investigations Gary L. Cantrell of HHS-OIG. “Instead of receiving quality care, Medicare beneficiaries may be victimized in the form of scare tactics, identity theft, and in some cases, left to pay out of pocket. We will continue working with our law enforcement partners to investigate those who steal from federal healthcare programs and protect the millions of Americans who rely on them.”
“Healthcare fraud and related illegal kickbacks and bribes impact the entire nation,” said Assistant Director Terry Wade of the FBI’s Criminal Investigative Division. “Fraudulently using genetic testing laboratories for unnecessary tests erodes the confidence of patients and costs taxpayers millions of dollars. These investigations revealed some medical professionals placing their greed before the needs of the patients and communities they serve. Today’s law enforcement actions reinforce that the FBI, along with its partners, will continue to pursue and stop this type of illegal activity.”

CMS is proposing that hospitals make public their payer-specific negotiated charges for a limited set of “shoppable” services.
Hospitals and insurers have made clear their opposition to the Centers for Medicare and Medicaid Services proposed rule requiring the disclosure of their privately negotiated contract rates.
CMS is proposing that hospitals make public their payer-specific negotiated charges for a limited set of “shoppable” services or face civil monetary penalties, in a rule to go into effect on January 1, 2020. Comments were due by September 27.
Under the rule, hospitals would display payer-specific negotiated charges for at least 300 shoppable services, including 70 selected by CMS and 230 by the provider.
The American Hospital Association called it the wrong approach, even though it said it supported ensuring patients have the information they need, including knowing what their expected out-of-pocket costs would be. However, the AHA said, “Instead of helping patients estimate their out-of-pocket obligations, it would introduce confusion and fuel anticompetitive behavior among commercial health insurers in an already highly-concentrated insurance industry, seriously limiting the choices available to patients.”
America’s Essential Hospitals said, “We are particularly concerned that the agency’s proposals regarding the public posting of charges, in particular the posting of negotiated rates, offer little benefit to the consumer, add substantial burden to hospitals, and pose harm to competition, potentially driving up prices.”
America’s Health Insurance plans said that forcing disclosure of privately and competitively negotiated rates will not provide consumers with information that is actionable or helpful. I
“Instead,”AHIP said, “it will hamper competitive negotiations and push healthcare prices and premiums higher for patients, consumers, businesses and taxpayers. This proposed rule also has significant implications for, and is interconnected with, other proposed rules regarding interoperability of health care data. We are concerned that unknown entities will have open access to the data, with few restrictions on how they may use it.”
WHY THIS MATTERS
CMS released the proposals on July 29 in the 2020 hospital outpatient prospective payment and ambulatory surgical center payment rule.
The rule also has three additional proposed policies that run afoul of the law, the AHA said.
Specifically, the AHA opposes completion of the phase-in of payment reductions for the hospital outpatient clinic visit in excepted off-campus provider-based departments to the “physician fee schedule equivalent” rate of 40% of the outpatient prospective payment system rate.
The AHA said the proposal “exceeds the Administration’s legal authority and should be abandoned.”
The AHA has already won a case in court on the government’s site neutral payment policy.
“On the clinic visit policy, we remind CMS that the agency was recently found by the courts to have exceeded its statutory authority when it cut the payment rate for clinic services at excepted off-campus provider-based departments,” the AHA said.
Hospitals also object to continuing the current policy that pays for separately payable drugs acquired through the 340B drug savings program at the rate of average sales price minus 22.5%.
And the AHA objects to the implementation of a prior authorization process for five categories of outpatient department services.
THE LARGER TREND
On September 17, a federal judge ruled in favor of the AHA and hospital organizations, saying CMS exceeded its statutory authority when it reduced payments for hospital outpatient services provided in off-campus provider-based departments that were grandfathered under the Bipartisan Budget Act of 2015.
The AHA, joined by the Association of American Medical Colleges and several member hospitals, had filed the lawsuit in December.
ON THE RECORD
America’s Essential Hospitals said, “These cuts deter hospitals from expanding access in communities with the most need for healthcare services and run counter to CMS’ goal of integrated, coordinated healthcare.
“Taken together, these proposals would have a chilling effect on beneficiary access to care while also increasing regulatory burden,” the AHA said.
https://apnews.com/1c5c5dc43950421a9ab4ff7edb9fe678?omnicid=CFC1688174&mid=henrykotula@yahoo.com
Major legislation to reduce prescription drug costs for millions of people may get sidelined now that House Democrats have begun an impeachment inquiry of President Donald Trump. Proposals had been moving in Congress, but there are more ways for the process to break down than to succeed. Still, nobody says they’re giving up.
Some questions and answers about the legislation and its uncertain prospects:
Q: Why, now, is there a big push to lower drug prices?
A: Some would say it’s overdue. Drug prices emerged as the public’s top health care concern near the end of the Obama administration as people with health insurance got increasingly worried about their costs.
In the 2016 campaign, Trump and Democrat Hillary Clinton called for authorizing Medicare to negotiate prices. But after Trump won the White House, his focus shifted to the failed Republican drive to repeal the Affordable Care Act. A year went by before the administration reengaged on prescription drugs .
Now, facing the 2020 election, Trump and lawmakers of both parties in Congress have little to show for all their rhetoric about high drug prices. For there to be a deal , enough Democrats and Republicans have to decide they’re better off delivering results instead of election-year talking points.
Q: What are the major plans on the table?
A: On the political left is House Speaker Nancy Pelosi’s plan authorizing Medicare to negotiate prices for the costliest drugs. In the middle is bipartisan legislation from Sens. Chuck Grassley, R-Iowa, and Ron Wyden, D-Ore., to restrain drug price increases. The wild card is Trump. He doesn’t share the traditional Republican aversion to government as price negotiator and keeps complaining that it’s unfair for Americans to pay more than patients in other countries.
There’s significant overlap among the major approaches.
Trump, the Senate bill, and Pelosi would all limit what Medicare enrollees pay annually in prescription copays. That would be a major change benefiting more than 1 million seniors with high costs.
Pelosi and the Senate bill would require drugmakers to pay rebates if they raise their prices to Medicare beyond the inflation rate. Long-available medicines like insulin have seen steep price hikes.
Pelosi and the administration would use lower international prices to determine what Medicare pays for at least some drugs. Pelosi is echoing Trump’s complaint that prices are unfair for Americans.
“If they wanted to do a deal, it’s sitting right there in front of them,” said John Rother, president of the National Coalition on Health Care, an umbrella group representing a cross-section of organizations.
Q: How would any of these plans reduce what I pay for prescription drugs?
A: Under Pelosi’s bill, private purchasers such as health insurers and employer-sponsored plans would be able to get the same price that Medicare negotiates. Medicare would focus on the costliest medications for individual patients and the health care system as whole.
People on Medicare could be the biggest winners. There’s consensus that seniors should get an annual limit on out-of-pocket costs for medications — $2,000 in the Pelosi bill or $3,100 in the Senate bill. Older people are the main consumers of prescription medicines.
Q: What would “Medicare for All” do about drug prices?
A: Under Medicare for All, the government would negotiate prices for prescription drugs.
Whether or not they support Medicare for All, Democratic presidential candidates are calling for Medicare to negotiate prices.
Q: Why are drug prices so much higher in the U.S. than in other countries?
A: It’s not the case for all drugs. U.S. generics are affordable for the most part.
The biggest concern is over cutting-edge brand-name drugs that can effectively manage life-changing diseases, or even cure them. Drugs with a $100,000 cost are not unusual any more. In other countries, governments take a leading role in setting prices.
In the U.S., some government programs such as Medicaid and the veterans’ health system get special discounts. But insurers and pharmacy benefit managers negotiate on behalf of Medicare and private health plans. Federal law protects the makers of a new drug from generic competition, which gives the manufacturer a lot of leverage.
Pharmaceutical companies say high initial prices are justified to recoup the costs of research and development.
However, a major case study — the 2015 Senate investigation of costly breakthrough drugs for hepatitis C infection — found that drugmaker Gilead Sciences priced the medication to maximize profits, not to foster access.
Q: What’s the outlook for drug pricing legislation?
A: Impeachment could suck the air out of the room.
“It is extremely difficult to get things done in that type of environment, and certainly for a president who is largely incapable of compartmentalizing,” said longtime Democratic health care adviser Chris Jennings. “Having said that, the work of policymakers in power must include being responsive to here-and-now domestic problems.”
Trump has pointedly refrained from criticizing Pelosi’s bill even as other Republicans called it “socialist.”
Pelosi’s legislation had its first committee consideration last week, and the leading Democrat on that committee promoted it using Trump-like rhetoric that it’s unfair for Americans to pay more. The bill will get a floor vote, and it could gain political momentum if a pending budget analysis finds big savings.
Democrats would be hard-pressed to drop their demand for Medicare negotiations. But could Trump agree to a more limited form of negotiations than what’s now in Pelosi’s bill? Could he sell that to Senate Republicans?
“It boils down to the crude political calculus of whether in the end this will help my side,” said health economist Joe Antos of the business-oriented American Enterprise Institute. “Will Democrats be able to stomach Donald Trump taking credit for all of this? On the Trump side, it is going to be more of a legacy issue for him.”

