Why Atlantic Health’s CEO Is Treating Innovation as a ‘Cultural Shift’

Saad Ehtisham says the nonprofit health system is looking beyond typical ROI benchmarks for determining worthwhile investments in AI and digital tools for operational growth.


KEY TAKEAWAYS

Atlantic Health views innovation as an organizational and cultural transformation effort rather than simply a technology initiative.

The system’s AI investments are focused on reducing friction across care delivery, including clinician documentation burden and patient scheduling delays.

CEO Saad Ehtisham sees workforce resilience and consumer access as long-term strategic returns, alongside traditional financial performance metrics.

For many health systems, innovation has become shorthand for digital expansion and AI deployment designed to create a return on investment. At Atlantic Health, president and CEO Saad Ehtisham frames that approach in another way.

“We’re looking at innovation much differently than most systems are and not as a tool, but as a cultural shift,” Ehtisham told HealthLeaders.

That philosophy is driving the New Jersey-based health system’s use of technology to improve workflows for clinicians while simplifying access for patients.

Investment, according to Ehtisham, is flowing into ambient listening tools, workflow automation, digital scheduling capabilities, and AI applications aimed at reducing friction across care delivery.

A Happier Workforce is a Better Workforce

One of Atlantic Health’s biggest strategic priorities involves workforce sustainability.


The system has emphasized upskilling employees and encouraging leaders to think beyond traditional operational silos, Ehtisham highlighted. The organization wants managers and staff members to develop enterprise-level understanding that allows them to grow internally rather than looking for opportunities outside the system.

“What we want to do is make sure our team members don’t stay in the vertical expertise that they’re framed in, but they have the ability to cross-train into a different vertical and be able to grow in their acumen,” Ehtisham said.

Technology investments have become integral to that workforce strategy.

Atlantic Health recently piloted ambient listening tools that document physician-patient conversations during appointments. While many organizations evaluate those platforms through productivity or revenue gains, Ehtisham is more interested in the impact on clinician experience and long-term sustainability.

“How does that make our clinicians’ and physicians’ lives a lot easier and their flow throughout the day?” Ehtisham said. “Does that reduce their pajama time where they can spend more time with their families instead of having to be in their computers?”

Atlantic Health is also exploring agentic AI capabilities that can respond to certain administrative patient questions through Epic’s MyChart platform. The goal is to reduce after-hours inbox management that contributes to physician burnout.

“It is increasing the resilience of our physicians and that will in turn increase their ability to want to practice longer and want to be with the system,” Ehtisham said. “So that’s our ROI. And I don’t think you can put a dollar value on that. You probably could, you get a mathematician, you can quantify that through some algorithm. I would rather not.”

That same mindset has influenced nursing operations.

Atlantic Health has deployed robots capable of retrieving supplies and handling tasks that frequently pull nurses away from bedside care, Ehtisham noted.

“Twenty-five percent of the time our nursing or any nurse in any health system is spending is non-patient facing,” he said.

By supplementing those activities through automation, the system can allow its team members to focus on taking care of the patient and performing at the top of their license.

As Ehtisham puts it, staff are more likely to produce 150% output if they’re working at 90% of their capability from a resource intensity standpoint, and happier in what they do.

Pictured: Saad Ehtisham, president and CEO, Atlantic Health.

Opening the Digital Front Door Wider

Atlantic Health’s innovation strategy extends into consumer access.

One of the earliest operational changes implemented under Ehtisham involved measuring the next available appointment within 30 days across clinics and reducing delays that prevented patients from getting timely care.

“That was one operational lever we pulled early on,” he said.

According to Ehtisham, improving appointment access generated gains in consumer experience while contributing to stronger financial performance.

“We’re beginning to see it from consumer experience,” he said. “They’re much happier being able to get in when they want to be seen.”

The system is now experimenting with on-demand self-scheduling capabilities designed to better connect patients with its ambulatory infrastructure.

Atlantic Health continues to expand outpatient locations anchored around primary care as well. Many of those sites include rotating specialty services, imaging, laboratory capabilities, and physical therapy offerings intended to create centralized outpatient destinations.

The organization’s digital ambitions also include patient-facing AI applications.

Ehtisham said Atlantic Health is looking at developing its own version of Claude or ChatGPT, capable of guiding consumers toward the appropriate level of care based on conversations occurring through the platform. He envisions systems eventually using those interactions to direct patients toward physician appointments or virtual visits while simultaneously transferring relevant information into the clinical workflow before the encounter begins.

“We know consumers are going on those platforms and typing in, ‘I have this, what should I be?’” Ehtisham said. “That’s a platform that’s being engineered by non-healthcare providers systems. We’d rather get into that technology.”

Keeping Financial Discipline in Focus

Even as Atlantic Health expands technology investments, Ehtisham acknowledged the tension many health systems face when balancing the pursuit of innovation with financial realities.

“Healthcare is the only place where you bring in technology, the cost goes up versus going down,” he said. “We’re trying to invert that thinking.”

That influences how Atlantic Health approaches vendor relationships and operational deployment. Ehtisham said the system prefers working more deeply with select partners capable of improving workflows end-to-end, rather than as a one-off.

He pointed to operational throughput as one example. The organization is evaluating how technology can reduce bottlenecks beginning in the emergency department and continuing through inpatient discharge processes. Smoother patient flow can improve experience while generating financial yield through shorter lengths of stay, Ehtisham stressed.

“It starts creating this pipeline of revenue streams and future predicted models that’s going to be coming through market share that you’re going to be gaining over time,” he said. “It doesn’t happen overnight. But you have to commit to what you’re trying to do.”

Innovation can’t happen without resourcing though, which is why Atlantic Health has dedicated annual capital dollars specifically toward technology investments tied to operational improvements.

“It’s more of a derivative,” Ehtisham said. “You’ve got to generate so much operating margin in order to invest in that,” creating a direct link between financial discipline and innovation capacity.

Why Hospitals Are Targeting Leadership, Administrative Jobs in Latest Layoffs

As financial challenges persist and clinical labor remains difficult to replace, many hospitals are turning to restructuring for cost savings.


KEY TAKEAWAYS

Care New England, Washington Regional Medical System, and Intermountain Health all announced layoffs that prominently affected administrative functions.

Hospitals are increasingly embracing “The Great Flattening,” consolidating nonclinical roles to reduce overhead while preserving frontline care capacity.

While leaner organizational structures may improve efficiency and speed decision-making, reducing leadership layers can also create operational strain and place added burden on remaining staff.

Three notable health systems announced layoffs in recent days, and in all three cases, management and leadership roles were largely affected. Even as labor costs continue to climb, clinical talent remains scarce, making administrative jobs often the primary target of workforce reductions.

Healthcare, and hospitals specifically, are not immune to “The Great Flattening” impacting corporate America. Companies across industries have spent recent years trimming down middle management, if not outright eliminating those positions, for the purpose of creating leaner workforce structures and cutting overhead.


In the case of hospitals, many have taken the step to consolidate functions that aren’t directly tied to delivering patient care.

The trend became particularly visible over the past week with Care New England, Washington Regional Medical System, and Intermountain Health all initiating reductions.

Providence, Rhode Island-based Care New England eliminated more than 30 leadership and nonclinical positions as part of a restructuring to address financial pressures and help close an estimated $20 million budget gap for fiscal year 2026. System president and CEO Michael Wagner said in a statement that “current financial conditions have made additional cost-saving measures unavoidable.”

Elsewhere, Washington Regional Medical System announced a restructuring plan that included 86 job cuts through consolidation of management and support functions. “By restructuring our management operations and consolidating roles, Washington Regional will reduce redundancies and optimize efficiency while still providing the high-quality care our community has come to expect,” Lucas Campbell, president and CEO of Washington Regional, said in the announcement.

At Intermountain Health, the 93 positions that were eliminated amid clinic closures and operational changes in Colorado and Montana looked a little different. While clinical roles were affected as part of the restructuring, the organization also pointed to leadership and administrative consolidation to improve efficiency and better align resources.

Though the circumstances surrounding the three systems differed, the overlap across the layoffs was the emphasis on leadership restructuring and administrative streamlining.

The logic behind these restructurings is straightforward: clinical workers are difficult to replace, whereas administrative costs often represent one of the few areas where organizations can still reduce spending relatively quickly.

According to Kaufman Hall’s latest National Hospital Flash Report for March, hospitals are operating more efficiently, but financial performance is still being weighed down by rising expenses. Length of stay, for example, was down 3% year-over-year, indicative of improved throughput. However, that clinical efficiency requires adequate staffing, and that labor is costly, as seen in a 4% rise in labor expense per calendar day year-over-year.

To just maintain their thin margins, hospitals are being forced to cut costs in areas that won’t directly hinder patient flow. That’s why administrative restructuring is often viewed as a less disruptive path toward reducing overhead while sustaining operational efficiency.

The result can also be a faster decision-making structure, allowing organizations to be strategically nimbler during a time when moving slow can leave hospitals behind the curve.

Still, the benefits come at a price. The loss of leadership and management may not be felt in financial performance immediately, but over time, it can create operational strain and place additional burden on remaining leaders and frontline staff.

For hospital executives, the question they must answer is how far their organization can streamline before efficiency gains start to create new organizational pressures.

The Bill That Never Ends

Even with insurance, millions of Americans with serious illnesses are trapped in a cycle of deductibles, debt collectors and annually resetting medical bills.

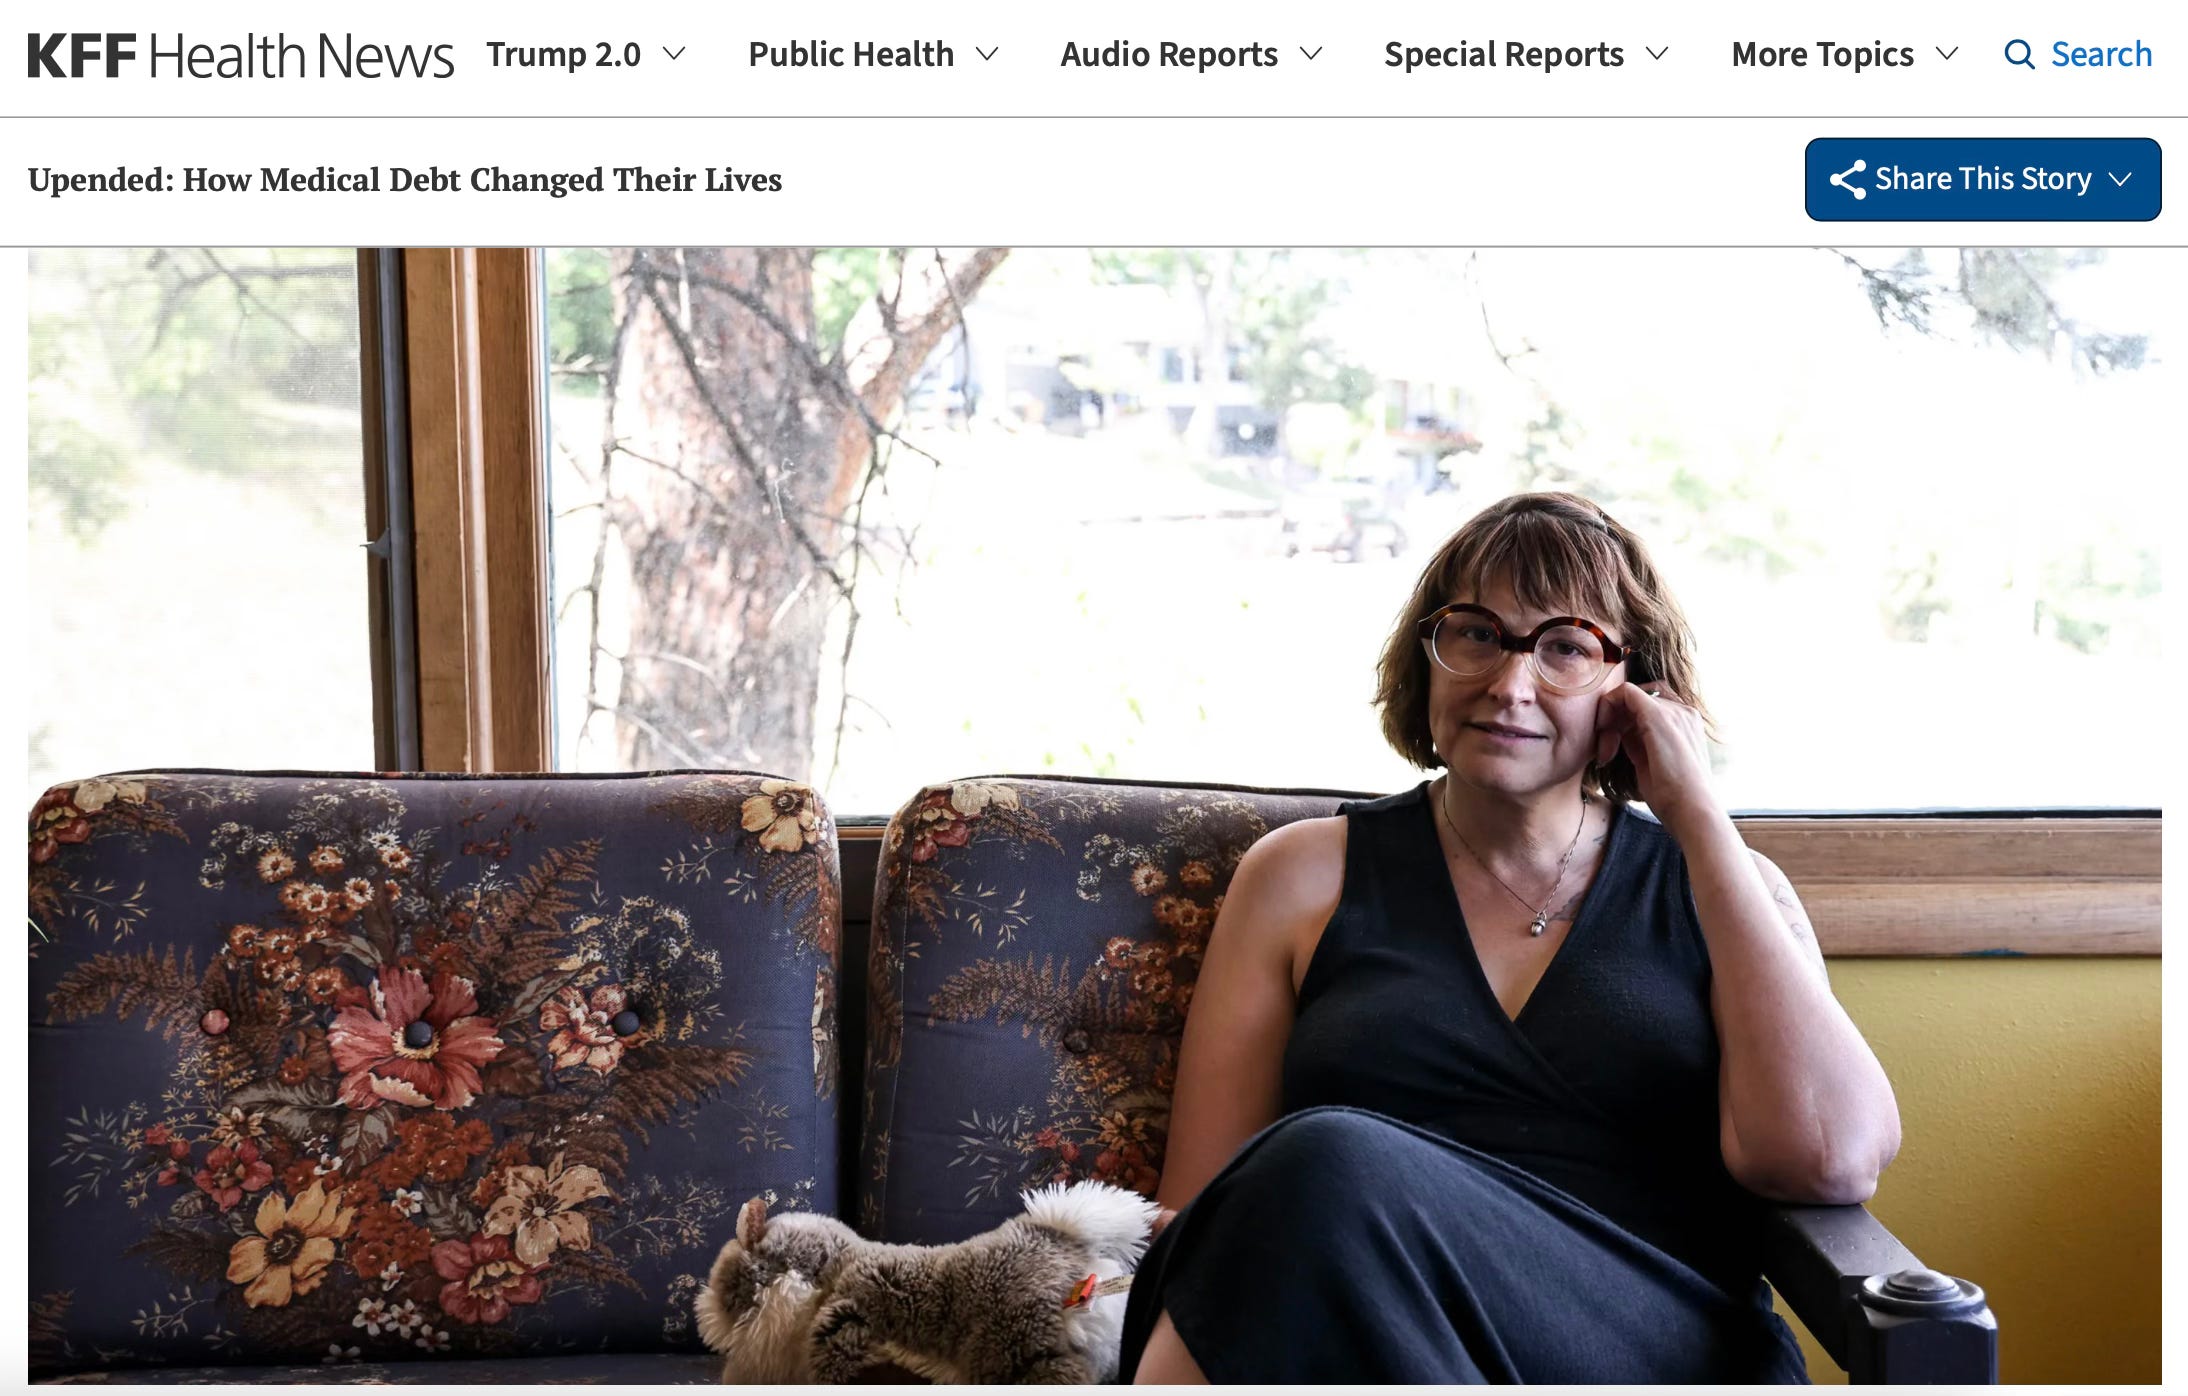
Jeni Rae Peters was a single mother and mental health counselor in Rapid City, South Dakota, when she was diagnosed with stage 2 breast cancer in 2020. She had health insurance through her employer. She kept working through surgery and chemotherapy because she knew that losing her job meant losing her coverage, and losing her coverage meant losing everything.

As KFF Health News reported in its landmark “Diagnosis: Debt” investigation, the bills came anyway. Her deductible and out-of-pocket limit reset every Jan. 1 — as they do for most health plans. When she switched jobs and her insurance changed, the clock reset again. In 2021 it reset once more, and when she slipped on the ice and broke her wrist — a fracture likely made worse by chemotherapy that had weakened her bones — she was charged thousands more. Surgeries, radiation and chemotherapy left her with at least $30,000 in debt. She couldn’t tell you exactly how much she owed anymore. The bills kept coming.

Jeni Rae Peters in KFF Health News.

One of the debt collection calls came while she was lying in the recovery room after her double mastectomy. She was still half-delirious from anesthesia. She thought it was her kids calling. It was someone asking her to pay a medical bill.

Jeni Rae Peters’ story is not unusual. In the brutal current version of American health insurance, it is practically routine.

A 2024 survey by the American Cancer Society Cancer Action Network found that nearly half of cancer patients and survivors — 49% — have incurred medical debt to pay for their cancer care, with another 13% expecting to incur debt as they begin or continue treatment. We’re not talking about uninsured Americans here. In fact, nearly all of them — 98% — had health care coverage at the time they accumulated that debt. What they had in common is that most of them were enrolled in a high-deductible health plan.

Having insurance, in other words, did not protect them. In many cases, the insurance plan itself was the mechanism of their financial destruction.

Over the past two decades, the insurance industry — with the quiet approval of employers eager to cut their own costs — systematically shifted financial risk onto patients. The gears of the mechanism are familiar to anyone who has ever tried to read an Explanation of Benefits: deductibles, copayments, coinsurance, out-of-pocket maximums. These instruments were designed, in theory, to discourage unnecessary care. In practice, they have become a second billing system — one that activates precisely when a person is most sick, most frightened and least equipped to fight back.

The numbers have grown staggering. The average deductible for a single worker in employer-sponsored coverage now exceeds $1,700 — and that figure masks the reality for workers at smaller firms or in lower-wage jobs, where deductibles of $3,000, $5,000 or more are common. The Affordable Care Act limits the amount of money Americans with commercial insurance have to pay out of pocket, but the cap was unreasonably high from the start, it increases every year – and it resets every year. This year the out-of-pocket maximum is $10,600 for an individual and $21,200 for a family. For a cancer patient like Jeni Rae Peters, hitting that cap wasn’t a worst-case scenario. It was the first-year scenario. And then the calendar flipped to Jan. 1. And it all reset.

This is the particular cruelty that most Americans don’t fully understand until they get sick: the out-of-pocket maximum isn’t a lifetime protection. It’s an annual one. Every January, the counter goes back to zero. The deductible resets. The coinsurance begins again.

For someone managing cancer — or diabetes, or multiple sclerosis, or heart disease — this isn’t a one-time financial hit. It’s a recurring one, year after year, for as long as the disease persists. Oncologists have a term for it: financial toxicity. The treatment harms the body. The bills harm everything else.

The harm is measurable and well documented. Among cancer patients who accumulate medical debt: 60% are unable to put money into savings; 49% have their credit score damaged; 46% report being harassed by creditors and debt collectors. Eighteen percent consider filing for bankruptcy. Six percent actually do. Eight percent lose their home or are forced to live somewhere they don’t feel safe.

Researchers have also found that cancer patients who go bankrupt are more likely to die than cancer patients who don’t. Financial toxicity is not a metaphor. It is a cause of death.

There is a philosophical argument, still advanced in insurance industry testimony and in certain policy circles, that requiring patients to pay something for care makes them more cost-conscious consumers. I used to help make that argument when I was an insurance industry communications executive. It is one of the things I regret most about that career.

What that argument leaves out is that no one rations chemotherapy because it seems unnecessary. No one decides their insulin isn’t worth the cost because they’re being “judicious.” The cost-sharing model punishes the sick for being sick. It was designed to shift costs, not to improve health. And it has worked spectacularly well for health insurers. Forcing health plan enrollees to pay hundreds and often thousands of dollars out of their own pockets before their coverage kicks in enables insurers to pay far fewer claims today than they did before they began pushing Americans into high-deductible plans two decades ago.

In the coming weeks, I’m going to tell more stories like Jeni Rae Peters’. I’ll be writing about what’s happening to people who buy coverage through the ACA Marketplace and discover that “covered” doesn’t mean what they thought it meant, about how our employers have become the primary architects of most Americans’ financial exposure when they get sick, and what we can do about it.

It’s The End of the Independent Hospital. Here’s What Comes Next for Community Care

An unforgiving financial climate is forcing many community hospitals to choose between preserving independence and pursuing consolidation. But the path forward doesn’t have to be strictly binary.


KEY TAKEAWAYS

The financial pressure facing community hospitals is driven by widespread underpayment that makes sustaining independence difficult. 

Consolidation can provide stability, but it often brings higher costs, workforce disruption, and reduced local control over decision-making. 

Hospitals that act early have more strategic options, while delayed action leads to fewer choices and diminished leverage in shaping their future.

Independent hospitals have survived reimbursement cuts, labor shortages, and waves of consolidation before. But according to the executives in this month’s HealthLeaders cover story, this time may be different.

In a sweeping look at the financial and political pressures reshaping healthcare, our CEO editor Jay Asser examines why leaders at independent and regional health systems increasingly believe the traditional hospital business model is reaching its breaking point.

The story features candid conversations with Russ Ranallo, CFO of Owensboro Health; Pat Charmel, President and CEO of Griffin Health; Scott Rathgaber, MD, CEO of Emplify Health; and longtime healthcare executive Peter Wright, all of whom argue that the combination of Medicaid cuts, collapsing public trust, political gridlock, and rising operational costs is forcing hospitals into a new era of survival.


Their message is blunt: the old playbook no longer works.

For decades, hospitals found ways to absorb federal payment reductions through cost-shifting, consolidation, and commercial payer leverage. But as Jay reports, leaders now say those escape valves are closing all at once. Rural and independent systems are confronting impossible math, policymakers are demanding accountability without offering solutions, and communities still expect hospitals to provide care regardless of financial reality.

The story dives into the uncomfortable questions many executives are now asking privately:

  • Is fee-for-service finally collapsing under its own weight?
  • Have hospitals lost the political and public trust needed to defend themselves?
  • And if the current model is no longer sustainable, what replaces it?

Forget reimbursement cuts. Now the conversation centers around whether independent hospitals can survive the next decade at all.

Read the full cover story to see why healthcare leaders say the industry is heading toward a reckoning it can no longer avoid.

Congress, Hospital CEOs Clash Over What’s Behind Rising Costs

At a House Ways and Means Committee hearing, lawmakers targeted pricing and market power while executives pointed to cost pressures and reimbursement gaps.


KEY TAKEAWAYS

House Ways and Means Committee members cast hospitals as central figures contributing to increased costs for patients.

CEOs from major health systems highlighted labor costs, Medicare Advantage delays, and uneven reimbursement.

Ongoing disconnect between lawmakers and hospital leaders continues to affect affordability policy and provider strategy.

hearing before the House Ways and Means Committee brought hospital finances into focus as lawmakers questioned the drivers of healthcare spending and health system CEOs described the reality facing providers.

The discussion centered on pricing, profit margins, and consolidation, with members of Congress pressing for accountability, while CEOs of HCA Healthcare, CommonSpirit Health, New York-Presbyterian, and ECU Health pointed to cost pressures and reimbursement challenges impacting business decisions.

Though both sides agreed that rising costs remain a significant issue, the hearing illustrated a divide in how those costs are understood. That tension continues to influence both policy proposals and provider strategy as the debate over affordability moves forward.

Committee chairman Jason Smith, R-Mo., opened the hearing by comparing hospital profitability with major corporations and tying that performance to what patients pay for care.

“Hospitals with more than 100 beds have a higher profit margin than Delta Air Lines, Target, or Disney,” Smith said. “Turns out charging an arm and a leg for health care is more lucrative than the Happiest Place on Earth.”

Smith placed responsibility on the entire healthcare system and highlighted insurers, which also faced the committee in January, but stressed that hospitals must answer for their role.


“This committee isn’t interested in hearing about how the high prices your businesses charge are someone else’s fault,” Smith said. “The blame game didn’t work with insurers, and it won’t work today. Simply put, hospitals are charging an insane amount for care. Hospital prices have skyrocketed 300 percent in just over two decades – more than any other sector of our economy.”

That line of questioning reflects a growing focus in Washington on hospital pricing as a central factor in affordability, and a push to rein in price increases through policymaking.

During the hearing, lawmakers raised concerns about the impact of consolidation on negotiated rates, the role of large systems in shaping local markets, and the degree to which higher commercial prices ripple through employers and households.

Executives described a more complex financial picture that extends beyond headline margins.

Sam Hazen, CEO of HCA, acknowledged elements of the committee’s concerns while emphasizing that hospital reimbursement varies widely based on factors like patient mix and acuity.

“There are certain aspects of your discussion here that have merit,” Hazen said. “I think there’s also merit to the hospitals receiving a premium in certain circumstances, so we would be more than willing to work with you on that.”

Payment friction emerged as a recurring theme, particularly in relation to Medicare Advantage. Wright Lassiter III, CEO of CommonSpirit, pointed to delays and denials as a source of strain for large nonprofit systems.

“Medicare Advantage plans are the most challenging today,” he said. “We have $4.3 billion in unpaid Medicare Advantage claims, with nearly $1 billion of that being more than 150 days past due for care that CommonSpirit has delivered to patients and communities that you represent.”

The conversation also turned to consolidation and access in regional markets. Michael Waldrum, CEO of ECU Health, described consolidation as a response to shifting market dynamics rather than a strategy aimed at expanding pricing leverage.

“Consolidation in our market is not driven by preference, it is how we survive,” he said. “As some exit and others enter with profit-driven agendas, systems like ECU Health are left to serve as a safety-net. The result is reduced access, worsening outcomes and increasing costs.”

statement submitted by the AHA for the hearing reiterated the current pressures facing hospitals, but noted an effort to reduce the cost of care by “improving efficiency, embracing innovative technologies and redesigning how services are delivered.”

The AHA called on insurers, purchasers, drug and supply manufacturers, and policymakers to work together with hospitals on four key areas of the healthcare system: improving the health of individuals and communities, advancing value through care transformation, reducing regulatory and administrative waste, and innovating to improve care quality and outcomes.

However, the gap between how lawmakers view hospital pricing and how health system leaders contend with rising costs and uneven reimbursement continues to limit alignment on policies aimed at improving affordability.