Steward’s bankruptcy documents reveal sprawling debt, planned hospital fire sale

Since filing for bankruptcy Monday, Steward Health Care revealed it’s carrying more than $1 billion in debt and said its entire hospital portfolio is for sale.

At 3:30 a.m. Monday, Steward Health Care filed for Chapter 11 protections in U.S. Bankruptcy Court for the Southern District of Texas.

Eleven minutes later, Steward employees had an email waiting from their CEO, Ralph de la Torre. The CEO told his staff that industrywide economic headwinds and delays in Steward’s planned asset sales had forced the physician-owned health network to initiate restructuring proceedings.

“It is incumbent on all of us to ensure that this process has no impact on the quality care our patients, their families, and our communities can continue to receive at our hospitals,” de la Torre wrote in an email viewed by Healthcare Dive. “To the vast majority of you, operations will either not be different or improve.”

“To be clear, this is a restructuring under chapter 11; it is not a closure and it is not a liquidation,” he wrote.

The email was the first time employees had heard directly from Steward leadership about the company’s financial distress — though rumors and uncertainty about the operator had been festering for weeks, according to Marlishia Aho, regional communications director for the union 1199SEIU United Healthcare Workers East.

Leading up to Monday’s filing, state and federal lawmakers were increasingly worried about how a bankruptcy at the largest physician-led hospital operator in the country would impact access to care. 

Regulators in Massachusetts — where Steward operates eight hospitals — held closed-door strategy sessions to map out contingency in case of a bankruptcy, and workers staged rallies to protest possible hospital closures.

Steward provides care for more than 2 million patients each year across 31 hospitals and 400 facility locations, according to bankruptcy filings. The company also employs nearly 30,000 employees across its eight-state portfolio, including 4,500 primary and specialty care physicians. 

Steward’s first-day bankruptcy motions shed light on the operator’s future — and outlines its strategy for paying down its massive debt by selling assets. Here are the biggest takeaways.

Steward’s sprawling debt

Steward has earned a reputation for being cagey about its finances — to the dismay of Massachusetts Gov. Maura Healey, who accused the company of operating in a “black box” in a letter to its CEO earlier this year.

The operator has refused to file routine finances with Massachusetts regulators for years, citing a need to protect confidential business data. Even as the company shuttered hospitals this winter, regulators said Steward still dragged its feet on providing financial data, frustrating policymakers’ efforts to build out contingency plans.

“One of the good things about bankruptcy is that Steward and its CEO … will no longer be able to lie,” said Healey during a press conference Monday morning. “Transparency is really important here, and that’s why you know we’re looking forward to seeing what is in the various documents … We need clarity about debts and liabilities.”

In a slew of first-day motions, Steward now revealed it owes around $1.2 billion in total loan debts and about $6.6 billion in long-term lease payments.

Steward owes north of $600 million to 30 of its largest lenders, which include UnitedHealth-owned Change Healthcare, Philips North America LLC, Medline Industries, AYA Healthcare and Cerner.

The healthcare operator owes $289.8 million in unpaid compensation obligations, including $68 million to its own workers in unpaid employee salaries, $105.6 million in payments for physician services and $47.7 million owed to staffing agencies.

It also has approximately $979.4 million outstanding in trade obligations, of which approximately 70% are over 120 days past due.

The filings follow lawsuits from a multitude vendors — including staffing firms, consultants, medical equipment companies, electricians and marketing research companies — who said Steward reneged on payment obligations.

Steward’s interim funding tied to hospital sales

Though Steward had a consortium of six private lenders financing its asset-based loans this year, now only one lender is listed in bankruptcy filings as funding its debtor-in-possession financing: its landlord, Medical Properties Trust.

The change in vendors is notable, according to Laura Coordes, professor of law at the Sandra Day O’Connor College of Law at Arizona State University.

“Something went on to get these other lenders to drop out,” she said.

The landlord may be opting to fund Steward during bankruptcy proceedings in hopes of getting its own money back more expediently, according to Coordes.

Steward is MPT’s largest tenant and the healthcare network will owe MPT at least $6.9 billion in debt and lease obligations by 2041, according to the filings.

MPT agreed to finance $75 million debtor-in-possession financing and could fund up to $225 million more if Steward completes asset sale milestones on time.

During Tuesday morning’s first day hearing a representative for Steward told Judge Chris Lopez that all of Steward’s 31 hospitals are for sale. But to receive the $225 million from MPT, Steward has to hit aggressive sales milestones. It must host an auction for all non-Florida hospitals by June 28 and all Florida properties by July 30.

Since February, MPT executives have said there is strong interest from buyers in taking over Steward leases. However, Steward has yet to sell a hospital.

Experts have told Healthcare Dive they’re skeptical other operators would take on Steward’s leases at MPT’s current rental rates.

“Given the unaffordability of the leases and given that it hasn’t worked in the past, I do think that really material rent concessions are going to be needed to get this done,” said Rob Simone, sector head of real estate investment trusts at analyst firm Hedgeye.

Steward also signed a letter of intent to sell its physician group, Stewardship Health, to UnitedHealth. Although the deal was first announced in March, regulators have not yet begun reviewing the deal, according to David Seltz, executive director of the Massachusetts Health Policy Commission. Seltz said missing paperwork is delaying the review.

The Stewardship deal is not tied to further funding. A representative from UnitedHealth declined to comment on the pending deal and whether the bankruptcy proceeding would impact the sale.

Future of Steward

Employees have received conflicting messages about the future of Steward hospitals.

On one hand, both de la Torre and Massachusetts officials said Monday that Steward hospitals would remain open this week. However, Healey also emphasized that she wants Steward out of the state.

“Ultimately, [bankruptcy] is a step toward our goal of getting Steward out of Massachusetts,” Healey said during a press conference Monday.

Some Steward facilities may wind down during the bankruptcy proceedings, said Massachusetts Attorney General Andrea Campbell. Her office will oversee that process closely, and Steward will be required to provide licensing and notice obligations.

A healthcare worker at Steward’s Nashoba Valley Hospital told Healthcare Dive Monday she’s particularly concerned about the fate of her facility, which she says serves 14 communities but is small compared to some other hospitals in Steward’s portfolio. She doesn’t want regulators to forget about Nashoba.

“What I’m hoping for is that our state representatives and our local representatives really push to keep the hospital open,” she said. “But my concern is we get overlooked.”

State officials said they would continue monitoring Steward facilities to ensure quality care and push for the appointment of a patient care ombudsman to represent the interests of patients and employees during bankruptcy proceedings. Officials have already launched a website to offer resources about the bankruptcy process.

Still, employees are unsure of the path forward.

The Nashoba Valley Hospital employee told Healthcare Dive they’re conflicted about whether to stay at the hospital they’ve worked at for years or try to find a new position while they can.

“I’ve used the hospital since I moved out here. I’ve been living out in this area for like 25 years … I’ve brought my mother to this hospital,” the worker said. “It’s my hospital. It’s not just where I work. It’s what I use, and it’s vitally important to the community.”


HHS finalizes revised dispute resolution process for 340B program

https://www.kaufmanhall.com/insights/blog/gist-weekly-april-26-2024

Late last week, the Department of Health and Human Services (HHS) published a final rule establishing a new administrative dispute resolution process for the 340B drug discount program.

A panel, composed of government experts from the Office of Pharmacy Affairs, will resolve claims raised by covered entity providers about drugmakers overcharging them for 340B drugs, as well as claims from pharmaceutical companies that covered entities are diverting or duplicating discounts improperly. The new process, which will go into effect in mid-June, allows the panel to review claims on issues related to those pending in federal court. It’s intended to be “more accessible, administratively feasible, and timely” than a prior process established by HHS in 2020 that was paused after legal challenges.

The Gist: 

This new 340B dispute resolution process is likely to see extensive use, as battles between providers and drugmakers over the drug discount program have heated up significantly in recent years. There are more than 50 ongoing court cases related to the program, many of which concern actions taken by at least 20 major drugmakers to restrict 340B sales to contract pharmacies. Although this new process may provide more effective dispute resolution, none of its decisions can be considered final until courts have settled the myriad cases before them.

    U.S. labor market slows in April, adding 175,000 jobs

    https://www.axios.com/2024/05/03/jobs-report-april-us-economy

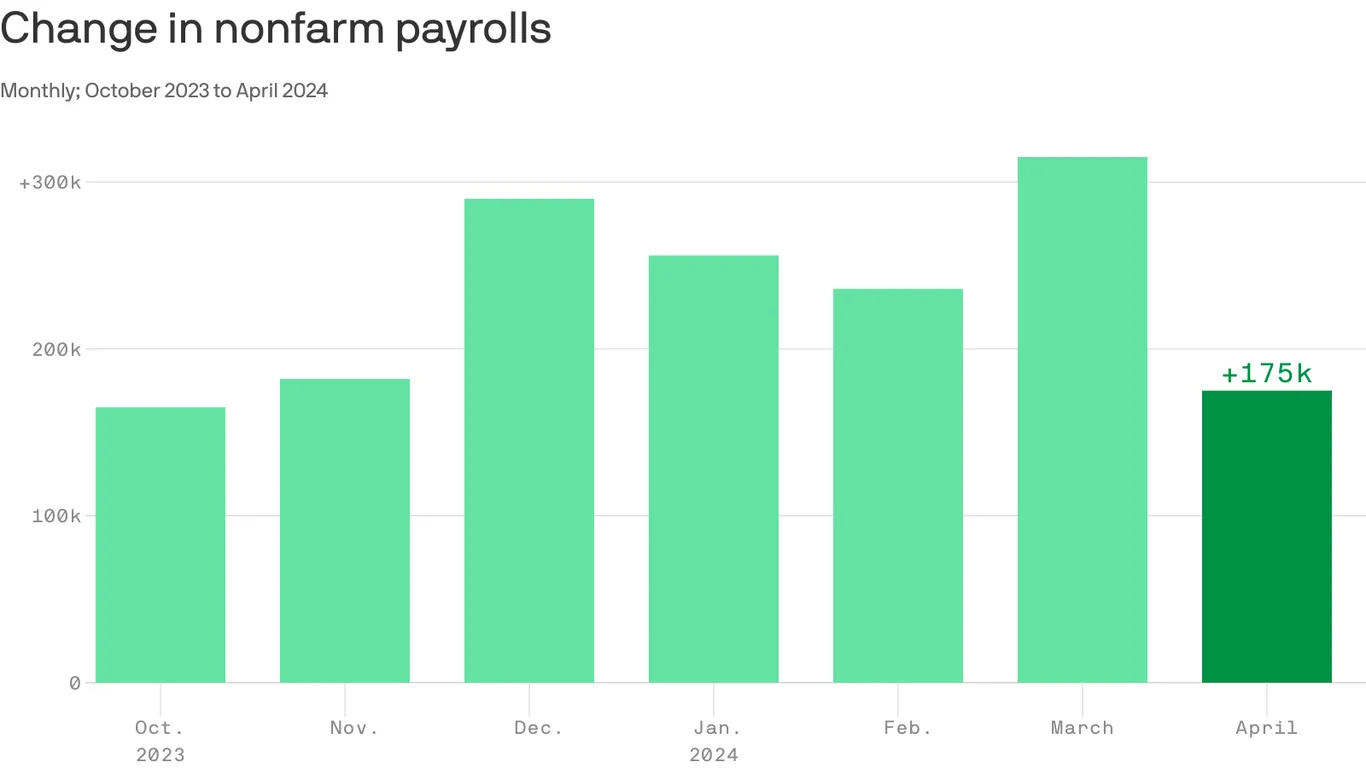
    The U.S. economy added 175,000 jobs in April, while the unemployment rate ticked up to 3.9% from 3.8%, the Labor Department said on Friday.

    Why it matters: 

    Jobs growth slowed from the prior month’s hot pace, but the data suggests that the labor market is still chugging along with healthy demand for workers.

    • The pace of hiring was notably slower than economists’ estimate of 240,000 jobs in April.
    • Job gains in March were slightly better than previously thought, upwardly revised to 315,000 from 303,000—though payrolls in February were revised lower by 34,000 to 236,000.

    Driving the news:

    The lower-than-expected job gains were concentrated in health care, social assistance, transportation and warehousing

    • Average hourly earnings, a measure of wage growth, rose 0.2%.
    • Over the past 12 months, average hourly earnings increased 3.9%.

    State of play:

    Friday’s data is the latest evidence that the labor market is holding steady — an important development for the broader economy.

    • The Federal Reserve this week kept interest rates at the highest level in more than two decades.
    • Its policymakers suggested that any rate cuts would happen later than previously thought due to stalled progress on curbing inflation.
    • Fed chair Jerome Powell this week said that the central bank would be “prepared to respond to an unexpected weakening in the labor market.”

    Thought of the Day: Carnegie on Leadership

    Insurers brace for continued Medicare Advantage medical costs

    https://www.healthcaredive.com/news/health-insurer-medicare-advantage-utilization-2024/707360

    The big question coming out of the health insurance earnings season is how much elevated utilization among seniors is carrying over into 2024.

    Medicare Advantage medical costs dominated fourth-quarter discussions between health insurers and investors, after higher healthcare utilization popped up like weeds in some segments of each payers’ business.

    Yet health insurers’ forecasts for how higher utilization will affect their performance in 2024 are night and day.

    Some payers controlled medical costs more effectively than analysts expected, said rising spending shouldn’t affect their outlooks for this year or guided to a stronger 2024 than previously forecast. That group includes UnitedHealth, Centene, Elevance and Cigna.

    However, Humana and CVS cut their 2024 earnings outlooks on the heels of last year’s results, and said they expect elevated medical costs to continue this year.

    Humana’s outlook is especially grim: The Kentucky-based payer’s earnings expectations for 2024 came in about half as low as analysts had expected.

    Even payers that emerged from 2023 with their financial outlooks unscathed said they plan to cut benefits or raise premiums this year. The plan redesigns are to protect margins in MA — a business that historically generates significant profits, but is facing challenges that threaten to kill the golden goose.

    Why didn’t payers see medical costs coming?

    MA plans have skyrocketed in popularity. More than half of Medicare seniors are currently signed up for the plans, attracted by benefits like lower monthly premiums and dental and vision coverage. An onslaught of marketing by insurers didn’t hurt, either, as payers jockey for members. Competition is fierce, as MA margins per enrollee can be twice as high as those in other types of plans.

    Yet, more members are creating more problems for some insurers because of rising medical utilization. Starting in the second quarter last year, seniors sought out medical care they had delayed during the COVID-19 pandemic, hiking insurers’ spending.

    For example, CVS added 800,000 MA enrollees for 2024, mostly nabbed from other payers after CVS aggressively expanded its benefits. But that’s coming back to haunt the Rhode Island-based insurer, which cut its earnings per share outlook for this year due to high medical costs.

    There are a few potential explanations for what’s driving the elevated utilization, and why insurers might not have properly forecast the uptick in trend, according to J.P. Morgan analyst Lisa Gill.

    Enrollees in MA tend to be healthier than those in traditional Medicare. But as more seniors join MA, the program’s risk population could be skewing sicker, Gill wrote in an early February research note. Insurers could have missed early warning signs of higher acuity as seniors avoided doctor’s offices during the pandemic.

    Higher demand could have also existed earlier, but providers might not have been able to address it because of labor shortages that have now ameliorated, Gill said. Similarly, insurers could have added new MA enrollees with less diagnosis history relative to the rest of their population, resulting in lower visibility into their conditions.

    Medical loss ratio is a useful metric for understanding how unexpectedly high utilization is affecting insurers.

    Medical loss ratio, or MLR, is a percentage of how much in healthcare premiums insurers spend on clinical services and quality improvement. The higher the MLR, the less in premiums insurers are spending on administration or marketing — or retaining as profit. As such, insurers generally try to keep their MLRs low (though within regulatory bounds to avoid sanctions).

    MLRs soared in payers’ Medicare businesses in the fourth quarter, as the utilization trends that emerged earlier in 2023 conflated with a typical seasonal rise in medical spending during the winter months.

    Utilization inflation

    Insurers chalked the increase in medical costs up to different drivers.

    Seniors covered by UnitedHealth and Humana, which together hold almost half of the total MA market share, continued to seek outpatient care in droves in the fourth quarter, including procedures like orthopedic surgeries.

    UnitedHealth’s members required more spending on seasonal diseases like the flu, COVID or respiratory virus RSV. Elevance, Centene and CVS also reported elevated outpatient care overall for things like elective procedures, along with higher spend on seasonal needs.

    That wasn’t the case for Cigna — which had lower than expected spending on seasonal diseases — and Humana. Humana’s uptick in care was “not respiratory driven,” said CFO Susan Diamond on the payer’s fourth-quarter earnings call in January.

    “We don’t have any clear indicators that it is something you can reasonably assume is seasonal,” Diamond said.

    As for inpatient care, Centene and CVS didn’t report higher utilization of hospital services than expected. Elevance also didn’t say that inpatient trends were contributing to growing costs.

    Yet, UnitedHealth and Humana warned investors about rising inpatient costs, which is concerning for insurers given hospital care is more expensive to cover. UnitedHealth blamed pricey COVID admissions, while Humana said it was seeing more short stays in hospitals across the board.

    Humana’s Diamond said recent government regulations requiring MA payers to comply with coverage determinations in traditional Medicare could be a potential driver of the higher inpatient spend. The rule requires insurers to cover an inpatient admission if the patient is expected to require hospital care for at least two midnights.

    Other insurers said they had planned for the so-called “two-midnight rule.”

    On Feb. 6, Centene CFO Drew Asher told investors that the payer had factored the rule into its planning for 2024. Meanwhile, CVS CFO Tom Cowhey said one day later the company had adjusted internally in response to the rule.

    Looking forward

    The increase in utilization — combined with weaker payment rates, changes to MA quality ratings and a shifting risk adjustment model — have created an updraft for MLRs, especially for insurers with high exposure to MA like Humana and UnitedHealth.

    The big question is how much of this utilization will carry over into this year, and whether payers have properly accounted for utilization changes in their plan designs.

    Every major insurer besides Elevance expects to record a higher MLR in 2024 than in 2023. Though, the size of the growth ranges from a 0.8 percentage point increase for UnitedHealth to a 2.7 percentage point increase for Humana.

    The outlier, Elevance, expects its MLR to remain flat.

    In response to the challenging financial environment, payers — even those that excelled in controlling medical costs last year — said they’ve been pulling back benefits, raising premiums or exiting underperforming markets to boost profitability.

    That’s true for insurers that expect their MA membership to grow this year (UnitedHealth, CVS), and those that expect it to fall (Cigna) or stay flat (Elevance).

    As a result, further growth could be curtailed as payers prioritize margins.

    “We are first and foremost focused on recovering margin, and market share gains is a secondary consideration,” Brian Kane, who leads CVS’ health benefits division, told investors during its February earnings call.

    “I look at next year as a year that I think the whole industry will possibly reprice. I don’t know how the industry can take this kind of increase in utilization along with regulatory changes that will continue to persist in 2025 and 2026,” Humana CEO Bruce Broussard said on the payer’s earnings call.

    Insurers said they could revise plans further in light of MA rates for 2025 that the government proposed midway through the earnings reporting season. The rates represent a renewed effort by regulators to rein in growing spending in Medicare.

    Executives with Humana, Centene and CVS all said the payment changes are insufficient to cover cost trends. Humana and Centene said the rule would result in a 1.6% and 1.3% drop in rates, respectively. (That’s before risk scoring, which should result in an overall increase in reimbursement in 2025).

    Insurers warned regulators that seniors could see their benefits reduced if they finalize the rates as proposed.

    “We’ll just adjust the bids accordingly,” Asher said on Centene’s call. “The products may be a little less attractive for seniors from an industry standpoint if we don’t make a lot of progress on the final rates.”

    CVS slashes 2024 outlook — again — as Medicare seniors drive spending

    Runaway inpatient spending in particular caused CVS’ insurance costs to snowball after returning “to patterns we have not seen since the start of the pandemic,” its CFO said.

    Dive Brief:

    • CVS had a significantly worse first quarter than the healthcare giant — or Wall Street — expected, after its insurance arm failed to adequately prepare for seniors’ high use of medical care, especially in inpatient facilities.
    • The Rhode Island-based company’s health services segment — usually a reliable driver of growth — also saw its revenue and income fall in the quarter as its pharmacy benefit manager adjusted to the loss of a major contract with insurer Centene.
    • CVS slashed its earnings expectations for 2024 on Wednesday following the results. It’s the second time the company has lowered financial expectations this calendar year. “Clearly this is a disappointing result for us,” CFO Tom Cowhey said on a Wednesday call with investors, after which CVS’ stock fell more than 19%.

    Dive Insight:

    CVS brought in revenue of $88.4 billion in the quarter, up 4% year over year but significantly below analysts’ expectations. Net income was slashed by almost half compared to the prior-year quarter, to $1.1 billion.

    The quarter was “burdened by utilization pressures in Medicare Advantage,” CEO Karen Lynch said on the call.

    Starting last year, MA seniors began using higher levels of medical services after a long dry spell during the COVID-19 pandemic. The trend has continued into this year, leaving private insurers that manage the plans scrambling to contain costs.

    CVS assumed utilization would moderate somewhat coming into the first quarter, but instead it was “notably above” expectations, according to Lynch.

    Outpatient services, like mental health and medical pharmacy, along with supplemental benefits like dental continued to be elevated in the first quarter. However, inpatient utilization was particularly to blame for runaway spending.

    Inpatient admissions per thousand in the quarter were up “high-single digits” compared to the same time last year, Cowhey said. A small portion of the growth was expected due to implementation of the CMS’ two-midnight rule that’s resulted in insurers having to cover more inpatient admissions. But overall, admissions “meaningfully exceeded” expectations for the quarter, according to the CFO.

    “Inpatient seasonality returned to patterns we have not seen since the start of the pandemic,” Cowhey said.

    Executives stressed that some of those costs appear to be seasonal and shouldn’t carry into the rest of the year. Inpatient utilization patterns are similar to what CVS’ insurance arm Aetna saw in normal years before the COVID-19 pandemic, and appear to be moderating in April, according to Lynch.

    Still, the higher utilization caused the insurer’s medical loss ratio — a marker of spending on patient care — to soar to 90.4% in the first quarter, compared to 84.6% during the same time last year.

    Overall, medical costs in the quarter were about $900 million higher than CVS expected, Cowhey said.

    CVS’ results suggest the insurer “severely underestimated utilization of new members,” TD Cowen analyst Charles Rhyee wrote in a Wednesday morning note. “Investors already had lowered expectations for MA, but actual results and impact to guidance is likely way worse than expected.” 

    CVS added more MA members coming into 2024 than any other U.S. health insurer, according to an analysis by consultancy Chartis. That growth caused CVS’ membership to grow 1.1 million members in the first quarter compared to the end of 2023, to 26.8 million individuals.

    Revenue in CVS’ health benefits segment, which houses its insurer Aetna, subsequently inflated to $32.2 billion, up 21% compared to the fourth quarter of 2023.

    Despite the boom, higher medical costs slashed the segment’s operating income, as did the impact of lower quality ratings in MA.

    Lower quality or “star” ratings for 2024 cut steeply into CVS’ reimbursement. Aetna’s largest contract fell from 4.5 stars to 3.5 stars for 2024, causing the payer to lose out on about $800 million in revenue.

    As a result of the pressures, “we think [MA] will lose a significant amount of money this year,” Cowhey said.

    Following the quarter, CVS lowered its full-year financial expectations for earnings per share on a GAAP and adjusted basis, and for cash flow from operations.

    CVS expects to notch an MLR of 89.8% in 2024, up 2.1 percentage points from its previous guidance, because of continued medical utilization pressures, Cowhey said.

    Moving into 2025, CVS does expect to recover most of what it lost this year from the star ratings changes. But the insurer faces another setback: MA payment rates recently finalized for 2025 that insurers are slamming as a cut, despite only a modest decrease in base rates.

    On the call, Lynch maligned the rates as “insufficient” and a “significant added disruption” in the program.

    Like its other peers with major MA footprints, CVS plans to focus on improving profits at the potential expense of members. That includes hiking premiums and exiting counties where Aetna thinks it can’t improve profits in the near term. Aetna could lose members as a result, but the size of eventual losses will in large part depend on what the insurer’s competitors do, according to CVS executives.

    Other major MA payers have said they will take similar steps to hike profits.

    CVS also dealt with lower visibility into its claims in the quarter because of the massive cyberattack on claims clearinghouse Change Healthcare earlier this year. Change took its systems offline as a result, hamstringing providers’ payments across the U.S. and making it harder for insurers to predict how much they might have to spend on their members’ medical costs.

    CVS established a reserve of nearly $500 million for claims it estimates were lodged in the quarter but it has yet to receive. Cowhey said the insurer is “confident” about the adequacy of its reserves.

    Empowering healthcare providers against rising payer denials

    https://www.healthcaredive.com/spons/empowering-healthcare-providers-against-rising-payer-denials/712098

    In the rapidly evolving landscape of U.S. healthcare, the tug-of-war between payers and providers is continually intensifying, raising the stakes on the strategic maneuvers that shape the industry’s financial and operational dynamics.

    The crux of the issue lies in the increasingly sophisticated strategies employed by insurance companies to deny claims: a move that ostensibly aims to safeguard their bottom lines, often at the expense of provider sustainability and patient access.

    The rise in denial rates is more than a mere statistic; it’s a symptom of a broader systemic challenge that calls for strategic foresight and robust expertise. In this intricate environment, providers face numerous administrative challenges, working to balance clinical decisions with financial sustainability. 

    Drawn from in-depth proprietary analytics, clinical regulatory expertise and decades of experience, CorroHealth addresses what is needed to successfully combat payer denial tactics. Broader industry trends, such as the shift towards value-based care and the increasing emphasis on patient-centric models, will continue to disrupt the historic provider business model. CorroHealth’s insights offer a beacon for steering through these turbulent waters. Their strategic recommendations, from optimizing contract negotiations to leveraging data analytics to managing payer denials, to formalizing escalation paths, reflect a comprehensive approach to mitigating the adverse effects of ever-shifting payer denial tactics.

    Delving deeper into the anatomy of payer denials reveals a long-term pattern of deliberate complexity designed to wear down provider resilience. By dissecting the layers of denial management, from initial claim submission to final resolution, CorroHealth uncovers pivotal areas where targeted interventions dramatically shift outcomes in favor of healthcare providers.

    This process involves a granular analysis of denial codes, predictive analytics to pre-empt possible denials and rigorous training staff to maneuver through the intricate appeals process effectively. 

    Taking a proactive stance towards payer contract management, their approach emphasizes the importance of scrutinizing the fine print and negotiating terms that anticipate and mitigate denial strategies. CorroHealth advocates on the providers’ behalf for clearer definitions of medical necessity, timely filing limits and transparent appeal processes. By equipping providers with negotiation tactics grounded in comprehensive data analysis and a deep understanding of payer methodologies, their contracts become a tool for protection against denials, rather than a source of vulnerability.

    Woven throughout this work is CorroHealth’s commitment to advancing the dialogue between payers and providers toward a more equitable healthcare system. Through forums, partnerships and collaborative initiatives, CorroHealth bridges the gap between these two entities, fostering an environment where mutual understanding and respect pave the way for innovative solutions to longstanding challenges.

    Hospitals and health systems require an experienced partner to navigate the complexities of the healthcare landscape, balancing financial sustainability with top-tier patient care. CorroHealth offers a comprehensive suite of solutions to address challenges associated with payer denials, enabling providers to recover lost revenues and uphold the fundamental goal of accessible, high-quality patient care. Beyond financial strategies and operational adjustments, the narrative calls for a more productive and transparent dialogue between payers and providers. This aims to encourage an ecosystem where financial sustainability and high-quality patient care are complementary facets of holistic healthcare delivery.

    Facing these challenges, the importance of strategic partnerships becomes increasingly vital for healthcare providers. Such alliances are indispensable in maneuvering through the complex healthcare landscape and are strengthened by CorroHealth’s comprehensive understanding of the payer-provider dynamic and dedication to fostering innovation. A collaborative approach is essential for progressing towards a healthcare system characterized by greater equity and efficiency.

    The industry stands at an existential crossroads. The insights and strategies shared by CorroHealth serve as a testament to the company’s expertise and its dedication to shaping a future where healthcare is accessible, affordable and effective for all.