The great Medicare Advantage marketing scam: How for-profit health insurers convince seniors to enroll in private Medicare plans

https://wendellpotter.substack.com/p/the-great-medicare-advantage-marketing
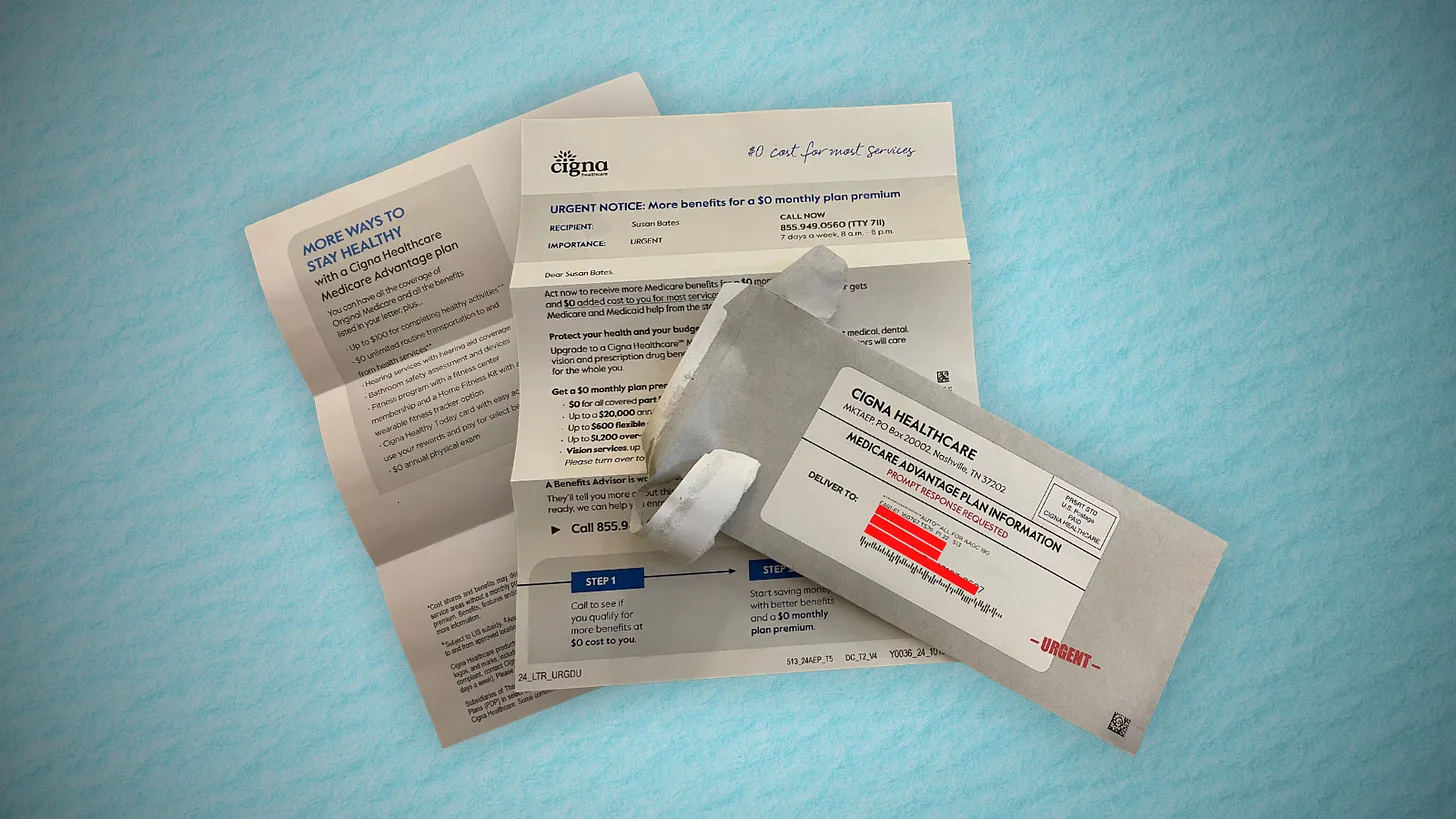
Jayne Kleinman is bombarded with Medicare Advantage promotions every open enrollment period — even though she has no interest in leaving traditional Medicare, which allows seniors to choose their doctors and get the care they want without interference from multi-billion-dollar insurance companies. 

“My biggest problem with being barraged is that so many of the ads were inaccurate,” Kleinman, a retired social services professional in New Haven County, Connecticut, told HEALTH CARE un-covered.

“They neglect to say that the amount of coverage you get is limited. They don’t talk about what you are losing by leaving traditional Medicare. It feels like insurance companies are manipulating us to get Medicare Advantage plans sold so that they can control the system, as opposed to treating us like human beings.” 

Seniors face a torrent of Medicare Advantage advertising: an analysis by KFF found 9,500 daily TV ads during open enrollment in 2022. A recent survey by the Commonwealth Fund found that 30% of seniors received seven or more phone calls weekly from Medicare Advantage marketers during the most recent open enrollment (Oct. 15 to Dec. 7) for 2024 coverage.

In 2023, a critical milestone was passed: over half of seniors are now enrolled in privatized Medicare Advantage plans. The marketing for these plans nearly always fails to mention how hard it is to return to traditional Medicare once you are in Medicare Advantage, and that the MA plans have closed provider networks and require prior authorization for medical procedures. Instead, the marketing emphasizes the fringe benefits offered by Medicare Advantage plans like gym memberships. 

U.S. Sen. Ron Wyden (D-Ore.), chairman of the Senate Finance Committee, criticized the widespread and predatory marketing of Medicare Advantage in a report in November 2022 and has continued to pressure the Biden administration to do more to address the problem. 

The report said that consumer complaints about Medicare Advantage marketing more than doubled from 2020 to 2021 to 41,000. It cites cases such as that of an Oregon man whose switch to Medicare Advantage meant he could no longer afford his prescription drugs, as well as a 94-year-old woman with dementia in a rural area who bought a Medicare Advantage plan that required her to obtain care miles further from her residence than she had to travel before. 

When open enrollment began last fall, it was “the start of a marketing barrage as marketing middlemen look to collect seniors’ information in order to bombard them with direct mail, emails, and phone calls to get them to enroll,” Wyden stated in a letter to the Centers for Medicare and Medicaid Services (CMS), which was signed by the other Democrats on the Senate Finance Committee. 

Just three weeks after Wyden sent the letter, CMS released a proposed rule reforming Medicare Advantage practices that the main lobby group for Medicare Advantage plans, the Better Medicare Alliance, endorsed. 

But key recommendations by Wyden were missing, including a ban on list acquisition by Medicare Advantage third-party marketing organizations, which includes brokers, and banning brokers that call beneficiaries multiple times a day for days in a row.

Among the prominent third-party marketing organizations is TogetherHealth, a subsidiary of Benefytt Technologies, which runs ads featuring former football star Joe Namath.

In August 2022, the Federal Trade Commission forced Benefytt to repay $100 million for fraudulent activities. The month before, the Securities and Exchange Commission levied more than $12 million in fines against Benefytt.

But CMS continues to allow Benefytt to work as a broker. Benefytt is owned by Madison Dearborn Partners, a Chicago-based private equity firm with ties to former Chicago mayor and current Ambassador to Japan Rahm Emanuel. Benefytt collects leads on potential customers, which they then sell to brokers and insurers to aggressively target seniors. CMS did not provide comment as to why they had not blocked Benefytt’s continuing work as a third-party marketing organization for Medicare. 

Two different rounds of rule-making on Medicare Advantage marketing in 2023 instead focused on such reforms as reining in exaggerated claims and excessive broker compensation. 

The enormous profits generated by Medicare Advantage plans — costing the federal government as much as $140 billion annually in overpayments to private companies — explains what drives the aggressive and often unethical marketing practices, said David Lipschutz, an associate director at the Center for Medicare Advocacy. 

“The fact is, there is an increasingly imbalanced playing field between Medicare Advantage and traditional Medicare,” he said. “Medicare Advantage is being favored in many ways. Medicare Advantage plans are paid more than what traditional Medicare spends on a given beneficiary.

Those factors combined with the fact that they generate such profits for insurance companies, leads to those companies doing everything they can to maximize enrollment.”

Adding to the problem, Lipschutz argued, was the enormous influence of the health insurance industry in Washington. Health insurers spent more than $33 million lobbying Washington in just the first three quarters of 2023 alone. 

“There is no real organized lobby for traditional Medicare, or organized advertising efforts,” he said. “During open enrollment, 80% of Medicare-related ads have to do with Medicare Advantage. We regularly encounter very well-educated and savvy folks who are tripped up by advertising and lured in by the bells and whistles. The deck is stacked against the consumer.”

Private equity firms have made a large investment in the Medicare Advantage brokerage and marketing sector, in addition to Madison Dearborn’s acquisition of Benefytt. Bain Capital, which Sen. Mitt Romney (R-Utah) co-founded, invested $150 million in Enhance Health, a Medicare Advantage broker, in 2021.

The CEO of EasyHealth, another private equity-backed brokerage, told Modern Healthcare in 2021 that “Insurance distribution is our Trojan horse into healthcare services.”

As federal law requires truth in advertising, a group of advocacy organizations–led by the Center for Medicare Advocacy, Disability Rights Connecticut, and the National Health Law Project–cited what they considered blatantly deceptive marketing by UnitedHealthcare to people who are eligible for both Medicare and Medicaid, in a complaint to CMS. 

UnitedHealthcare had purchased ads in the Hartford Courant asking seniors in large bold-faced type: “Eligible for Medicare and Medicaid? You could get more with UnitedHealthcare.” 

People who are eligible for both Medicare and Medicaid due to their income level are better off in traditional Medicare than Medicare Advantage given that Medicaid covers their out-of-pocket costs, meaning that they have wide latitude to choose their doctors, hospitals and medical procedures.

Sheldon Toubman, an attorney with Disability Rights Connecticut who worked to draft the complaint, framed the ad in the broader context of poor marketing practices by the Medicare Advantage industry. 

“I have been aware for a long time of basically fraudulent advertising in the MA insurance industry,” Toubman told HEALTH CARE un-covered. “There’s an overriding misrepresentation — they tell you how great Medicare Advantage is, and never the downsides. 

“There are two big downsides of going out of traditional Medicare:

They don’t tell you that you give up the broad Medicare provider network, which has nearly every doctor. And should you need expensive medical care in Medicare Advantage, you will learn there are prior authorization requirements. Traditional Medicare does almost no prior authorization, so you don’t have that obstacle. They don’t ever tell you any of that,” he said.

But it is marketing to dual-eligible individuals that is arguably the most problematic, Toubman argued. “They have Medicare and they are also low income. Because they are low-income, they also have Medicaid.

“Medicaid is a broader program — it covers a lot of things that Medicare doesn’t cover.

In Connecticut, 92,000 dual-eligible seniors have been ‘persuaded’ to sign up for Medicare Advantage. What’s outrageous about the marketing is they get you to sign up by offering extra services. … If you look at the ad in the Hartford Courant, it says you could get more, with the only real benefit being $130 per month toward food. But you now have this problem of a more limited provider network and prior authorization. UnitedHealth is doing false advertising.”

It’s a nationwide problem, Toubman said. “All insurers are doing this everywhere. We’re asking CMS and the Federal Trade Commission to conduct a nationwide investigation of this kind of problem. The failure to tell people that they give up their broader Medicare network — they don’t tell anybody that.”

For Jayne Kleinman, the unending ads are about one thing only: insurance industry profits. “Medicare Advantage has been strictly based on the people who make millions of dollars at the top of the company making more,” she said. “It’s all about money, not about you as an individual. Every time I saw an ad I’d get angry every single time — because I felt they were misleading people. The Medicare Advantage insurers are trying to scam people out of an interest of making money.”
How cognitive biases impact healthcare decisions

https://www.linkedin.com/pulse/how-cognitive-biases-impact-healthcare-decisions-robert-pearl-m-d–ti5qc/?trackingId=eQnZ0um3TKSzV0NYFyrKXw%3D%3D

Day one of the healthcare strategy course I teach in the Stanford Graduate School of Business begins with this question: “Who here receives excellent medical care?”

Most of the students raise their hands confidently. I look around the room at some of the most brilliant young minds in business, finance and investing—all of them accustomed to making quick yet informed decisions. They can calculate billion-dollar deals to the second decimal point in their heads. They pride themselves on being data driven and discerning.

Then I ask, “How do you know you receive excellent care?”

The hands slowly come down and room falls silent. In that moment, it’s clear these future business leaders have reached a conclusion without a shred of reliable data or evidence.

Not one of them knows how often their doctors make diagnostic or technical errors. They can’t say whether their health system’s rate of infection or medical error is high, average or low.

What’s happening is that they’re conflating service with clinical quality. They assume a doctor’s bedside manner correlates with excellent outcomes.

These often false assumptions are part of a multi-millennia-long relationship wherein patients are reluctant to ask doctors uncomfortable but important questions: “How many times have you performed this procedure over the past year and how many patients experienced complications?” “What’s the worst outcome a patient of yours had during and after surgery?”

The answers are objective predictors of clinical excellence. Without them, patients are likely to become a victim of the halo effect—a cognitive bias where positive traits in one area (like friendliness) are assumed to carry over to another (medical expertise).

This is just one example of the many subconscious biases that distort our perceptions and decision-making.

From the waiting room to the operating table, these biases impact both patients and healthcare professionals with negative consequences. Acknowledging these biases isn’t just an academic exercise. It’s a crucial step toward improving healthcare outcomes.

Here are four more cognitive errors that cause harm in healthcare today, along with my thoughts on what can be done to mitigate their effects:

Availability bias

You’ve probably heard of the “hot hand” in Vegas—a lucky streak at the craps table that draws big cheers from onlookers. But luck is an illusion, a product of our natural tendency to see patterns where none exist. Nothing about the dice changes based on the last throw or the individual shaking them.

This mental error, first described as “availability bias” by psychologists Amos Tversky and Daniel Kahneman, was part of groundbreaking research in the 1970s and ‘80s in the field of behavioral economics and cognitive psychology. The duo challenged the prevailing assumption that humans make rational choices.

Availability bias, despite being identified nearly 50 years ago, still plagues human decision making today, even in what should be the most scientific of places: the doctor’s office.

Physicians frequently recommend a treatment plan based on the last patient they saw, rather than considering the overall probability that it will work. If a medication has a 10% complication rate, it means that 1 in 10 people will experience an adverse event. Yet, if a doctor’s most recent patient had a negative reaction, the physician is less likely to prescribe that medication to the next patient, even when it is the best option, statistically.

Confirmation bias

Have you ever had a “gut feeling” and stuck with it, even when confronted with evidence it was wrong? That’s confirmation bias. It skews our perceptions and interpretations, leading us to embrace information that aligns with our initial beliefs—and causing us to discount all indications to the contrary.

This tendency is heightened in a medical system where physicians face intense time pressures. Studies indicate that doctors, on average, interrupt patients within the first 11 seconds of being asked “What brings you here today?” With scant information to go on, doctors quickly form a hypothesis, using additional questions, diagnostic testing and medical-record information to support their first impression.

Doctors are well trained, and their assumptions prove more accurate than incorrect overall. Nevertheless, hasty decisions can be dangerous. Each year in the United States, an estimated 371,000 patients die from misdiagnoses.

Patients aren’t immune to confirmation bias, either. People with a serious medical problem commonly seek a benign explanation and find evidence to justify it. When this happens, heart attacks are dismissed as indigestion, leading to delays in diagnosis and treatment.

Framing effect

In 1981, Tversky and Kahneman asked subjects to help the nation prepare for a hypothetical viral outbreak. They explained that if the disease was left untreated, it would kill 600 people. Participants in one group were told that an available treatment, although risky, would save 200 lives. The other group was told that, despite the treatment, 400 people would die. Although both descriptions lead to the same outcome—200 people surviving and 400 dying—the first group favored the treatment, whereas the second group largely opposed it.

The study illustrates how differently people can react to identical scenarios based on how the information is framed. Researchers have discovered that the human mind magnifies and experiences loss far more powerfully than positive gains. So, patients will consent to a chemotherapy regiment that has a 20% chance of cure but decline the same treatment when told it has 80% likelihood of failure.

Self-serving bias

The best parts about being a doctor are saving and improving lives. But there are other perks, as well.

Pharmaceutical and medical-device companies aggressively reward physicians who prescribe and recommend their products. Whether it’s a sponsored dinner at a Michelin restaurant or even a pizza delivered to the office staff, the intention of the reward is always the same: to sway the decisions of doctors.

And yet, physicians swear that no meal or gift will influence their prescribing habits. And they believe it because of “self-serving bias.”

In the end, it’s patients who pay the price. Rather than receiving a generic prescription for a fraction of the cost, patients end up paying more for a brand-name drug because their doctor—at a subconscious level—doesn’t want to lose out on the perks.

Thanks to the “Sunshine Act,” patients can check sites like ProPublica’s Dollars for Docs to find out whether their healthcare professional is receiving drug- or device-company money (and how much).

Reducing subconscious bias

These cognitive biases may not be the reason U.S. life expectancy has stagnated for the past 20 years, but they stand in the way of positive change. And they contribute to the medical errors that harm patients.

A study published this month in JAMA Internal Medicine found that 1 in 4 hospital patients who either died or were transferred to the ICU had been affected by a diagnostic mistake. Knowing this, you might think cognitive biases would be a leading subject at annual medical conferences and a topic of grave concern among healthcare professionals. You’d be wrong. Inside the culture of medicine, these failures are commonly ignored.

The recent story of an economics professor offers one possible solution. Upon experiencing abdominal pain, he went to a highly respected university hospital. After laboratory testing and observation, his attending doctor concluded the problem wasn’t serious—a gallstone at worst. He told the patient to go home and return for outpatient workup.

The professor wasn’t convinced. Fearing that the medical problem was severe, the professor logged onto ChatGPT (a generative AI technology) and entered his symptoms. The application concluded that there was a 40% chance of a ruptured appendix. The doctor reluctantly ordered an MRI, which confirmed ChatGPT’s diagnosis.

Future generations of generative AI, pretrained with data from people’s electronic health records and fed with information about cognitive biases, will be able to spot these types of errors when they occur.

Deviation from standard practice will result in alerts, bringing cognitive errors to consciousness, thus reducing the likelihood of misdiagnosis and medical error. Rather than resisting this kind of objective second opinion, I hope clinicians will embrace it. The opportunity to prevent harm would constitute a major advance in medical care.

Two Lawsuits. Two Issues. One Clear Message.

Last Monday, two lawsuits were filed that strike at a fundamental challenge facing the U.S. health system:

In the District Court of NJ, a class action lawsuit (ANN LEWANDOWSKI v THE PENSION & BENEFITS COMMITTEE OF JOHNSON AND JOHNSON) was filed against J&J alleging the company had mismanaged health benefits in violation of the Employee Retirement Income Security Act (“ERISA”). As noted in the 74-page filing “This case principally involves mismanagement of prescription-drug benefits. “Over the past several years, defendants breached their fiduciary duties and mismanaged Johnson and Johnson’s prescription-drug benefits program, costing their ERISA plans and their employees millions of dollars in the form of higher payments for prescription drugs, higher premiums, higher deductibles, higher coinsurance, higher copays, and lower wages or limited wage growth… Defendants’ mismanagement is most evident in (but not limited to) the prices it agreed to pay one of its vendors—its Pharmacy Benefits Manager (“PBM”)—for many generic drugs that are widely available at drastically lower prices.”

The issue is this: what liability risk does a self-insured employer have in providing health benefits to their employees?

Is the structure of the plan, the selection of providers and vendors, and costs and prices experienced by employees subject to litigation? What’s the role of the employer in protecting employees against unnecessary costs?

On the same day, in the District Court of Eastern Wisconsin, an 85-page class action lawsuit was filed against Advocate-Aurora Health (AAH) claiming it “uses its market power to raise prices, limit competition and harm consumers in Wisconsin:

  • Forces commercial health plans to include all its “overpriced facilities” in-network even when they would prefer to include only some facilities.
  • Goes to “extreme efforts to drive out innovative insurance products that save commercial health plans and their members money.”
  • Suppresses competition through “secret and restrictive contract terms that have been the subject of bipartisan criticism.”
  • Acquires new facilities, which then allows it to raise prices due to reduced competition

… without intervention, the health system will continue to use “anticompetitive contracting and negotiating tactics to raise prices on Wisconsin commercial health plans and their members and use those funds for aggressive acquisitions and executive compensation.”

The issue is this: is a health system’s liable when its consolidation activities result in higher prices for services provided communities and employers in communities where they operate?

Is there a direct causal relationship between a system’s consolidation activities and their prices, and how should alleged harm be measured and remedied?

Two complicated issues for two reputable mega-players in the U.S. health system. Both lawsuits were brought as class actions which guarantees widespread media attention and a protracted legal process. And each contributes directly to the gradual erosion of public trust in the health system since the plaintiffs essentially claim the business practices of J&J and Advocate-Aurora willfully harm the individuals they pledge to serve.

In the November 2023 Keckley Poll, I asked the sample of 817 U.S. adults to assess the health system overall. The results were clear:

  • 69% think the system is fundamentally flawed and in need of major change vs. 7% who think otherwise.
  • 60% believe it puts its profits above patient care vs. 13% who disagree.
  • 74% think price controls are needed vs. 7% who disagree.
  • 83% believe having health insurance that’s ‘affordable and comprehensive’ is essential to financial security vs 3% who disagree.
  • 52% feel confident in their ability to navigate the U.S. system “when I have a problem” vs. 32% who have mixed feelings and 16% who aren’t.
  • And 76% think politicians avoid dealing with healthcare issues because they’re complex and politically risky vs/ 6% who think they tackle them head-on.

The poll also asked their level of trust and confidence in five major institutions “to develop a plan for the U.S. health system that maximizes what it has done well and corrects its major flaws.”

Clearly, trust and confidence in the health system is low, and expectations about solutions fall primarily on hospitals and doctors. Lawsuits like these widen suspicion that the industry’s dominated first and foremost by Big Businesses focused on their own profitability before all else. And they pose particular problems for sectors in healthcare dominated by not-for-profit and public ownership i.e. hospitals, home care, public health agencies and others.

My take

These lawsuits address two distinct issues: the roles of employers in designing their health benefits for employees including the use of PBMs, and the justification for consolidation of hospital and ancillary services in markets. 

But each lawsuit s predicated on a legal theory that prices set by organizations are geared more to corporate profits than public good and justifiable costs.

Pricing is the Achilles of the health system. Pushback against price transparency by some, however justified, has amplified exposure to litigation risk like these two  and contributed to the public’s loss of trust in the system.

It is unlikely greater price transparency and business practice disclosures by J&J and Advocate-Aurora could have avoided these lawsuits, but it’s clearly a message that needs consideration in every organization.

Healthcare organizations and their trade groups can no longer defend against lack of transparency by defaulting to the complexity of our supply chains and payment systems. They’re excuses. The realities of generative AI and interoperability assure information driven healthcare that’s publicly accessible and inclusive of prices, costs, outcomes and business practices. In the process, the public’s interest will heighten and lawsuits will increase.

P.S. Nashville is known as a hot spot for healthcare innovation including transparency solutions. Check out this meeting February 29: https://www.eventbrite.com/e/leaping-into-the-future-of-healthcare-2024-insights-tickets-809310819447

Resources

Lawsuit 119120873885 (documentcloud.org)

Microsoft Word – Aurora Class Action Complaint (FINAL filed Feb. 5 2024) (aboutblaw.com) February 5, 2024

Is the Tax Exemption for Not-for-Profit Hospitals at Risk?

Last Thursday, Seattle-based Providence Health System announced it is refunding nearly $21 million in medical bills paid by low-income residents of Washington and erasing $137 million more in outstanding debt for others. Other systems are likely to follow as pressure con mounts on large, not-for-profit systems to modify their business practices in sensitive areas like patient debt collection, price transparency, executive compensation, investment activities and others.

Not-for profit systems control the majority of the 2,987 nongovernment not-for-profit community hospitals in the U.S. Some lawmakers think it’s time to revisit to revisit the tax exemption. It has the attention of the American Hospital Association which lists “protecting not-for-profit hospitals’ the tax-exempt status” among its 15 Advocacy Priorities in 2024 (it was not on their list in 2023).

Background:  Per a recent monograph in Health Affairs: “The Internal Revenue Service (IRS) uses the Community Benefit Standard (CBS), a set of 10 holistically analyzed metrics, to assess whether nonprofit hospitals benefit community health sufficiently to justify their tax-exempt status. Nonprofit hospitals risk losing their tax exemption if assessed as underinvesting in improving community health. This exemption from federal, state, and local property taxes amounts to roughly $25 billion annually.

However, accumulating evidence shows that many nonprofit hospitals’ investments in community health meet the letter, but not the spirit, of the CBS.

Indeed, a 2021 study showed that for every $100 in total expenses nonprofit hospitals spend just $2.30 on charity care (a key component of community benefit)—substantially less than the $3.80 of every $100 spent by for-profit hospitals. A 2022 study looked at the cost of caring for Medicaid patients that goes unreimbursed and is therefore borne by the hospital (another key component of community benefit); the researchers found that nonprofit hospitals spend no more than for-profit hospitals ($2.50 of every $100 of total expense).”

In its most recent study, the AHA found the value of CBS well-in-excess of the tax exemption by a factor of 9:1. But antagonism toward the big NFP systems has continued to mount and feelings are intense…

  • Insurers think NFP systems exist to gain leverage in markets & states over insurers in contract negotiations and network design. They’ll garner support from sympathetic employers and lawmakers, federal anti-consolidation and price transparency rulings and in the court of public opinion where frustration with the system is high.
  • State officials see the mega- NFP systems as monopolies that don’t deserve their tax exemptions while the state’s public health, mental health and social services programs struggle.
  • Some federal lawmakers think the NFP systems are out of control requiring closer scrutiny and less latitude. They think the tax exemption qualifiers should be re-defined, scrutinized more aggressively and restricted.
  • Well-publicized investments by NFP systems in private equity backed ventures has lent to criticism among labor unions and special interests that allege systems have abandoned community health for Wall Street shareholders.
  • Investor-owned multi-hospital operators believe the tax exemption is an unfair advantage to NFPs while touting studies showing their own charity care equivalent or higher.
  • Other key NFP and public sector hospital cohorts cry foul: Independent hospitals, academic medical centers, safety-net (aka ‘essential’) hospitals, rural health clinics & hospitals, children’s hospitals, rural health providers, public health providers et al think they get less because the big NFPs get more.
  • And the physicians, nurses and workforces employed by Big NFP systems are increasingly concerned by systemization that limits their wages, cuts their clinical autonomy and compromises their patients’ health.

My take:

The big picture is this: the growth and prominence of multi-hospital systems mirrors the corporatization in most sectors of the economy: retail, technology, banking, transportation and even public utilities. The trifecta of community stability—schools, churches and hospitals—held out against corporatization, standardization and franchising that overtook the rest. But modernization required capital, the public’s expectations changed as social media uprooted news coverage and regulators left doors open for “new and better” that ceded local control to distant corporate boards.

Along the way, investor-owned hospitals became alternatives to not-for-profits, and loose networks of hospitals that shared purchasing and perhaps religious values gave way to bigger multi-state ownership and obligated groups.

The attention given large NFP hospital systems like Providence and others is not surprising. These brands are ubiquitous. Their deals with private equity and Big Tech are widely chronicled in industry journalism and passed along in unfiltered social media. And their collective financial position seems strong:  Moody’s, Fitch, Kaufman Hall and others say utilization has recovered, pandemic recovery is near-complete and, despite lingering concerns about workforce issues, growth in their core businesses plus diversification in new businesses are their foci. (See Hospital Section below).

I believe not-for-profit hospital systems are engines for modernizing health delivery in communities and a lightening rod for critics who think their efforts more self-serving than for the public good.

Most consumers (55%) think they earn their tax exemption but 34% have mixed feelings and 10% disagree. (Keckley Poll November 20, 2023). That’s less than a convincing defense.

That’s why the threat to the tax exemption risk is real, and why every organization must be prepared. Equally important, it’s why AHA, its state associations and allies should advance fresh thinking about ways re-define CBS and hardwire the distinction between organizations that exist for the primary purpose of benefiting their shareholders and those that benefit health and wellbeing in their communities.

PS: Must reading for industry watchers is a new report from by Health Management Associates (HMA) and Leavitt Partners, an HMA company, with support from Arnold Ventures. The 70-page report provides a framework for comparing the increasingly crowned field of 120 entities categorized in 3 groups: Hybrids (6.9 million), Delivery (5.8 million) and Enablers 17.5 million

“At the start of the movement, value-based arrangements primarily involved traditional providers and payers engaging in relatively straight-forward and limited contractual arrangements. In recent years, the industry has expanded organically to include a broader ecosystem of risk-bearing care delivery organizations and provider enablement entities with capabilities and business models aligned with the functions and aims of accountable care…Inclusion criteria for the 120 VBD entities included in this analysis were:

  • 1-Serve traditional Medicare, MA, and/or Medicaid populations. Entities that are focused solely on commercial populations were excluded
  • 2-Operate in population-based, total cost of care APMs—not only bundled payment models.
  • 3- Focus on primary care and/or select specialties that are relevant to total cost of care models (i.e., nephrology, oncology, behavioral health, cardiology, palliative care). Those exclusively focused on specialty areas geared toward episodic models (e.g., MSK) were excluded. –
  • 4-Share accountability for cost and quality outcomes. Business models must be aligned with provider performance in total cost of care arrangements. Vendors that support VBP but do not share accountability for outcomes were excluded.

HMA_VBP-Entity-Landscape-Report_1.31.2024-updated.pdf (healthmanagement.com) February 2024

Three Must-Haves for Every Rating Presentation

Creating a great rating agency presentation is imperative to telling your story. I’ve probably seen a thousand presentations across the past three decades and I can say without a doubt that a great presentation will find its way into the rating committee. Show me a crisp, detailed, well-organized presentation, and I’ll show you a ratings analyst who walks away with high confidence that the management team can navigate the industry challenges ahead.

During the pandemic, Kaufman Hall recommended that hospitals move financial performance to the top of the presentation agenda. Better presentations chronicled the immediate, “line item by line item” steps management was taking to stop the financial bleeding and access liquidity. We still recommend this level of detail in your presentations, but as many hospitals relocate their bottom line, management teams are now returning to discussing longer-term strategy and financial performance in their presentations.

Beyond the facts and figures, many hospitals ask me what the rating analysts REALLY want to know. Over those one thousand presentations I’ve seen, the presentations that stood out the most addressed the three themes below:

  1. What makes your organization essential? Hospitals maintain limited price elasticity as Medicare and Medicaid typically comprise at least half of patient service revenue, leaving only a small commercial slice to subsidize operations. The ability to negotiate meaningful rate increases with payers will largely rest on the ability to prove why the hospital is a “must-have” in the network. In other words, a health plan that can’t sell a product without a hospital in its network is the definition of essential. This conversation now also includes Medicare Advantage plans as penetration rates increase rapidly across the country. Essentiality may be demonstrated by distinct services, strong clinical outcomes and robust medical staff, multiple access points across a certain geography, or data that show the hospital is a low-cost alternative compared to other providers. Volume trends, revenue growth, and market share show that essentiality. A discussion on essentiality is particularly needed for independent providers who operate in crowded markets.
  2. What makes your financial performance durable? Many hospitals are showing a return to better performance in recent quarters. Showing how your organization will sustain better financial results is important. Analysts will want to know what the new “run rate” is and why it is durable. What are the undergirding factors that make the better margins sustainable? Drivers may include negotiated rate increases from commercial payers and revenue cycle improvements. On the expense side, a well-chronicled plan to achieve operating efficiencies should receive material airtime in the presentation, particularly regarding labor. It is universally understood that high labor costs are a permanent, structural challenge for hospitals, so any effort to bend the labor cost curve will be well received. Management should also isolate non-recurring revenue or expenses that may drive results, such as FEMA funds or 340B settlements. To that end, many states have established new direct-to-provider payment programs which may be meaningful for hospitals. Expect questions on whether these funds are subject to annual approval by the state or CMS. The analysts will take a sharpened pencil to a growing reliance on these funds. 

    The durability of financial performance should be represented with highly detailed multi-year projections complete with computed margin, debt, and liquidity ratios. Know that analysts will create their own conservative projections if these are not provided, which effectively limits your voice in the rating committee. 

    We also recommend that hospitals include a catalogue of MTI and bank covenants in the presentation. Complying with covenants are part of the agreement that hospitals make with their lenders, and it is the organization’s responsibility to report how it’s performing against these covenants. General philosophy on headroom to covenants also provides insight to management’s operating philosophy. For example, is it the organization’s goal to have narrow, adequate, or ample headroom to the covenants and why? As the rating agencies will tell you, ratings are not solely based on covenant performance, but all rating factors influence your ability to comply with the covenants.
  3. What makes your capital plan affordable? Every rating committee will ask what the hospital’s future capital needs are and how those capital needs will be supported by cash flow, also known as “capital capacity.” To answer that question, a hospital must understand what it can afford, based on financial projections. Funding sources may require debt, which requires a debt capacity analysis with goals on debt burden, coverage, and liquidity targets. Over the years, better presentations explain the organization’s capital model, outline the funding sources, and discuss management’s tolerance for leverage.

There is always a lot to cover when meeting with the rating agencies and a near endless array of metrics and indicators to provide. As I’ve written before, how you tell the story is as important as the story itself. If you can weave these three themes throughout the presentation, then you will have a greater shot at having your best voice heard in rating committee.



