Health systems risk being reduced to their core

https://mailchi.mp/9b1afd2b4afb/the-weekly-gist-december-1-2023?e=d1e747d2d8
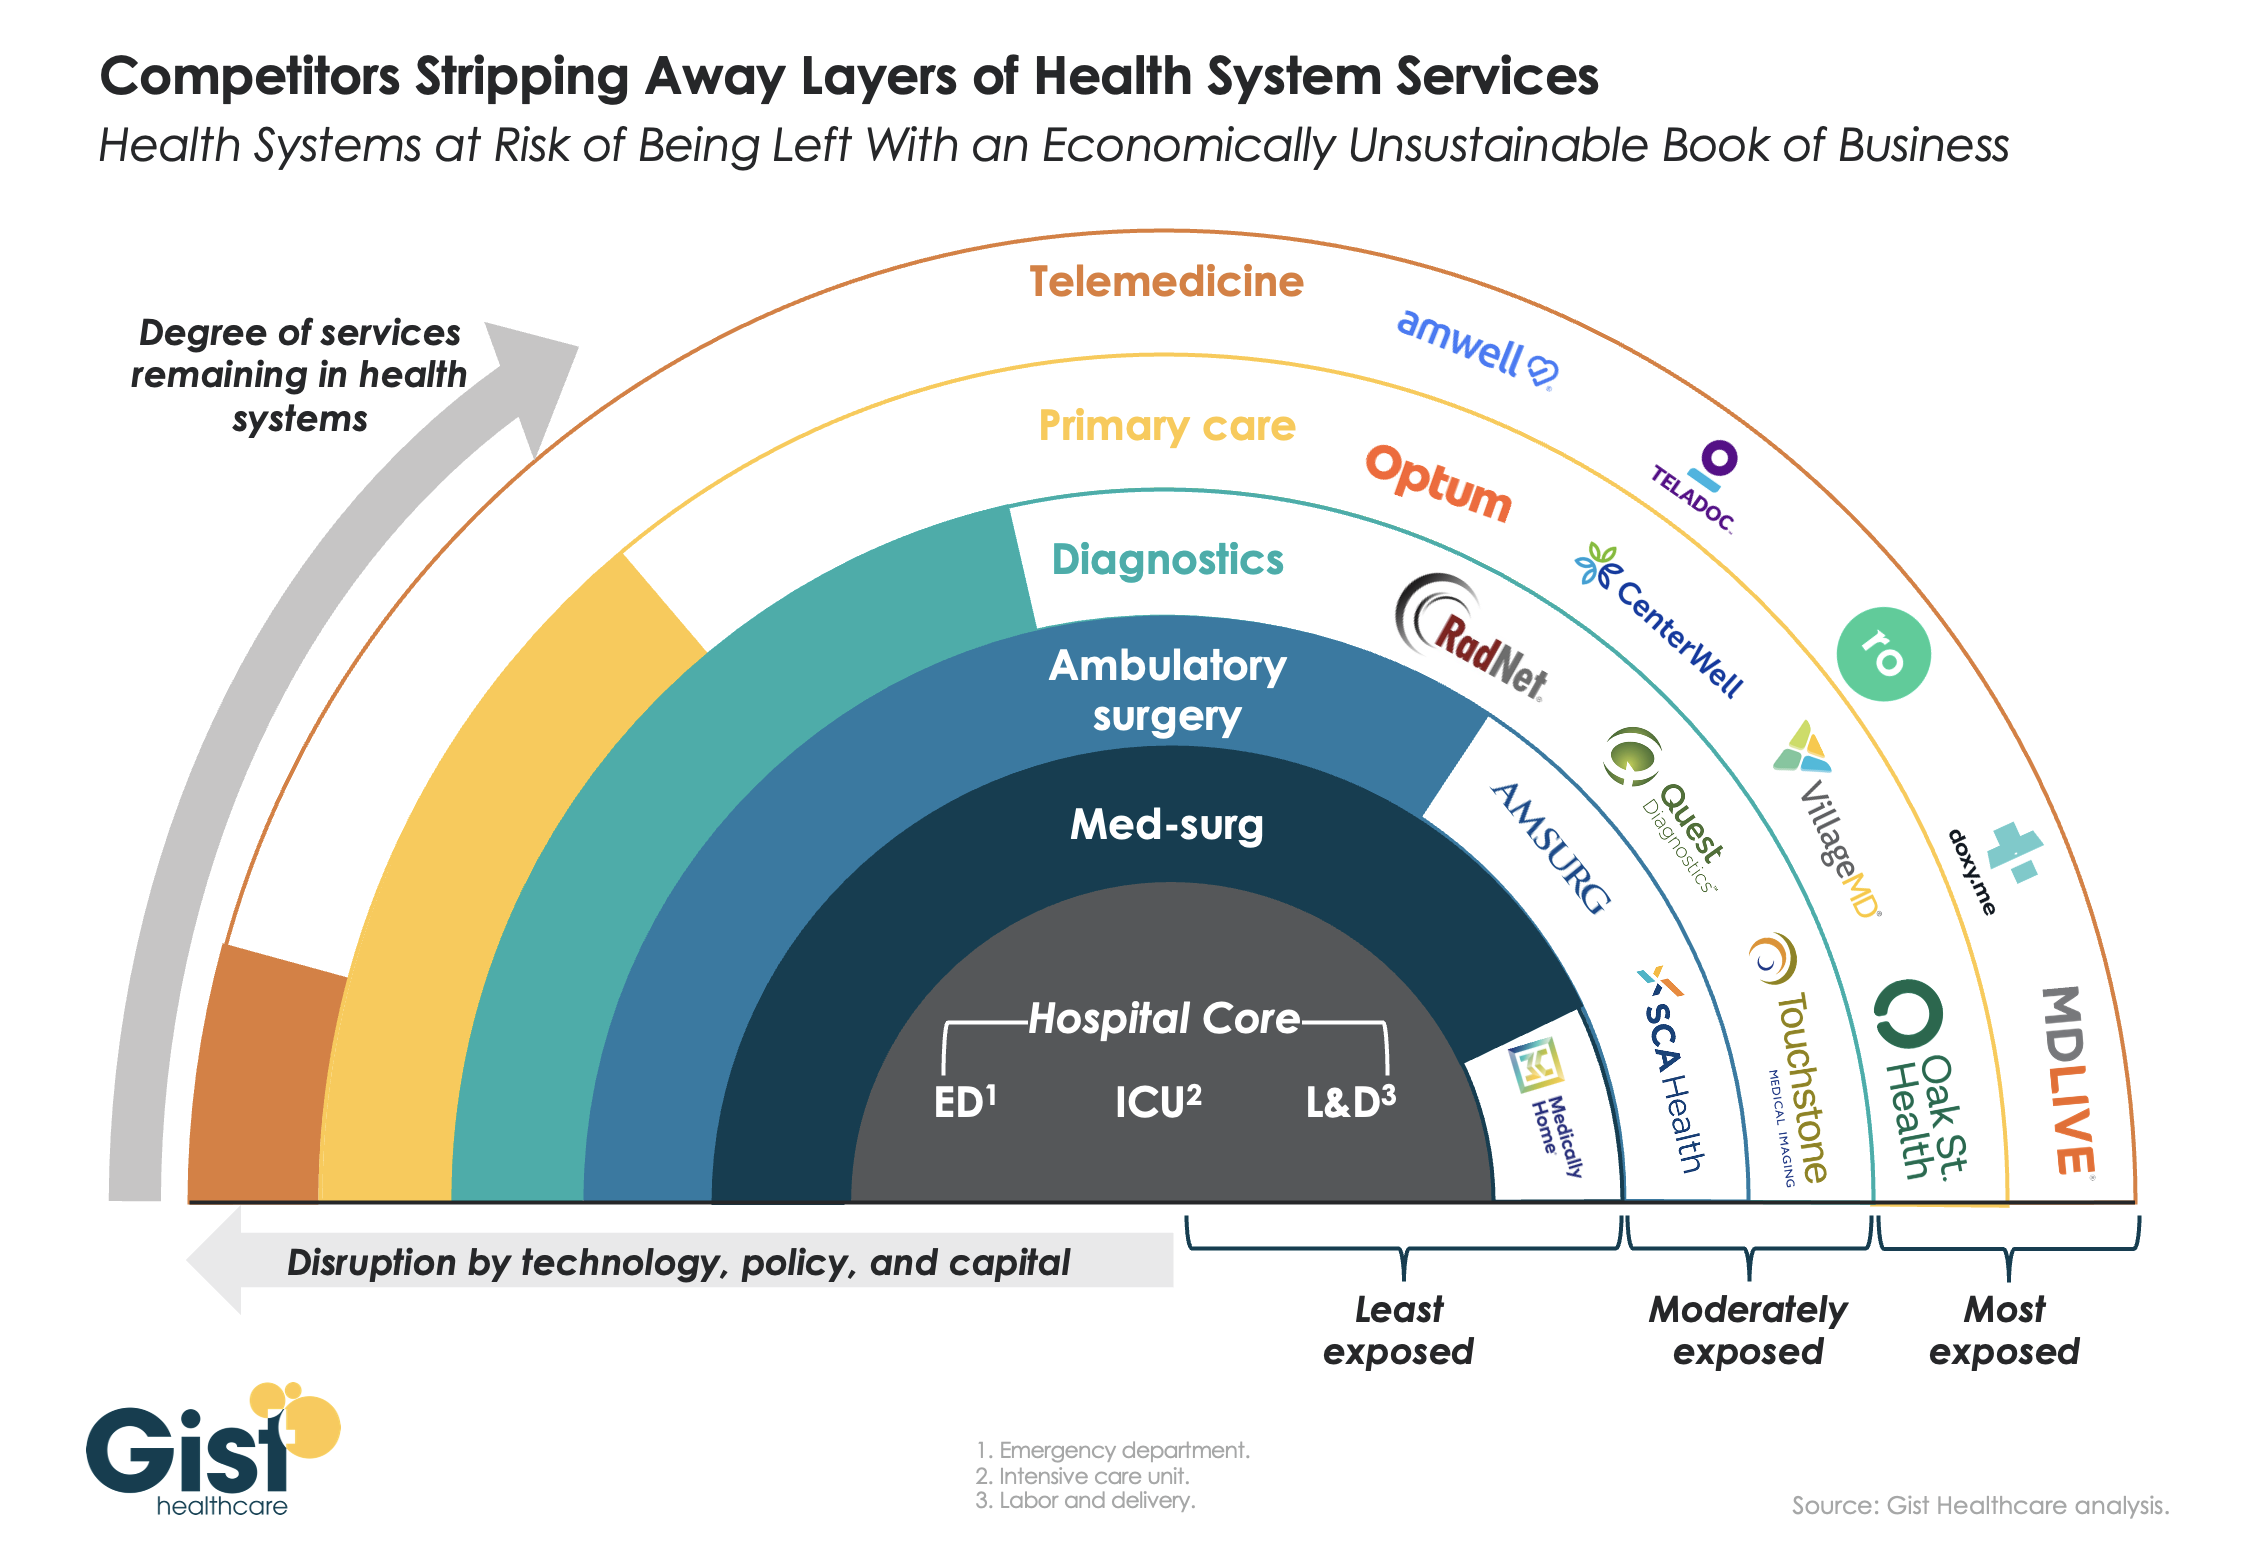
This week’s graphic features our assessment of the many emerging competitive challenges to traditional health systems.

Beyond inflation and high labor costs, health systems are struggling because competitors—ranging from vertically integrated payers to PE-backed physician groups—are effectively stripping away profitable services and moving them to lower-cost care sites. The tandem forces of technological advancement, policy changes, and capital investment have unlocked the ability of disruptors to enter market segments once considered safely within health system control. 

While health systems’ most-exposed services, like telemedicine and primary care, were never key revenue sources (although they are key referral drivers), there are now more competitors than ever providing diagnostics and ambulatory surgery, which health systems have relied on to maintain their margins. 

Moving forward, traditional systems run the risk of being “crammed down” into a smaller portfolio of (largely unprofitable) services: the emergency department, intensive care unit, and labor and delivery. 

Health systems cannot support their operations by solely providing these core services, yet this is the future many will face if they don’t emulate the strategies of disruptors by embracing the site-of-care shift, prioritizing high-margin procedures, rethinking care delivery within the hospital, and implementing lower-cost care models that enable them to compete on price.

Higher-risk patients paying more for colonoscopies

https://mailchi.mp/9b1afd2b4afb/the-weekly-gist-december-1-2023?e=d1e747d2d8

Published this week in Stat, this article explores the confusing payment landscape patients must navigate when receiving colonoscopies. While the Affordable Care Act requires that preventative care services be covered without cost-sharing, this only applies to the “screening” colonoscopies that low-risk patients are recommended to get every ten years.

But when procedures are performed at more frequent intervals for higher-risk patients, they are called “surveillance” or “diagnostic” colonoscopies, for which patients have no guarantees of cost-sharing protections, despite being essentially the same procedure, done for the same purpose.

If a gastroenterologist finds and excises one or more precancerous polyps during a screening colonoscopy, the procedure can leave the patient—especially one with a high deductible health plan—with a large, unexpected bill. 

The Gist: Against the backdrop of a sharp rise in colorectal cancer rates among US adults under 65, articles like this are a frustrating demonstration of how insurance incentive structures can work against optimal care delivery. 

Incentives should be carefully designed such that proven, preventative screenings—at the discretion of their doctor—are widely available to patients with minimal financial barriers. Surely, no one is “choosing” to have an “unnecessary” colonoscopy—as the procedure is notoriously disliked by patients. 

BJC-Saint Luke’s $10B merger expected to close soon

https://mailchi.mp/9b1afd2b4afb/the-weekly-gist-december-1-2023?e=d1e747d2d8

After signing a letter of intent in late May, St. Louis, MO-based BJC HealthCare and Kansas City, MO-based Saint Luke’s Health System announced on Wednesday that they have signed a definitive merger agreement, having received the necessary regulatory approvals. 

Based on opposite sides of the “Show-Me State,” the systems’ markets do not directly overlap. The merger, expected to close on Jan. 1, 2024, will create a $10B revenue, 28-hospital system spanning Missouri, southern Illinois, and eastern Kansas. The two systems plan to retain their respective brands and will be dually headquartered in St. Louis and Kansas City. 

The Gist: BJC and Saint Luke’s are following in the footsteps of other recent mergers involving large health systems with no geographic overlap, which regulators have allowed to move forward. However, recent history shows there’s more to closing a deal than just passing regulatory muster. 

Both the Sanford-Fairview and UnityPoint-Presbyterian mergers were called off earlier this year for non-regulatory reasons, including the concerns of local stakeholders.

Given the difficult financial environment and the growing threat of vertically integrated payers, health systems looking to pursue scale strategies must ensure they will actually realize the promise these combinations may hold.

UnitedHealth Group’s Optum grows to 90K employed or affiliated physicians

https://mailchi.mp/9b1afd2b4afb/the-weekly-gist-december-1-2023?e=d1e747d2d8

At UnitedHealth Group’s (UHG’s) 2023 investor conference, Optum Health CEO Amar Desai, MD, revealed that Optum has added nearly 20K physicians in 2023, bringing its total physician count to nearly 90K.

None of these acquisitions were formally disclosed, including this year’s largest known pickup, Crystal Run Healthcare—a Middletown, NY-based group with over 400 doctors—which only became public after an internal email was shared with the press. Optum was already the nation’s largest employer of physicians by far, and its nearly 30 percent growth in 2023 only extends its lead.

The next two largest physician employers, Ascension and HCA Healthcare, manage a combined total of around 100K. Optum also employs or affiliates with an additional 40K advanced practice clinicians.

The Gist: Optum’s physician acquisition binge continues at a stunning pace: it has tripled its physician ranks since 2017, and now controls nearly 10 percent of all physicians in the US. But now that it has amassed a veritable physician army, there are emerging signs that it’s turning attention to right-sizing and rationalizing this massive portfolio. 

Recent layoffs at the Everett Clinic and the Polyclinic in greater Seattle suggest an end to Optum’s more hands-off initial approach to integration. While each of Optum’s myriad medical group acquisitions has been too small, relative to total company revenue, to trigger regulatory review, the proposed updates to federal merger reporting requirements could put a damper on its unfettered provider buying spree.   

Cigna and Humana reportedly engaged in merger talks

https://mailchi.mp/9b1afd2b4afb/the-weekly-gist-december-1-2023?e=d1e747d2d8

According to a Wall Street Journal exclusive published this Wednesday, Bloomfield, CT-based Cigna and Louisville, KY-based Humana, two of the nation’s largest health insurers, are exploring a merger that could close as soon as the end of this year.

With Cigna valued at around $83B and Humana at roughly $62B, their potential combination would be the largest domestic merger of the year, not just in healthcare, but across all industries.

According to anonymous insiders, the companies are discussing a cash-and-stock deal, but nothing has been finalized. Should an agreement be reached, the merger is expected to receive close attention from antitrust authorities. Both Humana and Cigna have attempted to merge with rival insurers over the past decade, only to see the deals blocked on antitrust grounds.

The Gist: This would be a blockbuster deal, putting the combined entity on par with CVS Health and UnitedHealth Group. 

Though Cigna and Humana have relatively little direct overlap in their health insurance businesses—Humana recently announced it will exit the commercial group business to focus on its more successful Medicare Advantage (MA) offerings and Cigna, mostly a commercial insurer, is reportedly shopping its much smaller MA business—their respective pharmacy benefit managers (PBMs) may be an antitrust sticking point. (By market share, Cigna’s Express Scripts is the second-largest PBM, while Humana’s CenterWell Pharmacy is fourth.)

Given the Biden administration’s focus on targeting potentially anticompetitive healthcare mergers, as well as rising Congressional scrutiny around PBMs, this potential merger is sure to face many hurdles prior to closing.






