Renton, Wash.-based Providence has reported a $345 million operating loss in the first quarter on revenue of $6.8 billion.
While revenues were up on the same period in 2022, expenses also rose 5.1 percent to total $7.1 billion. The operating loss compares with a $510 million loss in the first quarter of 2022.
Improving non-operating income, mainly from investment returns, helped mitigate the net loss to $117 million compared with an $840 million net loss in the same period last year, excluding the disaffiliation of Newport Beach, Calif.-based Hoag.
The 51-hospital system reiterated it is taking a number of initiatives to reduce some of its costs under its Destination Health 2025 Recover and Renew plan. One of those prime areas of focus is reducing staffing costs, particularly in regard to contract labor, which continues to be a challenge for Providence.
“With current labor shortages, the use of premium labor, including the number and wage rate of agency nurses, continues to be significantly higher than in previous years,” management said in its filing. “Several initiatives are underway to reduce those expenses in combination with increasing core productivity.”
Providence is also undergoing portfolio management reassessment to try and improve efficiencies and save costs, according to the filing.
The system, which had $7.8 billion long-term debt as of March 31, provided $563 million in community benefit in the first quarter, up from $412 million in the same period of 2022.
“Together, we will continue meeting the health care needs of our communities, no matter how challenging the environment gets, and will ensure the mission of Providence thrives for years to come,” Rod Hochman, MD, Providence president and CEO said in the filing.
In the mid-1980’s, managed care advocate Dr. Paul Ellwood predicted that eventually, US healthcare would be dominated by perhaps a dozen vast national firms he called SuperMeds that would combine managed care based health insurance with care delivery systems. Ellwood was a leader of the “managed competition” movement which advocated for a private sector alternative to a federal government-run National Health Insurance system. Ellwood and colleagues believed that Kaiser Foundation Health Plans and other HMOs would be able to stabilize health costs and thus affordably extend care to the uninsured.
The US political system and market dynamics would not co-operate with Ellwood and his Jackson Hole Group’s vision. In the ensuing thirty-five years, healthcare has remained both highly fragmented and regional in focus. However, unbeknownst to most, during the past decade, as a result of a major merger and relentless smaller acquisitions, two SuperMeds were born- CVS/Aetna and UnitedHealth Group, that whose combined revenues comprise 14% of total US health spending.
CVS/Aetna is slightly larger than United, by dint of grocery sales in its drugstores and its vast Caremark pharmacy benefits management business. However, CVS’s Aetna health insurance arm is one third the size of United’s, and though CVS is rapidly scaling up its care delivery apparatus through its in-store Health Hubs, it remains is a tiny fraction of United’s care footprint. Despite being slightly smaller at the top line, United’s market capitalization is more than 3.5 times that of CVS.
United’s vast scope is difficult to comprehend because much of it is not visible to the naked eye, and the most rapidly growing businesses are partly nested inside United’s health insurance business.
United employs over 300 thousand people. At $287.6 billion total revenues in 2021, United exceeded 7% of total US health spending (though $8.3 billion are from overseas operations).
In 2021, United was $100 billion larger than the British National Health Service. It is more than three times the size of Kaiser Permanente, and five times the size of HCA, the nation’s largest hospital chain. United is both larger and richer than energy giant Exxon Mobil. United has over $70 billion in cash and investments, and is generating about $2 billion a month in operating cash flow.
Its highly regulated health insurance business is the visible tip of a rapidly growing iceberg. Revenue from United’s core health insurance business grew at 11% in 2021, compared to 14% growth in United’s diversified Optum subsidiary. Optum generated $155.6 billion in 2021 (of which 60% were from INSIDE United’s health insurance business). You can see the relationship of Optum’s three major businesses to United’s health insurance operations in Exhibit I.
Optum is the Key to United’s Growth
Understanding the role of Optum is key to understanding United’s business. It is remarkable how few of my veteran health care colleagues have any idea what Optum is or what it does. Optum was once a sort of dumping ground for assorted United acquisitions without a seeming core purpose. A private equity colleague once derided Optum as “The Island of Lost Toys”. Now, however, Optum is driving United’s growth, and generates billions of dollars in unregulated profits both from inside the highly regulated core health insurance business and from external customers.
Optum consists of three parts:Optum Health, its care delivery enterprise ($54 billion revenues in 2021), Optum Rx, its pharmacy benefits management enterprise ($91 billion revenues in 2021) and Optum Insight, a diversified business services enterprise ($12.2 billion in 2021). Virtually all of United’s acquisitions join one of these three businesses.
Optum Health: The Third Largest Care Delivery Enterprise in the US
By itself, Optum Health is almost the size of HCA ($54 billion in 2021 vs HCA’s $58.7 billion) and consists of a vast national portfolio of care delivery entities: large physician groups, urgent care centers, surgicenters, imaging centers, and now by dint of the recently announced $5.7 billion acquisition of LHC, home health agencies. Optum Health has studiously avoided acquiring beds of any kind: hospitals, nursing homes, etc. and likely will continue to do so. Optum Health’s physician groups not only generate profits on their own, but also provide powerful leverage for United to control health costs for its own subscribers, pushing down United’s highly visible and regulated Medical Loss Ratio (MLR), and increasing health plan profits.
Optum Health began in 2007 when United acquired Nevada-based Sierra Health, and thus became the new owner of a small multispecialty physician group which Sierra owned. The group did not belong in United’s health insurance business and came to rest over in Optum. Over the past twelve years, Optum Health has acquired an impressive percentage of the major capitated medical groups in the US- Texas’ WellMed, California’s HealthCare Partners (from DaVita), as well as Monarch, AppleCare and North American Medical Management, Massachusetts’ Reliant (formerly Fallon Clinic) and Atrius in Massachusetts (pending) , Kelsey Seybold Clinic (also pending) in Houston, TX and Everett Clinic and PolyClinic in Seattle.
Optum Health claims over 60 thousand physicians, though many of these are actually independent physicians participating in “wrap around” risk contracting networks. By comparison, Kaiser Permanente’s Medical Groups employ about 23 thousand physicians. United’s management claims that Optum Health provides continuing care to about 20 million patients, of whom 3 million are covered by some form of so-called “value based” contracts. Perhaps half of this smaller number are covered by capitated (percentage of premium-PMPM) contracts.
Optum Health straddles fierce competitive relationships between United’s health insurance business and competing health plans in well more than a dozen metropolitan areas. Almost half (44%) of Optum Health’s revenues come from providing care for health plans other than United.
When Optum acquires a large physician group, it acquires those groups’ contracts with United’s health insurance competitors, some of which contracts have been in place for decades. Premium revenues from other health plans, presumably capitation or per member per month (PMPM) revenues, are one-quarter of Optum Health’s $54 billion total revenues. These “external” premium revenues have quadrupled since 2018, largely for Medicare Advantage subscribers. Optum Health contributes about $4.5 billion in operating profit to United. It is impossible to determine from United’s disclosures how much of this profit comes from Optum Health’s services provided to United’s insured lives and how much from its medical groups’ extensive contracts with competing health plans.
Optum Health’s surgicenters and urgent care centers provide affordable alternatives to using expensive hospital outpatient services and emergency departments, potentially further reducing United medical expense. This creates obvious tensions with United’s hospital networks, since Optum Health can use its large medical practices and virtual care offerings to divert patients from hospitals to its own services, or else render those services unnecessary.
Though some observers have termed Optum/United’s business model “vertical integration”-ownership of the suppliers to and distributors of a firm’s product– Optum Health has actually grown less vertical since 2018, with revenues from competing health plans growing from 36% of total revenues in 2018 to 44% in 2021. A 2018 analysis by ReCon Strategy found at best a sketchy matchup between United’s health plan enrollment by market and its Optum Health assets (https://reconstrategy.com/2018/04/uniteds-medicare-advantage-footprint-and-optumcare-network-do-not-overlap-much-so-far/.
Optum Rx: The Nation’s Third Largest Pharmacy Benefits Management Business
Optum’s largest business in revenues is its Optum Rx pharmaceutical benefits management (PBM) business, which generates $91 billion in revenues, and processes over a billion pharmacy claims not only for United but also many competing insurers and employer groups. Pharmaceutical costs are a rapidly growing piece of total medical expenses, and controlling them is yet another source of largely unregulated profits for United; Optum Rx generated over $4.1 billion of operating profit in 2021.
Optum Rx is the nation’s third largest PBM business after Caremark, owned by CVS/Aetna and Express Scripts, owned by CIGNA, and processes about 21% of all scripts written in the US. Pharmacy benefits management firms developed more than two decades ago to speed the conversion of patients from expensive branded drugs to generics on behalf of insurers and self-funded employers. They were given a big boost by George Bush’s 2004 Medicare Part D Prescription Drug benefit, as a “pro-competitive” private sector alternative to Medicare directly negotiating prices with pharmaceutical firms.
Reducing drug spending is one key to United’s profitability. Since generics represent almost 90% of all prescriptions written, Optum Rx now relies on fees generated by processing prescriptions and on rebates from pharmaceutical firms to promote their costly branded drugs as preferred drugs on Optum Rx’s formularies. These rebates are determined based on “list” prices for those drugs vs. the contracted price for the PBMs, and are actual cash payments from manufacturers to PBMs.
Drug rebates represent a significant fraction of operating profits for health insurers that own PBMs, particularly for their older Medicare Advantage patients that use a lot of expensive drugs. Unfortunately, PBMs have incentives to inflate the list price, because rebates are caculated based on the spread between list prices and the contract pricel Unfortunately, this increases subscribers’ cash outlays, because patient cost shares are based on list prices.
Optum Rx generates about 39% of its revenues (and an undeterminable percentage of its profits) serving other health insurers and self-funded employers. Many of those self-funded employers demand that Optum pass through the rebates directly to them (even if it means being charged higher administrative fees!).
Unlike the situation with Optum Health, the “verticality” of Optum’s PBM business-the percentage of Optum revenues derived from serving United subscribers- has increased in the last seven years, to more than 60% of Optum Rx’s total business. What happens to the billions of dollars in rebates generated by Optum Rx is impossible to determine from United’s disclosures. However, our best guess is that pharmaceutical rebates represent as much as a quarter of United’s total corporate profits.
Optum Insight: “Intelligent” Business Solutions
The fastest growing and by far the most profitable Optum business is its business intelligence/business services/consulting subsidiary. Optum Insight was generated $12.2 billion in revenues in 2021, but a 27.9% operating margin, five times that of United’s health insurance business. Optum Insight is strategically vital to enhancing the profitability of United’s health insurance activities, but also generates outside revenues selling services to United’s health insurance competitors and hospital networks.
The core of Optum Insight is a business intelligence enterprise formerly known as Ingenix, which provided “big data” to United and other insurers about hospital and pricing behavior and utilization-crucial both for benefits design and administration. In 2009, Ingenix was accused by New York State of under reporting prices for out of network health services for itself and its clients, which had the effect of reducing its own medical reimbursements, and increasing patient cost shares. United signed a consent decree to alter Ingenix business practices and settled a raft of lawsuits filed on behalf of patients, physicians and employers. Its name was subsequently changed to Optum Insight.
By dint of aggressive acquisitions, Optum Insight has dramatically increased its medical claims management business, consulting services and business process outsourcing activities. . Most of United’s investment in artificial intelligence can be found inside Optum Insight. Big data plays a crucial role in United’s overall strategy. Optum Insight’s claims management software uses vast medical claims data bases and artificial intelligence/machine learning software to spot and deny medical claims for which documentation is inadequate or where services are either “inappropriate” or else not covered by an individual’s health plan. Providers also claim that the same software rejects as many as 20% of their claims, often for problems as tiny as a mis-spelled word or a missing data field.
Optum Insight software plays a crucial role in helping United’s health insurance plans manage their medical expense. Traditional health plan profitability is generated by reducing medical expense relative to collected premiums to increase underwriting profit. These profits are regulated, with highly variable degrees of rigor by state health insurance commissioners, and also by provisions of ObamaCare enacted in 2010.
Though its acquisition of Equian in 2019 and the proposed $13 billion acquisition of health information technology conglomerate Change Healthcare in 2021, United came within an eyelash of a near monopoly on “intelligent” medical claims processing software. The Justice Department challenged this latter acquisition and United may agree to divest Change’s claims processing software business as a condition of closing the deal. Even without the Change acquisition, Optum Insight processes hundreds of millions of medical claims annually not only for United’s health insurance business but for many of United’s competitors.
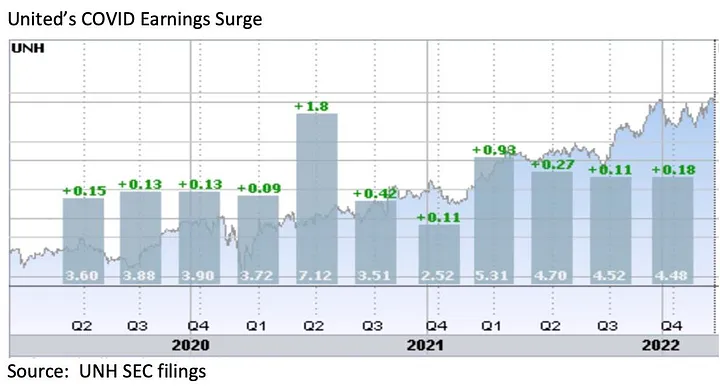
However, Optum Insight’s claims management system can also be used to increase MLR if medical expense unexpectedly declines, exposing the firm to federal requirement that it rebate excessive ‘savings’ to subscribers. This happened in 2020, when the COVID pandemic dramatically and unexpectedly added billions to United’s earnings due to hospitals suspending elective care. The chart below shows United’s 2Q2020 earnings per share almost doubling due to the precipitous drop in its medical claims expenses!
Hospital finance colleagues reported an immediate and substantial drop in medical claims denials from United and other carriers in the summer and fall of 2020. United’s quarterly profits dutifully and steeply declined in the subsequent two quarters, because its medical expenses sharply rebounded. The rise in
United’s medical expenses helped the firm avoid premium rebates to patients required by provisions of the ObamaCare legislation passed in 2010. The firm did voluntarily rebate about $1.5 billion to many of its customers in June, 2020.
However the most rapidly growing part of Optum Insight is its Optum 360 business process outsourcing business, which helps hospitals manage their billing and collections revenue cycle, as well as information technology operations, supply chain (purchasing and materials management) and other services. Through Optum 360, Optum Insight has signed five long term master contracts in the past two years’ worth many billions of dollars with care providers in California, Missouri and other states to provide a broad range of business services.
With all these different businesses, it is theoretically possible for one piece of Optum to be reducing a hospital’s cash flow by denying medical claims for United subscribers, while United’s health insurance network managers bargain aggressively to reduce the hospital’s reimbursement rates while yet another piece of Optum runs the billing and collection services for the same hospital and its employed physicians, while yet another piece of Optum competes with the hospital’s physicians and ambulatory services, diverting patients from its ERs and clinics, reducing the hospital’s revenues.
It is not difficult to imagine a future in which Optum/United offers hospital systems an Optum 360 outsourcing contract that run most of the business operations of a hospital system in exchange for preferred United health plan rates, an AI-enabled EZ pass on its medical claims denials and inpatient referrals from Optum physician groups and urgent care centers, at the expense of competing hospitals.
Managing these potential conflicts will be an increasing challenge as these various businesses grow, placing intense pressure on United’s leadership to get the various pieces of United to work together. To many anxious hospital executives, United resembles nothing so much as the Kraken, rising up out of the sea, surrounding and engulfing them- a powerful friend perhaps or a fearsome foe. As you might expect, United’s growing market power and growth has generated a fierce backlash in the hospital management community.
What Business is United Healthcare In?
United Healthcare is the most successful business in the history of American healthcare. The rapid growth of Optum and continued health insurance enrollment growth from government programs like Medicaid and Medicare has created a cash engine which generates nearly $2 billion a month in free cash flow. Optum’s portfolio has given United an impressive array of tools, unequalled in the industry, to improve its profitability and to reach into every corner of the US health system. United Healthcare is managed care on steroids.
United’s diversified portfolio of businesses gives the firm what a finance-savvy colleague termed “optionality”- the ability to redirect capital and management attention to areas of growth and away from areas that have ceased to grow, in the US or overseas. With its substantial investable capital, it will have the pick of the litter of the 11 thousand digital health companies as the overextended digital health market consolidates. United will be able to use its vast resources to build state-of-the-art digital infrastructure to reach and retain patients and manage their care.
United’s main short term business risks seem to be running out of accretive transactions effectively to deploy its growing horde of capital and managing the firm’s rising political exposure. United has had tremendous business discipline and has shied away from speculative acquisitions that are not immediately accretive to earnings. If its earnings growth falters, however, it will also encounter pressure from the investment community to increase dividends (presently about 1.2%) or share buybacks to bolster its share price, or else divest some or all of Optum in order to “maximize shareholder value”.
Answering the question, “What Business is United In” is simple: just about everything in health but hospitals and nursing homes.
Answering the questions- who are its customers and what do they want? — is a great deal harder. The customers United serves are in a sort of cold war with one another. United’s original business was protecting employers from health cost growth , and tempering the influence of hospitals and doctors by reducing their rates and utilization. By fostering so-called Consumer Directed Health Plans that expose many of their subscribers to very high front-end copayments, United and its health insurance brethren, have also increased their out-of-pocket costs, whether they have the savings to pay them or not.
There are also some ironies in United’s development. Optum Insight’s suite of hospital business services are designed to reduce administrative costs created in major part by United and other insurers’ medical claims data requirements. Its PBM business, originally intended to reduce drug spending by bargaining aggressively with pharmaceutical manufacturers has ended up pushing up drug list prices and consumer cost shares.
While presumably everybody benefits if United can somehow help patients become and remain healthy, it is still far from obvious how to do this. Managing all these markedly divergent customer needs will be a tremendous management challenge for whoever succeeds United’s reclusive (and very effective) 70 year old Chairman Stephen Hemsley.
What Does Society Get from this Vast Enterprise?
However, as Peter Drucker told a different generation of business giants, businesses are not entities unto themselves, accountable only to shareholders and customers. They are organs of society, and are expected to create social value. Americans are suspicious of vast enterprises, as businesses from Standard Oil, US Steel and ATT to Microsoft and Facebook have learned. As businesses grow and become more successful, public suspicion grows.
Private health insurers already face strident opposition from progressive Democrats, who believe that health coverage ought to be a public good, a right of citizenship provided publicly; in other words, that private health insurers have no business being in business. And large insurers like United also face intense opposition from hospitals and many physicians because they reduce their incomes and impose major administrative burdens upon them.
In the age of Twitter and TikTok, United is highly vulnerable to “event risks” that confirm the hostile narratives of the firm’s detractors that United is mainly about maximizing its own profits, not about improving the health of its subscribers or the communities it serves. It is not clear how many the tens of millions of United subscribers have warm and fuzzy feelings about their giant health insurer. Memories of the HMO backlash of the 1990’s reside in the firm’s corporate memory.
United has grown to its present immense scale largely without public knowledge. United has within its reach the capability of constraining overall health cost growth across dozens of metropolitan areas and regions, not merely cost growth for its own beneficiaries (roughly one in seven US citizens already get their health insurance through United). With its expanding digital health operations, it can deploy state of the art tools for helping United’s 50 million subscribers avoid illness and live healthier lives.
United also has the ability to damage the financial operations of beloved local hospitals and deny coverage to families, raising their out of pocket expenses. How United frames and defends its social mission and how it manages all the delicate and increasingly fraught customer relationships will determine its future, and in important ways, ours as well.
Kaiser Permanente on Wednesday announced it is acquiring Geisinger Health, and Geisinger will operate independently under a new subsidiary of Kaiser called Risant Health.
Deal details
The combination of the two companies will need to be reviewed by federal and state agencies, but if approved, the two companies will have more than $100 billion in combined annual revenue.
Geisinger will operate independently as part of Risant Health, which will be headquartered in Washington, D.C. and will be led by Geisinger president and CEO Jaewon Ryu. The health systems said they intend to acquire four or five more hospital systems to fold into Risant in an effort to reach $30 billion to $35 billion in total revenue over the next five years.
In an interview, Ryu and Kaiser chair and CEO Greg Adams said Risant will specifically target hospital systems already working to move into value-based care.
According to Adams, Risant Health “is a way to really ensure that not-for-profit, value-based community health is not only alive but is thriving in this country.”
“If we can take much of what is in our value-based care platform and extend that to these leading community health systems, then we extend our mission,” Adams said. “We reach more people, we drive greater affordability for health care in this country.”
Why we’re ‘cautiously optimistic’ about this acquisition
Just when you thought healthcare couldn’t get more interesting, Kaiser and Geisinger announce their union through newly established Risant Health. At first pass, it is hard to see a downside with this deal — and that’s something that raises my “spidey-senses.”
Kaiser and Geisinger are coming together through a vehicle that could allow them to clear an increasingly skeptical Federal Trade Commission. It affords two health systems — both in comparatively weaker financial positions than before the pandemic — the ability to get bigger through the merger. Its pitch is decidedly hospital- (and in the future provider) led, with Geisinger retaining its brand and elevating its CEO to the head of Risant. It also gives Geisinger and future partners the latitude to pursue their own payer relationships.
In addition, it is ostensibly a play to increase providers’ control over the nature and pace of value-based care (VBC) adoption. In its press release, Kaiser acknowledges that its closed network model of care management hasn’t scaled well to other markets. And Geisinger, with its own health plan and a track-record of developing its own VBC incentives, is no neophyte and brings a clear wealth of expertise.
Without a doubt, the offer to future partners is compelling: “Come for the size and stay for the value-based care.” But like all things in life, it’s all in the details. And that’s where my “spidey-sense” kicks in.
Partnership and affiliation models alone do not make the hard work of VBC easier. While this emerging group could become a valuable, provider-led clearing house for VBC concepts, applying them in communities remains a stubborn challenge that requires individual work and leadership.
The true test of the concept will come when the first new partner joins. How they decide to participate and whether the model has the right mix of scale and flexibility is what I’ll be watching closely. The overall objective and success measure of this endeavor remains somewhat opaque, but I would say that the concept has real legs here. Right now, I’m leaning toward “cautiously optimistic.”
Physician staffing firm Envision Healthcare filed for Chapter 11 bankruptcy this week, but will “continue operating its business as usual” so that the company can “provide patients with the high-quality care they require.”
Envision Healthcare files for Chapter 11 bankruptcy
On Monday, Envision Healthcare filed for Chapter 11 bankruptcy in the U.S. Bankruptcy Court for the Southern District of Texas. Following the filing, all of the company’s debt — except for a revolving credit facility for working capital — will be cancelled, totaling around $5.6 billion.
In a news release, Envision said several events have placed significant pressure on its finances since it was acquired by private equity (PE) firm KKR for $10 billion in 2018.
“The lingering impacts from COVID-19 on volume and labor costs, the delays resulting from tactics and recalcitrance by Envision’s largest insurance payors, and the ongoing regulatory uncertainty caused by the flawed implementation of the No Surprises Act have proven too much,” said Paul Keglevic, Envision’s chief restructuring officer.
Throughout the pandemic, healthcare staffing firms struggled to find enough workers to meet patient demand, especially in the highly competitive contract labor market, Modern Healthcare reports.
While Envision said it filed for bankruptcy because it is not generating enough revenue to cover its expenses and debt, it currently has $665 million of cash in the bank. According to the filing, the company expects those funds to help it exit bankruptcy faster.
“The decision to file these chapter 11 cases now, while the debtors have ample cash on hand, will ensure that the company can continue to provide patients with the high-quality care they require,” Keglevic said in the filings.
The company has entered a Restructuring Support Agreement (RSA), with plans to operate normally during the restructuring. Pending court approval, Envision said it will tap into cash collateral from ongoing operations to cover costs, “including supplier obligations and employee wages, salaries, and benefits during the restructuring process.”
“This will enable the company to continue operating its business as usual throughout the process and provide support to critical partners, including clinicians, hospitals, vendors and suppliers,” the company said.
Under the RSA, the company will divide its primary businesses, AMSURG and Envision Physician Services, which will be owned by their respective lenders.
Does Envision’s bankruptcy spell trouble for other PE investments?
Envision isn’t like other medical group PE investments
As we discussed in a previous expert insight, PE investments in physician practices aren’t a monolith. Many different types of medical groups receive investments, and PE firms have a range of healthcare sector experience and business practices.
Envision is an example of an outlier in all of these areas. First, their physician services are all hospital-based, with a heavy emphasis on emergency medicine — this contrasts with the predominant wave of physician practice investment in ambulatory practices. KKR only has one other physician practice investment, and their healthcare portfolio is rather limited.
Most importantly, Envision’s business model was reliant on exploiting questionable business practices and loopholes, which were heavily impacted by the No Surprises Act.
So, this bankruptcy isn’t an indictment of PE investment in physician groups. It just shows that healthcare organizations are not immune to being caught on their bad business practices — though PE, which is already struggling in the court of public opinion, won’t be helped by Envision’s demise.
What Envision’s bankruptcy means
Envision’s bankruptcy shines a light on trends we’ve been watching with hospital-based medicine that make financial solvency challenging: the strain of uninsured patients on revenue, workforce shortages driving up labor costs, and COVID-related volume impacts, to name a few.
What’s different with the average health system compared to Envision? While clearly rife with inefficiencies, health systems have mechanisms to self-correct.
Envision’s business model was not an innovation on care design or delivery.
It was a model taking advantage of pricing distortions and patients who are not in a position to shop for emergency care. That model inherently has limited running room.
On the physician practice front, Envision’s bankruptcy highlights the challenging business environment PE firms choose to enter when they invest in physician practices. Medical groups are a low-margin business, and the running room on cost savings has a low ceiling.
While many of the highest profile PE investments in physician groups come from firms with a long track record in the physician space, it remains to be seen whether the return on their investments will be high enough to satisfy investors.
The spotlight on large, heavily resourced healthcare organizations is not going away anytime soon. In fact, as consolidation continues, new investors enter the forefront, and organizations diversify the type of assets they acquire, that spotlight is only getting brighter.
Starting June 1, UnitedHealthcare will require physicians to submit prior authorization requests for certain types of colonoscopies. While routine screening colonoscopies will remain exempt, United beneficiaries requiring surveillance or diagnostic colonoscopies—which are performed on patients at greater risk of developing colon cancer or those already exhibiting worrisome symptoms—will need advance approval for the procedures to be covered by the payer. A UnitedHealthcare spokesperson said that this policy change is due to concerns that colonoscopy overutilization generates unnecessary medical risks and higher healthcare spending for patients.
The American College of Gastroenterology released a statement criticizing the new policy on the grounds that prior authorization requirements create harmful delays for patients and are a significant source of provider burnout.
The Gist: So much for the planned rollback of prior authorizations that UnitedHealthcare recently touted.
While the insurer is not wrong in saying that some studies have documented overutilization of colonoscopies,
prior authorization is a blunt tool that takes care decision making out of practicing providers’ hands, redirecting that power (along with more profit) to the payer.
To process prior authorization requests in a timely manner, insurers now commonly rely on AI algorithms, which are an imperfect solution. For patients exhibiting signs of colon cancer,improper denials and delayed approvals for colonoscopies could have life-threatening implications.
On Wednesday, CVS revealed plans to phase out its clinical trials unit by December 2024. The company launched the business line in 2021, building off its successful participation engaging CVS patrons in COVID vaccine and treatment studies.
With 40 percent of Americans living near a CVS pharmacy, the company had hoped to facilitate the decentralization of the clinical trials business, recruiting patients who lived in markets without academic medical centers, with goals to engage 10M patients across 150 research sites. However, to date it has only enrolled 33K participants, just over 10 percent of its COVID vaccine volunteer patient cohort.
The Gist: While CVS appears to be focusing on its faster-growing Medicare Advantage and provider businesses, following its expensive acquisitions of Oak Street Health and Signify Health, the promise for decentralized clinical research remains.
Traditional clinical trials often suffer from low participation; recruiting from more diverse populations would improve enrollment and could enhance the quality of research conducted.
Decentralization is also a win for patients, providing access to clinical trials for lower-income patients who may have difficulty regularly traveling to academic centers. Other players, ranging from startups to retail giants like Walmart and Walgreens, remain active in this space. While we hope they may bring new models to market, they will likely evaluate their programs against similar business decisions and profit objectives.







 HENRY KOTULA
