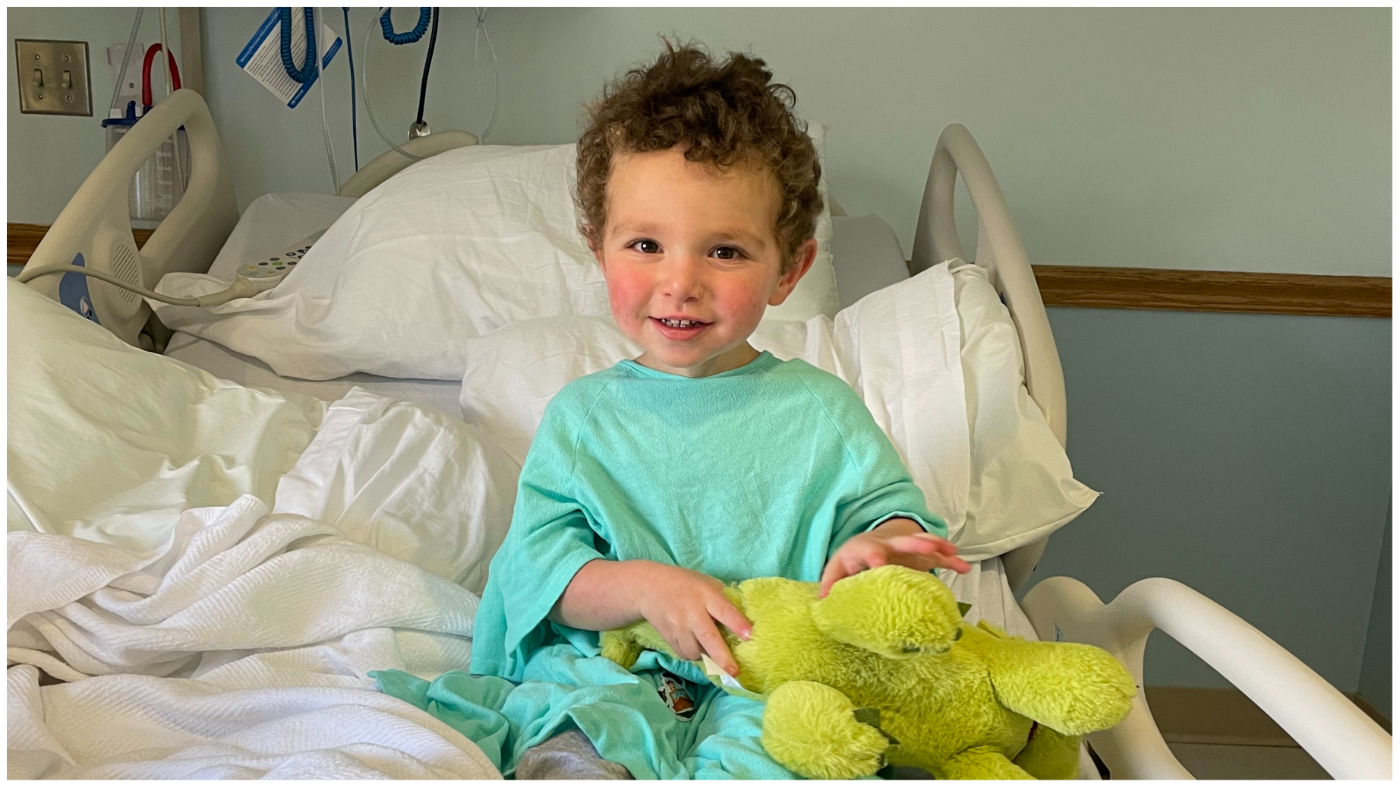
A mother’s harrowing RSV story ends with a simple lesson

I began to wonder if this trip to a pediatric urgent care with my son was even necessary.  

Sure, he had been diagnosed with pneumonia a week ago and didn’t seem to be getting better. His cough sounded uglier. But here Ethan was in classic two-and-a-half-year-old mode: running in big circles around the waiting room chairs and causing the kind of ruckus only a toddler can.  

He’d stuff some Pirate’s Booty I had hastily thrown into my purse in his mouth, before returning to his wild banshee ways and dashing around in circles again. 

Our pediatrician said their office was too swamped with sick kids to see us, and referred us to this place. We had been told the wait to see a doctor would be a minimum of an hour. We struggled to find a seat in the packed waiting room as far as possible from other coughing kids. 

We finally graduated from the waiting room to the doctor’s office, only for Ethan to continue his marathon by scooting a rolling chair back and forth, roaring with laughter every time it hit the examining table. When the physician walked in, I felt like I needed to defend wasting her time with this visit with my seemingly A-OK, albeit destructive, son. 

But Ethan wasn’t OK.  

The doctor listened to his chest with her stethoscope and didn’t like what she heard: wheezing, some crackling.

She showed me how Ethan’s Pirate’s Booty-stuffed stomach moved heavily each time he inhaled and exhaled. 

They had Ethan complete a nebulizer treatment in the office, which meant slipping a device on his face that resembled an oxygen mask, while medicated air meant to open up his lungs flowed through a frightfully loud machine. I held him in my lap while the nebulizer was on, scrambling to find 100 different versions of “Wheels on the Bus” videos on YouTube to try to distract him from the vacuum-like whirring of the machine. 

The doctor listened to his lungs again. His breathing still didn’t sound great, but she said the hospitals were too inundated right now.  

I knew all too well what she meant. A few days before our urgent care visit, I had flagged a report for editors at The Hill that said children’s hospitals in the Washington area were at capacity, flooded with young kids suffering from RSV, a potentially life-threatening respiratory illness that has no vaccine. 

After a three-hour visit, she gave Ethan a steroid and told us to follow up with his pediatrician the next day. 

By the time we got to the pediatrician’s office the following morning, my happy-go-lucky, playful little guy was anything but. He curled up in my lap, as we went through a similar routine that the urgent care doctor had done just the night before. His oxygen levels were too low, and our pediatrician had him do another nebulizer treatment. 

“Our goal is to keep you from going to the hospital,” our pediatrician told us.

It seemed like an unusual “goal” from a doctor, but I understood her reasoning. But after Ethan’s oxygen levels dipped lower still after the nebulizer, she said we should rush him straight to the hospital after all. 

My “Blue’s Clues” and vehicle-obsessed son, usually the epitome of toddler “I can do it myself!” independence, wouldn’t let me put him down for even a moment as we waited in the emergency room lobby. Surprisingly, a separate waiting area in the ER just for children wasn’t completely full, and I wondered if maybe news reports of endless waits were overblown.  

Not so. 

“He’s so cute,” a young mother in the waiting room told me, as she motioned to Ethan’s head of curls. She cradled her two-month-old in her arms, patiently rocking the baby after telling me she had waited three hours so far. 

I held Ethan as my husband rushed from work to the hospital, meeting us there and with us as we were brought to an ER triage area. They ran more oxygen tests on Ethan, got some of his history, and then sent us back to the waiting room. 

Finally, they called Ethan’s name and we were in the ER. My vibrant, otherwise-healthy kid was lethargic, laying on me with a glazed look in his eyes. We struggled to fit the two of us on an exam table meant for a single adult. They draped a lead apron over me and Ethan as they took X-rays of his tiny lungs. The nurse placed a cannula in Ethan’s nose for supplemental oxygen and put an IV in his arm to give him fluids, before wrapping it with a diaper so he wouldn’t try to take out the tube.  

My husband and I, loopy from what was happening, laughed at the sight of a diaper being used MacGyver-style. “Hey, it works!” the nurse said, explaining that he’d done the maneuver with kid after kid in recent weeks. 

The ER doctor finally came in our room and delivered a crash course in what might be to come. “Everywhere is full. The entire Eastern seaboard,” he said of hospitals. 

“We’ve been airlifting kids to Pittsburgh, sometimes to Richmond,” he added. This hospital had a pediatric unit, but not an intensive care geared towards kids. So if Ethan’s condition became even more dire, they wouldn’t be able to treat him there. Our only hope was that the pediatric unit, which had just a few remaining beds, accepted him. 

It was a gut punch. As the doctor left, my husband looked at Ethan, who had fallen asleep with a mask on as the nebulizer loudly buzzed away for another treatment. 

“He’s just a baby. He’s not supposed to be here,” my husband said, defeated. 

The pediatric unit doctor finally came into our room. She examined Ethan, and briefed us on how they’ve been dealing with case after case of the same thing: RSV.  

But she offered us hope: he could head to the pediatric unit at the hospital. We wouldn’t need to travel for his care, as long as he didn’t worsen. Ten hours after we first entered the hospital, we had a bed for Ethan. 

We’re among the lucky ones. We were told beyond airlifting, plenty of families had been spending multiple nights in the ER because there were no beds.  

In Maryland, Gov. Larry Hogan (R) announced last week that that hospitals would receive $25 million in additional funding from the state to prioritize pediatric intensive care unit staffing. Children from birth to age two comprised 57 percent of hospitalizations last week, according to Hogan’s office. 

Next to the ghost decorations for Halloween adorning the doors of the pediatric unit, room after room had the same notice taped up: isolation guidelines. The rooms were all filled with kids facing the exact same thing as Ethan. RSV was everywhere. 

There’s no cure for RSV. Every two hours on the dot, the nurses would give Ethan the nebulizer treatment.

A monitor affixed to his foot would alert nurses if his oxygen dipped dangerously low, which it did several times throughout the first night. I thought at one point to ask what happens if Ethan stopped responding to the treatments, but then didn’t ask because I didn’t want to know the answer.  

The goal was to get him going without the need for additional oxygen, and breathing well for at least four hours between treatments, two times in a row. 

That seemingly simple goal proved elusive for two full days. I originally thought it would be a nightmare trying to get a two-year-old to stay in a hospital bed for more than five minutes, but Ethan was in such bad shape that he barely made a fuss. Then, after midnight on our second night in the hospital, Ethan suddenly perked up. 

He sat up and rolled over in the hospital bed. Then, he rolled onto my head, spreading his arms and legs out as far as he could stretch, and giggled. 

“Should I sleep here?” he said, cracking himself up. 

It was like someone hit the power button on my kid, and suddenly he snapped back to himself. I didn’t care that it was midnight and we needed to get some extremely interrupted sleep before the next nebulizer treatment. My son was back. 

A nurse later told me that she enjoyed working with kids because for as quickly as their health can deteriorate, they can just as speedily bounce back. 

After that, the doctor advised us to try stretching out his time between treatments. Finally, we were told he was stable enough to go home. I somehow hadn’t shed a tear the entire time we were at the hospital, but when the doctor signed off on us leaving, I bawled.  

As nightmarish an experience as it was, I realize how incredibly fortunate my family is.  

My husband and I have jobs that allowed us to drop everything when our son needed help, we have health insurance policies, and resources to get through spending days at the hospital.  

Perhaps most importantly, we had access to an incredible team of doctors and nurses and the sheer fortune of being able to get a bed for our son during an unprecedented and unthinkable time for hospitals. 

At the risk of repeating one of those parenting cliches that I would’ve rolled my eyes at a week ago, I’m thankful that I trusted my gut. Even when Ethan was being a wild child at urgent care, I knew something just wasn’t right. What I didn’t know was how much he had been struggling to breathe. 

At the hospital after being discharged, Ethan and I waited in the lobby as my husband went to get our car from the parking lot to pick us up. Ethan spotted some empty wheelchairs in the corner of the lobby, and immediately ran over to them. He giggled as he tried to roll one of the chairs into the automatic opening and closing doors. As I looked on as he laughed and laughed at the pint-sized commotion he created, I breathed a sigh of relief. 

U.S. economy adds 261,000 jobs in October as labor market stays solid

https://www.axios.com/2022/11/04/october-job-report-2022-release

The labor market remained solid in October: the U.S. economy added 261,000 jobs, while the unemployment rate rose to 3.7% from 3.5%, the government said on Friday.

Why it matters: The last major economic report before the midterm elections shows that while jobs growth has slowed, employers continue to add workers at a robust pace as the labor market defies fears of a recession.

Driving the news: October’s jobs gains were above the 205,000 payrolls economists expected. It’s a slightly slower pace than the 315,000 jobs added in September, which was revised higher by 52,000.

  • Average hourly earnings, a proxy for wage growth, rose by 0.4% in October — a bit faster than the prior month, when wages grew 0.3%.
  • The share of people working or looking for work, known as the labor force participation rate, was 62.2%, a tick below the 62.3% in September.

The backdrop: The Federal Reserve this year has raised interest rates at historically rapid pace in an effort to slow the economy and, in turn, beat back soaring inflation. Many economists warn that the U.S. will soon enter a recession. Still, the labor market has chugged along.

  • Layoffs are being reported in a handful of sectors, including technology. But a range of job market indicators have suggested that, generally, employers are hungry for workers and trying to hold on to staff.

That is worrisome for the Fed, which fears the too-hot labor market will stoke inflation. But, on the flip side, it’s been great for American workers — though the booming job market has been coupled with decades-high inflation that’s eaten away at wage gains.

  • The economy is a top issue for voters in next week’s midterm elections.

GOP floats Medicare changes while ducking details

https://www.axios.com/2022/11/03/gop-floats-medicare-reform

Some House Republicans aren’t waiting for the election to think about overhauling Medicare. But it’s hard to tell if there are specifics behind the talking point.

Why it matters: Past GOP attempts to cut Medicare landed with a thud, and Democrats in recent weeks have been hammering on the message that Republicans are intent on gutting the program.

  • The critical moment could be next year’s talks on the debt ceiling, if Republicans flip one or both houses of Congress.

What they’re saying: “If we’re going raise the debt ceiling, we can’t just raise it without focusing on some way to address the debt and the deficit,” Rep. Bruce Westerman (R-Ark.), a member of the House GOP’s health care task force, told Axios, adding Medicare should be made “sustainable over time.”

  • “We’re going to have a lot of hearings on this,” Rep. Jason Smith (R-Mo.), the current top Republican on the Budget Committee who wants to move up to chairman of Ways and Means, told Axios. “I’m not going to get into the inner details.”
  • “Everything is on the table, we haven’t really nailed down any specific policies one way or the other,” Rep. Buddy Carter (R-Ga.), who is running to chair the House Budget panel. “I think it could be wrapped up with that [debt ceiling talks], that’s shaping up to be pretty dynamic.”

Yes, but: Not all Republicans are eager to kick off their time in the majority with another grinding health care fight against a Democratic president. Health policy experts are also skeptical of how realistic Medicare reform may be, recalling failed GOP agendas from the pre-Trump years.

  • Senate GOP Leader Mitch McConnell (R-Ky.) earlier this year rebuked a plan from Sen. Rick Scott (R-Fla.) that would sunset all federal legislation every five years — including entitlement programs. McConnell told reporters a plan that “sunsets Social Security and Medicare within five years … will not be part of the Republican Senate majority agenda.”
  • House GOP Leader Kevin McCarthy (R-Calif.) raised eyebrows when he told Punchbowl News last month that he wouldn’t “predetermine” if Medicare and Social Security would be involved in talks on raising the debt ceiling. McCarthy later tried to clarify in a CNBC interview that “I never mentioned Social Security or Medicare.”
  • Joseph Antos, a senior fellow and health care scholar at the American Enterprise Institute, puts the odds of Medicare reform as “pretty unlikely,” adding, “I don’t see any major changes happening over the next two years, and I think Republicans might wait to see what Medicare policies the Republican presidential candidate will push.”

The big picture: While a GOP Medicare push is not certain, Democrats are seizing on the possibility.

  • “They’re coming after your Social Security and Medicare in a big way,” President Biden said Tuesday in a speech in Florida, saying Republicans would create “chaos” by risking government default over demands to raise the debt limit next year.

Between the lines: Republicans are not being specific about the changes they would push. But there’s a limited universe of possibilities.

  • The proposed budget of the Republican Study Committee, an influential group of House Republicans, includes proposals like raising the Medicare eligibility age to 67 to align with Social Security, and converting Medicare to a “premium support” system where seniors received a subsidy they could use on private plans competing against traditional Medicare.
  • Tricia Neuman, a Medicare expert at the Kaiser Family Foundation, said such a policy would have “uneven” results, where “some could save money but others might have to pay a whole lot more.”
  • Other GOP-backed Medicare changes are less partisan, like “site neutral” reforms to pay hospital outpatient departments the same rates as doctors’ offices, though hospitals oppose those measures.
  • The Committee for a Responsible Federal Budget, recently issued a fiscal blueprint to reduce the budget deficit, which included reforms such as changing Medicare provider payments, benefit design and payroll taxes, but included nothing about changing eligibility requirements.

The bottom line: Republicans point to the Medicare trust fund’s projected insolvency date in 2028 to argue change is needed to make the program sustainable. But any change is hard, and cuts that hit beneficiaries are not the only way to seek savings.

  • “McCarthy won’t shoot down talk of addressing debt because it matters to him and his caucus, and you can’t do debt without entitlement reform, but he knows at this point there’s no interest from Democrats, and any entitlement reform will require serious political capital from Ds and Rs,” said a former GOP leadership aide. “The last time those conversations happened in a meaningful way was in 2011.”

For hospitals, ‘difficult decisions’ loom after 9 months of negative margins

The third quarter brought little relief to hospitals in what is shaping up to be one of their worst financial years. 

Kaufman Hall’s October National Hospital Flash Report — based on data from more than 900 hospitals — found slightly lower hospital expenses in September did not outweigh lower revenue across the board, with decreases in discharges, inpatient minutes and operating minutes.

The median year-to-date operating margin index for hospitals was -0.1 percent in September, marking a ninth straight month of negative operating margins and a dimmer outlook for their climb back into the black by year’s end. 

Kaufman Hall noted that expense pressures and volume and revenue declines could force hospitals to make “difficult decisions” about service reductions and cuts. 

“Health systems are starting to get a clear picture of what service lines have a positive effect on their margins and which ones are weighing them down,” said Matthew Bates, managing director and Physician Enterprise service line lead with Kaufman Hall. “Without a positive margin there is no mission. Health systems must think carefully and strategically about what areas of care they invest in for the future.”

Health systems suffer while payer profits soar

Large health systems are reporting big losses this year while insurers continue to turn billion-dollar profits.

Humana reported $1.2 billion in third quarter profits, a slight drop from the same period last year. The company has focused on regaining Medicare Advantage market share and increased quarterly revenues 10.2 percent year over year.

Cigna’s third quarter profits jumped 70 percent year over year, hitting $2.8 billion. The company reported $45.3 billion in third quarter revenues and raised its annual earnings outlook based on the results. The company now projects $179 billion for full year 2022 adjusted revenue.

CVS Health also beat investor expectations in the third quarter and raised its earnings outlook. The company’s third quarter revenue jumped almost 10 percent year over year to $81.2 billion, although it reported $3.4 billion in losses after agreeing to pay into a $5 billion global opioid lawsuit settlement over 10 years.

At the same time, health systems are reporting multimillion and even billion-dollar losses. Chicago-based CommonSpirit Health reported $1.3 billion operating loss for the 12-months end on June 30. Ascension, based in St. Louis, also reported a $1.8 billion loss for the fiscal year’s end in June.

Community Health System reported a $42 million net loss for the third quarter in October and both Dallas-based Tenet Healthcare and Nashville, Tenn.-based HCA Healthcare reported more than 50 percent drops in quarterly net income from 2021 to 2022.

The profitability mismatch between the nation’s largest payers and health systems of all sizes will be front and center during contract negotiations in the coming year. There have already been high profile contract impasses between insurers and large systems, with some leading to contract termination.


