As we’ve talked to health system executives about the challenges of rolling out COVID vaccines in their communities, one topic keeps coming up: how difficult it’s been to get hospitals’ own workers fully vaccinated. One system told us recently that only 55 percent of their frontline caregivers have opted to get vaccinated, despite early and easy availability, and ongoing encouragement from the hospital’s leaders.
Healthcare workers, it turns out, are just like the general population, bringing the same diversity of perspectives and concerns about vaccination to work with them from their own communities. Vaccine hesitancy is not a new issue for hospital staffers; getting the workforce to take the flu vaccine is an annual struggle for many hospitals.
But given the risks of COVID-19, why not just mandate that hospital employees get the vaccine, as other employers have started to do? We commonly hear two concerns.
One is a labor relations worry: will mandating vaccination cause workers to quit, or make it harder to hire staff in an already difficult market for talent? And given growing concerns about unionization of healthcare workers, will mandatory vaccination become a flashpoint issue?
The second concern is medical liability: can we force workers to get a vaccine that hasn’t been fully approved by the FDA? Would that expose the hospital to legal challenges down the road, if there turn out to be long-term complications from the vaccine?
Our own view is that the first concern is overblown—we suspect vaccine mandates are going to become more and more common as the economy reopens. As to the second, we’re more sympathetic. But once the FDA does grant full approval for the vaccines, we’d hope hospitals will get tougher about vaccine mandates (with the necessary exemptions for health, religious, and other concerns).
At the end of the day, hospitals are in the patient care business, and they should view vaccine mandates—whether for COVID or for influenza—as a patient safety issue, not a workforce engagement issue.
Though consumers say they’re increasingly confident in returning to healthcare settings, hospital volume is not returning with the same momentum across the board. Using the most recent data from analytics firm Strata Decision Technology, covering the first quarter of this year, the graphic above shows that observation, inpatient, and emergency department volumes all remain below pre-COVID levels.
Consumers are still most wary about returning to the emergency department, with volume down nearly 20 percent across the past year. Meanwhile, hospital outpatient visits rebounded quickly, and have been growing steadily month over month, finishing March 2021 at 36 percent above the 2019 level.
Meanwhile, a recent report from the Commonwealth Fund shows that no ambulatory specialty fully made up for the COVID volume hit by the end of last year. But some areas, including rheumatology, urology, and adult primary care, have bounced back faster than others.
With continued success in rolling out vaccines and reducing COVID cases, we’d expect a continued recovery of most hospital visit volume. It may be, however, that some areas, such as the emergency department, will never fully recover to pre-COVID levels. To the extent those visits are now being replaced by more appropriate telemedicine and urgent care utilization, that’s welcome news.
But the continued lag of inpatient admissions indicates that some of the loss of emergency volume is more worrisome—warranting continued efforts on the part of providers to reassure patients it’s safe to use healthcare services. Stay tuned as our team continues to dig into this data.
This week Mayo Clinic and Kaiser Permanente announced a $100M joint investment in Boston-based Medically Home, a provider of virtual hospital solutions. Founded in 2016, Medically Home is one of a handful of companies that coordinate with hospitals and doctors to provide in-home clinician visits, round-the-clock communications and monitoring, and access to support services to enable hospital-level care in the home. While interest has surged during the pandemic, the first hospital at home programs launched in the 1990s, and the model has a proven track record of delivering care that is lower cost and clinically equivalent (or better), when compared to a traditional hospital admission.
A confluence of market forces has driven rapid expansion in the model across the past year. Health systems are increasingly looking to hospital at home to address emerging consumer demand for care outside the hospital,and achieve the longer-term goals of providing flexible, lower-cost acute care capacity. And payers are looking to add hospital at home capabilities to their growing virtual and home-based care platforms to manage acutely ill Medicare Advantage beneficiariesin a lower-cost care setting.
Early adopters estimate that as many as 30 percent of patients admitted to hospitals today could be candidates for treatment at home. The large infusion of funding from Kaiser and Mayo will enable Medically Home to scale across the US, and also provides an endorsement of, and commitment to, the care modelfrom these respected systems, which may help convince physicians who remain skeptical.
Coupled with the Centers for Medicare & Medicaid Services’ waiver program, allowing payment for home-hospital care, this investment should drive a new wave of growth in the model—and will likely make hospital at home a routine part of the care options available to patients.
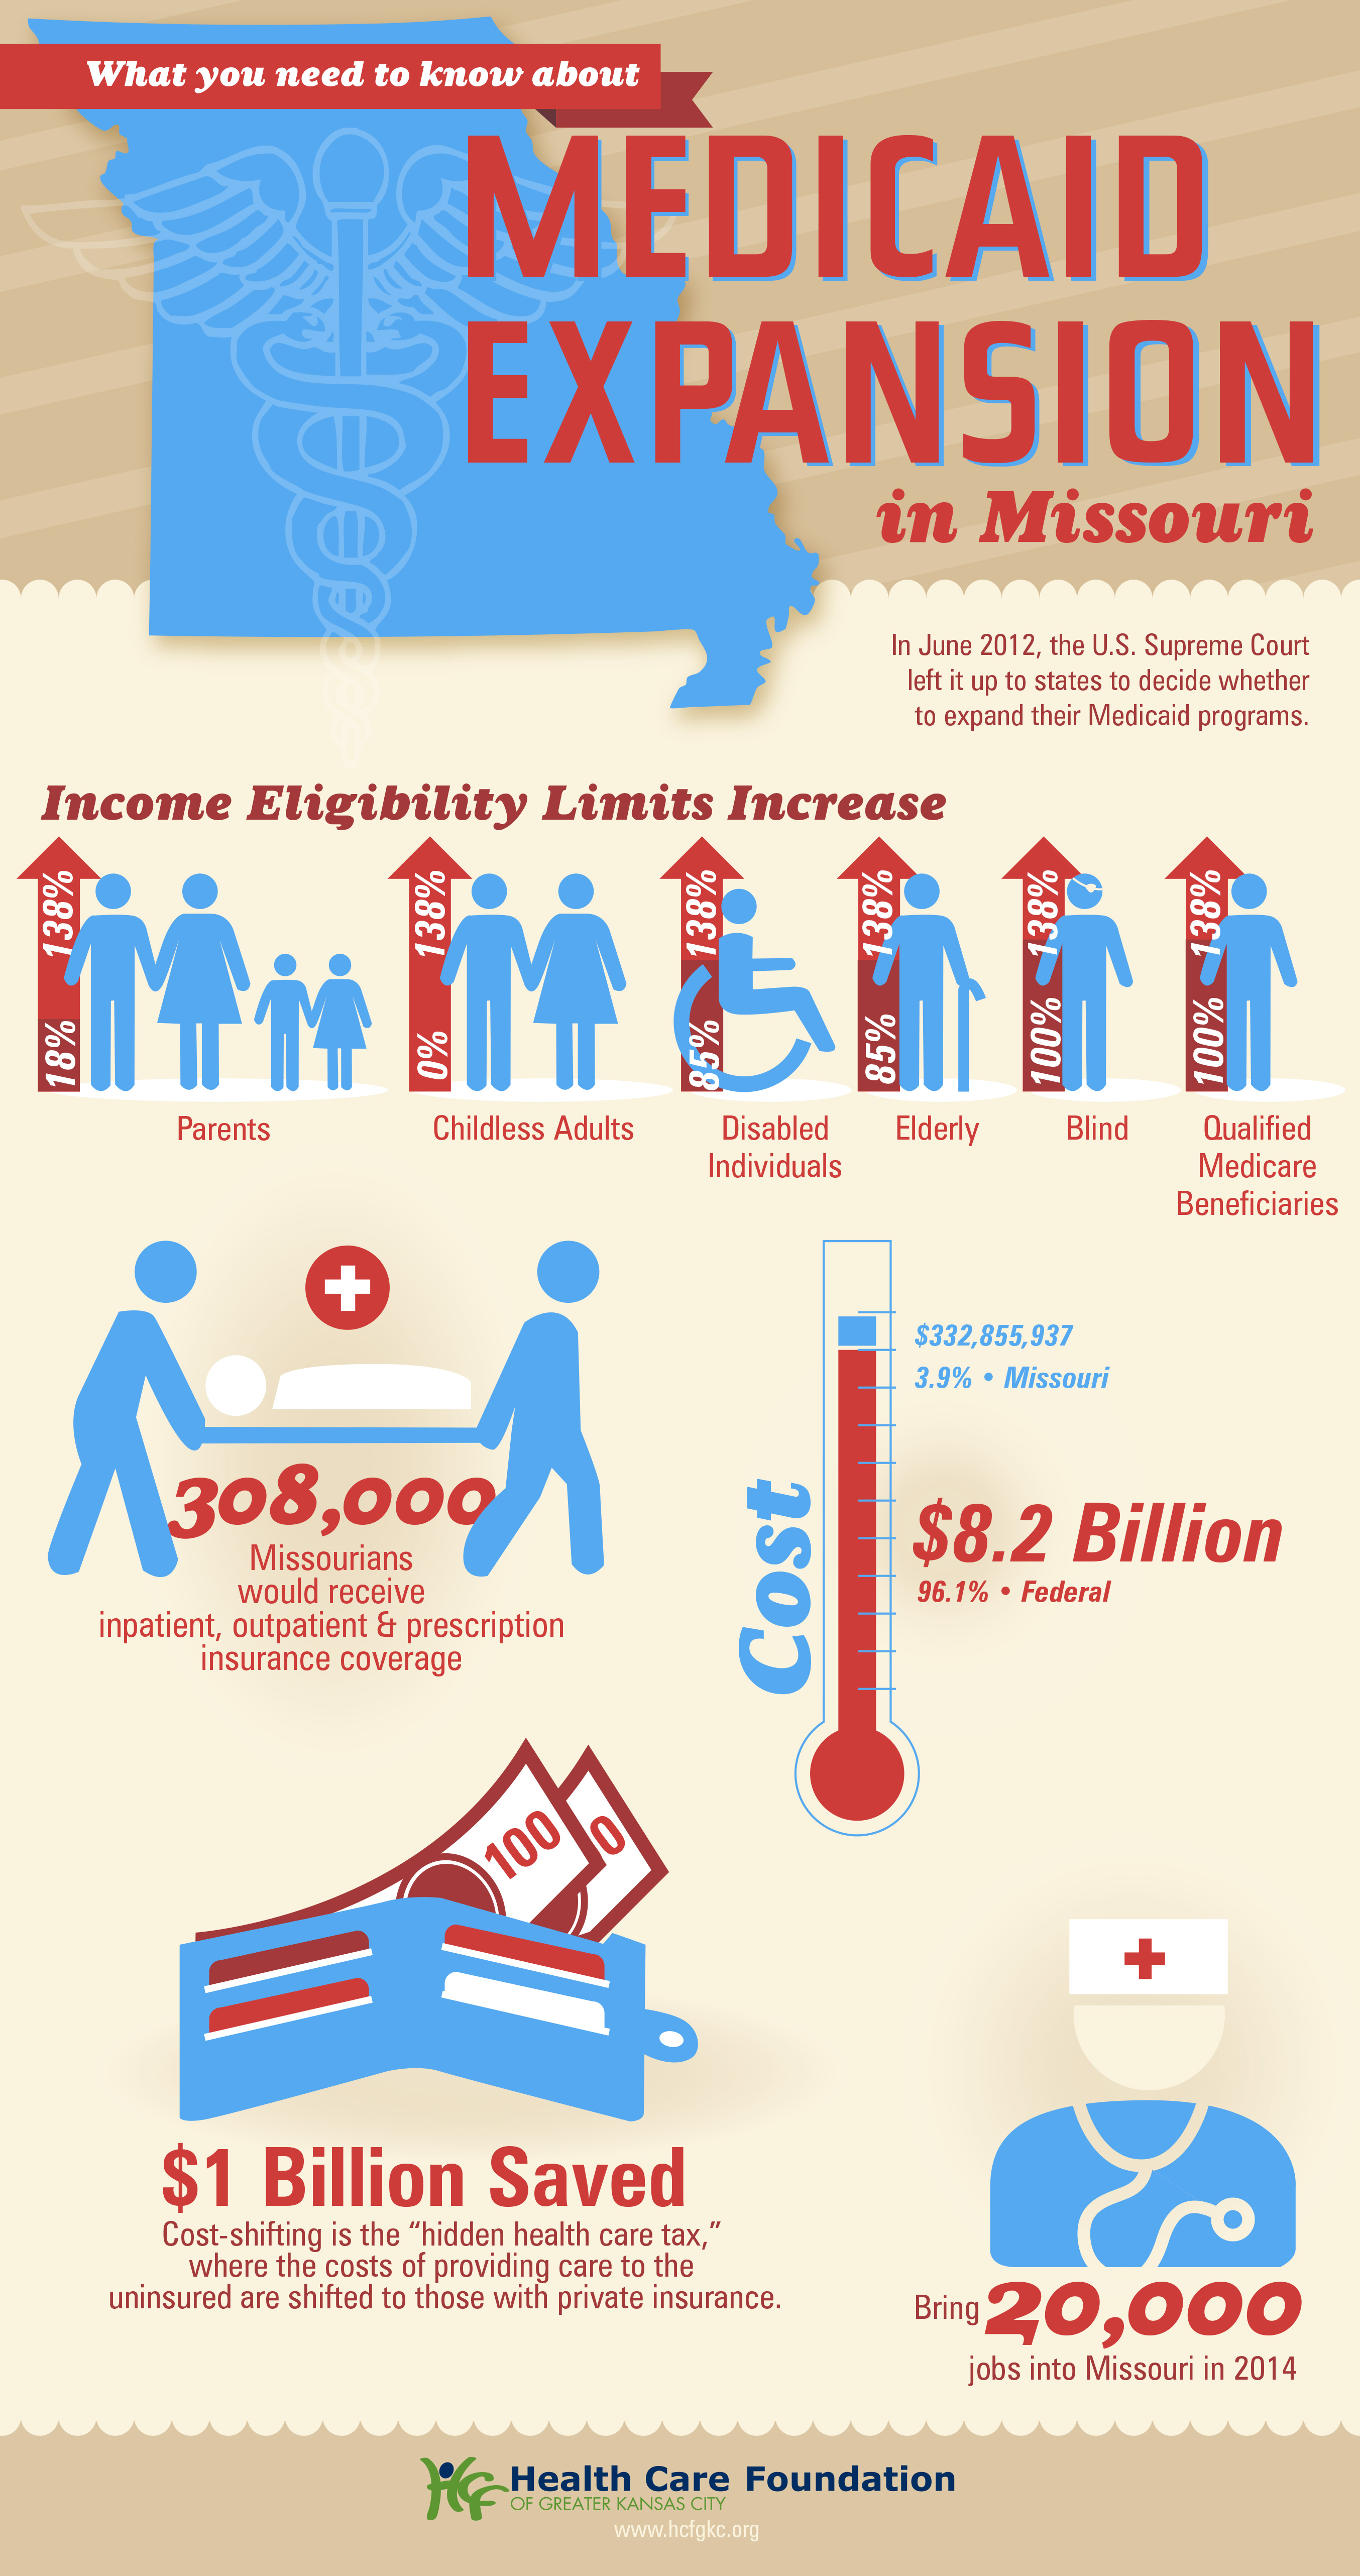
Missouri Gov. Mike Parson announced Thursday that his state would not expand Medicaid coverage to 275,000 residents who will become eligible on July 1st, despite a 2020 ballot initiative in which a majority of the state’s voters approved the expansion. Because the Missouri legislature has blocked funding for the expansion, Parson declared that the state’s Medicaid program, MO HealthNet, would run out of money if it moved forward.
The legislature’s decision to block funding was bolstered by an appeals court opinion last year, which challenged the expansion because the ballot initiative did not include a funding mechanism for widening coverage.
Under the Affordable Care Act (ACA), the federal government would have picked up 90 percent of the cost of expanding Medicaid in the state, in addition to boosting funding for existing Medicaid enrollees by 5 percent, thanks to a measure in the recent American Rescue Plan Act.
The governor’s decision leaves in place one of the strictest Medicaid eligibility standards in the nation: a family of three in Missouri must earn less than 21 percent of the federal poverty level—$5,400 per year—in order to qualify for coverage. The expansion measure would have opened the program to childless adults, and raised the eligibility limit to 138 percent of the federal poverty level.
The Missouri Hospital Association called the decision an “affront” to voters, pointing out that the state is currently running a budget surplus, and could easily allocate funds for the expansion. The status of Medicaid expansion in Missouri, which would become the 38th state to undertake expansion since the ACA’s passage, will ultimately be decided by court ruling, according to observers.
Meanwhile, like other states (mostly in the Southeast) that have resisted Medicaid expansion,Missouri will continue to see tax dollars flow out of the state to fund benefits in states that have expanded eligibility—despite the express will of voters. Given ample evidence that Medicaid expansion boosts access to care, health status, and health system sustainability,it’s nearly unfathomable that the politics of “Obamacare” continue to complicate the extension of this critical safety-net program.
Federally-subsidized childcare centers took care of an estimated 550,000 to 600,000 children while their mothers worked wartime jobs.
When the United States started recruiting women for World War II factory jobs, there was a reluctance to call stay-at-home mothers with young children into the workforce. That changed when the government realized it needed more wartime laborers in its factories. To allow more women to work, the government began subsidizing childcare for the first (and only) time in the nation’s history.
An estimated 550,000 to 600,000 children received care through these facilities, which cost parents around 50 to 75 cents per child, per day (in 2021, that’s less than $12). But like women’s employment in factories, the day care centers were always meant to be a temporary wartime measure. When the war ended, the government encouraged women to leave the factories and care for their children at home. Despite receiving letters and petitions urging the continuation of the childcare programs, the U.S. government stopped funding them in 1946.
Before World War II, organized “day care” didn’t really exist in the United States. The children of middle- and upper-class families might go to private nursery schools for a few hours a day, says Sonya Michel, a professor emerita of history, women’s studies and American studies at the University of Maryland-College Park and author of Children’s Interests/Mothers’ Rights: The Shaping of America’s Child Care Policy. (In German communities, five- and six-year-olds went to half-day Kindergartens.)
For children from poor families whose father had died or couldn’t work, there were day nurseries funded by charitable donations, Michel says. But there were no affordable all-day childcare centers for families in which both parents worked—a situation that was common for low-income families, particularly Black families, and less common for middle- and upper-class families.
The war temporarily changed that. In 1940, the United States passed the Defense Housing and Community Facilities and Services Act, known as the Lanham Act, which gave the Federal Works Agency the authority to fund the construction of houses, schools and other infrastructure for laborers in the growing defense industry. It was not specifically meant to fund childcare, but in late 1942, the government used it to fund temporary day care centers for the children of mothers working wartime jobs.
Communities had to apply for funding to set up day care centers; once they did, there was very little federal involvement. Local organizers structured childcare centers around a community’s needs. Many offered care at odd hours to accommodate the schedules of women who had to work early in the morning or late at night. They also provided up to three meals a day for children, with some offering prepared meals for mothers to take with them when they picked up their kids.
“The ones that we often hear about were the ‘model’ day nurseries that were set up at airplane factories [on the West coast],” says Michel. “Those were ones where the federal funding came very quickly, and some of the leading voices in the early childhood education movement…became quickly involved in setting [them] up,” she says.
For these centers, organizers enlisted architects to build attractive buildings that would cater to the needs of childcare, specifically. “There was a lot of publicity about those, but those were unusual. Most of the childcare centers were kind of makeshift. They were set up in church basements or garages.”
Though the quality of care varied by center, there hasn’t been much study of how this quality related to children’s race (in the Jim Crow South, where schools and recreational facilities were segregated, childcare centers were likely segregated too).At the same time, the United States was debuting subsidized childcare, it was also incarcerating Japanese American families in internment camps. So although these childcare facilities were groundbreaking, they didn’t serve all children.
Subsidized Childcare Ends When War Ends
Ruth Pease opened the Little Red School House in 1945 in response to the country’s request for help in meeting the child care needs of the post-war community.
When the World War II childcare centers first opened, many women were reluctant to hand their children over to them. According to Chris M. Herbst, a professor of public affairs at Arizona State University who has written about these programs in the Journal of Labor Economics, a lot of these women ended up having positive experiences.
“A couple of childcare programs in California surveyed the mothers of the kids in childcare as they were leaving childcare programs,” he says. “Although they were initially skeptical of this government-run childcare program and were worried about the developmental effects on their kids, the exit interviews revealed very, very high levels of parental satisfaction with the childcare programs.”
As the war ended in August 1945, the Federal Works Agency announced it would stop funding childcare as soon as possible. Parents responded by sending the agency 1,155 letters, 318 wires, 794 postcards and petitions with 3,647 signatures urging the government to keep them open. In response, the U.S. government provided additional funding for childcare through February 1946. After that, it was over.
Lobbying for national childcare gained momentum in the 1960s and ‘70s, a period when many of its advocates may have themselves gone to World War II day care as kids. In 1971, Congress passed the Comprehensive Child Development Act, which would have established nationally-funded, locally-administered childcare centers.
This was during the Cold War, a time when anti-childcare activists pointed to the fact that the Soviet Union funded childcare as an argument for why the United States shouldn’t.President Richard Nixon vetoed the bill,arguing that it would “commit the vast moral authority of the National Government to the side of communal approaches to child rearing over against the family-centered approach.”
In this case, “family-centered” meant the mother should care for the children at home while the father worked outside of it—regardless of whether this was something the parents could afford or desired to do. World War II remains the only time in U.S. history that the country came close to instituting universal childcare.
Gout can take a toll on not only health, but also on your wallet. Gout-related costs, on average, can be $12,000 per year. To minimize costs—and painful flares—make sure to get checked early and get uric acid levels checked once every six months. https://bit.ly/GoutCost
The Food and Drug Administration cleared the first coronavirus vaccine for emergency use in children as young as 12 on Monday, expanding access to the Pfizer-BioNTech shot to adolescents ahead of the next school year and marking another milestone in the nation’s battle with the virus.
The decision that the two-shot regimen is safe and effective for younger adolescents had been highly anticipated by many parents and pediatricians, particularly with the growing gap between what vaccinated and unvaccinated people may do safely. Evidence suggests that schools can function at low risk with prevention measures, such as masks and social distancing.But vaccines are poised to increase confidence in resuming in-person activities and are regarded as pivotal to returning to normalcy.
“Adolescents, especially, have suffered tremendously from the covid pandemic. Even though they’re less likely than adults to be hospitalized or have severe illness, their lives really have been curtailed in many parts of the country,” said Kawsar R. Talaat, an assistant professor of international health at the Johns Hopkins Bloomberg School of Public Health. “A vaccine gives them an extra layer of protection and allows them to go back to being kids.”
Expert advisers to the Centers for Disease Control and Prevention are scheduled to meet Wednesday to recommend how the vaccine should be used in that age group, and the vaccine can be administered as soon as the CDC director signs off on the recommendation.
In a news briefing Monday evening after the announcement, FDA officials said the Pfizer authorization for 12- to 15-year-olds was a straightforward decision because the data showed that the vaccine was safe and that the response to the vaccine was even better than among the 18- to 25-year-olds who got the shots.
Children rarely suffer serious bouts of covid-19, the illness caused by the coronavirus. But there is no way to predict the few who will become dangerously sick or develop a rare, dangerous inflammatory syndrome. Out of more than 581,000 covid-19 deaths in the United States, about 300 have been people under 18 — a tiny fraction of the total. But that exceeds the number of children who die in a bad flu season.
Children appear to be less efficient at spreading the virus, although their role in transmission is still not fully understood — another reason for pediatric vaccinations.
Clinicians also worry that with a new virus with many unknowns, the possibility exists for long-term impacts of infection, even from the mild or asymptomatic courses of illness common among children.
The Pfizer-BioNTech vaccine, already authorized for adolescents 16 and older, was the first to be tested in younger adolescents. The FDA’s decision will provide a potential path for other vaccine-makers to follow, most of which have launched or plan to initiate trials of their vaccines in teenagers and younger children.
The agency based its authorization on a trial of nearly 2,300 adolescents between 12 and 15 years old, half of whom received the same two-shot regimen shown effective and safe in adults. Researchers took blood samples and measured antibody levels triggered by the shots and foundstronger immune responses in the teens than those found in young adults. There were 16 cases of covid-19 in the trial, all of them among adolescents who received a placebo, suggesting the regimen offered similar protection to younger recipients as it does to adults.
Robert W. Frenck Jr., the researcher who led the adolescent trial at Cincinnati Children’s Hospital Medical Center, said the study was designed to test whether it triggered immune responses, not whether it prevented disease. But because of the number of children who became ill in the placebo arm of the trial, it also became evident the vaccine offered robust protection.
“That really points out how much covid there is in the adolescent community,” Frenck said.
The data has not been published or peer-reviewed, but Kathryn M. Edwards, a pediatric infectious-disease specialist at Vanderbilt University Medical Center, said the results announced by Pfizer were “pretty exciting — it looked very effective and the immune responses were really good.”
Edwards said she is comfortable the benefits of vaccinations are clear among teens, noting that while children, in general, are at lower risk of severe covid-19 than adults, older adolescents seem to be more like adults in their risk for covid-19 than the very youngest children.
Audrey Baker, 15, and Sam Baker, 12, rolled up their sleeves for shots in the Pfizer-BioNTech trial at Cincinnati Children’s Hospital Medical Center. Audrey said she had no hesitation about signing up, and misses little things about how life used to be — eating out in restaurants and seeing family.
“I just trusted the science,” Audrey said. “I knew it was tested in adults. I was really just joining, hoping that maybe I could get vaccinated and help out science.”
Sam said he was more hesitant, in part because participating meant many follow-up lab tests. But he decided to do it and thinks he may have gotten the vaccine in the trial because he developed a headache and fever after his second dose.
Their mother, Rachel Baker, said she felt relief because of Sam’s symptoms.
“The biggest benefit has been that I feel a weight off my shoulders,” Rachel said. “We haven’t changed how we do anything. … We’re still masking, we’re still social distancing, but we’re a bit calmer about it all.”
H. Cody Meissner, a pediatrician at Tufts Medical Center and a member of an external advisory committee to the FDA, said he thinks a pediatric vaccine is needed. But he said he would like to see more safety data because the messenger RNA technology at the core of vaccines from Pfizer-BioNTech and the biotechnology company Moderna does not have a long, established safety record, and its first large-scale use began in December.
Meissner abstained from the December vote that overwhelmingly recommended authorization of the Pfizer-BioNTech vaccine for people 16 and older, because he thought the vaccine should be authorized in people 18 and older.
“For those who are eager to get it, it’s important for them to understand that this is very rarely a severe disease in young adolescents, number one, and this is an entirely new vaccine,” Meissner said. “I just don’t want people to get too swept up in fear of hospitalization and death from covid-19 for the first few decades of life.”
But many other physicians take comfort knowing that 250 million shots of messenger RNA vaccine have been given in the United States alone.Serious side effects, such as a risk of anaphylaxis, are extremely rare. Because the trial in teens was an “immune bridging” trial designed to test whether the vaccine triggered immune responses similar to those in adults, researchers did not need to recruit tens of thousands of people to see if those who received a vaccine were protected against illness. The immunebridging technique is commonly used to expand access to vaccines that have been proved effective and safe to adolescents or other populations.
The expansion of eligibility to children will probably ignite debates in families about when to get vaccinated, and among policymakers about whether it should be required.
Dorit Reiss, a law professor focused on vaccine policy at the University of California Hastings College of Law, said she thinks it is unlikely children will be mandated to receive a coronavirus shot until the vaccines win full approval and not just emergency use authorization.
She predicted that acceptance of the vaccine will evolve as more children are vaccinated and depend on the state of the pandemic. She noted that when vaccines are introduced, the rollout often starts slowly before accelerating.
“Nervousness about a new vaccine is normal, especially when it’s for kids,” Reiss said. “Parents that are nervous now might feel different in a few months, once their friends’ kids have gotten vaccinated. And the views of the kids are also going to matter — if teens are going to think this is going to make their lives easier.”
Opening up vaccinations to children may sharpen a debate unfolding globally about the equity of vaccine access. Talaat said that while she can’t wait for her kids to have access to a vaccine, she is troubled by the global inequities as high-risk front-line workers or older people still don’t have access to vaccines in countries where the coronavirus is out of control.
Moderna announced Thursday that an initial analysis of its teen trial found its vaccine was 96 percent effective among participants who received at least one dose. Moderna is in discussions with regulators about the data. Pfizer-BioNTech and Moderna are testing their vaccines in children as young as infants. Johnson & Johnson is planning pediatric trials of its single-shot vaccine.
Trials in younger children are expected to take longer, because researchers must step down gradually in age and determine a safe and effective dose. William Gruber, senior vice president of vaccine clinical research and development at Pfizer, said data from tests in children as young as 2 years old may be available by September or October, with data on children as young as 6 months possible by the end of the year.
Within each age category, a separate risk-benefit assessment may take place. In the youngest children, given the low risk from the coronavirus, side effects may figure more prominently into the analysis, for example. Researchers may end up choosing a lower dose of vaccine. The understanding of children’s role in transmission may also evolve and help guide vaccine use and public policy.
“We are proceeding carefully, cautiously,” Edwards said. “We’re using the same rigid guidelines we use in all vaccines, and we take this very seriously. I think as time goes on and more information becomes available, some of the questions may be easier to address.”