Adult inpatient volumes will recover to pre-pandemic numbers but grow only 2 percent over the next decade, a new report from Sg2 forecasts.
At the same time, adult inpatient days are expected to increase 8 percent and tertiary inpatient days are poised to increase 17 percent, fueled by an increase in chronic conditions.
“While case mix varies by hospital, it is likely this combination of increased inpatient volume, patient complexity and length of stay may require healthcare organizations to rethink service line prioritization, service distribution and investment in care at-home initiatives,” Maddie McDowell, MD, senior principal and medical director of quality and strategy for Sg2, said in a June 7 news release for the report.
Five other key takeaways from Sg2’s forecasts:
1. Outpatient volumes are projected to return to pre-pandemic levels in 2022 and then grow 16 percent through 2032, three percentage points above estimated population growth.
2. Surgical volumes are projected to grow 25 percent at ambulatory surgery centers and 18 percent at hospital outpatient departments and physician offices over the next decade.
3. The pandemic-driven decline in emergency department visits is expected to plateau with a decline in demand projected at -2 percent over the next 10 years.
4. Over the next five years, home care is expected to gain traction, with home evaluation and management visits seeing 19 percent growth, home hospice at 13 percent growth and home physical and occupational therapy at 10 percent growth.
5. Telehealth is expected to resume its climb and by 2032 account for 27 percent of all evaluation and management visits.
COVID-19 cases have risen in the U.S. to around 100,000 per day, and the real number could be as much as five times that, given many go unreported.
But the situation is far different from the early months of the pandemic. There are now vaccines and booster shots, and new treatments that dramatically cut the risk of the virus. So how much do cases alone still matter?
That question has prompted debate among experts, even as much of America goes on with their lives, despite the recent surge in cases.
How much concern high case numbers alone should prompt is “the trillion-dollar question,” said Bob Wachter, chair of the department of medicine at the University of California-San Francisco.
In the early days of the pandemic, dying of COVID-19 was a concern for him, but now, in an era of vaccines and treatments, “it doesn’t even cross my mind anymore,” he said.
But he noted there are other risks, including long COVID-19: symptoms like fatigue or difficulty concentrating that can linger for months.
“I think long COVID is pretty scary,” he said.
While cases have risen to around 100,000 reported per day, deaths have stayed flat, a testament to the power of vaccines and booster shots in preventing severe illness, as well as the Pfizer treatment pills Paxlovid, which cut the risk of hospitalization or death by around 90 percent.
Hospitalizations have risen, but only modestly, to around 27,000, one of the lowest points of the pandemic, according to a New York Times tracker.
Cases have now been “partially decoupled” from causing hospitalizations and deaths, said Preeti Malani, an infectious disease expert at the University of Michigan, such that hospitals are no longer overwhelmed.
“[Cases are] not without any consequence, but in terms of pressure on the health system, so far we’re not seeing that, which is really what drove all of this,” she said.
The behavior of much of America reflects a lessened concern about the risk of being infected. Restaurants and bars are packed. Many people do not wear masks even on airplanes or on the subway.
An Axios-Ipsos poll in May found just 36 percent of Americans said there was significant risk in returning to their “normal pre-coronavirus life.”
In the Biden administration, health officials are still advising people to wear masks in areas the Centers for Disease Control and Prevention classifies as at “high” risk. But President Biden himself is talking about the virus far less than he did at the start of his administration, and is not making sustained calls for people to wear masks.
White House COVID-19 response coordinator Ashish Jha touted progress in defanging cases on Thursday.
“We see cases rising, nearly 100,000 cases a day, and yet we’re still seeing death numbers that are substantially, about 90 percent lower, than where they were when the president first took office,” he told reporters.
Some experts are pushing back on the deemphasis of case numbers, saying they still matter.
“The bunk that cases are not important is preposterous,” Eric Topol, professor of molecular medicine at Scripps Research, wrote last month. “They are infections that beget more cases, they beget Long Covid, they beget sickness, hospitalizations and deaths. They are also the underpinning of new variants.”
Even if one does not get severely ill oneself, more cases mean more chances for the virus to spread on to someone who is more vulnerable, like the elderly or immunocompromised.
While deaths are way down from their peak earlier in the pandemic, there are still around 300 people dying from the virus every day, a number that would have proved shocking in a pre-COVID-19 world.
Leana Wen, a public health professor at George Washington University, recommended that people take a rapid test before visiting a more vulnerable person, as a safeguard that avoids more burdensome restrictions.
“Cases alone do not tell the whole story,” she said, adding, “As a policy matter we need to stop using the same comparisons we were in 2020 and 2021.”
There is still much that is unknown about long COVID-19, one of the biggest risks remaining for healthy, younger people who are vaccinated.
A recent article in the Journal of the American Medical Association estimated 10 percent to 30 percent of COVID-19 infections result in long COVID-19 symptoms, but there is no precise estimate.
Experts also urge people who have not gotten their booster shots, or not been vaccinated at all, to do so, given that many are more vulnerable to the virus if they are not up-to-date on their shots.
A new variant also always holds the risk of upending the current risk-benefit calculations. The virus has continued to evolve to spread more easily, and a future mutation could cause more severe illness or more greatly evade vaccines.
Pfizer and Moderna are working on updated vaccines to better target the omicron variant, but the Biden administration warns it will not have enough money to purchase those new vaccines for all Americans this fall unless Congress provides more funding. The funding request has been stalled for months, though, itself a sign of the reduced sense of urgency around the virus fight.
At least for now, though, while many people are getting COVID-19, fewer are getting extremely sick.
“It’s a very risky time if you don’t want to get COVID [at all],” Wachter said. “But a relatively less risky time if your goal is to not get severe COVID or die.”
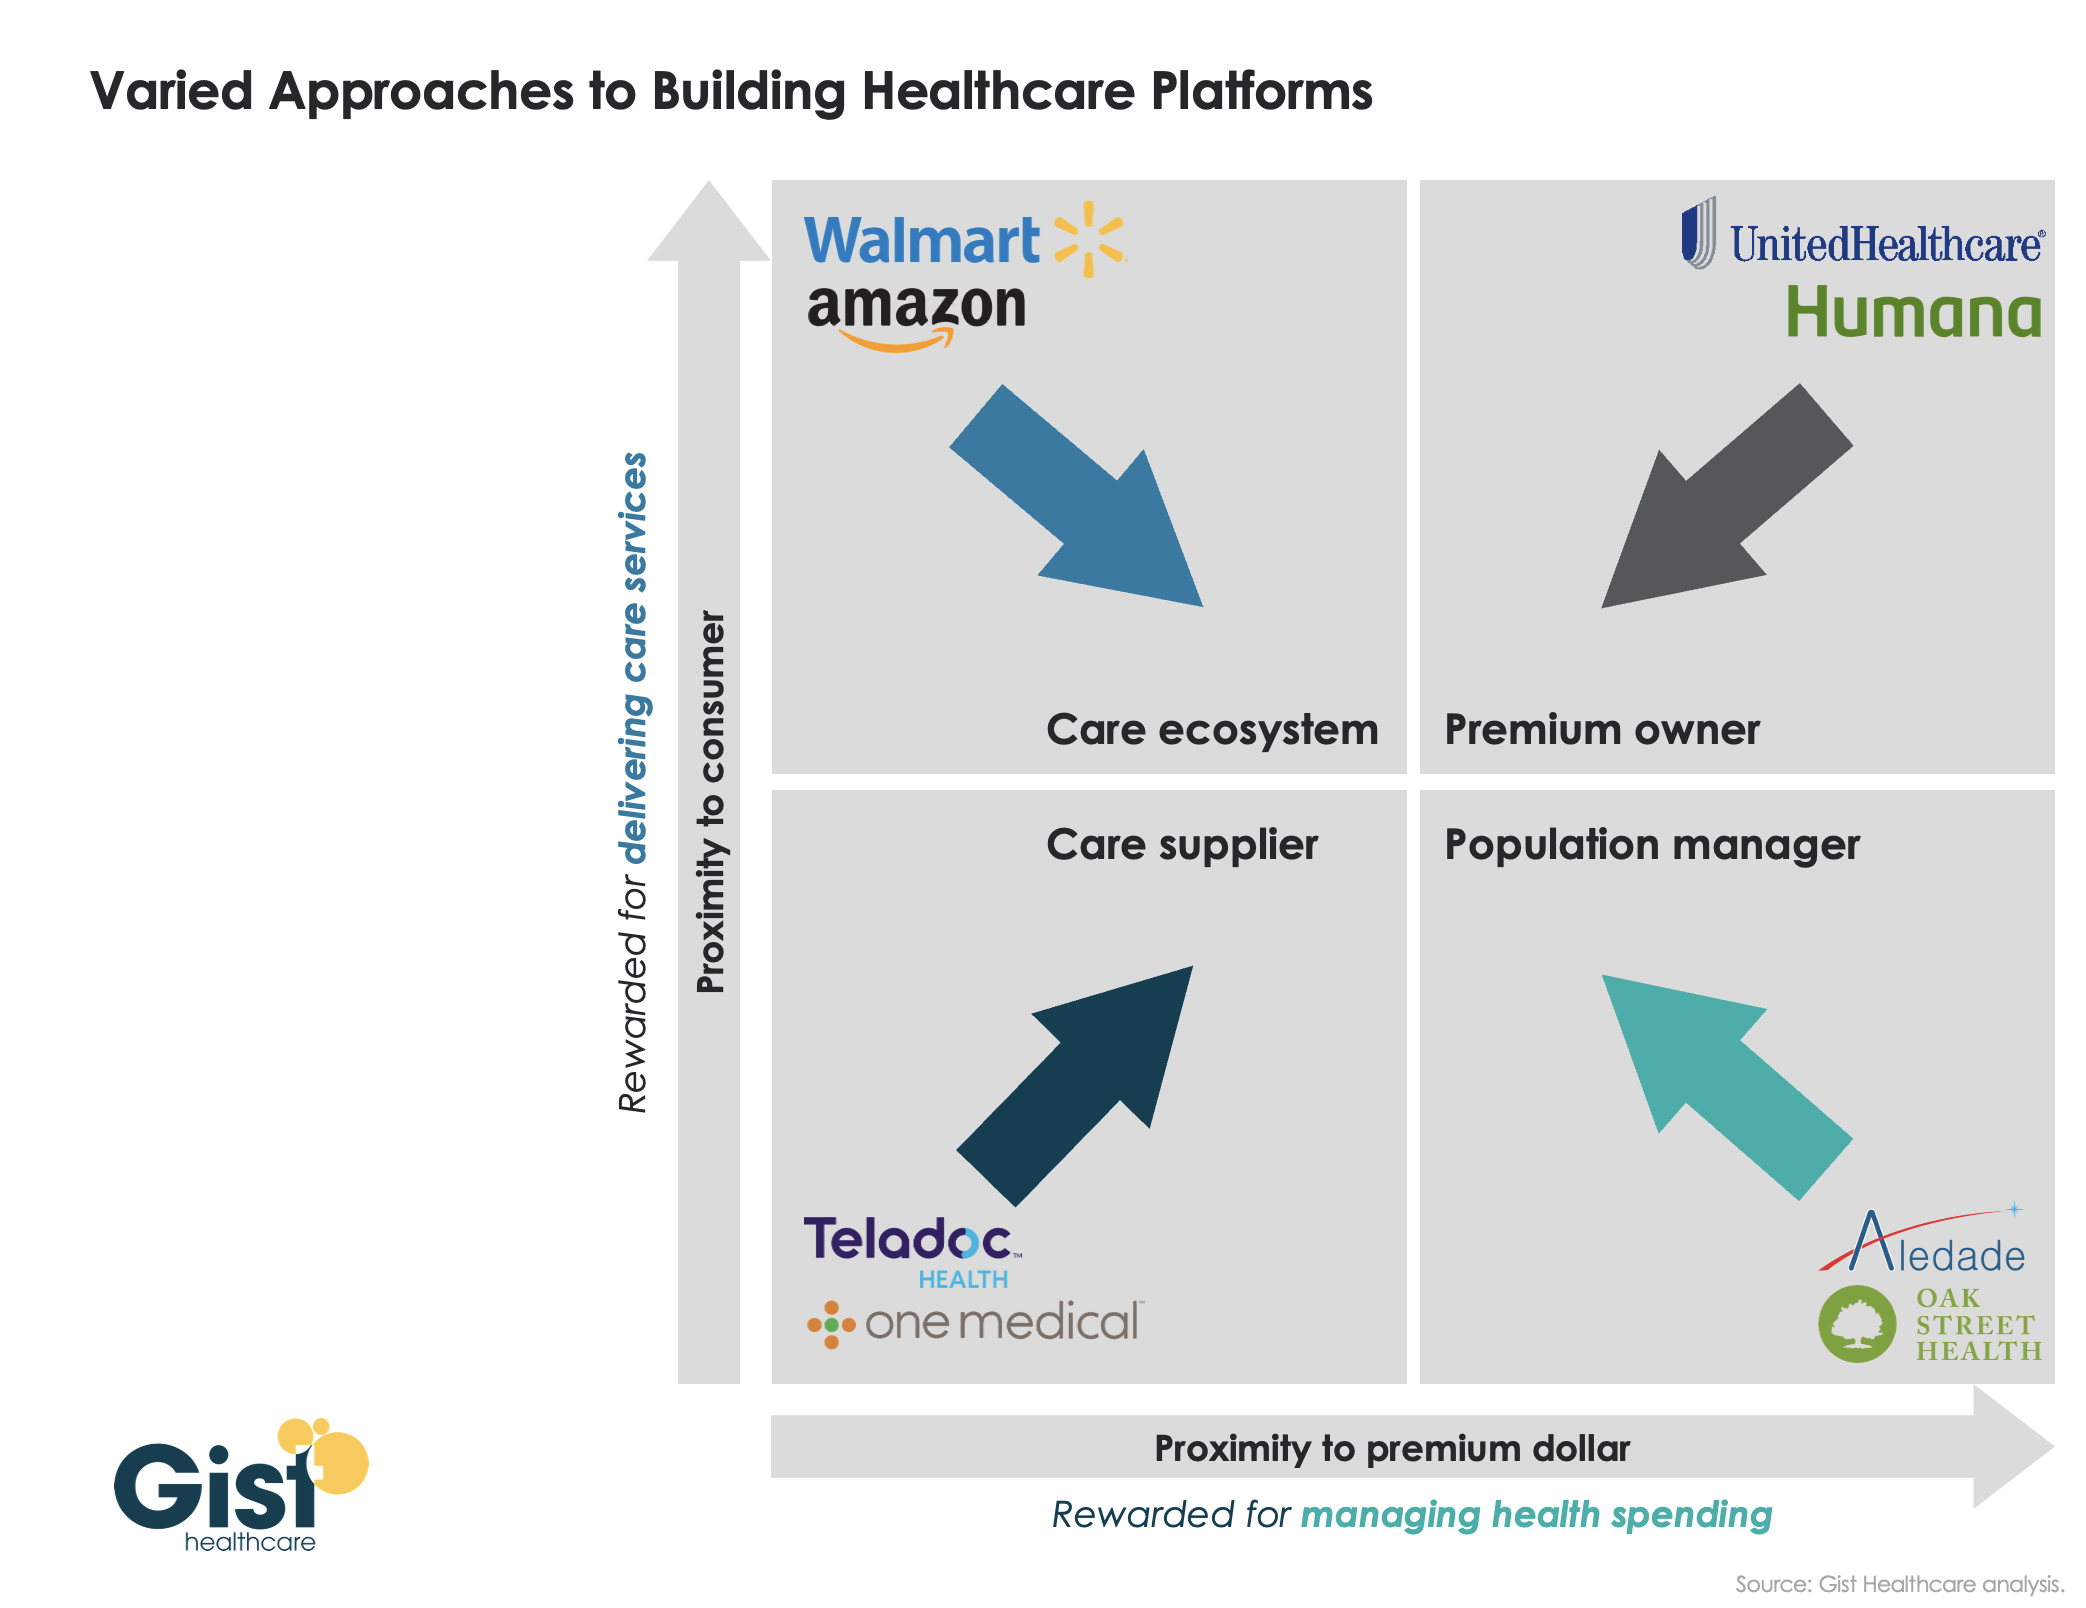
Last week, we introduced our framework for value delivery as a “healthcare platform”, in which an organization’s proximity to both the consumer and to the premium dollar determines how it competes as a “care supplier,” a “care ecosystem,” a “premium owner,” or a “population manager.” Traditionally, different healthcare companies have operated primarily in one of these four domains. However, as shown in the graphic below, we’ve recently seen many shift their business into one or more additional quadrants, as they seek to expand their value propositions. UnitedHealth Group is an obvious example: it has moved well beyond the traditional insurance business, via numerous provider and care delivery acquisitions across the continuum.
Other players have shifted from their own “pure play” positions toward more comprehensive “platform” strategies as well: One Medical adding Iora Health to enhance population health capabilities; Walmart moving beyond retail and pharmacy services, partnering with Oak Street Health to expand its ability to manage Medicare patients; Amazon getting into the employer health business.
There’s a clear pattern emerging—value propositions are converging on a “strategic high ground” that encompasses all four dimensions of platform value, creating a comprehensive set of solutions to deliver accessible care, promote health, and grow consumer loyalty, with an aligned financial model centered on managing the total cost of care. Health systems looking to build platform strategies will find many of these competitors also vying for pride of place as the “platform of choice” for healthcare consumers and purchasers.
This week we heard from three healthcare executives that they’ve seen a recent uptick in emergency department (ED) volumes. As we’ve discussed before, ED visits plummeted at the beginning of the pandemic, and were the slowest class of care volume to rebound. Over the past year, many systems reported that ED volume had remained persistently stuck at 10 to 15 percent lower than pre-COVID levels, leading us to question whether there had been a secular shift in patient demand, with consumers choosing alternative options like telemedicine or urgent care as a first stop for minor acute care needs.
An uptick in ED volume would be welcome news to many hospital executives, as the emergency department is the source of half or more of inpatient admissions for many hospitals. But according to what we’re hearing, the recent rise in emergency department patient volume has not resulted in an expected bump in inpatient volume.
“We’ve dug into it, and it seems like the jump in ED visits is a function of COVID,” one leader shared. “There’s just so much COVID out there now…even though the disease is milder, there are still a lot of patients coming to the ED. But unlike last year, most aren’t sick enough to be admitted.”
And ED visits for other causes have not rebounded in the same way: “We’re hoping patients aren’t still staying away because they’re afraid of catching the virus.” We’ll be watching closely across the summer to see how volumes trend as the pandemic waxes and wanes across the country—we’d still bet that many consumers have changed their thinking on where and how they will seek care when the need arises.
When Congress passed the “No Surprises Act” in 2021, credit rating agencies like Moody’s warned that the bill would hurt physician staffing firms, especially those that provide emergency department (ED) services, which result in a surprise bill in roughly one in five visits. A piece from investigative outlet The Lever highlights how one private equity-backed physician staffing firm, Nashville-based American Physician Partners, is responding to the resultant cash flow challenges by cutting ED physician pay, after already reducing staffing levels. As the article describes, this is possible in an otherwise tight labor market because, unlike many other specialties, there’s an oversupply of ED physicians, due to the rapid growth in emergency medicine residency programs over the last decade.
The Gist: With two-thirds of hospitals outsourcing at least some ED physician labor, the potential insolvency of large physician staffing firms could bring a crisis in access and coverage.
In addition to revenue cuts tied to the surprise billing ban, rising interest rates also mean that PE firms may soon find it more difficult to fund their aggressive growth strategies.
Health systems should proactively evaluate their partnerships with PE-backed physician staffing groups, with an eye toward anticipating potential staffing problems and service quality shortfalls.
The for-profit, 39-hospital Steward system manages 171K lives across the Medicare Advantage, Medicare shared savings, and Medicare direct contracting programs. This deal will allow Miami-based CareMax, a publicly-traded, value-based care company with 42 senior centers (mostly in Florida) and 34K lives under management, to expand across Steward’s footprint, which includes Texas and Arizona, states with rapidly growing Medicare populations.
The Gist:This deal is an example of the rise of venture-funded MSO (medical services organization) services that aim to subsume and scale value-based care functions from hospitals and medical groups. Steward wagers it can find greater success in managing risk in partnership with CareMax, moving a greater share of its Medicare population into risk, and outsourcing care management and patient engagement functions.
Many health systems have spent substantial resources building out accountable care organizations and risk-based Medicare businesses over the last decade. While selling these assets to a company like CareMax may be one way to generate a return, particularly for those frustrated by lower-than-anticipated gains from moving to value-based care, it also requires relinquishing control of functions likely central to the future health system business model.











 HENRY KOTULA
