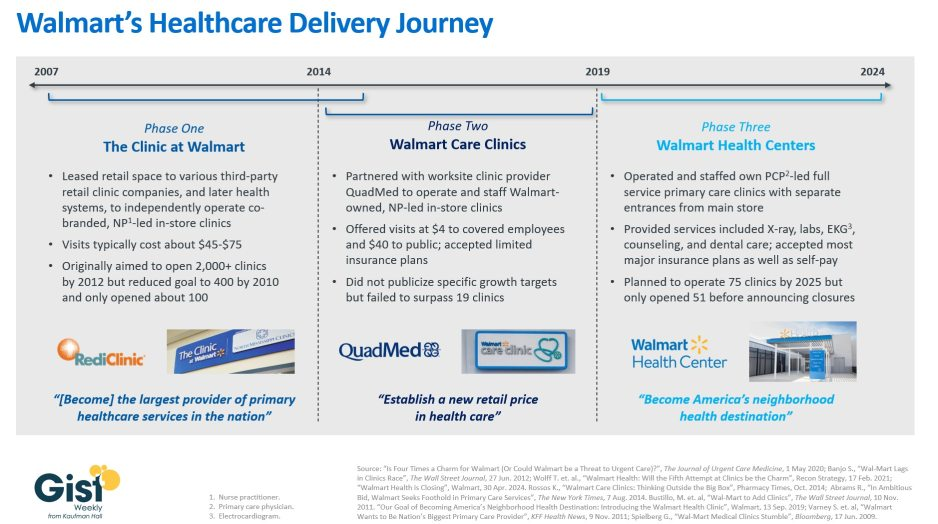
With Walmart’s announcement last week that it plans to shutter its Walmart Health business, this week’s graphic takes stock of the company’s healthcare delivery journey over nearly the past two decades.
In about 2007, Walmart launched “The Clinic at Walmart,” which leased retail space to various third-party retail clinic companies, and then later health systems, to provide basic primary care services inside Walmart stores, with the ambition of eventually becoming “the largest provider of primary healthcare services in the nation.”
However, low volumes and incompatible incentives between Walmart and its contractors led most of these clinics to close over time. In 2014 Walmart partnered with a single company, the worksite clinic provider QuadMed, to launch “Walmart Care Clinics.” These in-store clinics offered $4 visits for covered Walmart employees and $40 visits for the cash-paying public. Despite these low prices, this iteration of care clinic also suffered from low volumes, and Walmart scrapped the idea after opening only 19 of them.
The retail giant’s most recent effort at care delivery began in 2019 with its revamped “Walmart Health Centers,” which it announced alongside its goal to “become America’s neighborhood health destination.”
These health centers, which had separate entrances from the main store, featured physician-led, expanded primary care offerings including X-ray, labs, counseling, and dental services. As recently as April 2024, Walmart said it was planning to open almost two dozen more within the calendar year, until it announced it was shutting down its entire Walmart Health unit, which included virtual care offerings in addition to 51 health centers, citing an unfavorable operating environment.
Despite multiple rebranding efforts, consumers have thus far appeared unwilling to see affordability-focused Walmart as a healthcare provider.
Almost two decades of clinic experimentation have shown the company is willing to try things and admit failure, but it remains to be seen if this is just the end of Walmart’s latest phase or the end of the road for its healthcare delivery ambitions altogether.
“Incrementalism.” The word is perceived as the enemy of hope for universal health care in the United States.
Those who advocate for single-payer, expanded Medicare for all tend to be on the left side of the political spectrum, and we have advanced the movement while pushing back on incremental change. But the profit-taking health industry giants in what’s been called the medical-industrial complex are pursuing their own incremental agenda, designed to sustain the outrageously expensive and unfair status quo.
In recent years, as the financial sector of the U.S. economy has joined that unholy alliance, scholars have begun writing about the “financialization” of health care.
It has morphed into the medical-financial-industrial complex (MFIC) so vast and deeply entrenched in our economy that a single piece of legislation to achieve our goal–even with growing support in Congress–remains far short of enough votes to enact.
If we are to see the day when all Americans can access care without significant financial barriers, policy changes that move us closer to that goal must be pursued as aggressively as we fight against the changes that push universal health care into the distant future. Labeling all positive steps toward universal health care as unacceptable “incrementalism” could have the effect of aiding and abetting the MFIC and increase the chances of a worst-case scenario: Medicare Advantage for all, a goal of the giants in the private insurance business. But words matter. Instead of “incremental,” let’s call the essential positive steps forward as “foundational” and not undermine them.
The pandemic crisis exposed the weaknesses of our health system. When millions of emergencies in the form of COVID-19 infections overtook the system, most providers were ill-prepared and understaffed. More than 1.1 million U.S. citizens died of COVID-19-related illness, according to the Centers for Disease Control.
For years, the MFIC had been advancing its agenda, even as the U.S. was losing ground in life expectancy and major measures of health outcomes. While health care profits soared in the years leading up to and during the pandemic, those of us in the single-payer movement demanded improved, expanded Medicare for all. And we were right to do so. Progress came through almost every effort. The number of advocates grew, and more newly elected leaders supported a single-payer plan. Bernie Sanders’ 2016 presidential bid proved that millions of Americans were fed up with having to delay or avoid care altogether because it simply cost too much or because insurance companies refused to cover needed tests, treatments and medications.
But as the demand for systemic overhaul grew, the health care industry was making strategic political contributions and finding ways to gain even more control of health policy and the political process itself.
Over the years, many in the universal health care movement have opposed foundational change for strategic reasons. Some movement leaders believed that backing small changes or tweaks to the current system at best deflected from our ultimate goal. And when the Patient Protection and Affordable Care Act was passed, many on the left viewed it as a Band-Aid if not an outright gift to the MFIC. While many physicians in our movement knew that the law’s Medicaid expansion and the provisions making it illegal for insurers to refuse coverage to people with preexisting conditions would save many thousands of lives, they worried that the ACA would further empower big insurance companies. Both positions were valid.
After the passage of the ACA, more of us had insurance cards in our wallets and access to needed care for the first time, although high premiums and out-of-pocket costs have become insurmountable barriers for many. Meanwhile, industry profits soared.
The industry expanded its turf. Hospitals grew larger, stand-alone urgent care clinics, often owned by corporate conglomerates, opened on street corners in cities across the country, private insurance rolls grew, disease management schemes proliferated, and hospital and drug prices continued the march upward. The money flowing into the campaign coffers of political candidates made industry-favored incremental changes an easier lift.
To change this “system” would require an overhaul of the whole economy. Single-payer advocates must consider that herculean task as they continue their work. We must understand that the true system of universal health care we envision would also disrupt the financial industry – banks, collection agencies, investors – an often-forgotten but extraordinarily powerful segment of the corporate-run complex.
Even if the research and data show that improved, expanded Medicare for all would save money and lives (and they do show that), that is not motivating for the finance folks, who fear that without unfettered control of health care, they might profit less. Eliminating medical bills and debt would be marvelous for patients but not for a large segment of the financial community, including bankruptcy attorneys.
Following the money in U.S. health care means understanding how deep and far the tentacles of profit reach, and how embedded they are now.
We know the MFIC positioned itself to continue growing profits and building more capacity. The industry made steady, incremental progress toward that goal. There is no illusion that better overall health for Americans is the mission of the stockholders who drive this industry. No matter what the marketers tell us, patients are not their priority. If too many of us get healthier, we might not use as much care and generate as much money for the owners and providers. Private insurers want enough premiums and government perks to keep flowing their way to keep the C-Suite and Wall Street happy.
More than health insurers
Health insurers are far from the only rapidly expanding component of the MFIC. A recent documentary, “American Hospitals: Healing a Broken System,” for example, explores a segment of the U.S. health industry that is often overlooked by policymakers and the media. Though they were unprepared for the national health crisis, hospitals endured the pandemic in this country largely because the dedicated doctors, nurses and ancillary staff risked their own lives to keep caring for COVID-19 patients while everything from masks, gowns and gloves to thermometers and respirators were in short supply. But make no mistake, many hospitals were still making money through the pandemic. In fact, some boosted their already high profits, and private insurance companies had practically found profit-making nirvana. Patients put off everything from colonoscopies to knee replacements, physical therapy to MRIs. Procedures not done meant claims not submitted, while monthly insurance premiums kept right on coming and right on increasing.
The pandemic was a time of turmoil for most businesses and families, yet the MFIC took its share of profits. It was pure gold for many hospitals until staffing pressures and supply issues grew more dire, COVID patients were still in need of care, and more general patient care needs started to reemerge.
We might be forgiven for thinking there wasn’t much regulating or legislating done around health care during the pandemic years. We’d be wrong. There was a flurry of legislation at the state level as some states took on the abuses of the private insurance industry and hospital billing practices.
And the movement to improve and expand traditional Medicare to cover all of us stayed active, though somewhat muted. The bills before Congress that expanded access to Medicaid during the pandemic through a continuous enrollment provision offered access to care for millions of people. Yet as that COVID-era expansion ended, many of those patients were left without coverage or access to care. This might have been a chance to raise the issue loudly, but the social justice movement did not sufficiently activate national support for maintaining continuous enrollment in Medicaid. Is that the kind of foundational change worth fighting for? I would argue it most certainly is.
As those previously covered by Medicaid enter this “unwinding” phase, many will be unable to secure equivalent or adequate health insurance coverage. The money folks began to worry as coverage waned. After all, sick people will show up needing care and they will not be able to pay for it. As of this writing, patient advocacy groups are largely on the sidelines.
But Allina Health took action. The hospital chain announced it would no longer treat patients with medical debt. After days of negative press, the company did an about-face.
Throughout the country, even as the pandemic loomed, the universal, single-payer movement focused on explaining to candidates and elected officials why improving and expanding Medicare to cover all of us not only is a moral imperative but also makes economic sense. In many ways, the movement has been tremendously effective: More than 130 city and county governing bodies have passed resolutions in support of Medicare for all, including in Seattle, Denver, Cincinnati, Washington, D.C., Tampa, Sacramento, Los Angeles, St. Louis, Atlanta, Duluth, Baltimore, and Cook County (Chicago).
The Medicare for All Act, sponsored by Rep Pramila Jayapal (D-Wash.) and Sanders (I-Vt.) has 113 co-sponsors in the House and 14 in the Senate. Another bill allowing states to establish their own universal health care programs has been introduced in the House and will be introduced soon in the Senate.
Moving us closer
The late Dr. Quentin Young was a young Barack Obama’s doctor in Chicago. Young spoke to his president-in-the-making patient about universal health care and Obama, then a state legislator, famously answered that he would support a single-payer plan if we were starting from scratch. Many in the Medicare–for-all movement dismissed that statement as accepting corporate control of health care.
But Young would steadfastly advocate for single-payer health care for years to come and as one of the founding forces behind Physicians for a National Health Program. Once Dr. Young was asked if the movement should support incremental changes. He answered, “If a measure makes it easier and moves us closer to achieving health care for all of us, we should support that wholeheartedly. And if a measure makes it harder to get to single-payer, we need to oppose it and work to defeat that measure.” Many people liked that response. Others were not persuaded.
But in recent years, PHNP has become a national leader in a broad-based effort to halt the privatization of Medicare through so-called Medicare Advantage plans and other means. A case can be made that those are incremental/foundational but essential steps to achieving the ultimate goal.
We must fight incrementally sometimes, for instance when traditional Medicare is threatened with further privatization. Bit by painful bit, a program that has served this nation so well for more than 50 years will be carved up and given over to the private insurance industry unless the foundational steps taken by the industry are met with resistance and facts at every turn. We can achieve our goal by playing the short game as well as the long game. Foundational change can be and has been powerful. It just has to be focused on the health and well-being of every person.
ALSO: We’re premiering our Magic Translation Box to help you decipher corporate jargon and understand what’s coming down the pike.
If you are enrolled in an Aetna Medicare Advantage plan, now might be a good time to get more nervous than usual.
Wall Street is not happy with Aetna’s parent, CVS Health. In response to that unhappiness, triggered by the company’s admission that it has been paying more claims than usual, CVS execs have promised to do whatever it takes to get profit margins back to a level investors deem suitable.
That means the odds have increased that Aetna will refuse to cover the treatments and medications your doctor says you need. It also means CVS/Aetna likely will increase your premiums next year and might dump you altogether. The company has a long history of doing just that, as you’ll see below.
Medicare Advantage companies in general are facing what Wall Street financial analysts call headwinds, and those winds are now coming from several sources: increased Congressional scrutiny of insurers’ business practices, Biden administration efforts to end years of overpayments that have cost taxpayers hundreds of billions of dollars, enrollee discontent, and a gathering storm of negative press.
To understand the pressures CVS CEO Karen Lynch and her C-Suite team are under to satisfy the company’s remaining shareholders (many have fled), you need to know and understand what they told them in recent weeks–and what she undoubtedly will have to say again, with conviction, this coming Thursday when CVS holds its annual meeting of shareholders. You can be certain Lynch’s staff has prepared a binder chock full of the rudest questions she could face from rich folks (mostly institutional investors) who’ve become a little less rich in recent months as the golden calf calf called Medicare Advantage has lost some of its luster. (My former colleagues and I used to put together such a CEO-briefing binder during my Cigna days, which coincided with Lynch’s years at Cigna.)
To help with that understanding, we’re introducing the HEALTH CARE un-covered Magic Translation Box (MTB). We’ll fire it up occasionally to decipher the coded language executives use when they have to deal with analysts and investors in a public setting. We’ll start with what Lynch and her team told analysts on May 1 when CVS announced first-quarter 2024 results that caused a stampede at the New York Stock Exchange.
Lynch: We recently received the final 2025 (Medicare Advantage) rate notice (from the Center for Medicare and Medicaid Services), and when combined with the Part D changes prescribed by the Inflation Reduction Act, we believe the rate is insufficient. This update will result in significant added disruption to benefit levels and choice for seniors across the country. While we strive to deliver benefit stability to seniors, we will be adjusting plan-level benefits and exiting counties as we construct our bid for 2025. We are committed to improving margins.
Magic Translation Box: Can you believe it? CMS did not bend to industry pressure to pay MA plans what we demanded for next year. We only got a modest increase, not enough, in our opinion, to protect our profit margins. To make matters worse, starting next year we won’t be able to make people enrolled in Medicare prescription drug plans (Part D) pay more than $2,000 out of their own pockets, thanks to the Inflation Reduction Act President Biden signed in 2022. So, to make sure you, our most important stakeholder, once again have a good return on your investment, we will notify CMS next month that we will slash the value of Medicare Advantage plans by reducing or eliminating some benefits, like dental, hearing and vision, that attract people to MA plans in the first place. And, for good measure, we’ll be dumping Medicare Advantage enrollees who live in zip codes where we can’t make as much money as we’d like. For them: too bad, so sad. For you: more money in your bank account. And for extra good measure, to keep seniors from blaming greedy us for what we have in store for them, our industry will be bankrolling dark money ads to persuade voters that Biden and the Democrats are the bad guys cutting Medicare.
Later during CVS’s earnings call, CFO Thomas Cowhey reiterated Lynch’s remarks about reducing benefits.
Cowhey:So, we’ve given you all the pieces to kind of understand why we think it (Medicare Advantage) will lose a significant amount of money this year. But as you think about improvement there, obviously there’s a lot of work that we still need to do to understand what benefits we’re going to adjust and what ones we can and can’t…To the extent that we don’t believe we can credibly recapture margin in a reasonable period of time, we will exit those counties…(And) as we’ve all mentioned we’re going to be taking significant pricing actions and really it’s going to depend on what our competitors do.
Magic Translation Box: We’re under the gun to figure this out because we have to notify CMS by June 3 how much we will increase Medicare Advantage premiums and cut benefits next year and which counties we’ll abandon altogether. We’ll also be watching what our competitors do, but we know from what they’ve been telling you guys that they, too, will be dumping enrollees, hiking premiums and slashing benefits.
To make sure investors couldn’t miss what they were saying, Lynch jumped back into the conversation to make clear they knew they were #1 in her book:
Lynch: I’m just going to reiterate what I said in my prepared remarks. (You can bet what follows were prepared, too.) We are committed to improving margin in Medicare Advantage [emphasis added] and we will do so by pricing for the expected trends. We will do so by adjusting benefits and exiting service counties. And we are committed to doing that.
Magic Translation Box: Have I made myself clear? We will do whatever it takes to deliver the profits you expect. We will keep a closer eye on how much care people are trying to get and we’ll swing into action faster next time if we see evidence of an uptick. There will be carnage, but you guys rule. You mean a lot more to us than those old and disabled people who don’t have nearly as much money as you do in their bank accounts.
This will not be the first time Aetna has dumped health plan enrollees who were a drain on profits. In 2000, when Medicare Advantage was called Medicare+Choice, Aetna notified the Clinton administration it would stop offering Medicare plans in 14 states, affecting 355,000 people, more than half of Aetna’s total Medicare enrollment at the time. Other companies, including Cigna, did the same thing. My team and I wrote a press release to announce that Cigna would be bailing from almost all the markets where we sold private Medicare plans.
We of course blamed the federal government (i.e., the Democrats) for being the skinflints that made it necessary to bail. Our CEO at the time, Ed Hanway, said the government just couldn’t be relied upon to be a reliable “partner.”
Back then, just a relatively small percentage of Medicare beneficiaries were in private plans. Today, more than half of Medicare-eligible Americans are enrolled in a Medicare Advantage plan, which means the disruption could be much worse this time. Some people in counties where Aetna and other companies stop offering plans likely will not find a replacement plan with the same provider network, premiums and benefits.
But in most places, those who get dumped will be stuck in the volatile, often nightmarish Medicare Advantage world, unable to return to traditional Medicare and buy a Medicare supplement policy to cover their out-of-pocket obligations.
That’s because in all but a handful of states, seniors and disabled people will not be able to buy a Medicare supplement policy as cheaply as they could within six months of becoming eligible for Medicare benefits. After that, Medicare supplement insurers, including Aetna, get their underwriters involved. If your health isn’t excellent, expect to pay a king’s ransom for a Medigap policy.
This is National Hospital week. It comes at a critical time for hospitals:
The U.S. economy is strong but growing numbers in the population face financial insecurity and economic despair. Increased out-of-pocket costs for food, fuel and housing (especially rent) have squeezed household budgets and contributed to increased medical debt—a problem in 41% of U.S. households today. Hospital bills are a factor.
The capital market for hospitals is tightening: interest rates for debt are increasing, private investments in healthcare services have slowed and valuations for key sectors—hospitals, home care, physician practices, et al—have dropped. It’s a buyer’s market for investors who hold record assets under management (AUM) but concerns about the harsh regulatory and competitive environment facing hospitals persist. Betting capital on hospitals is a tough call when other sectors appear less risky.
Utilization levels for hospital services have recovered from pandemic disruption and operating margins are above breakeven for more than half but medical inflation, insurer reimbursement, wage increases and Medicare payment cuts guarantee operating deficits for all. Complicating matters, regulators are keen to limit consolidation and force not-for-profits to justify their tax exemptions. Not a pretty picture.
And, despite all this, the public’s view of hospitals remains positive though tarnished by headlines like these about Steward Health’s bankruptcy filing last Monday:
The public is inclined to hold hospitals in high regard, at least for the time being. When asked how much trust and confidence they have in key institutions to “to develop a plan for the U.S. health system that maximizes what it has done well and corrects its major flaws,” consumers prefer for solutions physicians and hospitals over others but over half still have reservations:
A Great Deal
Some
Not Much/None
Health Insurers
18%
43%
39%
Hospitals
27%
52%
21%
Physicians
32%
53%
15%
Federal Government
14%
42%
44%
Retail Health Org’s
21%
51%
28%
The American Hospital Association (AHA) is rightfully concerned that hospitals get fair treatment from regulators, adequate reimbursement from Medicare and Medicaid and protection against competitors that cherry-pick profits from the health system.
It can rightfully assert that declining operating margins in hospitals are symptoms of larger problems in the health system: flawed incentives, inadequate funding for preventive and primary care, the growing intensity of chronic diseases, medical inflation for wages, drugs, supplies and technologies, the dominance of ‘Big Insurance’ whose revenues have grown 12.1% annually since the pandemic and more. And it can correctly prove that annual hospital spending has slowed since the pandemic from 6.2% (2019) to 2.2% (2022) in stark contrast to prescription drugs (up from 4% to 8.4% and insurance costs (from -5.4% to +8.5%). Nonetheless, hospital costs, prices and spending are concerns to economists, regulators and elected officials.
National health spending data illustrate the conundrum for hospitals: relative to the overall CPI, healthcare prices and spending—especially outpatient hospital services– are increasing faster than prices and spending in other sectors and it’s getting attention: that’s problematic for hospitals at a time when 5 committees in Congress and 3 Cabinet level departments have their sights set on regulatory changes that are unwelcome to most hospitals.
My take:
The U.S. market for healthcare spending is growing—exceeding 5% per year through the next decade. With annual inflation targeted to 2.0% by the Fed and the GDP expected to grow 3.5-4.0% annually in the same period, something’s gotta’ give. Hospitals represent 30.4% of overall spending today (virtually unchanged for the past 5 years) and above 50% of total spending when their employed physicians and outside activities are included, so it’s obvious they’ll draw attention.
Today, however, most are consumed by near-term concerns– reimbursement issues with insurers, workforce adequacy and discontent, government mandates– and few have the luxury to look 10-20 years ahead.
I believe hospitals should play a vital role in orchestrating the health system’s future and the role they’ll play in it. Some will be specialty hubs. Some will operate without beds. Some will be regional. Some will close. And all will face increased demands from regulators, community leaders and consumers for affordable, convenient and effective whole-person care.
For most hospitals, a decision to invest and behave as if the future is a repeat of the past is a calculated risk. Others with less stake in community health and wellbeing and greater access to capital will seize this opportunity and, in the process, disable hospitals might play in the process.
Near-term reactive navigation vs. long-term proactive orchestration–that’s the crossroad in front of hospitals today. Hopefully, during National Hospital Week, it will get the attention it needs in every hospital board room and C suite.
PS: Last week, I wrote about the inclination of the 18 million college kids to protest against the healthcare status quo (“Is the Health System the Next Target for Campus Unrest?” The Keckley Report May 6, 2024 www.paulkeckley.com). This new survey caught my attention:
According to the Generation Lab’s survey of 1250 college students released last week, healthcare reform is a concern. When asked to choose 3 “issues most important to you” from its list of 13 issues, healthcare reform topped the list. The top 5:
Health Reform (40%)
Education Funding and access (38%)
Economic fairness and opportunity (37%)
Social justice and civil rights (36%)
Climate change (35%)
If college kids today are tomorrow’s healthcare workforce and influencers to their peers, addressing the future of health system with their input seems shortsighted. Most hospital boards are comprised of older adults—community leaders, physicians, et al.
And most of the mechanisms hospitals use to assess their long-term sustainability is tethered to assumptions about an aging population and Medicare.
College kids today are sending powerful messages about the society in which they aspire to be a part. They’re tech savvy, independent politically and increasingly spiritual but not religious. And the health system is on their radar.
Back in 2020, Steward Health Care System needed $400 million to dig it “out of a deep financial hole.” Instead of investing in the struggling health system, Steward’s owner, Cerberus Capital Management, reportedly convinced Steward’s landlord, Medical Properties Trust (MPT), to provide the cash infusion.
Cerberus also sold its majority stake in Steward to a group that included the health system’s CEO Ralph de la Torre, MD, WSJ reported.
MPT had to put up millions of dollars for its tenant over a series of financial deals, and recent Congressional inquiries uncovered more details about how that went down. The first part of the cash infusion came in $205 million from MPT to invest in overseas hospitals in a joint venture with Steward. The second half was covered when MPT forgave the mortgage for a Steward hospital and paid $200 million for two Utah hospitals.
In the end, Cerberus ended up with a whopping $800 million in profit while Steward filed for Chapter 11 bankruptcy this week, WSJ reported.
Oh, and de la Torre bought a $40 million yacht with the proceeds of a 2021 payout related to his ownership of Steward.
As Medicare Advantage grows bigger and bigger, there’s one area the industry and regulators haven’t figured out how to make work yet: hospice.
Why it matters:
The end-of-life care option is the only Medicare service that can’t be offered in the private-run alternative, which now covers over half of enrollees.
Medicare is winding down an experiment — years earlier than expected — that let some Medicare Advantage plans offer a hospice benefit, citing operational challenges and limited interest from insurers and hospices.
Catch up quick:
Usually, when a Medicare Advantage beneficiary decides to enter hospice after receiving a terminal diagnosis, traditional Medicare pays for this care while they remain enrolled in their private plan.
That could make navigating insurance “very, very clunky” for hospice patients, especially when they have health care needs unrelated to their terminal illness, said Lynne Sexten, CEO of Agrace Hospice.
And this affects a lot of people. Nearly half of the 1.7 million Medicare Advantage beneficiaries who died in 2022 used hospice services, according to the Medicare Payment Advisory Commission (MedPAC).
Experts say the roots of this awkward arrangement likely goes back about 40 years, when private Medicare first became a permanent offering. At the time, traditional Medicare had just startedcovering hospice, so officials had limited data on how much it cost.
What they did:
Medicare’s Innovation Center began an experiment in 2021 that allowed Medicare plans to contract directly with hospice providers.
It aimed to test whether that could make end-of-life care transitions more seamless for Medicare Advantage patients while reducing costs and improving care quality.
Participating health plans also covered palliative care and transitional care, where patients continued curative treatments like dialysis or chemotherapy temporarily during their hospice stay.
The Innovation Center announced abruptly in March that it would end the program in December, a year after officials said it would run through 2030.
The news came after two major insurers — UnitedHealth Group and Elevance — pulled out of the model. Only 13 insurers participated this year.
Hospices largely cheered the decision. Lower reimbursement rates, delayed payment from insurers and burdensome quality reporting made the experiment difficult for hospices that chose to contract with insurers, an independent evaluation of the program found.
The Centers for Medicare and Medicaid Services stressed that its decision to end the experiment doesn’t meanit failed, and the agency in a statement to Axios said it will continue to evaluate results.
Many insurers also faced a learning curve on how to work with hospice for their Medicare enrollees. Hospice is delivered and paid for differently than other Medicare benefits.
The experiment tried to do too much too fast, said Kevin Kappel, vice president at SCAN Health Plan, a nonprofit insurer that joined Medicare’s hospice experiment last year.
“I think people underestimated how complex it was to do. … We’ve learned a lot,” Kappel said.
Yes, but:
Hospices and insurers said they still need to figure out how to make care more seamless for Medicare Advantage beneficiaries.
“This is by no means the end of the story for end-of-life care providers and MA plans,” said Ethan McChesney, policy director at the National Partnership for Healthcare and Hospice Innovation.
It’s been a full decade since MedPAC, the congressional advisory committee, recommended including hospice in Medicare Advantage, warning that excluding it“fragments care accountability and financial responsibility for MA enrollees who elect hospice.”
What we’re watching:
Industry leaders say hospice doesn’t necessarily have to become part of Medicare Advantage to improve care integration, or at least not right away.
Ohio’s Hospice, a nonprofit provider that participated in the Medicare experiment, said it will continue working with Medicare plans to extend palliative care and symptom management to more patients, CEO Kent Anderson said.
While Anderson said some peers worry about the growth of Medicare Advantage, “the longer we sit outside the managed care world, the less relevant we’ll become.”
Expenses per provider remained considerably higher than revenue generated in the first quarter of 2024, although there are signs the gap could be closing, according to the Kaufman Hall “Physician Flash Report,” released May 2.
Kaufman Hall based their findings on a monthly report from Syntellis Performance Solutions, part of Strata. The report gathered data from more than 200,000 employed providers, including physicians and advanced practice providers.
Net patient revenue per provider full-time equivalent was $383,881 for the first quarter, up 4% from the same period last year. Total direct expenses per provider FTE hit $620,729 for the quarter. Expense growth has slowed over the last three years, with a 5% growth from 2022 to 2023 and just 3% growth from 2023 to 2024.
“Labor expenses are a growing proportion of total expenses, a trend that is unlikely to change significantly. Organizations should shift from optimizing downstream revenue to optimizing downstream margins,” the report authors advised, noting hospitals and physician organizations can evaluate provider specialties by outcomes or other metrics when they aren’t big revenue drivers.
Provider productivity was up 4% as measured by work relative value units. Physician wRVU per FTE was 5,979 for the first quarter, up 6% year over year. Physician compensation jumped 3% to $364,319, down from 6% growth between 2022 to 2023.
Labor expenses continue to rise while support staff decline across specialties. Labor was 84% of total expenses in the first quarter, and support staff per 10k provider wRVUs dropped 6% year over year to 3.14, even after an 8% drop from 2022 to 2023. Report authors recommended organizations find better ways to use APPs for higher physician productivity.
Here are specific data points from the first quarter report.
Median net patient revenue per provider FTE by specialty cohort were:
Medicare Advantage insurers are planning to pare down their plan offerings in 2025.
Facing lower reimbursement rates from CMS and higher medical costs, many plan executives said they will prioritize margins over growing their membership numbers.
Brian Kane, CEO of Aetna, told investors May 1 that the company will prioritize “margins over membership” in 2025. The company will exit counties where it believes it can’t be profitable, Mr. Kane said.
“It’s hard to say right now that we won’t have a meaningful decrease in membership,” Mr. Kane said. “It’s certainly possible.”
Aetna’s competitors will be faced with the same choices, Mr. Kane said.
Humana executives also said the company is eyeing market exits in 2025. Susan Diamond, Humana’s CFO, said the company is expecting a net decline in its MA membership next year.
“Whether that is incrementally larger or smaller based on the other plans will be very dependent on what we see across the competitive landscape,” Ms. Diamond said April 24.
On first-quarter earnings calls, payer executives told investors they are disappointed in CMS’ 2025 rate notice. The notice will decrease benchmark payments, which insurers say amounts to a cut in funding for the program.
Medical costs are also on the rise in Medicare Advantage. CVS Health told its investors that Medicare Advantage costs keep climbing, partly driven by seasonal inpatient admissions. Outpatient services, including mental health and pharmacy, and dental spending also increased costs, CVS said.
In its final rate notice published April 1, CMS said it was aware Medicare Advantage organizations were reporting rising costs but was “not aware of all of the specific drivers accounting for the experience of these MA organizations. We have reviewed incomplete fourth quarter 2023 Medicare FFS incurred experience and it is consistent with our projections.”
Payers have also said they will cut back on supplemental benefits to account for lower rates.
CVS Health CEO Karen Lynch said it wil adjust plan-level benefits in 2025. The company led the industry in growth in 2024 but was a “notable outlier” compared to its peers in adding on supplemental benefits to entice members, The Wall Street Journalreported May 1.
Some Aetna plans offer a fitness reimbursement, according to The Wall Street Journal. Members could cash in the benefit for pickleball paddles, golf clubs and other sports equipment — but these extras could be a thing of the past in a tougher rate environment.
While every payer criticized CMS’s proposed rates, some executives said they would hold off on discussing their specific strategy until final bids are due. Insurers must send their MA plan proposals for 2025 to CMS by early June.
“It’s too early to provide specifics for the 2025 bid at this stage,” Elevance Health CEO Gail Boudreaux told investors. “I’m going to repeat, we’re looking to really balance growth and margins.”