Surging flu and RSV cases suggest difficult winter ahead

https://mailchi.mp/f1c5ab8c3811/the-weekly-gist-october-28-2022?e=d1e747d2d8

Early into flu season, nationwide flu activity is ten times higher than at the same point last year. Meanwhile, cases of respiratory syncytial virus (RSV), a virus most severe in young children and the elderly, have tripled in the past two months, with some children’s hospitals reporting “unprecedented” admissions for the virus. And most experts expect at least some winter COVID surge, possibly involving several different variants. The combined threat of these viruses circulating together has been labeled a potential “tripledemic.” 

The Gist: Across the past two winters, the widespread adoption of COVID prevention measures, including masking and social distancing, kept the spread of other viruses at bay. But with return to normal life for most Americans, other viruses have returned to circulation—and with a vengeance, as population immunity toward flu and RSV has weakened. 

While it’s hard to predict when and where local surges will occur, hospitals struggling with staffing shortages may be forced to hire more contract labor to care for an influx of patients—making this a potentially challenging winter for already stretched facilities.


Affordable Care Act (ACA)’s required coverage of preventive care services in further jeopardy

https://mailchi.mp/f1c5ab8c3811/the-weekly-gist-october-28-2022?e=d1e747d2d8

The plaintiffs in Braidwood v. Becerra filed a motion on Monday asking a US District Court judge in Texas—the same judge who ruled the entire ACA unconstitutional in 2018—to block enforcement of the ACA’s no-cost requirement for preventive care services. This judge already sided with the plaintiffs in September, ruling the government cannot require a company to fully cover preventive HIV drugs, also known as PrEP therapy, for its employees, on the grounds that doing so violates owners’ religious freedom.

In that ruling, the judge also asserted that the government’s system for deciding what preventive care services should be covered under the ACA is unconstitutional. This latest motion now asks him to invalidate all parts of the ACA requiring preventive health services on the grounds that the Preventive Services Task Force was never appointed by Congress, and thus lacks the authority to say which services insurers must cover. The final ruling is expected early next year, after which the case will certainly be appealed, regardless of outcome. 

The Gist: Given the judge’s initial ruling in Braidwood last month, this motion from the plaintiffs was expected. While the US Supreme Court reversed a 2018 ruling by this judge that struck down the entire ACA, it could potentially find the narrow targeting of this case more reasonable, making preventive care coverage optional for employers. 

If that happens, millions of Americans would once again have to pay for some of the most common and highest-value healthcare services, including screening tests for a variety of cancers, sexually transmitted infections, and diabetes. That additional financial burden, along with likely tightening of health plan benefit designs, would create barriers to access and exacerbate health disparities.

Purported Medicare profits spark criticism of North Carolina hospitals’ charity care spending

https://mailchi.mp/f1c5ab8c3811/the-weekly-gist-october-28-2022?e=d1e747d2d8

Drawing on a report published by the North Carolina State Health Plan for Teachers and State Employees, a recent Kaiser Health News article shines a light on the lack of transparency in financial reporting of not-for-profit hospitals’ community benefit obligations.

The report claims many North Carolina hospitals—including the state’s largest system, Atrium Health—show profits on Medicare patients in their cost report filings, while at the same time claiming sizable unrecouped losses on Medicare patients as a part of their overall community benefit analyses.

The Gist: These kind of reporting discrepancies draw attention to the controversial issue of whether not-for-profit hospitals provide sufficient community benefit to compensate for their tax-exempt status, which was worth nearly $2 billion in 2020 for North Carolina hospitals alone. 

Greater transparency around charity care, community benefit, and losses sustained from public payers could go a long way toward shoring up stakeholder support for not-for-profit institutions at a time when their political goodwill has deteriorated. Hospitals should be proactive on this front, as political leaders increasingly train their sites on high hospital spending in the current tight economic environment. 

COVID’s lingering effects on the US workforce

https://mailchi.mp/f1c5ab8c3811/the-weekly-gist-october-28-2022?e=d1e747d2d8

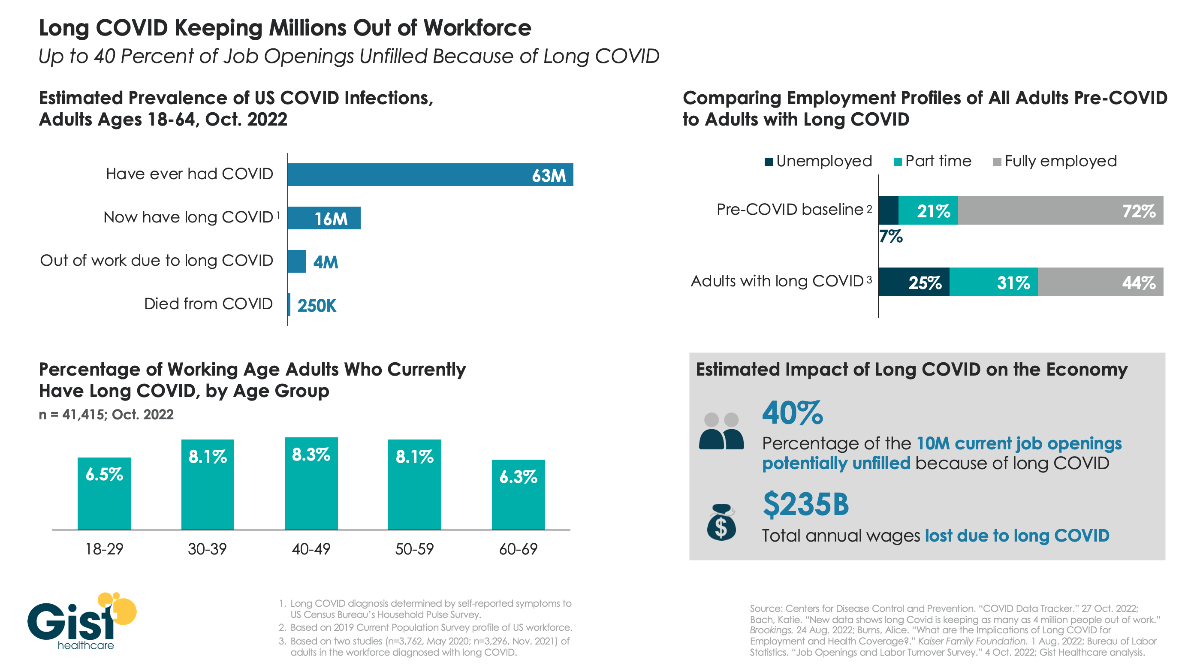
As the nation continues to grapple with the fallout from COVID, one of the greatest unknowns is “long COVID”, the broad range of health problems experienced by a significant number of individuals after contracting the virus. The Centers for Disease Control and Prevention defines long COVID as any post-COVID condition lasting three months or longer.

In the graphic above, we aim to quantify the prevalence of long COVID and its ongoing impact on the US workforce. While estimates for these numbers vary, data compiled by Brookings show that COVID infections in roughly one in four working age adults have resulted in long COVID, and up to one in four individuals with long COVID are unable to work due to their lingering health problems. Long COVID is also more prevalent in middle-aged adults, who are often at the peak of their working years. Dealing with symptoms like chronic fatigue and brain fog, long COVID patients are more likely to be unemployed or working reduced hours, compared to a pre-COVID baseline of the general adult population. 

While it’s difficult to assess the precise impact on the nation’s current labor shortage, the estimate that 4M working age adults are no longer working because of long COVID equals about 40 percent of the 10M total job openings in August of this year, undoubtedly exacerbating ongoing economic challenges. 

Where do patients go when hospitals shut down capacity?

https://mailchi.mp/f1c5ab8c3811/the-weekly-gist-october-28-2022?e=d1e747d2d8

Last week we met the CEO of the flagship hospital of a large academic health system. Like nearly every hospital, they are challenged in finding the staff they need to keep the hospital running at full capacity. Keeping all the hospital’s units open has been critical: “Over the past three months, we have been busting at the seams…more patients, and they’re sicker. And we’re not even really into flu season yet.” We asked what had changed, given that summer usually is lighter than other seasons for hospital admissions. 

His diagnosis: local community hospitals, also strapped for staff, had begun to regularly shut down units to keep premium labor spend in check. “If they’re not running at full capacity, the patients still have to go somewhere. Given that we’re both the quaternary care provider and the community’s safety net, they’re coming downtown to us. We don’t have the luxury to shut down.” The system had to ramp up agency nursing to accommodate the demand, leading to a sharp rise in labor costs.

This CEO wasn’t backing away from the system’s mission, and vowed to expand capacity as much as they could, but felt that policymakers and payers needed to understand the dynamics in the market: “We’re getting criticized for not being able to control our costs, despite the fact that we’re absorbing what other hospitals can’t handle.” As we head into winter, flu will surely spike, and another COVID surge is possible—the hospitals at the top of the “care chain” will become even more strained in their mission to accommodate their communities’ needs.