America Needs a National Healthcare System

There’s only one person in this photograph/video of a recent G7 meeting who represents a country where an illness can destroy an entire family, leaving them bankrupt and homeless, with the repercussions of that sudden fall into poverty echoing down through generations.

Most Americans have no idea that the United States is quite literally the only country in the developed world that doesn’t define healthcare as an absolute right for all of its citizens. That’s it. We’re the only one left.

The United States spends more on “healthcare” than any other country in the world: about 17% of GDP. 

Switzerland, Germany, France, Sweden and Japan all average around 11%, and Canada, Denmark, Belgium, Austria, Norway, Netherlands, United Kingdom, New Zealand and Australia all come in between 9.3% and 10.5%.

Health insurance premiums right now make up about 22% of all taxable payroll, whereas Medicare For All would run an estimated 10%.

We are literally the only developed country in the world with an entire multi-billion-dollar for-profit industry devoted to parasitically extracting money from us to then turn over to healthcare providers on our behalf. The for-profit health insurance industry has attached itself to us like a giant, bloodsucking tick.

And it’s not like we haven’t tried.

Presidents Theodore Roosevelt, Franklin Roosevelt, Harry Truman, Jack Kennedy and Lyndon Johnson all proposed and made an effort to bring a national healthcare system to the United States. Here’s one example really worth watching where President Kennedy is pushing a single-payer system (as opposed to Britain’s “socialist” model):

They all failed, and when I did a deep dive into the topic two years ago for my book The Hidden History of American Healthcare I found two major barriers to our removing that tick from our backs.

The early opposition, more than 100 years ago, to a national healthcare system came from southern white congressmen (they were all men) and senators who didn’t want even the possibility that Black people could benefit, health-wise, from white people’s tax dollars. (This thinking apparently still motivates many white Southern politicians.)

The leader of that healthcare-opposition movement in the late 19th and early 20th centuries was a German immigrant named Frederick Hoffman, as I mentioned in a recent newsletter. Hoffman was a senior executive for the Prudential Insurance Company, and wrote several books about the racial inferiority of Black people, a topic he traveled the country lecturing about.

His most well-known book was titled Race Traits and Tendencies of the American Negro. It became a major best-seller across America when it was first published for the American Economic Association by the Macmillan Company in 1896, the same year the Supreme Court’s Plessy v. Ferguson decision legally turned the entire US into an apartheid state.

Hoffman taught that Black people, in the absence of slavery, were so physically and intellectually inferior to whites that if they were simply deprived of healthcare the entire race would die out in a few generations. Denying healthcare to Black people, he said, would solve the “race problem” in America.

Southern politicians quoted Hoffman at length, he was invited to speak before Congress, and was hailed as a pioneer in the field of “scientific racism.” Race Traits was one of the most influential books of its era.

By the 1920s, the insurance company he was a vice president of was moving from life insurance into the health insurance field, which brought an added incentive to lobby hard against any sort of a national healthcare plan.

Which brings us to the second reason America has no national healthcare system: profits.

“Dollar” Bill McGuire, a recent CEO of America’s largest health insurer, UnitedHealth, made about $1.5 billion dollars during his time with that company.  To avoid prosecution in 2007 he had to cough up $468 million, but still walked away a billionaire. Stephen J Hemsley, his successor, made off with around half a billion.

And that’s just one of multiple giant insurance companies feeding at the trough of your healthcare needs.

Much of that money, and the pay for the multiple senior executives at that and other insurance companies who make over $1 million a year, came from saying “No!” to people who file claims for payment of their healthcare costs.

This became so painful for Cigna Vice President Wendell Potter that he resigned in disgust after a teenager he knew was denied payment for a transplant and died. He then wrote a brilliant book about his experience in the industry: Deadly Spin: An Insurance Company Insider Speaks Out on How Corporate PR Is Killing Health Care and Deceiving Americans.

Companies offering such “primary” health insurance simply don’t exist (or are tiny) in almost every other developed country in the world. Mostly, where they do exist, they serve wealthier people looking for “extras” beyond the national system, like luxury hospital suites or air ambulances when overseas. (Switzerland is the outlier with exclusively private insurance, but it’s subsidized, mandatory, and non-profit.)

If Americans don’t know this, they intuit it.

In the 2020 election there were quite a few issues on statewide ballots around the country. Only three of them outpolled Joe Biden’s win, and expanding Medicaid to cover everybody was at the top of that list. (The other two were raising the minimum wage and legalizing pot.)

The last successful effort to provide government funded, single-payer healthcare insurance was when Lyndon Johnson passed Medicare and Medicaid (both single-payer systems) in the 1960s. It was a hell of an effort, but the health insurance industry was then a tiny fraction of its current size.

In 1978, when conservatives on the Supreme Court legalized corporations owning politicians with their Buckley v Belotti decision (written by Justice Louis Powell of “Powell Memo” fame), they made the entire process of replacing a profitable industry with government-funded programs like single-payer vastly more difficult, regardless of how much good they may do for the citizens of the nation.

The Court then doubled-down on that decision in 2010, when the all-conservative vote on Citizens United cemented the power of billionaires and giant corporations to own politicians and even write and influence legislation and the legislative process.

Medicare For All, like Canada has, would save American families thousands every year immediately and do away with the 500,000+ annual bankruptcies in this country that happen only because somebody in the family got sick. But it would kill the billions every week in profits of the half-dozen corporate giants that dominate the health insurance industry.

This won’t be happening with a billionaire in the White House, but if we want to bring America into the 21st century with the next administration, we need to begin working, planning, and waking up voters now.


The Two Events that Changed U.S. Healthcare for Everyone

In late 2025, two events reset the U.S. health system’s future at least through 2026 and possibly beyond:

  • November 5, 2024: The Election: Its post-mortem by pollsters and pundits reflects a country divided and unsettled: 22 Red States, 7 Swing States and 21 Blue States. But a solid majority who thought the country was heading in the wrong direction and their financial insecurity driving voters to return the 45th President to the White House. With slim majorities in the House and Senate, and a short-leash before mid-term elections November 3, 2026, the Trump team has thrown out ‘convention’ in their setting policies and priorities for their second term. That includes healthcare.
  • December 4, 2024: The Murder of a Health Executive : The murder of Brian Thompson, United Healthcare CEO, sparked hostility toward health insurers and a widespread backlash against the corporatization of the U.S. health system. While UHG took the most direct hit for its aggressiveness in managing access and coverage disputes, social media and mainstream journalists exposed what pollsters affirmed—the majority of American’s distrust the health system, believing it puts its profits above their needs. And their polls indicate animosity is highest among young adults, in lower income households and among members of its own workforce.

These events provide the backdrop for what to expect this year and next. Four directional shifts seem to underly actions to date and announced plans:

  • From elitism to populism: Key personnel and policy changes will draw less from Ivy League credentials, DC connections and recycled federal health agency notables and more from private sector experience, known disruptors and unconventional thought leaders. Notably, the new Chairs of the 7 Congressional Committees that control healthcare regulation, funding and policy changes in the 119th Congress represent LA, AL, WV, ID, VA, MO & KY constituents—hardly Ivy League territory.
  • From workforce disparities to workforce modernization: The Departments of Health & Human Services, Labor, Commerce and Treasury will attempt to suspend/modify regulatory mandates and entities they deem derived from woke ideology. The Trump team will replace them with policies that enable workforce de-regulation and modernization in the private sector. Hiring quotas, non-compete contracts, DEI et al will get a fresh look in the context of technology-enabled workplaces and supply-demand constraints. The HR function in every organization will become ground zero for Trump Healthcare 2.0 system transformation.
  • From western medicine to whole person wellbeing: HHS Secretary Nominee Robert F. Kennedy Jr. (RFK) Jr.’s “Make America Healthy Again” pledges war on ultra-processed foods. CMS’ designee Mehmet Oz advocates for vitamins, supplements and managed care. FDA nominee Marty Makary, a Hopkins surgeon, is a RFKJ ally in the “Health Freedom” movement promoting suspicion about ‘mainstream medicine’ and raising doubts about vaccination efficacy for children and low-risk adults. NIH nominee Jay Bhattacharya, director of Stanford’s Center for Demography and Economics of Health and Aging, opposed Covid-19 lockdowns and is critical of vaccine policies. Collectively, this four-some will challenge conventional western (allopathic) medicine and add wide-range of non-traditional interventions that are a safe and cost-effective to the treatment arsenal for providers and consumers. The food supply will be a major focus: HHS will work closely with the USDA (nominee Brooke Rollins, currently CEO of the America First Policy Institute, to reduce the food chain’s dependence on ultra-processed foods in public health.
  • From DC dominated health policies to states: The 2022 Supreme Court’ Dobbs decision opened the door for states to play the lead role in setting policies for access to abortion for their female citizens. It follows federalism’s Constitutional preference that Washington DC’s powers over states be enumerated and limited. Thus, state provisions about healthcare services for its citizens will expand beyond their already formidable scope. Likely actions in some states will include revised terms and conditions that facilitate consolidation, allowance for physician owned hospitals and site-neutral payments, approval of “skinny” individual insurance policies that do not conform to the Affordable Care Act’s qualified health plan spec’s, expanded scope of practice for nurse practitioners, drug price controls and many others. At least for the immediate future, state legislatures will be the epicenters for major policy changes impacting healthcare organizations; federal changes outside appropriations activity are unlikely.

Transforming the U.S. health system is a bodacious ambition for the incoming Trump team. Early wins will be key—like expanding price transparency in every healthcare sector, softening restrictions on private equity investments, targeted cuts in Medicaid and Medicare funding and annulment of the Inflation Reduction Act. In tandem, it has promised to cut Federal government spending by $2 trillion and lower prices on everything including housing and healthcare—the two spending categories of highest concern to the working class. Healthcare will figure prominently in Team Trump’s agenda for 2025 and posturing for its 2026 mid-term campaign. And equally important, healthcare costs also figure prominently in quarterly earnings reports for companies that provide employee health benefits forecast to be 8% higher this year following a 7% spike the year prior. Last year’s 23% S&P growth is not expected to repeat this year raising shareholder anxiety and the economy’s long-term resilience and the large roles housing and healthcare play in its performance.

My take:

The 2024 election has been called a change election. That’s unwelcome news to most organizations in healthcare, especially the hospitals, physicians, post-acute providers and others who provide care to patients and operate at the bottom of the healthcare pyramid.

Equipping a healthcare organization to thoughtfully prepare for changes amidst growing uncertainty requires extraordinary time and attention by management teams and their Boards. There are no shortcuts. Before handicapping future state scenario possibilities, contingencies and resource requirements, a helpful starting point is this: On the four most pressing issues facing every U.S. healthcare company/organization today, Boards and Management should discuss…

  • Trust: On what basis can statements about our performance be verified? Is the data upon which our trust is based readily accessible? Does the organization’s workforce have more or less trust than outside stakeholders? What actions are necessary to strengthen/restore trust?
  • Purpose: Which stakeholder group is our organization’s highest priority? What values & behaviors define exceptional leadership in our organization? How are they reflected in their compensation?
  • Affordability: How do we measure and monitor the affordability of our services to the consumers and households we ultimately depend? How directly is our organization’s alignment of reducing cost reduction and pass-through savings to consumers? Is affordability a serious concern in our organization (or just a slogan)?
  • Scale: How large must we be to operate at the highest efficiency? How big must we become to achieve our long-term business goals?

This week, thousands of healthcare’s operators will be in San Francisco (JPM Healthcare Conference), Naples (TGI Leadership Conference) and in Las Vegas (Consumer Electronics Show) as healthcare begins a new year. No one knows for sure what’s ahead or who the winners and losers will be.  What’s for sure is that healthcare will be in the spotlight and its future will not be a cut and paste of its past.

PS: The parallels between radical changes facing the health system and other industries is uncanny. College athletics is no exception. As you enjoy the College Football Final Four this weekend, consider its immediate past—since 2021, the impact of Name, Image and Likeness (NIL) monies on college athletics, and its immediate future–pending regulation that will codify permanent revenue sharing arrangements (to be implemented 2026-2030) between college athletes, their institutions and sponsors. What happened to the notion of student athlete and value of higher education? Has the notion of “not-for-profit” healthcare met a similar fate? Or is it all just business?

Vaccine Research vs Anti-Vax Research

BIG INSURANCE 2022: Revenues reached $1.25 trillion thanks to sucking billions out of the pharmacy supply chain – and taxpayers’ pockets

HIGHLIGHTS

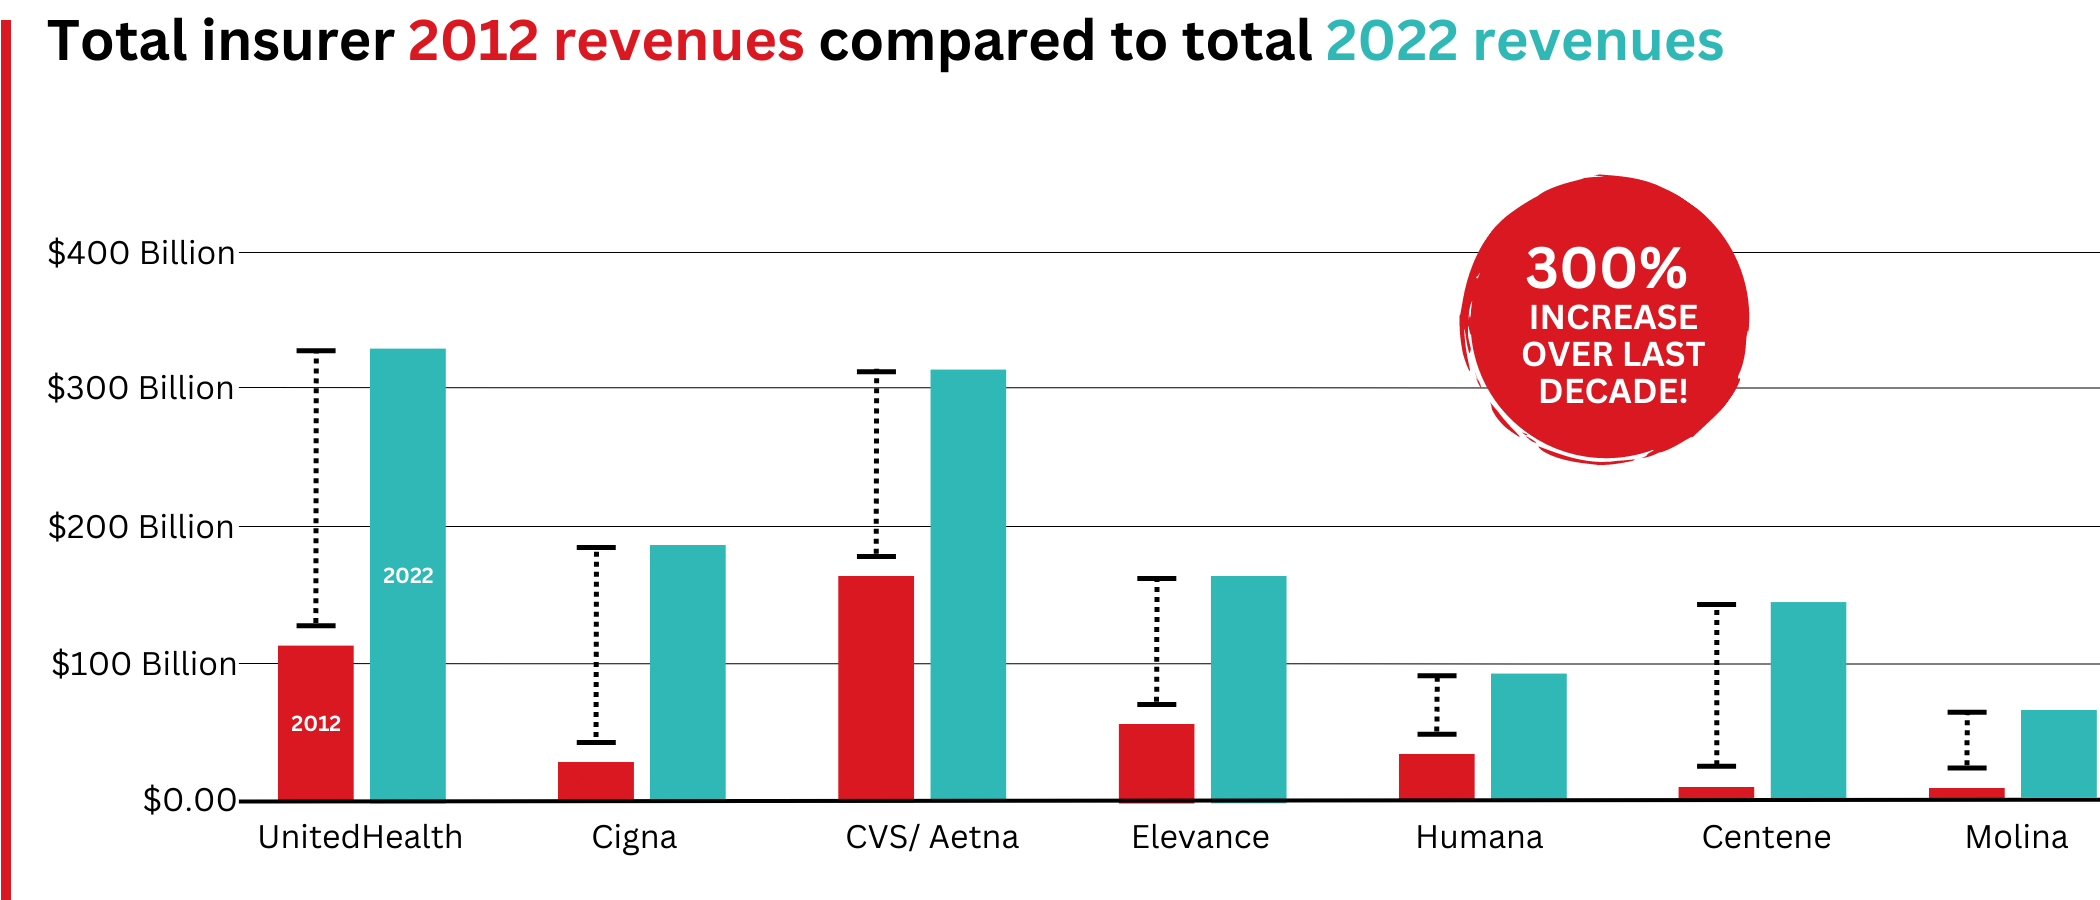
  • Big Insurance revenues and profits have increased by 300% and 287% respectively since 2012 due to explosive growth in the companies’ pharmacy benefit management (PBM) businesses and the Medicare replacement plans they call Medicare Advantage.
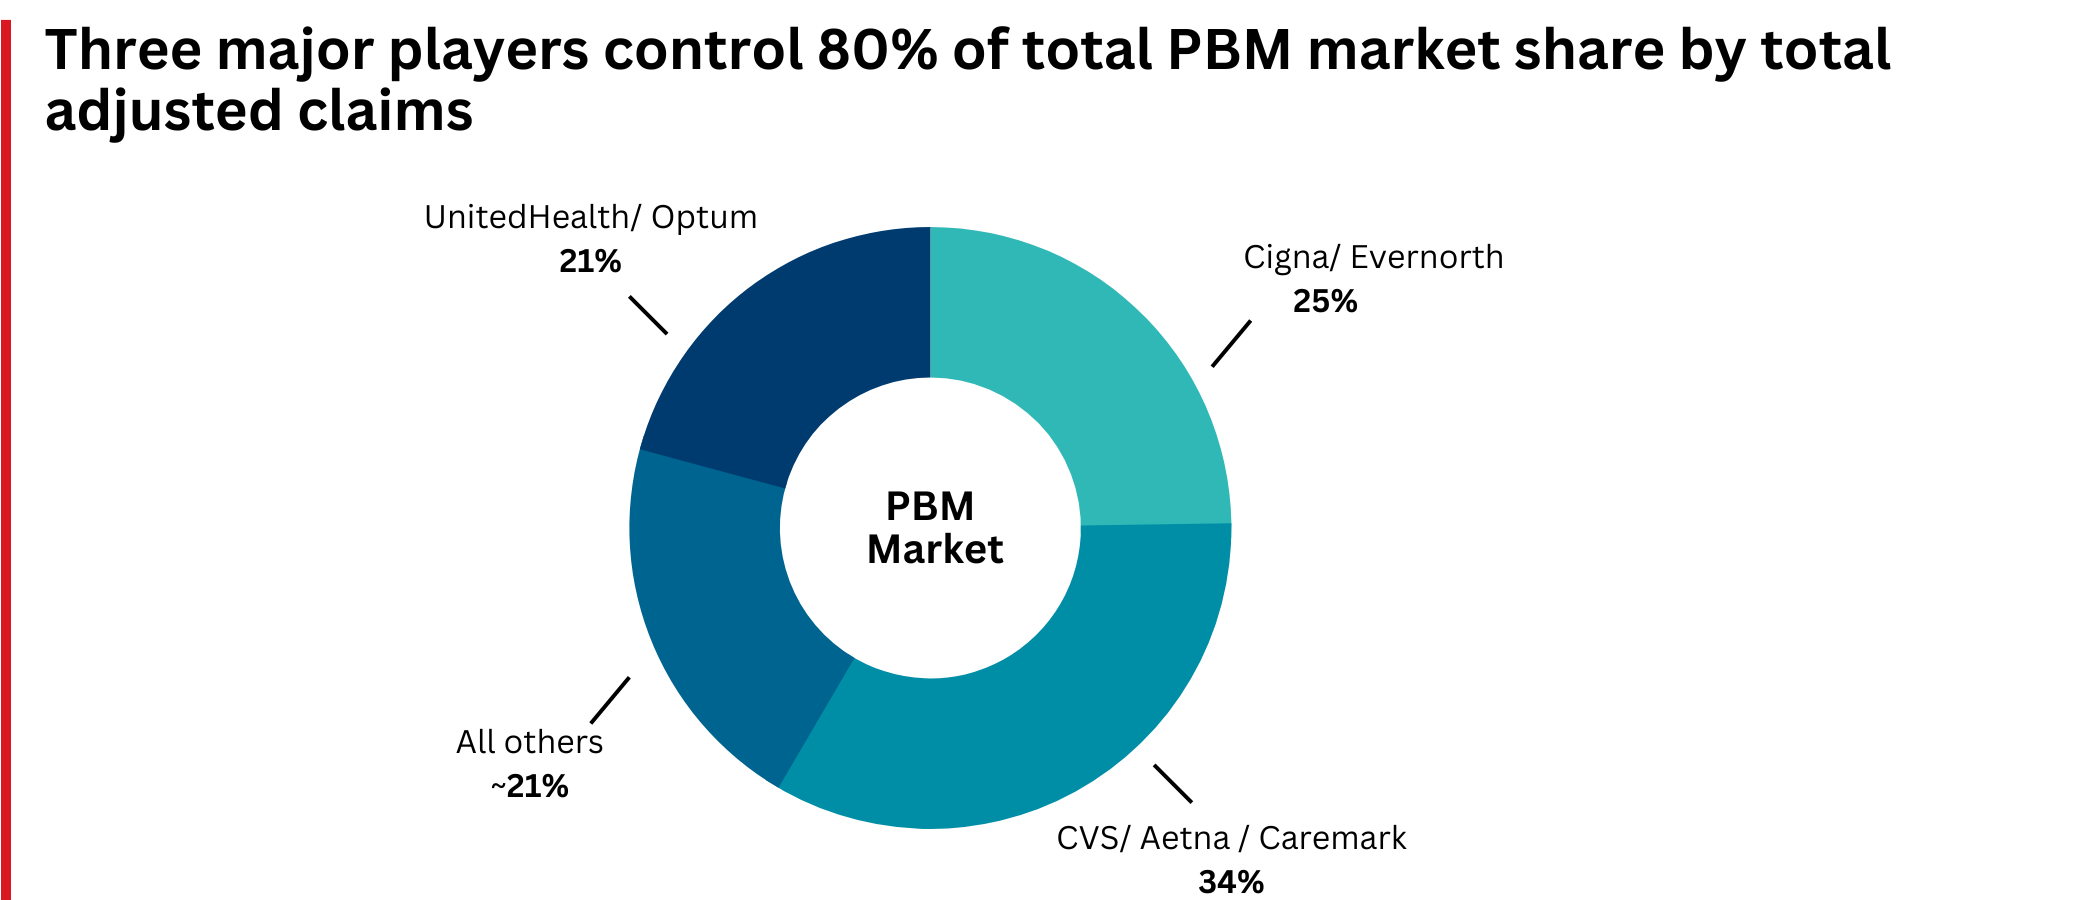
  • The for-profits now control more than 80% of the national PBM market and more than 70% of the Medicare Advantage market. 

In 2022, Big Insurance revenues reached $1.25 trillion and profits soared to $69.3 billion.

That’s a 300% increase in revenue and a 287% increase in profits from 2012, when revenue was $412.9 billion and profits were $24 billion.

Big insurers’ revenues have grown dramatically over the past decade, the result of consolidation in the PBM business and taxpayer-supported Medicare and Medicaid programs. 

Sucking billions out of the pharmacy supply chain – and taxpayers’ pockets

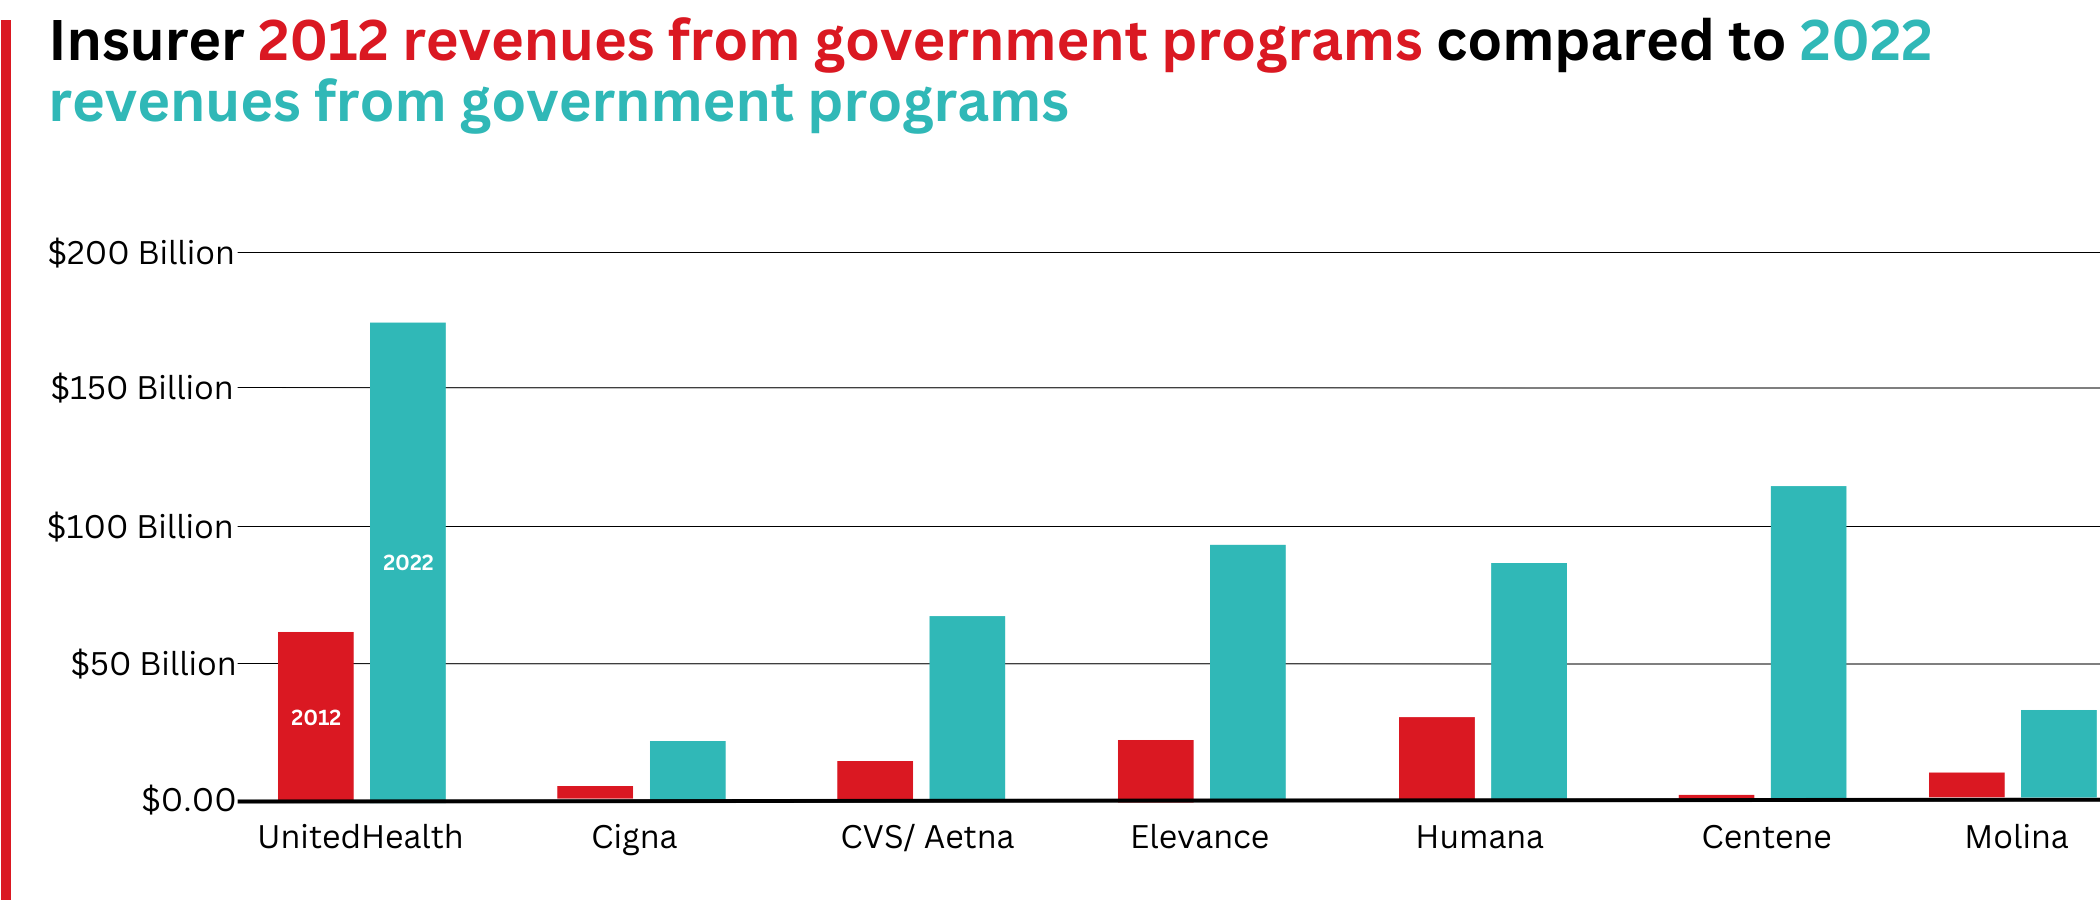
What has changed dramatically over the decade is that the big insurers are now getting far more of their revenues from the pharmaceutical supply chain and from taxpayers as they have moved aggressively into government programs. This is especially true of Humana, Centene, and Molina, which now get, respectively, 85%, 88%, and 94% of their health-plan revenues from government programs. 

The two biggest drivers are their fast-growing pharmacy benefit managers (PBMs), the relatively new and little-known middleman between patients and pharmaceutical drug manufacturers, and the privately owned and operated Medicare replacement plans they market as Medicare Advantage.

With the exception of Humana, Centene, and Molina, most of the companies that constitute Big Insurance continue to make substantial amounts of money selling policies and services in what they refer to as their commercial businesses – to individuals, families, and employers – but the seven companies’ commercial revenue grew just 260%, or $176 billion, over 10 years (from $110.4 billion to $287.1 billion). While that’s significant, profitable growth in the commercial sector has become a major challenge for big insurers – so much so that Humana just last week announced it is exiting the employer-sponsored health-insurance marketplace entirely. 

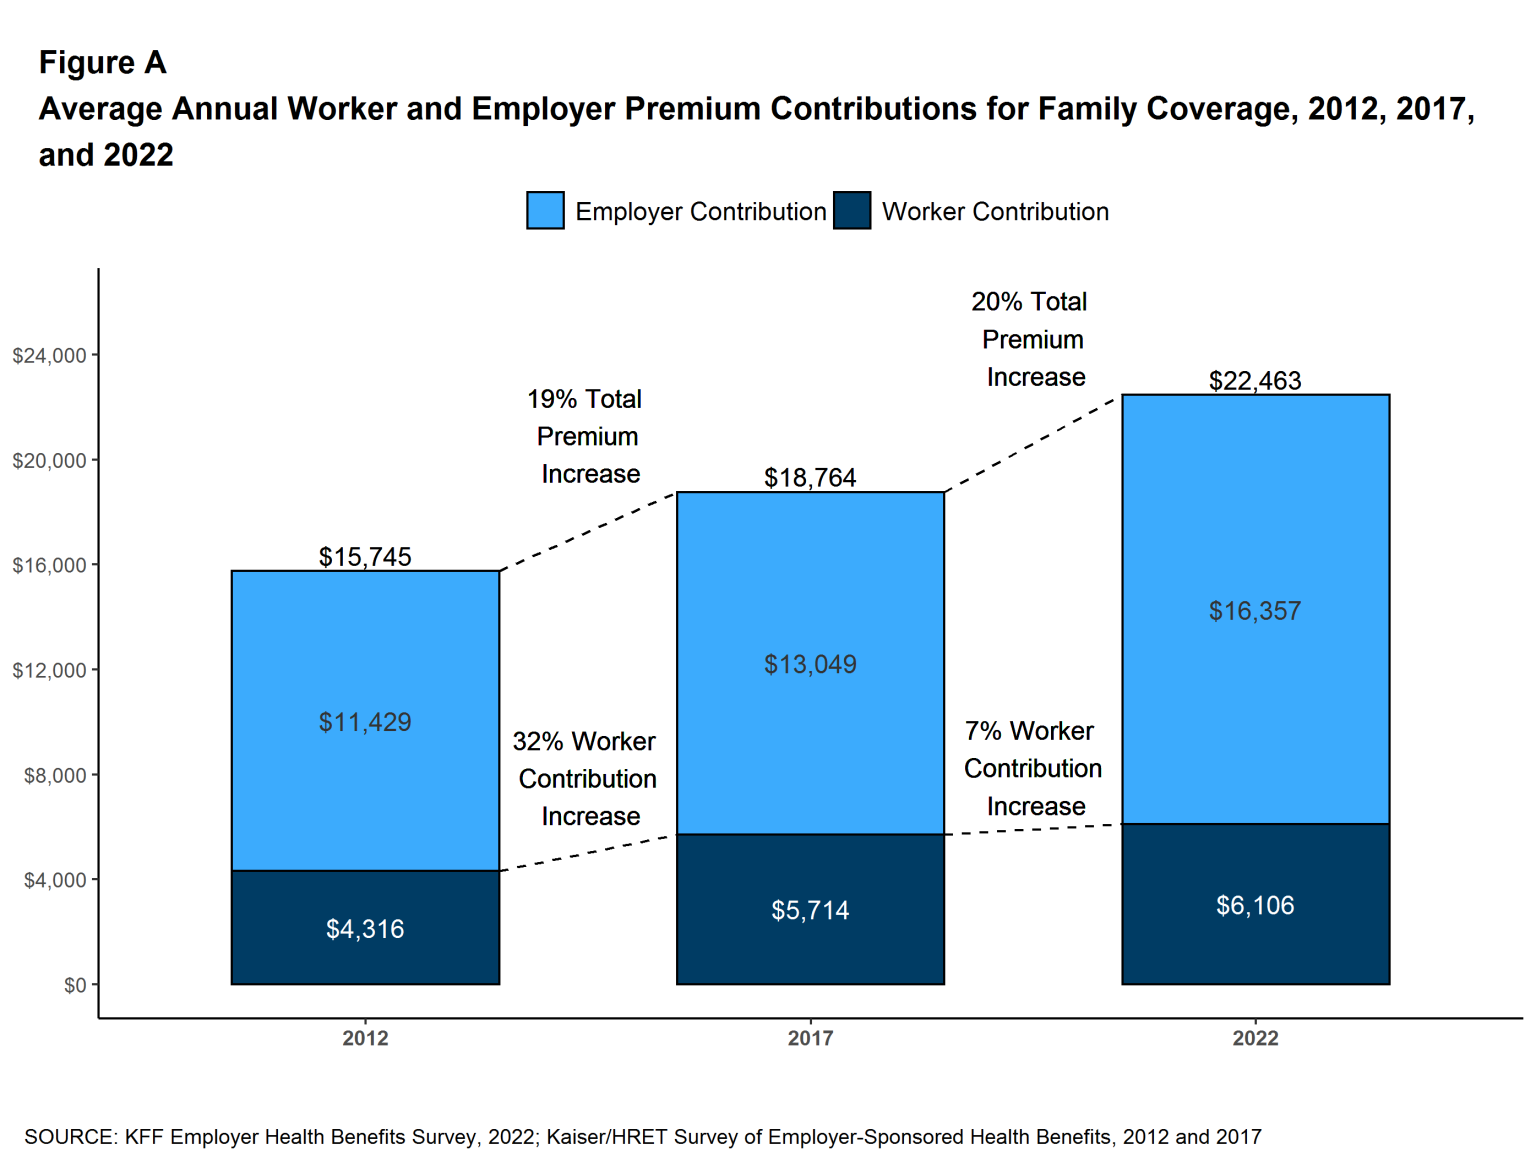
The insurers’ commercial businesses have stagnated because small businesses – which employ nearly half of the nation’s workers – are increasingly being priced out of the health insurance market. Most small businesses can no longer afford the premiums. The average premium for an employer-sponsored family plan – not including out-of-pocket requirements – was $22,463 in 2022, up 43% since 2012, which has contributed to the decades-long decline in the percentage of U.S. employers offering coverage to their workers.

The percentage of U.S. employers providing some level of health benefits to their workers dropped from 69% to 51% between 1999 and 2022 – including a dramatic 8% decrease last year alone. Growth in this category is largely the result of insurers “stealing market share” from each other or from smaller competitors.

As a consequence of this segment’s relative stagnation, PBMs and government programs have become the new cash cows for Big Insurance.

Spectacular PBM Growth

PBM HIGHLIGHTS

  • Cigna now gets far more revenue from its PBM than from its health plans. CVS gets more revenue from its PBM than from either Aetna’s health plans or its nearly 10,000 retail stores. 
  • UnitedHealth has the biggest share of both the PBM and Medicare markets and, through numerous acquisitions of physician practices, is now the largest U.S. employer of doctors.

PBMs are middlemen companies that manage prescription drug benefits for health insurers, Medicare Part D drug plans, employers, and, in some cases, unions. As the Commonwealth Fund has noted: 

PBMs have a significant behind-the-scenes impact in determining total drug costs for insurers, shaping patients’ access to medications, and determining how much pharmacies are paid. 

The Commonwealth Fund went on to say that PBMs have faced growing scrutiny about their role in rising prescription drug costs and spending. A big reason for the scrutiny – by Congress, state lawmakers and now also by the FTC – is that the biggest PBMs are now owned by Big Insurance.

Through mergers and acquisitions in recent years, three of the seven for-profit insurers – Cigna, CVS/Aetna, and UnitedHealth – now control 80% of the U.S. pharmacy benefits market.

They determine which drugs will be listed in each of their formularies (lists of drugs they will “cover” based on secret deals they negotiate with pharmaceutical companies) and how much patients will have to pay out of their own pockets at the pharmacy counter – in many cases hundreds or thousands of dollars – before their coverage kicks in. The PBMs also “steer” health-plan enrollees to their preferred or owned pharmacies (and, increasingly, away from independent pharmacists), thereby capturing even more of what we spend on our prescription medications.

Cigna, CVS/Aetna, and UnitedHealth now control 80% of the U.S. PBM market. Correction: this graph was initially published with inaccurate numbers. The source for this information can be found here.

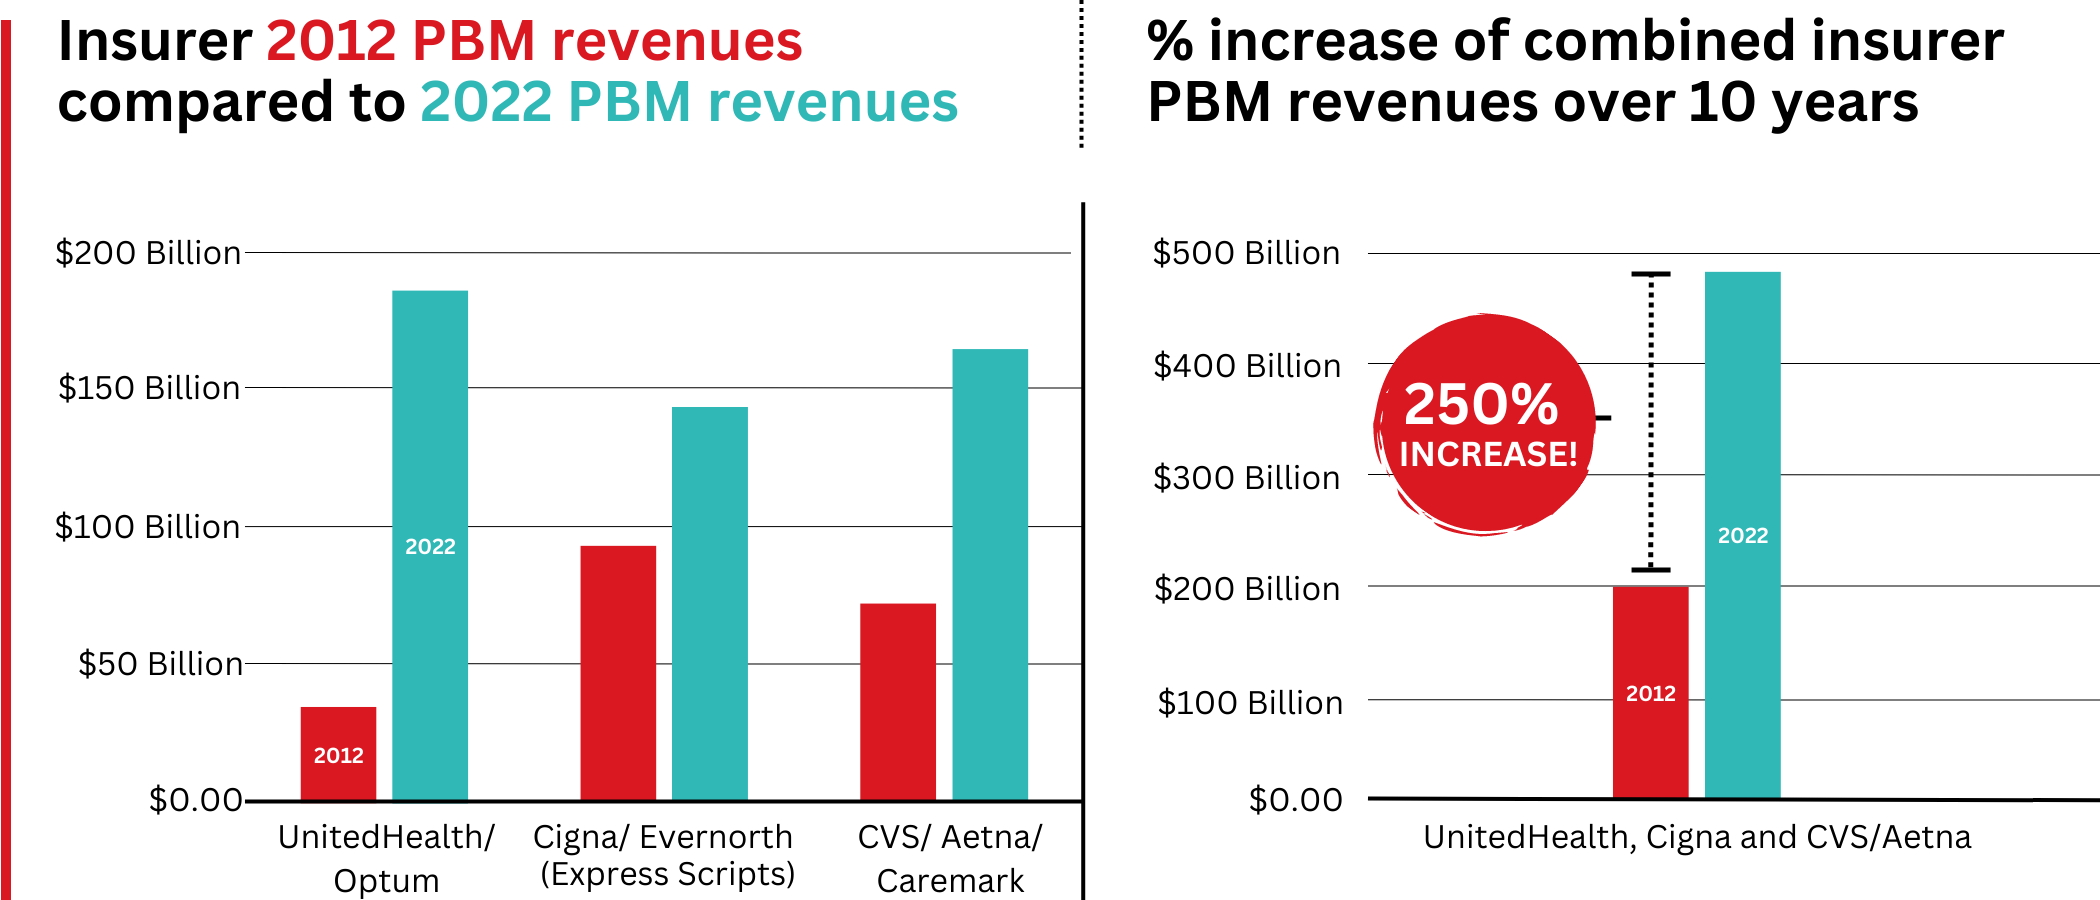
Ten years ago, PBMs contributed relatively little to the three companies’ revenues and profits. But since then, the rapid growth of PBMs has transformed all of the companies. The combined revenues from their PBM business units increased 250% between 2012 and 2022, from $196.7 billion to $492.4 billion.

Changes in PBM revenues between 2012 and 2022 for UnitedHealth Group, Cigna, and CVS/Aetna (Editor’s note: Cigna acquired PBM Express Scripts in 2018. To reflect revenue growth, Express Scripts’ pre-acquisition 2012 revenues are included in the Cigna total for that year.)

PBM Profit Generation

The PBM profit growth at the three companies over the past decade was even more dramatic than revenue growth. Collectively, their PBM profits increased 438%, from $6.3 billion in 2012 to $27.6 billion in 2022.

As a result of this fast growth, more than half (52%) of three companies’ profits in 2022 came from their PBM business units: Cigna’s Evernorth, CVS/Aetna’s Caremark, and UnitedHealth’s Optum. Cigna now gets far more revenue and profits from its PBM than from its health plans. And CVS gets more revenue from its PBM than from either Aetna’s health plans or its nearly 10,000 retail stores. (The companies’ business units that include their PBMs have also moved aggressively in recent years into health-care delivery through acquisitions of physician practices, clinics, dialysis centers, and other facilities. Notably, UnitedHealth Group is now the largest U.S. employer of physicians.)

Huge strides in privatizing both Medicare and Medicaid

GOVERNMENT PROGRAMS HIGHLIGHTS

  • More than 90% of health-plan revenues at three of the companies come from government programs as they continue to privatize both Medicare and Medicaid, through Medicare Advantage in particular.
  • Enrollment in government-funded programs increased by 261% in 10 years; by contrast commercial enrollment increased by just 10% over the past decade.
  • Commercial enrollment actually declined at both UnitedHealth and Humana.
  • 85% of Humana’s health-plan members are in government-funded programs; at Centene, it is 88%, and at Molina, it is 94%. 

The big insurers now manage most states’ Medicaid programs – and make billions of dollars for shareholders doing so – but most of the insurers have found that selling their privately operated Medicare replacement plans is even more financially rewarding for their shareholders.

Revenue growth from government programs has been dramatic over the past 10 years. (Note the numbers do not include revenue from the Medicare Part D program, federal subsidy payments for many ACA marketplace plan enrollees, or Medicare supplement policies.)

This is especially apparent when you see that the Big Seven’s combined revenues from taxpayer-supported programs grew 500%, from $116.3 billion in 2012 to $577 billion in 2022.

These numbers should be of interest to the Biden administration and members of Congress, many of whom are calling for much greater scrutiny of the Medicare Advantage program. Numerous media and government reports have shown that the federal government is overpaying private insurers billions of dollars a year, largely because of loopholes in laws and regulations that enable them to get more taxpayer dollars by claiming their enrollees are sicker than they really are. The companies also make aggressive use of prior authorization, largely unknown in traditional Medicare, to avoid paying for doctor-ordered care and medications.

In addition to their focus on Medicare and Medicaid, the companies also profit from the generous subsidies the government pays insurers to reduce the premiums they charge individuals and families who do not qualify for either Medicare or Medicaid or who work for an employer that does not offer subsidized coverage. But many people enrolled in those types of plans – primarily through the health insurance “marketplaces” established by the Affordable Care Act – cannot afford the deductibles and other out-of-pocket requirements they must pay before their insurers will begin paying their medical claims. 

Dramatic Enrollment Shifts

Changes in health-plan enrollment over the past decade show how dramatic this shift has been. Between 2012 and 2022, enrollment in the companies’ private commercial plans increased by 10%, from 85.1 million in 2012 to 93.8 million in 2022. 

By comparison, growth in enrollment in taxpayer-supported government programs increased 261%, from 27 million in 2012 to 70.4 million in 2022. 

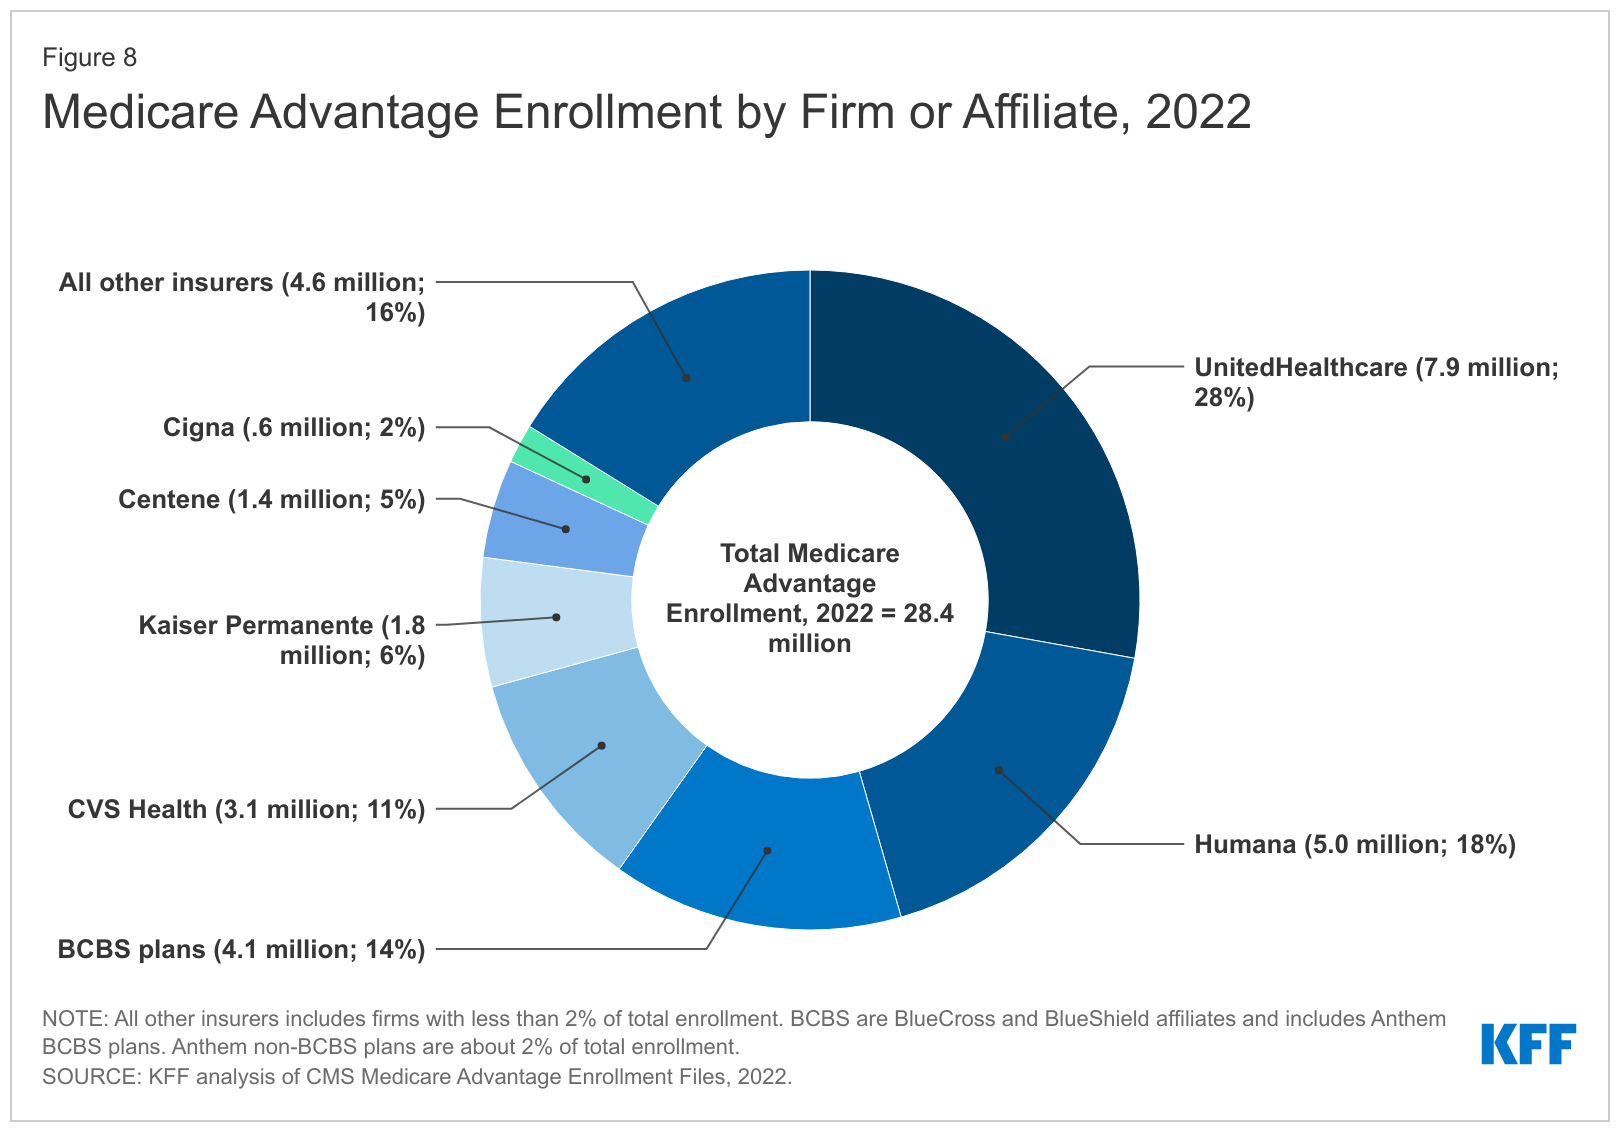
For-profit insurers dominate the Medicare Advantage market. Note that Anthem mentioned above is now known as Elevance. It owns 14 of the country’s Blue Cross Blue Shield plans. 

Within that category, Medicare Advantage enrollment among the Big Seven increased 252%, from 7.8 million in 2012 to 19.7 million in 2022. 

Nationwide, enrollment in Medicare Advantage plans increased to 28.4 million in 2022 (and to 30 million this year). That means that the Big Seven for-profit companies control more than 70% of the Medicare Advantage market. 

UnitedHealth, Humana, Elevance, and CVS/Aetna have captured most of the Medicare Advantage market since the Affordable Care Act was passed in 2010. 

The remaining growth in the government segment occurred in the Medicaid programs that a subset of the Big Seven (UnitedHealth, Elevance, Centene, and Molina in particular) manages for several states.

A few other facts and figures to keep in mind as Big Insurance thrives:

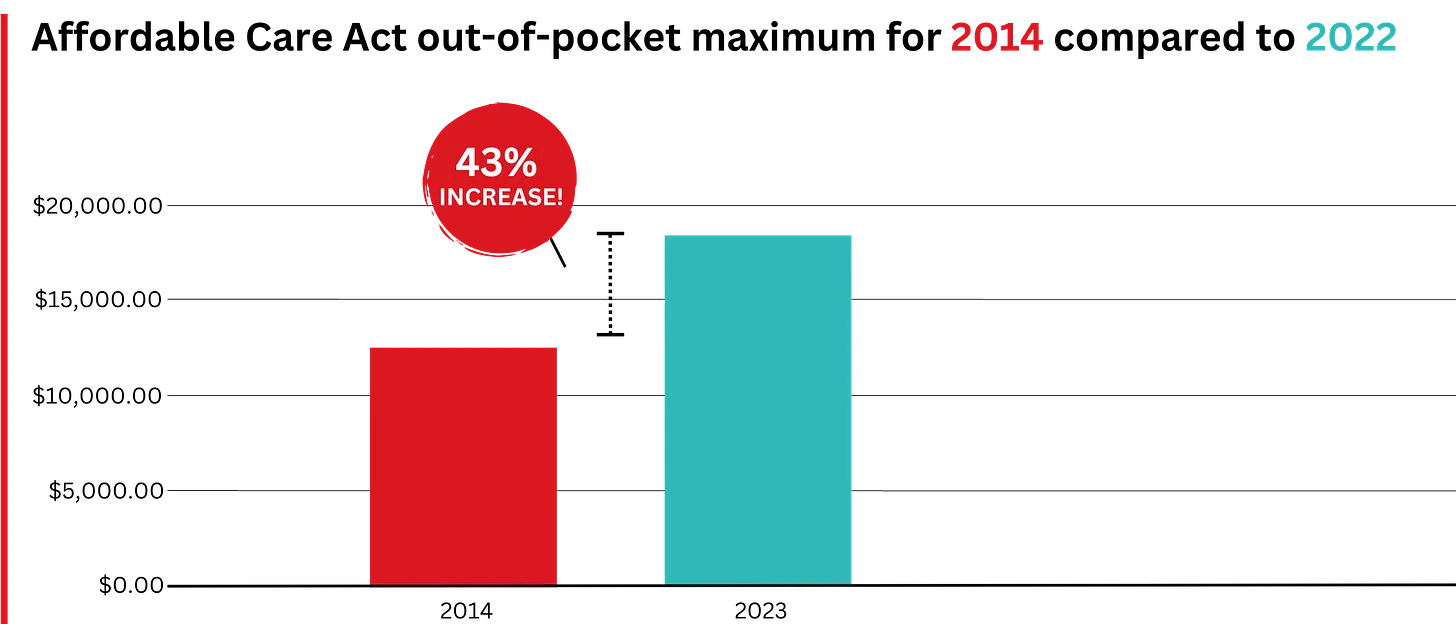
  • In 2023, U.S. families can be on the hook for up to $18,200 in out-of-pocket requirements before their coverage kicks in, up 43% since 2014 when it was $12,700.The Affordable Care Act allows the out-of-pocket maximum to increase annually – 43% since the maximum limit went into effect in 2014.
  • 44% of people in the United States who purchased coverage through the individual market and (ACA) marketplaces were underinsured or functionally uninsured.
  • 46% of those surveyed said they had skipped or delayed care because of the cost.
  • 42% said they had problems paying medical bills or were paying off medical debt.
  • Half (49%) said they would be unable to pay an unexpected medical bill within 30 days, including 68% of adults with low income, 69% of Black adults, and 63% of Latino/Hispanic adults. 
  • In 2021, about $650 million, or about one-third of all funds raised by GoFundMe, went to medical campaigns. That’s not surprising when you realize that in the United States, even people with insurance all too often feel they have no choice but to beg for money from strangers to get the care they or a loved one needs. 
  • 62% of bankruptcies are related to medical costs. 
  • Even as we spend about $4.5 trillion on health care a year, Americans are now dying younger than people in other wealthy countries. Life expectancy in the United States actually decreased by 2.8 years between 2014 and 2021, erasing all gains since 1996, according to the Centers for Disease Control and Prevention. 

BOTTOM LINE: 

The companies that comprise Big Insurance are vastly different from what they were just 10 years ago, but policymakers, regulators, employers, and the media have so far shown scant interest in putting their business practices under the microscope.

Changes in federal law, including the Medicare Modernization Act of 2003, which created the lucrative Medicare Advantage market, and the Affordable Care Act of 2010, which gave insurers the green light to increase out-of-pocket requirements annually and restrict access to care in other ways, opened the Treasury and Medicare Trust Fund to Big Insurance. In addition, regulators have allowed almost all of their proposed acquisitions to go forward, which has created the behemoths they are today.

CVS/Health is now the 4th largest company on the Fortune 500 list of American companies. UnitedHealth Group is now No. 5 – and all the others are climbing toward the top 10. 

When Profits Kill: The Deadly Costs of Treating Healthcare as a Business

The recent assassination of the CEO of UnitedHealthcare — the health insurance company with, reportedly, the highest rate of claims rejections (and thus dead, wounded, and furious customers and their relations) — gives us a perfect window to understand the stupidity and danger of the Musk/Trump/Ramaswamy strategy of “cutting government” to “make it more efficient, run it like a corporation.”

Consider health care, which in almost every other developed country in the world is legally part of the commons — the infrastructure of the nation, like our roads, public schools, parks, police, military, libraries, and fire departments — owned by the people collectively and run for the sole purpose of meeting a basic human need.

The entire idea of government — dating all the way back to Gilgamesh and before — is to fulfill that singular purpose of meeting citizens’ needs and keeping the nation strong and healthy. That’s a very different mandate from that of a corporation, which is solely directed (some argue by law) to generate profits.

The Veterans’ Administration healthcare system, for example, is essentially socialist rather than capitalist. The VA owns the land and buildings, pays the salaries of everybody from the surgeons to the janitors, and makes most all decisions about care. Its primary purpose — just like that of the healthcare systems of every other democracy in the world — is to keep and make veterans healthy. Its operation is nearly identical to that of Britain’s beloved socialist National Health Service.

UnitedHealthcare similarly owns its own land and buildings, and its officers and employees behave in a way that’s aligned with the company’s primary purpose, but that purpose is to make a profit. Sure, it writes checks for healthcare that’s then delivered to people, but that’s just the way UnitedHealthcare makes money; writing checks and, most importantly, refusing to write checks.

Think about it. If UnitedHealthcare’s main goal was to keep people healthy, they wouldn’t be rejecting 32 percent of claims presented to them. Like the VA, when people needed help they’d make sure they got it.

Instead, they make damn sure their executives get millions of dollars every year (and investors get billions) because making a massive profit ($23 billion last year, and nearly every penny arguably came from saying “no” to somebody’s healthcare needs) is their real business.

On the other hand, if the VA’s goal was to make or save money by “being run efficiently like a company,” they’d be refusing service to a lot more veterans (which it appears is on the horizon).

This is the essential difference between government and business, between meeting human needs (social) and reaching capitalism’s goal (profit).

It’s why its deeply idiotic to say, as Republicans have been doing since the Reagan Revolution, that “government should be run like a business.” That’s nearly as crackbrained a suggestion as saying that fire departments should make a profit (a doltish notion promoted by some Libertarians). Government should be run like a government, and companies should be run like companies.

Given how obvious this is with even a little bit of thought, where did this imbecilic idea that government should run like a business come from?

Turns out, it’s been driven for most of the past century by morbidly rich businessmen (almost entirely men) who don’t want to pay their taxes. As Jeff Tiedrich notes:

“The scariest sentence in the English language is: ‘I’m a billionaire, and I’m here to help.’”

Rightwing billionaires who don’t want to pay their fair share of the costs of society set up think tanks, policy centers, and built media operations to promote their idea that the commons are really there for them to plunder under the rubric of privatization and efficiency.

They’ve had considerable success. Slightly more than half of Medicare is now privatized, multiple Republican-controlled states are in the process of privatizing their public school systems, and the billionaire-funded Project 2025 and the incoming Trump administration have big plans for privatizing other essential government services.

The area where their success is most visible, though, is the American healthcare system. Because the desire of rightwing billionaires not to pay taxes have prevailed ever since Harry Truman first proposed single-payer healthcare like most of the rest of the world has, Americans spend significantly more on healthcare than other developed countries.

In 2022, citizens of the United States spent an estimated $12,742 per person on healthcare, the highest among wealthy nations. This is nearly twice the average of $6,850 per person for other wealthy OECD countries.

Over the next decade, it is estimated that America will spend between $55 and $60 trillion on healthcare if nothing changes and we continue to cut giant corporations in for a large slice of our healthcare money.

On the other hand, Senator Bernie Sanders’ single-payer Medicare For All plan would only cost $32 trillion over the next 10 years. And it would cover everybody in America, every man woman and child, in every medical aspect including vision, dental, psychological, and hearing.

Currently 25 million Americans have no health insurance whatsoever.

If we keep our current system, the difference between it and the savings from a single-payer system will end up in the pockets, in large part, of massive insurance giants and their executives and investors. And as campaign contributions for bought off Republicans. This isn’t rocket science.

And you’d think that giving all those extra billions to companies like UnitedHealthcare would result in America having great health outcomes. But, no.

Despite insanely higher spending, the U.S. has a lower life expectancy at birth, higher rates of chronic diseases, higher rates of avoidable or treatable deaths, and higher maternal and infant mortality rates than any of our peer nations.

Compared to single-payer nations like Canada, the U.S. also has a higher incidence of chronic health conditions, Americans see doctors less often and have fewer hospital stays, and the U.S. has fewer hospital beds and physicians per person.

No other country in the world allows a predatory for-profit industry like this to exist as a primary way of providing healthcare. Every other advanced democracy considers healthcare a right of citizenship, rather than an opportunity for a handful of industry executives to hoard a fortune, buy Swiss chalets, and fly around on private jets.

This is one of the most widely shared graphics on social media over the past few days in posts having to do with Thompson’s murder…

Sure, there are lots of health insurance companies in other developed countries, but instead of offering basic healthcare (which is provided by the government) mostly wealthy people subscribe to them to pay for premium services like private hospital rooms, international air ambulance services, and cosmetic surgery.

Essentially, UnitedHealthcare’s CEO Brian Thompson made decisions that killed Americans for a living, in exchange for $10 million a year. He and his peers in the industry are probably paid as much as they are because there is an actual shortage of people with business training who are willing to oversee decisions that cause or allow others to die in exchange for millions in annual compensation.

That Americans are well aware of this obscenity explains the gleeful response to his murder that’s spread across social media, including the refusal of online sleuths to participate in finding his killer.

It shouldn’t need be said that vigilantism is no way to respond to toxic individuals and companies that cause Americans to die unnecessarily. Hopefully, Thompson’s murder will spark a conversation about the role of government and the commons — and the very real need to end the corrupt privatization of our healthcare system (including the Medicare Advantage scam) that has harmed so many of us and killed or injured so many of the people we love.

In Healthcare, Most think We’re Shrewd and They’re Screwed

I never met Brian Thompson. His senseless death is first and foremost a human tragedy.

Second, it’s a business story that continues to unfold. Speculation about the shooter’s motive and whereabouts runs rampant.

But media attention has seized on a larger theme: the business of health insurance and its role in U.S. healthcare. 

Headlines like these illustrate the storyline that has evolved in response to the killing: health insurance is part of a complicated industry where business practices are often geared to corporate profit.

In this coverage and social media postings, health insurer denials are the focal point: journalists and commentators have seized on the use of Artificial intelligence-based tools used by plans like United, Cigna, Aetna and most others to approve/deny claims and Thompson’s role as CEO of UHG’s profitable insurance division.

The bullet-casing etchings “Deny. Defend. Depose” is now a T-shirt whistle to convey a wearer’s contempt for corporate insurers and the profit-seeking apparatus in U.S. healthcare. 

Laid bare in the coverage of Brian’s death is this core belief: the majority of Americans think the U.S. health system is big business and fundamentally flawed.

As noted in last week’s Gallup Poll, and in previous polling by Pew, Harris, Kaiser Family Foundation and Keckley, only one in three Americans believe the health system performs well. Accessibility, costs, price transparency and affordability are dominant complaints. They believe the majority of health insurers, hospitals and prescription drug companies put their financial interests above the public’s health and wellbeing. They accept that the health system is complex and expensive but feel helpless to fix it.

This belief is widely held: its pervasiveness and intensity lend to misinformation and disinformation about the system and its business practices. 

Data about underlying costs and their relationship to prices are opaque and hard to get. Clinical innovation and quality of care are understood in the abstract: self-funded campaigns touting Top 100 recognition, Net Promoter Scores are easier. The business of healthcare financing and delivery is not taught: personal experiences with insurers, hospitals, physicians and drugs are the basis for assessing the system’s effectiveness…and those experiences vary widely based on individual/household income, education, ethnicity and health status.  

The majority accept that operators in every sector of healthcare apply business practices intended to optimize their organization’s finances. Best practices for every insurer, hospital, drug/device manufacturer and medical practice include processes and procedures to maximize revenues, minimize costs and secure capital for growth/innovation. 

But in healthcare, the notion of profit remains problematic: how much is too much? and how an organization compensates its leaders for results beyond short-term revenue/margin improvement are questions of growing concern to a large and growing majority of consumers.

In every sector, key functions like these are especially prone to misinformation, disinformation and public criticism:

  • Among insurers, provider credentialing, coverage allowance and denial management, complaint management and member services, premium pricing and out-of-pocket risks for enrollees, provider reimbursement, prior authorization, provider directory accuracy, the use of AI in plan administration and others.
  • Among hospitals, price setting, employed physician compensation, 340B compliance, price and cost transparency, revenue-cycle management and patient debt collection, workforce performance composition, evaluation and compensation, integration of AI in clinical and administrative decision-making, participation in gainsharing/alternative payment programs, clinical portfolio and others.
  • And across every sector, executive compensation and CEO pay, Board effectiveness, and long-term strategies that balance shareholder interests with broader concern for the greater good.

The bottom line:

The public is paying attention to business practices in healthcare. The death of Brian Thompson opened the floodgate for criticism of health insurers and the U.S. healthcare industry overall. It cannot be ignored. The public thinks industry folks are shrewd operators and they’re inclined to conclude they’re screwed as a result.

Anthem’s reversal

A major health insurance company is backing off of a controversial plan to limit coverage of anesthesia, according to public officials.

Why it matters: 

Anthem Blue Cross Blue Shield recently decided to “no longer pay for anesthesia care if the surgery or procedure goes beyond an arbitrary time limit, regardless of how long the surgical procedure takes,” according to the American Society of Anesthesiologists, which opposed the decision.

  • The decision was based on surgery time metrics from federal health data, NPR reported.
  • The policy applied to plans in Connecticut, New York and Missouri.

The latest: 

“After hearing from people across the state about this concerning policy, my office reached out to Anthem, and I’m pleased to share this policy will no longer be going into effect here in Connecticut,” Connecticut Comptroller Sean Scanlon said Thursday on X.

  • Shortly afterward, New York Gov. Kathy Hochul issued a statement saying, “We pushed Anthem to reverse course and today they will be announcing a full reversal of this misguided policy.”

What they’re saying: 

The initial coverage decision was very unusual for a major health insurer, said Marianne Udow-Phillips, who teaches insurance classes at the University of Michigan School of Public Health and formerly made coverage decisions at Blue Cross Blue Shield of Michigan.

The big picture: 

Anthem’s initial decision was controversial at the time — but outrage erupted this week after the murder of UnitedHealthcare CEO Brian Thompson in New York City cast a spotlight on divisive insurance decisions.

  • On social media, critics of health insurers drew a direct line from controversial coverage decisions to the death of Thompson.

The spotlight is on health insurance companies. Patients are telling their stories of denied claims, bankruptcy and delayed care.

https://www.yahoo.com/lifestyle/spotlight-health-insurance-companies-patients-014648180.html

After UnitedHealthcare CEO Brian Thompson, left, was killed and Anthem released a controversial anesthesia policy, people shared their stories of insurance woes. (UnitedHealth Group via AP, Getty)

After UnitedHealthcare CEO Brian Thompson, left, was killed and Anthem released a controversial anesthesia policy, people shared their stories of insurance woes. (UnitedHealth Group via AP, Getty)

On Wednesday, Brian Thompson, the chief executive of UnitedHealthcare, was fatally shot in midtown Manhattan in what police are calling a “pre-meditated, preplanned, targeted attack.” Days before, Anthem Blue Cross Blue Shield said in a note to providers that it would limit anesthesia coverage in some states if a surgery or procedure exceeded a set time limit (the policy, set to go into effect in February, was swiftly reversed following an uproar).

The U.S. health care insurance system relies on private insurance, which covers 200 million Americans, and government-run programs.

Americans receive coverage through their employers, government programs like Medicaid or Medicare or by purchasing it themselves — often at a high cost. Even when an individual is covered by insurance, medical coverage can be expensive, with co-pays, deductibles and premiums adding up. Going to an out-of-network provider for care (which can be done unintentionally, for example if you are taken by ambulance to a hospital) can lead to exorbitant bills.

And then there’s the fact that, according to data from state and federal regulators, insurers reject about one in seven claims for treatment.

And most people don’t push back — a study found that only 0.1% of denied claims under the Affordable Care Act, a law designed to make health insurance more affordable and prevent coverage denials for pre-existing conditions, are formally appealed. This leaves many people paying out of pocket for care they thought was covered — or skipping treatment altogether.

For many, the cost of life-saving care is too high, and medical debt is the No. 1 cause of bankruptcy in America.

That is to say nothing of the emotional labor of navigating the complex system. With Thompson’s killing and the Anthem policy, there’s been widespread response with a similar through line: a pervasive contempt for the state of health insurance in the United States. The most illustrative reactions, though are the personal ones, the tales of denied claims, battles with insurance agents, delayed care, filing for bankruptcy and more.

‘We sat in the hospital for three days’

Jessica Alfano, a content creator who goes by @monetizationmom, shared her story on TikTok about battling an insurance company while her one-year-old child was in the hospital with a brain tumor. When her daughter needed to have emergency surgery at a different hospital was outside their home state, UnitedHealthcare allegedly refused to approve the transfer via ambulance to New York City. She also couldn’t drive her daughter to the hospital as the insurance company told them they would not cover her at the next hospital if they left the hospital by their own will and did not arrive by ambulance. “I vividly remember being on the phone with UnitedHealthcare for days and days — nine months pregnant about to give birth alone — while my other baby was sitting in a hospital room,” she said.

https://www.tiktok.com/embed/v2/7444723783765740830?lang=en-US&referrer=https%3A%2F%2Fwww.yahoo.com%2Flifestyle%2Fspotlight-health-insurance-companies-patients-014648180.html&embedFrom=oembed

‘Excruciating pain’

While pregnant, Allie, who posts on TikTok as @theseaowl44, went to the hospital in “excruciating pain,” she said in a video. After initially being sent home by a doctor who said she was having pain from a urinary tract infection and the baby sitting on her bladder, she returned to the hospital to learn she was suffering from appendicitis. She was sent to a bigger hospital in St. Louis, where she had emergency surgery. Her son survived the surgery but died the next day after she delivered him.

https://3489f1614246e47166ad8768064e31d6.safeframe.googlesyndication.com/safeframe/1-0-40/html/container.html

About 45 minutes later, Allie suffered a pulmonary embolism and had to have an emergency dilation and curettage (D&C) to remove the placenta, nearly dying in the process. It was after all of this that she learned she had been sent to a hospital that was out of network. “We ended up with a bill from the hospital that was more than what we paid for the home that we live in, and it was going to take probably, I don’t know, 20 to 30 years to pay off this hospital bill,” Allie said. “We opted to have to file bankruptcy, but not before I exhausted every appeal with [insurance company] Cigna — I wrote letters, I spilled my heart out, I talked on the phone, I explained our situation and our story, thinking surely someone would understand this was not my fault.

On the third and final appeal, because they only allow you three, Cigna’s appeal physician told me, point blank, it was my fault that when I was dying from a ruptured appendix in the ER, that I didn’t check and make sure that the hospital I was being sent to by ambulance was in my insurance network.”

https://www.tiktok.com/embed/v2/7445019152714173726?lang=en-US&referrer=https%3A%2F%2Fwww.yahoo.com%2Flifestyle%2Fspotlight-health-insurance-companies-patients-014648180.html&embedFrom=oembed

Hundreds of similar stories are being told, but the comments section on these videos paints a picture in itself. “I wear leg braces and walk with crutches as a paraplegic and they tried to deny my new leg braces and only approve me a wheelchair. They wanted to take my ability to WALK away,” commented TikToker @ChickWithSticks.

“Perfectly healthy pregnancy, until it wasn’t,” TikToker Meagan Pitts shared. “NICU stay was covered by my insurance, the neonatologist group contracted by the NICU: Denied. I’m sorry, what?”

Another wrote that her son was born with a congenital heart defect and needed open heart surgery. “My husband changed jobs & we switched to UHC,” she wrote. “They DENIED my son’s cath lab intervention!”

‘The most stressful time of my life’

One Redditor, @Sweet_Nature_7015, wrote that they struggled with UnitedHealthcare when they and their husband were in a “terrible car accident” that was the other driver’s fault. Since United Healthcare only covered two days in the hospital, the Redditor wrote that the case manager tried to find a way to “kick him out of the hospital” — but since their husband was in a coma, he was unable to be discharged safely. “The stress of being told — your health insurance isn’t covering this anymore, we have to discharge your husband — while he’s in a freaking coma and on a ventilator, etc, rediculous [sic],” they wrote. “I have to sign some papers to give up all of my husband’s benefits via his job – which included his life insurance that he had paid into, so we lost that. This allowed him to be covered by Medicaid. I can’t even put into words how much stress UHC caused on top of my husband (and my) health issues in the most stressful time of my life.”

The kicker, they wrote, was that years later the couple was awarded a court settlement from the other driver in the accident — and “UHC rolled up to the court and took the entire settlement money as their payment for those two days in the hospital they had paid for.”

‘I’m one of the lucky ones’

On the same thread, Redditor @sebastorio wrote that they went to the emergency room for an eye injury, which their doctor said could have resulted in a loss of sight. “UHC denied my claim, and I paid $1,400 out of pocket,” they said. “I’m one of the lucky ones. Can’t imagine how people would feel if that happened for critical or life-saving care.”

‘Constant stream of hostile collection calls’

Redditor @colonelcatsup opened up about their experience with insurance while having a baby, writing that they went into premature labor while insured under one company but that at midnight, their insurance switched to United Healthcare. “I gave birth in the morning. My daughter was two months early and was in the NICU for weeks so the bill was over $80,000 and United refused to pay it, saying it wasn’t their responsibility,” they wrote. “In addition to dealing with a premature baby, I had a constant stream of hostile collection calls and mail from the hospital for 18 months. My credit took a hit.”

Eventually, their employer hired an attorney to fight UHC, and the insurance company eventually paid. “I will never forgive them for the added stress hanging over me for the first year and a half of my child’s life,” they wrote.

‘Debt or death’

On Substack, on which she posted an excerpt from her Instagram, author Bess Kalb also recounted her experience with health insurance coverage when she was bleeding during her pregnancy and was asked by an EMT what insurance she had before deciding whether they would go to the nearest hospital. When her husband said to take Kalb to the hospital, despite not knowing the insurance implications, their bill was more than $10,000.https://www.instagram.com/p/DDNphXCp3Qu/embed/captioned/?cr=1&v=12

“The private insurance industry forces millions of Americans to choose between debt or death,” Kalb wrote. “Often, ghoulishly, the outcome is both. If I were worried about an ambulance out of coverage, I would have waited at home or waited in traffic for an hour to cross Los Angeles to get to my doctor’s office and sat in the waiting room bleeding out and perhaps would not be here to write this, and neither would my son.”

Trump picks HHS and CMS nominees

https://www.kaufmanhall.com/insights/blog/gist-weekly-november-22-2024

Last week, President-elect Donald Trump announced that Robert F. Kennedy, Jr. would be his nominee for Secretary of Health and Human Services (HHS). He followed this up on Tuesday with his selection of Dr. Mehmet Oz as his nominee for the Centers for Medicare and Medicaid Services (CMS) Administrator. If confirmed, the two men would replace Xavier Becerra and Chiquita Brooks-LaSure, respectively.

Kennedy, who ended his independent presidential campaign and endorsed Trump in August, has become known for his heterodox views on public health, including vaccine skepticism and opposition to water fluoridization.

Dr. Oz, first famous as a TV personality and more recently a Republican candidate for Pennsylvania Senator, is a strong proponent of Medicare Advantage, having co-authored an op-ed advocating for “Medicare Advantage for All” in 2020.

The Gist: 

These nominees, especially Kennedy, hold a number of personal beliefs at odds with the public health consensus. 

They are both likely to be confirmed, however, as the last cabinet nominee to be rejected by the Senate was John Tower in 1989. (This does not include nominees who have chosen to withdraw themselves from consideration, as former Representative Matt Gaetz has just done.)

Should they be confirmed, they will be responsible for implementing not their own but President Trump’s agenda, the specific priorities of which also remain relatively undefined. 

However, possible consensus points between Trump and his nominees include public health cuts and deregulation, greater scrutiny of pharmaceutical companies, and a favoring of Medicare Advantage over traditional Medicare.