Former Fed Chairs Bernanke and Yellen testified on COVID-19 and response to economic crisis

https://www.brookings.edu/blog/up-front/2020/07/17/former-fed-chairs-bernanke-and-yellen-testified-on-covid-19-and-response-to-economic-crisis/?utm_campaign=Economic%20Studies&utm_source=hs_email&utm_medium=email

Former Fed Chairs Bernanke and Yellen testified on COVID-19 and ...

In many respects this recession is unique. Most recessions result from developments inside the economy, but an external shock—the public health crisis—caused this one. To avoid getting sick, people have curtailed working, shopping, and attending school. Whatever the cause, the coronavirus recession, like all recessions, is imposing heavy costs. Many workers have lost jobs and income, and many business owners’ financial survival is at risk. The economy’s extraordinarily rapid decline earlier this year—as well as the sharp but incomplete rebound following the first steps toward reopening—reflect this recession’s unusual source. In addition, the sectors suffering most differ from past recessions. The heaviest blows have fallen on service industries that involve close personal contact (including retail trade, leisure and hospitality, and transportation) rather than, as is more typical, on the housing, capital investment, and durable goods sectors. Lower-paid workers, as well as women and minorities, are over-represented in the most-affected sectors, and thus have borne a disproportionate share of the job and income losses. And, the virus has affected almost every country, with potentially devastating consequences for trade and international investment.

Because this recession is unprecedented in so many ways, forecasting the recovery is difficult. The course of the pandemic itself is by far the most important factor. As long as people fear catching a potentially deadly illness from other people, they will be cautious about resuming normal activities, even after state and local governments lift lockdowns. Thus, controlling the spread of the virus must be the first priority for restoring more-normal levels of economic activity—but, more importantly, for saving possibly tens of thousands of lives. Members of Congress, local leaders, and other policymakers need to do all they can to support testing and contact tracing, medical research, and sufficient hospital capacity, and they must work to ensure that businesses, schools, and public transportation have what they need to operate safely. Both authors of this testimony are serving on state re-opening commissions, which has provided us insight into the substantial challenges to safe re-opening.

If the pandemic comes under better control, economic recovery should follow. However, the pace of the recovery could be slow and uneven, for several reasons. First, in the face of ongoing uncertainty, households and businesses may remain cautious for a time. They may increase saving and reduce spending, hiring, and capital investment. The longer the recession lasts, the greater the damage it will inflict on household and business balance sheets and the longer it will take to repair the damage. Second, the depth of the recession may leave scars—business closures and the deterioration of unemployed workers’ skills—that will affect growth for several years. Third, depending on the course of the virus, some restructuring of the economy may be needed. For example, people and resources will need to be redeployed out of the sectors most damaged by the pandemic, and business operations will need to be reorganized to protect workers and customers. All of that will take time and money. Fiscal and monetary policies must aim to speed the recovery and minimize the recession’s lasting effects.

ACTIONS BY THE FEDERAL RESERVE

The Federal Reserve has moved swiftly and forcefully in this crisis. It eased monetary policy in March by lowering the federal funds rate, the overnight interest rate on loans between banks, nearly to zero and indicating that it plans to keep rates low for several years. Low interest rates probably had limited economic benefits in the spring. Lockdowns prevented people from spending or working more. However, we expect low rates will spur spending in sectors like housing as the economy reopens. And the Fed may well do more in coming months as re-opening proceeds and as the outlook for inflation, jobs, and growth becomes somewhat clearer. In particular, to maintain downward pressure on longer-term interest rates, the Federal Open Market Committee (FOMC) likely will provide forward guidance about the economic conditions it would need to see before it considers raising its overnight target rate.  And it likely will clarify its plans for further securities purchases (quantitative easing). It is possible, though not certain, that the FOMC will also implement yield-curve control by targeting medium-term interest rates. It could, for example, target two-year rates by announcing its willingness to buy two-year Treasury notes at a fixed yield. The completion of the Fed’s internal review of its tools and framework in coming months will help guide these decisions.

The Fed also has been active beyond monetary policy.

First, the Fed has served as market maker of last resort by acting to stabilize critical financial markets when capital or other regulatory constraints have interfered with normal market-making or arbitrage. The Fed has served this role for repurchase agreements (repos) since September, when intermittent liquidity shortages led to spikes in repo rates. Banks did not provide liquidity to offset these spikes, as they normally would, citing balance sheet limits and other constraints. Because repo markets are critical to the functioning of broader financial and credit markets, as well as for the transmission of monetary policy, the Fed has restored more-normal function in repo markets by conducting large-scale repo operations and by steadily increasing the quantity of reserves in the banking system.

An even larger shock occurred in March, when uncertainty about the pandemic led hedge funds and others to scramble to raise cash by selling longer-term securities. The upsurge in the supply of longer-term securities, including Treasuries, was more than dealers and other market-makers could handle. Key financial markets, including for Treasury securities, experienced substantial volatility. To stabilize these markets, which like the repo market play a critical role in our financial system, the Fed purchased large quantities of Treasuries and mortgage-backed securities, again serving as market maker of last resort. It also set up a new repo facility to allow foreign official institutions to borrow dollars, using their Treasury reserves as collateral, thus avoiding the need to sell those Treasuries. Although risk and liquidity premiums in these key markets have returned closer to normal, at some point the Fed and the Treasury will need to review why the market-making facilities in place before the pandemic hit did not work more efficiently.

Second, the Fed has served as lender of last resort to the financial system, a classic function of central banks. Banks and other financial intermediaries typically borrow short and lend long—that is, they rely heavily on short-term funding to finance long-term loans and investments. If they lose their short-term funding—because their funders lose confidence or for other reasons—they can be forced to sell their assets in fire sales, restrict credit to customers, and, in extreme cases, become insolvent. Central banks can short-circuit that dangerous dynamic by lending to financial institutions against good collateral, replacing the lost liquidity. In the 2007-2009 crisis, which centered on the financial system and included a global financial panic, the Fed as lender of last resort took many actions to provide liquidity to financial institutions, with the goal of stabilizing the system and preserving the flow of credit to the economy.

Fortunately, the financial system is in much better shape today than in was during the financial crisis. Banks in particular are strong, with much higher levels of capital and liquidity. The Fed nevertheless has once again taken steps to ensure that the financial system has sufficient liquidity. Largely replicating our playbook from the crisis era, the Fed has eased terms on the discount window (which provides short-term loans to banks); re-established the Primary Dealer Credit Facility (which lends to broker-dealers); and established a facility that lends indirectly to money market mutual funds, ensuring that the funds can meet depositor withdrawals. In a novel step, the Fed also created a facility that lends to banks, without recourse, against Payroll Protection Program loans, ensuring that banks have sufficient funds to make those loans.

Under the heading of lender of last resort to the financial system, establishing currency swap lines with fourteen foreign central banks was one of the most important actions the Fed took in the 2007-2009 crisis. The Fed has revived this program. Currency swap lines allow foreign central banks (who assume all the credit risk) to lend dollars to banks in their jurisdictions. The broad availability of dollar liquidity is essential because most global banks do substantial borrowing and lending in dollars, including lending within the United States. The swap lines sustain the flow of dollar credit and reduce volatility in dollar-based markets, to the benefit of the U.S. economy.

Third, the Federal Reserve, with the support of the Congress and the Treasury, has also served during the current crisis as a lender of last resort to the non-financial sector, backstopping key credit markets facing the prospect of severe disruption from the pandemic. To take on this role, the Fed invoked its emergency lending powers under Section 13(3) of the Federal Reserve Act. Since those powers require that the Fed’s lending be well secured, it has had to rely on funds appropriated by the Congress and allocated by the Treasury to cover possible losses. Using these authorities, the Fed revived financial crisis-era facilities to stabilize commercial paper and asset-backed securities markets. Going beyond the financial crisis playbook, the Fed has also added new facilities to lend to corporations and state and local governments and to buy outstanding corporate bonds.

These programs have not extended much credit, so far, but that does not mean they have not succeeded. By establishing the programs, the Fed gave private investors the confidence to re-engage by reassuring them that the government would not allow these critical markets to become dysfunctional. Indeed, the corporate and municipal bond markets largely stabilized after the announcements, before any loans were made. Of course, if these markets seize up again, the Fed’s programs can extend credit.

The Fed also established the Main Street Lending Program to lend (through banks) to medium-sized companies. It is too soon, however, to judge its performance. This program is very different from anything the Fed has attempted before and poses difficult technical challenges. Although the Fed took many public comments while setting up the program, and made substantial changes, questions remain about how many banks and borrowers will participate. The Fed and Treasury may have to further ease terms for borrowers and increase incentives for banks for this program to have the desired effect. Or, the Fed and Treasury could add a new facility, along the lines of funding-for-lending programs run by the Bank of England and the European Central Bank, that simply subsidize banks for making additional loans to qualifying borrowers (for example, businesses below a certain size). That approach leaves the underwriting decision completely with the banks, while the size of the subsidy can be adjusted as needed to achieve the desired level of lending.

Finally, the Fed has also taken actions as a bank regulator—for example, encouraging banks to work with borrowers hobbled by the pandemic. It decided recently, based on stress test results, to bar stock buybacks by banks and to limit—but not eliminate—their dividends.  Based on our experience in the global financial crisis, we think the Fed may find it needs to go further. Although banks are currently strong, it is possible the pandemic will so damage the economy that credit losses mount rapidly. For a successful recovery, the banking system must remain strong and able to lend.

Is there more the Fed could do? As we noted, the Fed likely will provide more clarity about its monetary policy plans, and it may need to adjust the terms or borrower eligibility requirements of its various lending facilities. Broadly speaking, though, the Fed’s response has been forceful, forward-looking, and comprehensive. But, as Chair Powell often notes, the Fed’s authorities allow it to lend, not spend. Some households and firms will need subsidies or grants, rather than loans, and spending is, of course, the province of the Congress.

WHAT FISCAL POLICY MIGHT DO

The fiscal response to the pandemic has thus far been quite effective. Enhanced unemployment insurance and the Paycheck Protection Program have helped unemployed workers and their families, together with many businesses, survive the spring shutdowns. The fiscal support for the Fed’s lending programs likely will help preserve credit availability, possibly with only a portion of the allocated funds being spent.

However, some programs authorized by the Congress are ending, and new actions are necessary. Our recommendations for further fiscal action are:

First, Congress should develop a comprehensive plan to support medical research; increase testing, contact tracing and hospital capacity; make available critical supplies; and support state and local efforts to safely open businesses, schools, and public transportation.

Nothing is more important for restoring economic growth than improving public health. Investments in this area are likely to pay off many times over.



14 hospitals bringing back furloughed workers

https://www.beckershospitalreview.com/workforce/9-hospitals-bringing-back-furloughed-employees.html?utm_medium=email

COVID-19 Return To Work Quiz! | Constangy, Brooks, Smith ...

Many U.S. hospitals and health systems have furloughed staff to help offset revenue losses from the COVID-19 pandemic. Now, some are starting to bring furloughed workers back as they resume nonemergency procedures and medical appointments. 

Here are 14 reported in July and June:

Editor’s Note: This webpage will be updated routinely. 

July

1. Elmeria, N.Y.-based Arnot Health said it brought back about half of the about 400 people it furloughed in mid-April, according to WETM-TV .

2. Guthrie said most furloughed staff have returned to the Sayre, Pa.-based health system, according to WETM-TV .

3. Charlottesville-based University of Virginia Health System will end some of its pandemic-related furloughs and pay cuts by the end of July and others in August.

4. Holyoke (Mass.) Medical Center brought back nearly 170 of 250 furloughed employees at the start of July, and another 80 to 90 are expected to return at month’s end, President and CEO Spiros Hatiras told BusinessWest.

5. Sarasota (Fla.) Memorial Health Care System brought back 640 furloughed workers.

June

6. MUSC Health, an eight-hospital system based in Charleston, S.C., called back nearly half of the employees who had been furloughed.

7. Lewiston-based Central Maine Healthcare has recalled about three-quarters of its 300 employees furloughed in April, spokesperson Kate Carlisle told the Sun Journal. The remaining furloughed employees are expected to return by mid-July.

8. Lewiston, Maine-based St. Mary’s Health System has recalled 80 percent to 85 percent of its 77 employees furloughed in April, spokesperson Steve Costello told the Sun Journal. Others are expected to return in July.

9. About 3,000 furloughed workers at hospitals in the Dayton, Ohio, region have been called back to work, according to the Springfield News-Sun. As of June 24, 2,606 workers remained on furlough, Sarah Hackenbracht, CEO of the Greater Dayton Area Hospital Association, told the newspaper. Initially, 5,648 hospital employees were furloughed in the 11-county region during the pandemic.

10. As of June 1, Claxton-Hepburn Medical Center in Ogdensburg, N.Y., brought back 34 employees, including nurses and staff for surgery, according to WWNY-TV. This is out of about 175 employees who were furloughed in April.

11. St. Lawrence Health System, a three-hospital system in Potsdam, N.Y., had called 80 furloughed employees back to work as of June 1, according to WWNY-TV. The health system furloughed about 400 workers.

12. St. Joseph’s Health in Syracuse, N.Y., had brought back 135 workers as of June 1, according to Syracuse.com. The organization, a member of Livonia, Mich.-based Trinity Health, furloughed 500 employees in April.

13. Crouse Health in Syracuse, N.Y., an affiliate of New Hyde Park, N.Y.-based Northwell Health, had brought back 63 of its 278 furloughed workers as of June 1, according to Syracuse.com.

14. Lewis County Health System CEO Gerald Cayer said June 12 that the Lowville, N.Y.-based organization soon will end the eight-week furlough that put 14 percent of its workforce on unpaid leave, according to nny360.com. Ten furloughed employees had returned to work as of June 12, and Mr. Cayer said other employees would return to work beginning June 21.


700+ Chicago nurses reach labor deal after 2-week strike

https://www.beckershospitalreview.com/hr/700-chicago-nurses-reach-labor-deal-after-2-week-strike.html?utm_medium=email

How Have Health Workers Won Improvements to Patient Care? Strikes.

More than 700 nurses who walked off the job for two weeks approved a new contract July 20 with Amita Health Saint Joseph Medical Center Joliet (Ill.), hospital and union officials confirmed to Becker’s.

The nurses are represented by the Illinois Nurses Association, and both sides had been negotiating a new contract since early spring. Nurses had worked without a contract since May 9 and went on strike July 4.

Pay and benefits have been key sticking points at the bargaining table. Additionally, the Illinois Nurses Association had claimed the hospital was not adequately addressing staffing issues.

The new contract includes agreements by the hospital to improve the staffing guidelines on certain units before Dec. 31 and to meet and confer with the union by that date to improve staffing throughout the facility, the union said in a news release. Health insurance premium contributions were also capped at 25 percent for full-time nurses and 35 percent for part-time nurses, the union said.

“While a majority of nurses voted for this contract, there are still many nurses who want to see more progress on safe staffing,” said Pat Meade, RN, one of the lead union negotiators. “We will continue the fight for safe staffing through enforcement of our contract and in Springfield.”

In an emailed statement to Becker’s, hospital spokesperson Tim Nelson said Amita Health is pleased with the agreement and called it “fair and just for all involved.”

The hospital hired temporary nurses from an outside agency to fill in during the strike.

Mr. Nelson said the hospital’s nurses will return to work July 22 for their regularly scheduled shifts.


Hospital margins could sink to a negative 7% this year: 5 things to know

https://www.beckershospitalreview.com/finance/hospital-margins-could-sink-to-a-negative-7-this-year-5-things-to-know.html?utm_medium=email

New Kaufman Hall Report: Hospital Finances Crashed in April ...

The COVID-19 pandemic has created financial challenges for hospitals and health systems, and, without additional federal aid, half of US hospitals could be operating in the red in the second half of this year, according to an analysis released by the American Hospital Association on July 21.

Five takeaways from the analysis: 

1. Before the COVID-19 pandemic, the median hospital margin was 3.5 percent. COVID-19 is expected to drive the median hospital margin from positive to negative. 

2. Without funding from the Coronavirus Aid, Relief and Economic Security Act, hospital margins would have been a negative 15 percent in the second quarter of 2020. Margins are still expected to drop to a negative 3 percent in the second quarter.

3. Without additional aid from the federal government, hospital margins could sink to a negative 7 percent in the second half of this year. 

4. In the second quarter of this year, nearly half of U.S. hospitals had negative margins. Those hospitals will remain with negative margins without further financial support.  

5. “Heading into the COVID-19 crisis, the financial health of many hospitals and health systems were challenged, with many operating in the red,” said hospital association President and CEO Rick Pollack in a news release. “As today’s analysis shows, this pandemic is the greatest financial threat in history for hospitals and health systems and is a serious obstacle to keeping the doors open for many.” 

The full report, prepared by Kaufman, Hall & Associates and released by the AHA, is available here. 


Trump said more Covid-19 testing ‘creates more cases.’ We did the math

Trump said more Covid-19 testing ‘creates more cases.’ We did the math

Testing silhouette

The counter-narrative began almost instantly. After the U.S. count of Covid-19 cases began an inexorable rise in June, the White House sought to assure Americans that the increase was, basically, an illusion, created by an increase in testing for the novel coronavirus.

In a June 15 tweet, President Trump said testing “makes us look bad.” At his campaign rally in Tulsa five days later, he said he had asked his “people” to “slow the testing down, please.” At a White House press conference last week, he told reporters, “When you test, you create cases.”

And in an interview with Fox News that aired Sunday, Trump could not have been clearer: “Cases are up because we have the best testing in the world and we have the most testing.” Basically, the president was arguing that the U.S. had just as many new cases in June and July as it did in May but, with fewer tests being done in May, they weren’t being detected; with more testing now, they are.

A new STAT analysis of testing data for all 50 states and the District of Columbia, however, shows with simple-to-understand numbers why Trump’s claim is wrong. In only seven states was the rise in reported cases from mid-May to mid-July driven primarily by increased testing. In the other 26 states — among the 33 that saw cases increase during that period — the case count rose because there was actually more disease.

May had brought signs of hope that the U.S. had gotten its Covid-19 outbreak under control, with about 20,000 new cases reported per day after April highs closer to 30,000. But by late June, the daily count climbed to about 40,000, and now it’s at about 70,000. The STAT analysis shows that spread of the virus, far more than testing, explains that increase.

Epidemiologists and infectious disease experts have disputed the White House claims for weeks, citing rising hospitalization numbers and deaths. It’s hard to argue that extremely sick people, let alone dead people, had been obscured by low levels of testing but suddenly revealed by higher levels.

Without a doubt, many cases of Covid-19 in March, April, and May weren’t picked up. In late June, Centers for Disease Control and Prevention Director Robert Redfield told reporters that as many as 90% of cases had been missed; that is, although there were 2.3 million confirmed cases in the U.S. then, some 20 million people had probably been infected. But that reasoning applies today, too: Despite months of government claims to the contrary, not everyone who wants, or should have, a test is getting one.

Simple math belies the “it’s just because of more testing” claim — with some fascinating exceptions.

Using data from Covid Tracking, STAT looked at the number of people tested and the number who tested positive for the disease (cases) in every state and Washington, D.C. We did that for three dates: in mid-May, mid-June, and mid-July. (Due to reporting anomalies, the dates selected sometimes differed by a day or two between states.)

For each date, we calculated the number of cases found per 1,000 tests — a measure of the disease’s prevalence. For example, in Florida on May 13, that rate was 32. On June 13 it was 75. On July 13 it was 193. On May 13, Florida tested 15,159 people; on July 13, it tested 65,567. So indeed, the number of tests has increased.

But the number of cases per thousand, which is independent of the number of tests, has skyrocketed. On May 13, Florida recorded 479 cases; on July 13, it found 12,624. If the prevalence of Covid-19 were the same in July as in May, Florida would have found only 2,098 cases. In other words, 10,526 of the July 13 cases are not due to increased testing, but, instead, to the increased prevalence of disease.

Florida Gov. Ron DeSantis, however, echoes Trump’s explanation, telling a Saturday press briefing that his state’s soaring caseload is largely the result of more testing of people with no or minimal symptoms. “We’re now capturing a lot of those folks,” he said.

In fact, Florida has seen a sevenfold increase in cases in the past month, said Youyang Gu, who developed a well-respected, machine-learning-based model of Covid-19 whose projections have been quite accurate. “In the same time span, the number of tests only increased by a factor of two,” he said. “Obviously, if you double the testing but the number of cases increased sevenfold, then the virus is clearly spreading.”

Testing/cases graphic

The complete data for all 50 states can be found here.


Other states with soaring cases tell the same story as Florida.

In Arizona, the case-finding rate rose from 90 in May to 140 in June to 208 in July. Of its 2,537 cases on July 12, 1,441 were due to increased prevalence.

South Carolina has also experienced a steep rise in prevalence as its case count quintupled: Of the 2,280 cases on July 9, 1,869 were due to rising prevalence, not more testing. Texas and Georgia are similar: rising case counts well beyond increases in testing. In all, 26 states that did more testing in July than in May found more cases because Covid-19 was more prevalent. In 15 of them, the number of cases per 1,000 people tested had more than doubled.

Seven states (Colorado, Indiana, Michigan, Missouri, North Carolina, Ohio, and Wisconsin) meet the three criteria needed to support Trump’s claim that we’re seeing more cases only, or mostly, because we’re doing more testing. The criteria are doing more tests in July than in May, finding more cases on a typical day in July than May, but seeing the number of cases per 1,000 tests decline or remain unchanged from May to July.

Take Missouri. It’s reporting more cases, but not because the virus is exploding there (despite those crowded holiday scenes at Lake of the Ozarks). Its case finding rate has been pretty stable or even declining, from 48 in mid-May to 44 in mid-July. By tripling its number of daily tests, Missouri is finding roughly triple the number of cases.

California comes close to meeting the three criteria, but doesn’t quite. Its number of daily tests more than quadrupled from May to July, from roughly 32,000 to 137,000. But the rate of cases being found has risen, though only about 10%, from 55 to 61 per 1,000 tests. So a big reason — but not the main reason, as in Missouri — more cases are being found is that more testing is being done. Washington is similar: more testing, more cases, but also slightly greater prevalence of disease in mid-July compared to mid-May; its worsening situation is real.

New York tells the opposite story: more testing found fewer cases. The state nearly doubled its daily tests from May 13 (33,794) to July 12 (62,418). But its cases fell from 2,176 to 557. If the case rate had not dropped (by 86 %), New York’s expanded testing would have found 3,995 cases on July 12.

In fact, 16 states plus the District of Columbia are like New York. They tested much more, but found fewer cases in July than May — in most, not only “fewer” in the sense of fewer cases per 1,000 but fewer in absolute terms. New Jersey reported 10,246 tests and 1,144 cases on May 14, and 20,846 tests with a mere 393 new cases on July 14. Again, the virus hasn’t disappeared, but the expansion of testing, far from “creating” cases, has brought good news: In these states, it’s much less prevalent than it was two months ago.


Axios-Ipsos poll: The skeptics are growing

https://www.axios.com/axios-ipsos-poll-gop-skeptics-growing-deaths-e6ad6be5-c78f-43bb-9230-c39a20c8beb5.html

Axios-Ipsos poll: The skeptics are growing - Axios

A rising number of Americans — now nearly one in three — don’t believe the virus’ death toll is as high as the official count, despite surging new infections and hospitalizations, per this week’s installment of the Axios-Ipsos Coronavirus Index.

Between the lines: Republicans, Fox News watchers and people who say they have no main source of news are driving this trend.

Why it matters: It shows President Trump’s enduring influence on his base, even as Americans overall say they are increasingly dissatisfied with his handling of the virus and political support is shifting toward Joe Biden.

What they’re saying: “We live in highly tribal and partisan times, and people are more likely to believe cues and signals from their political leaders than the scientists or the experts,” says Cliff Young, president of Ipsos U.S. Public Affairs.

  • “And that’s just the purest form of populism, the demonization of experts to further political ends. But to what end? Fantasy is meeting reality head-on right now.”
  • “People can see the world around them, they know it’s different, but they still can think that the media and politicos are using it to go after Trump.”

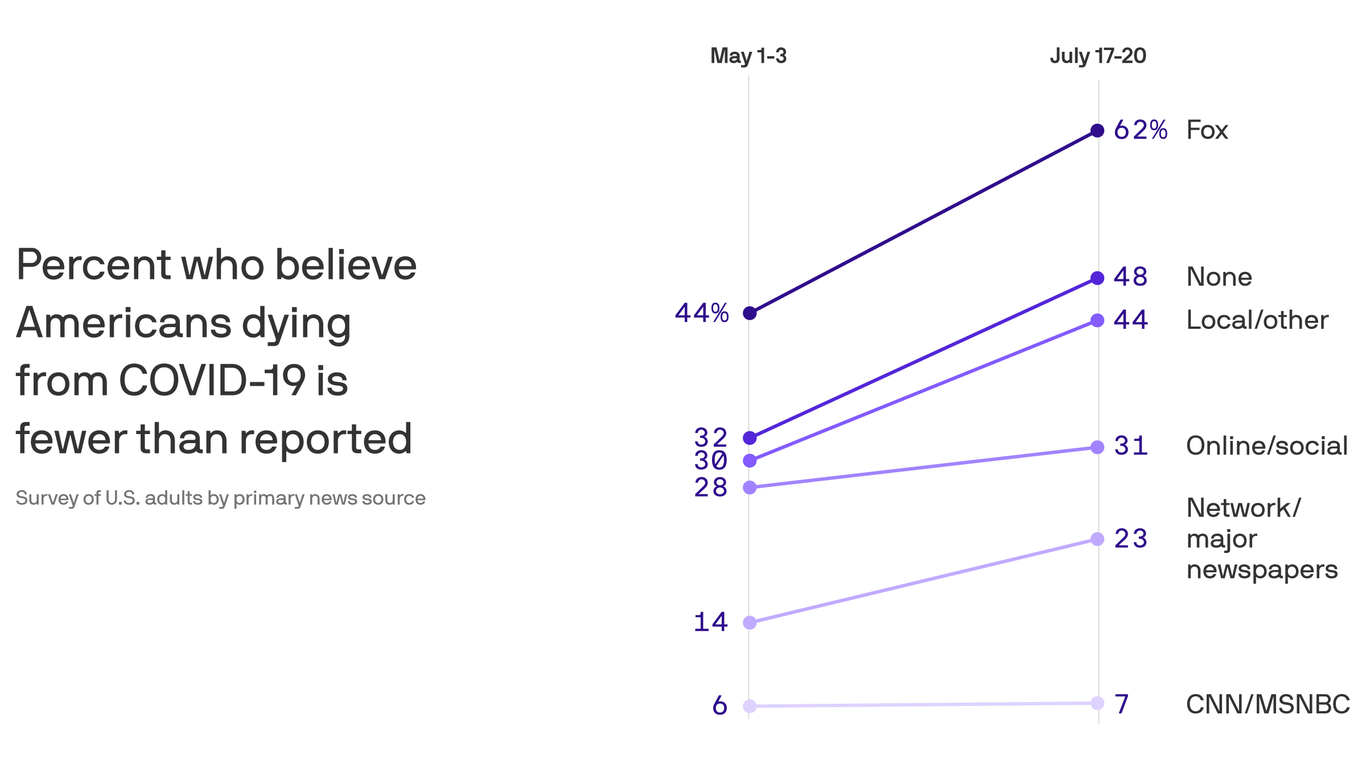
By the numbers: Overall, 31% of Americans say they believe the number of Americans dying is lower than the number reported, up sizably from 23% when we asked the same question in May.

Here’s what’s driving the shift in Week 17 of our national survey:

  • Republicans who say the death count is overinflated rose from 40% to 59%.
  • Among independents, that share rose from 24% to 32%.
  • The small share of Democrats with that view was effectively flat, ticking up from 7% to 9%.
  • Most Americans still believe the actual number of deaths is either higher (37%) or on par with (31%) the official count.

Where you get your news has a strong correlation to your faith in the numbers.

  • Fox News watchers who say deaths are being over-counted shot up from 44% to 62%, even higher than Republicans overall.
  • Other big gains came from those who say they have no primary news source, from 32% to 48%; and those whose primary sources include local news, from 30% to 44%.
  • There was a smaller increase among people whose primary news source is one of the networks or major U.S. newspapers, while views of those who primarily watch CNN and MSNBC remained about the same.

The big picture: The survey shows most Americans are digging in for a long fight against the virus, even if they have conflicting views about what to believe.

  • 72% say they’re prepared to maintain social distancing or self-quarantining for as long as it takes — up from 49% in May — as people realize the end is more than a couple of months off.

This survey finds the highest overall use of face masks since the pandemic began — with 99% of Democrats and 75% of Republicans now saying they’re wearing a mask sometimes or all of the time when they go out.

  • But there’s enough inconsistency in people’s precautions to undercut much of the gains.
  • Only 40% say they wore masks sometimes or all the time when visiting family and friends. And parents are less likely to make their children wear masks outside the home than to do so themselves.

1 big finger wag: Most Americans blame someone other than themselves for the crisis.

  • Three-fourths of respondents say most other Americans are behaving in ways that are making the country’s recovery from the COVID-19 pandemic worse, while one-fourth said they’re making it better.
  • Democrats were more likely (83%) than other groups to say others are making things worse.


The state of the global race for a coronavirus vaccine

https://www.axios.com/race-for-coronavirus-vaccine-us-china-oxford-eace8d13-59b6-404f-9dd9-569d00e01f58.html

The state of the global race for a coronavirus vaccine - Axios

Vaccines from the U.K., U.S. and China are sprinting ahead in a global race that involves at least 197 vaccine candidates and is producing geopolitical clashes even as it promises a possible pandemic escape route.

Driving the news: The first two candidates to reach phase three trials — one from the University of Oxford and AstraZeneca, the other from China — both appear safe and produce immune responses, according to preliminary results published today in The Lancet.

  • A vaccine from Moderna, the U.S. biotech firm, is heading into phase three trials after similarly encouraging initial results.
  • There are at least 16 other vaccines currently in clinical trials in Australia, France, Germany, India, Russia, South Korea, the U.K., the U.S. and China, which is experimenting with a variety of vaccine types and has five candidates already in trials.

What they’re saying: Experts are increasingly confident that it’s no longer a question of if but when vaccines will be available.

  • “Absolutely, for sure, we will get more than one vaccine,” Barry Bloom, a professor of public health at Harvard, told reporters today.
  • He cautioned that it’s not yet clear which vaccines will win the race and that we won’t know how effective they are in protecting against COVID-19 — and for how long — until after phase three trials.

Pressed on when a vaccine could be approved, Bloom said that while it seemed “utterly crazy seven months ago,” January was looking increasingly realistic.

  • Richard Horton, The Lancet‘s editor-in-chief, is more cautious: “If we have a vaccine by the end of 2021, we will have done incredibly well.”
  • Zeke Emanuel, chair of the Department of Medical Ethics and Health Policy at the University of Pennsylvania, splits the difference: “Seven months after we got the genome, to have three vaccines in phase three is literally unprecedented. If in six to eight months we get a license, that will be, again, totally unprecedented in world history.”

But, but, but: “Getting something approved doesn’t protect you from COVID,” Emanuel warns.

  • The challenges of producing, distributing and delivering a vaccine (particularly in two doses, as the Oxford vaccine requires) around the entire world are hard to even fathom.
  • Even distributing a vaccine in one country will require an unprecedented buildup of facilities, materials (like glass vials), personnel and protocols, assuming enough people are even willing to take it.

Illustration of syringe in the earth

The global picture is even murkier. Several countries and pharmaceutical companies have committed to “fair and equitable” distribution.

  • In principle, that would suggest a vulnerable front-line worker in Uganda, say, should get the vaccine before a young, healthy person in the United States.
  • In practice, well … no one really knows.

The bottom line: “It’s very fragmented, and in some ways that’s understandable,” Horton says. “But the danger of that is that many countries will lose out and only the strongest country, the country with the most money, will win.”

  • If countries hoard supplies rather than prioritizing at-risk people elsewhere, Bloom says, “that should be a cause not just of global concern but of global shame.”

For now, governments are prioritizing their own populations.

  • The Trump administration is pouring at least $3.5 billion into the development and manufacture of three leading vaccine candidates, with the promise of hundreds of millions of doses should they prove safe and effective.
  • Even as the homegrown Oxford vaccine takes a global lead, the U.K. is hedging its bets by purchasing 90 million doses being developed by German and French companies.
  • The U.K. and U.S. have both also put in large pre-orders of the Oxford vaccine, though AstraZeneca says 1 billion doses will also be manufactured in India and distributed mainly to other low- and middle-income countries.
  • The WHO and EU are attempting to create a framework for distributing the vaccine globally, though the U.S. has declined to take part.

Illustration of syringes forming a health plus/cross

What to watch: Managing the largest vaccination project in history will clearly require global collaboration — but it’s also becoming a competition between rival powers.

  • “Six months from now, we will be in a situation where a few countries will have vaccines, and we believe those countries will be the UK, Russia, China and the US,” Kirill Dmitriev, the head of Russia’s sovereign wealth fund, told the FT.

Between the lines: Others are less certain Russia will be in that group, though Dmitriev says a vaccine bankrolled by his fund and developed by the state-run Gamaleya Institute will move into phase three trials next month.

“Basically other countries will decide, you know, which vaccine to buy … and who do you trust?”

— Kirill Dmitriev

State of play: There’s a clear lack of trust among the competitors.

  • According to the U.S, U.K. and Canada, hackers linked to Russian military intelligence have attempted to steal vaccine research in order to aid their own efforts.
  • The U.S. has also accused China of pilfering American research.
  • House Republican leader Kevin McCarthy will introduce a bill on Tuesday that would sanction foreign hackers attempting to steal U.S. vaccine research, according to a copy of the bill obtained by Axios’ Alayna Treene.

Zoom out: It will be a victory for humanity when the first coronavirus vaccines are approved. But the competition to obtain one early goes beyond national pride.

  • Vaccines will save countless lives, drive economic recoveries, and could provide rare opportunities to generate goodwill and influence abroad.
  • “There’s a huge soft power advantage to the U.S. ensuring that other countries can get the vaccine and protect themselves,” Emanuel says. The same would, of course, be true for China.

The bottom line: The race is on, but it won’t end when the first vaccine is approved.


We’re still in the early stages of the vaccine race

https://www.axios.com/newsletters/axios-vitals-a91eb4fb-e10d-46cf-b919-96e1e6e08b22.html?utm_source=newsletter&utm_medium=email&utm_campaign=newsletter_axiosvitals&stream=top

Oxford and CanSino released coronavirus vaccine data. It's still ...

New clinical trial data from two experimental coronavirus vaccines — one from Oxford University and AstraZeneca in the U.K., and the other from CanSino Biologics in China — are providing cautious optimism in the race to combat the pandemic, Axios’ Bob Herman reports.

The big picture: Science has never moved this fast to develop a vaccine. And researchers are still several months away from a clearer idea of whether the leading candidates help people generate robust immune responses to this virus.

Driving the news: The Oxford and CanSino vaccines didn’t lead to any severe adverse reactions or hospitalizations, according to the results released yesterday.

  • Safety — not efficacy — was the main thing these studies were supposed to be testing. And they performed well enough to move on to further trials.
  • Competing candidates from Moderna and Pfizer/BioNTech have also performed well in safety trials.

Yes, but: Future trials will be the ones that tell us whether any of these potential vaccines actually trigger patients’ immune systems to respond to the virus.

  • In the results released yesterday, Oxford researchers gave their vaccine to 543 people but only tested 35 for “neutralizing antibodies.” A separate, nonrandomized group of 10 people got a booster dose of the Oxford vaccine a month after the initial dose.
  • Preliminary antibody responses from CanSino’s vaccine were “disappointing” to several experts.

The bottom line: There are 23 coronavirus vaccines in clinical testing right now, according to the World Health Organization.

  • We now have data on the first four, but the studies mostly are confirming that the vaccines aren’t severely harmful and that large-scale studies are warranted — not that they definitely work yet.
  • “It is good and hopeful news indeed, but we’ll only know when the large trials are done,” tweeted Robert Califf, a former FDA commissioner under President Obama.


A coronavirus vaccine: Where does it stand?

https://www.politifact.com/article/2020/jul/13/coronavirus-vaccine-where-does-it-stand/?fbclid=IwAR3hk04P0N3AuJXsKCr_JqV8vu0qZ6njsHE3if6xX6E2AxsllV1m81LjtX4

Coronavirus vaccines get a biotech boost

IF YOUR TIME IS SHORT

• Scientists are expressing cautious optimism that a vaccine can be ready to go by the late spring of 2021, although it’s unclear how much longer it would take to distribute the vaccine widely.

• Two possible vaccines are in phase 3 clinical trials; once those trials are completed, they would be candidates for approval. Another eight vaccines have begun phase 2 trials. And more than 100 other vaccines that haven’t begun clinical trials are in the pipeline.

• The Food and Drug Administration recently produced guidelines for the minimum effectiveness of vaccines seeking the agency’s approval. Vaccine officials say these guidelines are important to ensure public confidence in vaccines.


More than four months into the coronavirus pandemic, how close is the U.S. and the world to a safe and effective vaccine? Scientists say they see steady progress and are expressing cautious optimism that a vaccine could be ready by spring of 2021.

As of early July, there were roughly 160 vaccine projects under way worldwide, according to the World Health Organization. 

Generally, a vaccine trial has several phases. In an initial phase, the vaccine is given to 20 to 100 healthy volunteers. The focus in this phase is to make sure the vaccine is safe, and to note any side effects.

In the second phase, there are hundreds of volunteers. In addition to monitoring safety, researchers try to determine whether shots produce an immune-system response.

The third phase involves thousands of patients. This phase continues the goals of the first two, but adds a focus on how effective the vaccine is. This phase also collects data on more unusual negative side effects.

In ordinary circumstances, these phases take years to complete. But for coronavirus, the timeline is being shortened. This has spurred more public-private partnerships and significantly increased funding.

Here’s a rundown of the 13 vaccine candidates that are furthest along in the clinical phases:

Coronavirus vaccines that are the furthest along:

A Coronavirus Vaccine: Where Does It Stand? – Corridor News

The three vaccine candidates that are furthest along are both in phase 3. 

One is being developed by researchers at Oxford University in the U.K. It uses a weakened version of a virus that causes common colds in chimpanzees. Researchers then added proteins, known as antigens, from the novel coronavirus, in the hope that these could prime the human immune system to fight the virus once it encounters it.

Another candidate in a phase 3 trial is being developed in China. It uses a killed, and thus safe, version of the novel coronavirus to spur an immune reaction.

And on July 15, the biotech company Moderna, which is partnering with the National Institutes of Health, announced that it would be moving to phase 3 within two weeks.

Two others have made it as far as phase 2, while eight others are finishing their phase 1 trials while also beginning phase 2 trials.

These candidates are being developed by a mix of corporations and institutions in several countries. These efforts seek to leverage a range of different technologies.

One uses RNA material that provides the instructions for a body to produce the needed antigens itself. This is a relatively untested approach to vaccination, but if it works, it has aspects that could make it easier to manufacture. Another approach is similar, but uses DNA instead of RNA.

One U.S. biotech firm, Novavax, is receiving federal funding to produce a vaccine that uses a lab-made protein to inspire an immune response.

Beyond these, another 10 vaccine candidates are in phase 1 clinical trials, while another 140 haven’t reached the clinical phase yet.

Having so many potential vaccines this far along is impressive, experts say, given the short time scientists have known about the novel coronavirus. 

“Overall, the pace of development and advancement to Phase 3 trials is impressive,” said Matthew B. Laurens, associate professor at the University of Maryland School of Medicine’s Center for Vaccine Development and Global Health. “The public-private partnerships have been highly successful and are achieving goals for rapid vaccine development.”

In addition, the fact that several types of vaccine approaches are being tested means we aren’t putting all of our eggs in one basket.

“We will need several candidates should any one of these experience difficulties in manufacturing or show a safety signal when implemented in larger numbers of people,” Laurens said.

Meanwhile, at a time of rising public skepticism of government and vaccines, the Food and Drug Administration recently released additional guidelines on vaccine effectiveness. The new guidance requires vaccines to prevent or decrease the severity of the disease at least 50% of the time if they are to win the agency’s approval.

The FDA guidelines “reaffirmed the very rigorous FDA process for approving any vaccine. That gives a great deal of reassurance that this was going to be handled by the book,” said William Schaffner, a professor of preventive medicine and infectious diseases at Vanderbilt University Medical Center. “The more we talk about doing things fast, the more the public thinks, ‘They’re probably cutting corners.’”

How fast will we have access to a workable vaccine?

In early April, Kathleen M. Neuzil, director of the University of Maryland’s vaccine center, told PolitiFact that if all went well, there might be five or six vaccines in trials within six months. Now, three and a half months later, there are two to three times that number.

Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases, and other officials have remained consistent in their estimation of the timeline: 12 to 18 months from the start of the pandemic, or roughly the late spring of 2021.

Schaffner told PolitiFact that he continues to see the first quarter of 2021 as a reasonable target. “I think that’s where the needle is pointing,” he said.

It remains to be seen how fast vaccines can be manufactured and distributed once approved for general use. Officials are also grappling with which Americans will get access first. So it’s unclear how long a person would have to wait to get vaccinated.

Laurens said he is not overly concerned about the distribution, because that is something that officials have long experience with. “Well-established programs exist for vaccine distribution, including for seasonal vaccination of large numbers of individuals,” he said.

Another hopeful sign, Schaffner said, is that the coronavirus itself seems to be relatively stable. There had been concern that the novel coronavirus, like many other viruses, is mutating over time. If the virus changes enough, that could become a problem that bedevils vaccine researchers.

But so far, that hasn’t happened. Even if evidence emerges that mutations are making the virus more transmissible, or that a new variant is making people sicker, that shouldn’t affect the vaccine process. “The central core of the virus would remain the same,” Schaffner said.

During the past month, there has been relatively little news about how much progress is being made on particular vaccines. Schaffner is not worried by the relative quiet.

“In a vaccine trial, if there’s an adverse safety finding, the guillotine comes down and that trial is stopped,” he said. “So quiet is good, because we’d know if something bad happens.”


Op-Ed: We Still Don’t Know the Risk Posed by COVID-19

https://www.medpagetoday.com/infectiousdisease/covid19/87629?xid=fb_o&trw=no&fbclid=IwAR2V6CbOCIXDf2K9sJCcRb0PhbqM4inXixe_poOFYudOcoUFZCmU2JzyrDg

Op-Ed: We Still Don't Know the Risk Posed by COVID-19 | MedPage Today

The need for a coordinated national research strategy

Confused about the risks of dying from the coronavirus or of catching it from someone who seems healthy? We all are, and the dizzying differences in scientific opinion are now linked to political perspectives. Progressives cite evidence that loosening restrictions would cost lives and offer little benefit to the economy, while conservatives embrace evidence that the risks are low. We offer a guide to help navigate the tangle of numbers and suggest a way forward.

Google and many others display the number of cases and deaths (3.6 million and 138,840, respectively, by July 17). This invites a simple calculation for understanding the risk: divide the number who have died by the number who have been diagnosed. So, the chance of dying if infected is about 3.9%. Right? Well, not so fast. Six months into the pandemic, neither the number of deaths nor the number of people infected is known.

Some argue that deaths have been overemphasized since people who die of COVID are mostly older and sicker. Others suggest deaths have been overcounted since if a patient tests positive for COVID-19, it will likely be listed as the cause of death even if the person succumbs to another illness or, in some jurisdictions, dies due to an accident or suicide. Others argue that deaths have been undercounted.

Missing from the tally on any given day are those who died before testing was available, those who died shortly before or after but whose death has not yet been reported, or who died as an indirect result of the epidemic such as failing to seek medical care for fear of going to the hospital.

One carefully designed recent analysis compared deaths this year to the number of people who die during a “normal” year. The analysis concluded that through May, almost 100,000 people died from COVID-19 in addition to 30,000 who died from other causes related to the pandemic.

In short, uncertainty remains about the number of deaths due to COVID-19, which is supposed to be the easy part.

Estimating the number of people who have been infected is harder still. Most infected people are never formally diagnosed and never become one of the “cases” in the news. The limitations of the tests and the difficulty of attracting a representative population to be tested make it hard to estimate the true number of infections. The preferred test (reverse transcription polymerase chain reaction-based tests) uses RNA technology to see if the virus is present in nasal or oral swabs. It is a good test, but still may miss infections in up to 30% of cases.

A second type of test uses blood samples to look for an antibody called immunoglobulin (Ig)G that implies the person was previously infected. Based on IgG test results, the CDC assumes that 5% to 8% of the population has been infected. That would mean 24 million Americans have already had COVID-19 or a very similar illness. That is more than 10 times the number of confirmed cases.

The number is consequential: a higher infection rate for the same number of deaths implies that the virus is less deadly. A review by a prominent epidemiologist considered 23 population studies with sample sizes of at least 500 people and found the percentage who have positive antibodies ranged from 0.1% to 48% — a 480-fold difference. Although the study was robustly criticized and at odds with highly cited, peer-reviewed research, it has appeared in over 30 news outlets, and the range of estimates allows people to pick a number that justifies their political position.

Contributing to this uncertainty is the FDA decision to, in a hurry to catch up for lost time, temporarily relax its standards for approving tests. Among over 300 antibody tests currently on the market, data on only a handful are publicly available, and some are being recalled.

The other number we need to know is how many people are spreading the infection without knowing it. Estimates are all over the place. Some major employers, including Stanford Healthcare, have systematically tested all of their employees and found very few infected people who do not have symptoms. In contrast, a CDC study of young, healthy adults working on an aircraft carrier found that 20% of those infected reported no symptoms.

So here we are, months into the epidemic without consensus on the basic information about how many people are infected, the risk of death for those infected, or the risk of asymptomatic transmission. In contrast to official agencies that use transparent methods to report the weather or the unemployment rate, trust in our official health statistics agencies has broken down as reports continue to emerge form myriad sources with conflicting methodologies and motivations.

The time has come to activate impartial groups, like the National Academy of Medicine, to build consensus on how to monitor the epidemic. We know the risks are serious. As cases have started to rise, whether or not the number of U.S. deaths is higher or lower than 130,000, the risk of inaction is too high.

We are staying near home, wearing masks, and treating COVID-19 as a serious threat to public health.