29 health systems ranked by operating margins

The median year-to-date operating margin index for hospitals improved slightly in April to 0 percent. While recent reports show signs of improving margins, they remain far below historical norms, and inflation and workforce expenses continue to challenge hospitals’ bottom lines.

“Hospital and health system leaders must figure out how to navigate the new financial reality and begin to take action,” Erik Swanson, senior vice president of data and analytics with Kaufman Hall, said in a May 31 report. “In the face of operating margins that may never fully recover and inflated expenses, developing and executing a strategic path forward to a future that is financially sustainable is crucial.”

Here are 29 health systems ranked by their operating margins in the first quarter: 

1. Tenet Healthcare (Dallas)

Revenue: $5.02 billion
Expenses: $4.48 billion
Operating income/loss: $603 million
Operating margin: 12 percent

2. HCA Healthcare (Nashville, Tenn.)

Revenue: $15.59 billion
Expenses: $13.67 billion
Operating income/loss: $1.54 billion
Operating margin: 9.9 percent

3. Community Health Systems (Franklin, Tenn.)

Revenue: $3.108 billion
Expenses: $3.111 billion
Operating income/loss: $210 million
Operating margin: 6.7 percent

4. BJC HealthCare (St. Louis)

Revenue: $1.72 billion
Expenses: $1.67 billion
Operating income/loss: $59.5 million 
Operating margin: 3.5 percent

5. Banner Health (Phoenix)

Revenue: $3.51 billion
Expenses: $3.38 billion
Operating income/loss: $128 million
Operating margin: 3.6 percent

6. Mayo Clinic (Rochester, Minn.)

Revenue: $4.27 billion
Expenses: $4.12 billion
Operating income/loss: $149 million
Operating margin: 3.5 percent

7. Intermountain Health (Salt Lake City)

Revenue: $3.99 billion
Expenses: $3.70 billion
Operating income/loss: $104 million
Operating margin: 2.6 percent

8. Sutter Health (Sacramento, Calif.)

Revenue: $3.82 billion 
Expenses: $3.74 billion
Operating income/loss: $88 million 
Operating margin: 2.3 percent

9. IU Health (Indianapolis)

Revenue: $2.08 billion
Expenses: $2.04 billion
Operating income/loss: $45.1 million
Operating margin: 2.1 percent

10. Trinity Health (Livona, Mich.) 

*Data is for nine-month period 
Revenue: $15.95 billion
Expenses: $16.21 billion
Operating income/loss: ($283.5 million) 
Operating margin: 1.8 percent

11. Montefiore (New York City) 

Revenue: $1.91 billion
Expenses: $1.88 billion
Operating income/loss: $32 million
Operating margin: 1.7 percent

12. UPMC (Pittsburgh)

Revenue: $6.9 billion
Expenses: $6.8 billion
Operating income/loss: $100.4 million
Operating margin: 1.5 percent

13. ThedaCare (Appleton, Wis.)

Revenue: $306.4 million
Expenses: $302.8 million
Operating income/loss: $3.6 million
Operating margin: 1.2 percent

14. Cleveland Clinic

Revenue: $3.51 billion
Expenses: $3.28 billion
Operating income/loss: $32.3 million
Operating margin: 0.9 percent

15. Kaiser Permanente (Oakland, Calif.)

Revenue: $25.2 billion
Expenses: $25 billion
Operating income/loss: $233 million
Operating margin: 0.9 percent

16. Advocate Health (Charlotte, N.C.)

Revenue: $7.54 billion
Expenses: $7.53 billion
Operating income/loss: $10.4 million
Operating margin: 0.1 percent

17. Universal Health Services (King of Prussia, Pa.)

Revenue: $3.47 billion
Expenses: $3.19 billion
Operating income/loss: $278,700
Operating margin: 0 percent

18. MedStar Health (Columbia, Md.)

Revenue: $1.928 billion
Expenses: $1.927 billion
Operating income/loss: $400,000 
Operating margin: 0 percent

19. Geisinger (Danville, Pa.)

Revenue: $1.84 billion
Expenses: $1.88 billion
Operating income/loss: ($36,068)
Operating margin: 0 percent

20. Mass General Brigham

Revenue: $4.5 billion
Expenses: $4.5 billion
Operating income/loss: ($6 million)
Operating margin: (0.1 percent)

21. Novant Health (Winston-Salem, N.C.) 

Revenue: $1.939 billion
Expenses: $1.954 billion
Operating income/loss: ($15.18 million) 
Operating margin: (0.8 percent)

22. Scripps Health

Revenue: $1.01 billion
Expenses: $1.03 billion
Operating income/loss: ($22.2 million) 
Operating margin: (2.2 percent)

23. UnityPoint Health

Revenue: $1.09 billion
Expenses: $1.12 billion
Operating income/loss: ($29.03 million)
Operating margin: (2.7 percent)

24. SSM Health (St. Louis)

Revenue: $2.46 billion 
Expenses: $2.53 billion
Operating income/loss: ($68.4 million)
Operating margin: (2.8 percent)

25. Marshfield (Wis.) Clinic

Revenue: $779.7 million
Expenses: $812.3 million
Operating income/loss: (32.6 million)
Operating margin: (4.2 percent)

26. Providence (Renton, Wash.) 

Revenue: $6.8 billion
Expenses: $7.145 billion
Operating income/loss: ($345 million)
Operating margin: (5.1 percent)

27. MultiCare (Tacoma, Wash.) 

Revenue: $1.16 billion
Expenses: $1.22 billion
Operating income/loss: ($59.9 million)
Operating margin: (5.2 percent)

28. CommonSpirit (Chicago) 

Revenue: $8.3 billion
Expenses: $8.9 billion
Operating income/loss: ($658 million) 
Operating margin: (8 percent)

29. Ascension (St. Louis)

Revenue: $6.94 billion 
Expenses: $7.62 billion 
Operating income/loss: ($1.36 billion)
Operating margin: (19.6 percent)

Headwinds facing Not for Profit Hospital Systems are Mounting: What’s Next?

Correction: An earlier version incorrectly referenced a Texas deal between Houston Methodist and Baylor Scott and White.  News about deals is sensitive and unnecessarily disruptive to reputable organizations like these. I sourced this news from a reputable deal advisor: it was inaccurate. My apology!

Congressional Republicans and the White House spared Main Street USA the pain of defaulting on the national debt last week. No surprise.

Also not surprising: another not-for-profit-mega deal was announced:

  • St. Louis, MO-based BJC HealthCare and Kansas City, MO-based Saint Luke’s Health System announced their plan to form a $9.5B revenue, 28-hospital system with facilities in Missouri, Kansas, and Illinois.

This follows recent announcements by four other NFP systems seeking the benefits of larger scale:

  • Gundersen Health System & Bellin Health (Nov 2022): 11 hospitals, combined ’22 revenue of $2.425B
  • Froedtert Health & ThedaCare (Apr 2023 LOI): 18 hospitals, combined ’22 revenues of $4.6B

And all these moves are happening in an increasingly dicey environment for large, not-for-profit hospital system operators:

  • Increased negative media attention to not-for-profit business practices that, to critics, appear inconsistent with a “NFP” organization’s mission and an inadequate trade for tax exemptions each receives.
  • Decreased demand for inpatient services—the core business for most NFP hospital operations. Though respected sources (Strata, Kaufman Hall, Deloitte, IBIS et al) disagree somewhat on the magnitude and pace of the decline, all forecast decreased demand for traditional hospital inpatient services even after accounting for an increasingly aging population, a declining birthrate, higher acuity in certain inpatient populations (i.e. behavioral health, ortho-neuro et al) and hospital-at-home services.
  • Increased hostility between national insurers and hospitals over price transparency and operating costs.
  • Increased employer, regulator and consumer concern about the inadequacy of hospital responsiveness to affordability in healthcare.
  • And heightened antitrust scrutiny by the FTC which has targeted hospital consolidation as a root cause of higher health costs and fewer choices for consumers. This view is shared by the majorities of both parties in the House of Representatives.

In response, Boards and management in these organizations assert…

  • Health Insurers—especially investor-owned national plans—enjoy unfettered access to capital to fund opportunistic encroachment into the delivery of care vis a vis employment of physicians, expansion of outpatient services and more.
  • Private equity funds enjoy unfettered opportunities to invest for short-term profits for their limited partners while planning exits from local communities in 6 years or less.
  • The payment system for hospitals is fundamentally flawed: it allows for underpayments by Medicaid and Medicare to be offset by secret deals between health insurers and hospitals. It perpetuates firewalls between social services and care delivery systems, physical and behavioral health and others despite evidence of value otherwise. It requires hospitals to be the social safety net in every community regardless of local, state or federal funding to offset these costs.

These reactions are understandable. But self-reflection is also necessary. To those outside the hospital world, lack of hospital price transparency is an excuse. Every hospital bill is a surprise medical bill. Supporting the community safety net is an insignificant but manageable obligation for those with tax exemption status.  Advocacy efforts to protect against 340B cuts and site-neutral payment policies are about grabbing/keeping extra revenue for the hospital. What is means to be a “not-for-profit” anything in healthcare is misleading since moneyball is what all seem to play. And short of government-run hospitals, many think price controls might be the answer.

My take:

The headwinds facing large not-for-profit hospitals systems are strong. They cannot be countered by contrarian messaging alone.

What’s next for most is a new wave of operating cost reductions even as pre-pandemic volumes are restored because the future is not a repeat of the past. Being bigger without operating smarter and differently is a recipe for failure.

What’s necessary is a reset for the entire US health system in which not-for-profit systems play a vital role. That discussion should be led by leaders of the largest NFP systems with the full endorsements of their boards and support of large employers, physicians and public health leaders in their communities.

Everything must be on the table: funding, community benefits, tax exemption, executive compensation, governance, administrative costs, affordability, social services, coverage et al. And mechanisms for inaction and delays disallowed.

It’s a unique opportunity for not-for-profit hospitals. It can’t wait.

UPMC adds regional option to in-house travel program

More than a year after launching an in-house travel staffing agency, UPMC is adding a new regional approach to the effort.

Maribeth McLaughlin, MPM, BSN, RN, chief nursing executive for the Pittsburgh-based health system, told Becker’s the approach provides a new option for nurses and surgical technologists who desire to travel. 

Our overall travel program, when you travel for us, you travel across our hospitals in New York, Maryland and Pennsylvania,” she said. “And now we are launching a regional travel strategy where some staff can choose to travel only within certain regions.”

UPMC initially announced in December 2021 that it had created UPMC Travel Staffing, a new in-house travel staffing agency to address a nursing shortage and to attract and retain workers. 

Through the agency, nurses and surgical technologists earn $85 an hour and $63 an hour, respectively, in addition to a $2,880 stipend at the beginning of each six-week assignment.

Ms. McLaughlin said the rate is lower — about $60 an hour — for those who opt for the regional approach.

As of June 1, UPMC has hired more than 700 staff into the in-house travel staffing agency, with 60 percent of those workers being external hires, according to Ms. McLaughlin. And there have been fewer workers leaving UPMC to go to other travel agencies. 

“One of my goals since I’ve taken this role is to really look at building in as many flexible programs as I could for staff,” said Ms. McLaughlin, who has served in her current role since August 2022. “I think as we came out of the pandemic, it’s clear to me that work-life harmony means something different to staff today than it maybe meant when I was a young staff nurse years ago, and that we need to have as much flexibility and as many different programs as we can.”

She said UPMC Travel Staffing has delivered this flexibility and allowed the health system to cancel about 90 contracts with external travel agencies. Additionally, some external travelers have now moved into UPMC’s in-house agency. Ms. McLaughlin expects more to join the in-house agency now that UPMC has launched the regional approach. 

“We’re launching a win-back program where we’re going out and trying to see some of the people who we know we lost and see if they’re interested in coming back closer to home and traveling closer to home,” she explained.

Still, she acknowledged some of the challenges along the way.

Our IT department built us an app to be able to manage all of this because, as you can imagine, we have external travel, internal travelers, core staff and at times it could get a little confusing,” said Ms. McLaughlin. “So we’ve been able to build that to be able to figure out the best ways to assign the staff where the greatest needs are.”

Another challenge she noted is that shifts for workers from external travel agencies are often 12 weeks, while shifts with UPMC Travel Staffing are six weeks. She said this is a purposeful move because those in UPMC Travel Staffing receive benefits and are considered UPMC employees, rather than receiving an hourly rate.

“Overall, it’s been a really successful program for us because it’s allowed us to look at things in a different way,” said Ms. McLaughlin. “It’s a central function. It’s not something we did and farmed out to every hospital to administer themselves. We did it as a system and as a core, which I also think is important.”

Now, she said she’s excited about the new regional approach and the opportunities it presents for recruiting and retention. 

“We’re growing our own students, we’re bringing in all these students, and we’re not saying, ‘You have to just work here.’ We’re saying, ‘You can work for us at UPMC, and here are all the options. You can even be a traveler with us,'” she said.

49 hospitals, health systems partnering with CVS

As the nation’s leading provider of retail healthcare, CVS Health partners with hospitals and health systems in many local markets.

The health systems assist providers at CVS MinuteClinic locations and accept referrals from patients needing a higher level of care. Here are CVS’ clinical affiliates, according to its website:

Arizona

Dignity Health (San Francisco)

Northwest Healthcare (Tucson)

Tucson Medical Center

California

John Muir Health (Walnut Creek)

Sharp HealthCare (San Diego)

Sutter Health (Sacramento)

UCLA Health (Los Angeles)

Connecticut

Hartford HealthCare

District of Columbia

MedStar Health (Columbia, Md.)

Florida

Baptist Health Care (Pensacola)

Cleveland Clinic Florida (Weston)

Florida Hospital Medical Group (Orlando)

Millennium Physician Group (Fort Myers)

St. Vincent’s HealthCare (Jacksonville)

Georgia

Emory Healthcare (Atlanta)

Memorial Health (Savannah)

Illinois

Franciscan Health (Mishawaka, Ind.)

Rush University Medical Center (Chicago)

Indiana

Franciscan Health (Mishawaka)

Kansas

Lawrence Memorial Hospital

Shawnee Mission Health (Merriam)

Louisiana

The Baton Rouge Clinic

LSU Healthcare Network (New Orleans)

Maryland

MedStar Health (Columbia)

University of Maryland Medical System (Baltimore)

Massachusetts

Baystate Health (Springfield)

Lahey Health (Burlington)

UMass Memorial Health (Worcester)

Michigan

Franciscan Health (Mishawaka, Ind.)

Henry Ford Health (Detroit)

Minnesota

Allina Health (Minneapolis)

Nevada

Dignity Health-St. Rose Dominican (Henderson)

New Hampshire

Dartmouth Health (Lebanon)

New York

CareMount Medical (Mount Kisco)

Mount Sinai Health System (New York City)

Northwell Health (New Hyde Park)

New Jersey

RWJBarnabas Health (West Orange)

Virtua Health (Marlton)

Ohio

Cleveland Clinic

Premier Health (Dayton)

TriHealth (Cincinnati)

Oklahoma

OU Physicians (Tulsa)

Pennsylvania

Lehigh Valley Health Network (Allentown)

St. Luke’s University Health Network (Bethlehem)

Rhode Island

Lifespan (Providence)

South Carolina

Prisma Health (Greenville)

Tennessee

Parkridge Health System (Chattanooga)

TriStar Health (Brentwood)

Texas

Texas Health Resources (Arlington)

University of Texas Medical Branch (Galveston)

UT Health Physicians (San Antonio)

Virginia

Inova Health System (Falls Church)

U.S. economy adds 339,000 jobs as labor market stays hot

https://www.axios.com/2023/06/02/may-jobs-report-employment

The U.S. economy added 339,000 jobs in May, while the unemployment rate jumped to 3.7% from 3.4%, the Labor Department said Friday.

Why it matters: 

Job gains came in well above forecasters’ expectations — the latest sign that the economy is still underpinned by a hot labor market.

  • Economists expected a gain of 190,000 jobs last month. The May jobs figures are a pickup from the 294,000 added in April, which was revised up by 41,000. Job gains in March were revised up, too.

Details: 

Economic policymakers have kept a close eye on other details from the payrolls report — whether more Americans are joining the workforce and how quickly pay is rising.

  • The labor force participation rate — the share of workers with a job or hunting for one — held at 62.6% in May.
  • Meanwhile, average hourly earnings, a measure of pay, rose by 0.3% in May. Compared to the same period a year ago, wages are up 4.3%.

What we’re watching: 

The May jobs report is among the final data points Federal Reserve officials will consider before deciding whether to continue the interest rate hiking campaign that began more than a year ago.

  • Inflation remains too high, and there are concerns that rapid price gains are being fueled by the tight labor market and strong consumer demand.
  • Still, a top Fed official this week signaled the central bank may skip a rate hike at its meeting later this month.

The Great Resignation is over, quit rates return to pre-pandemic levels

https://www.axios.com/2023/05/31/great-resignation-quitting-boom

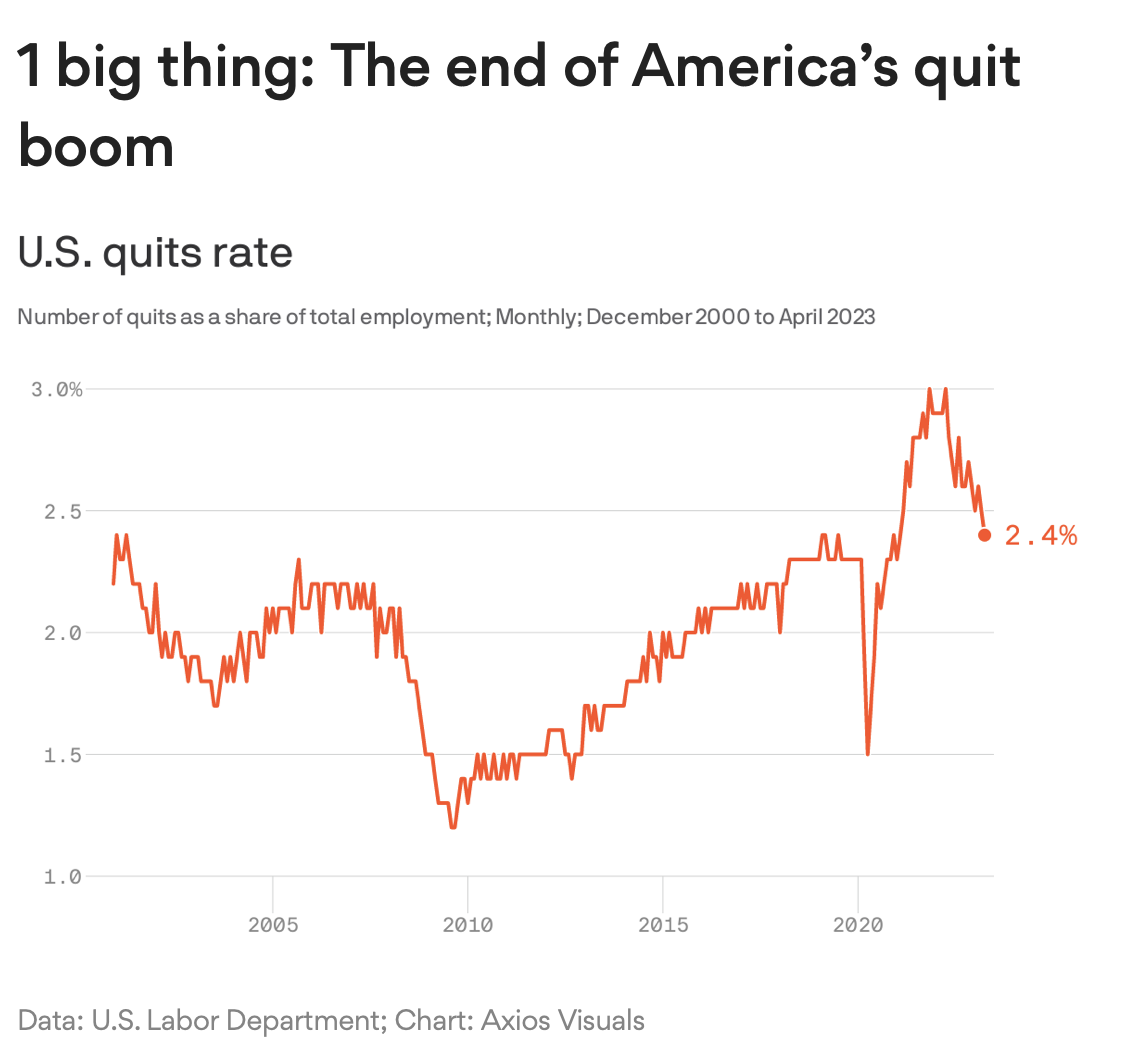
A phenomenon that defined the pandemic-era labor market is over: the Great Resignation — workers furiously quitting for new, likely higher paying jobs — is a thing of the past.

Why it matters:

The historic surge of quitters was a symptom of an on-fire labor market, where demand for workers far outstripped supply of them.

  • Now the job market may be entering a different era — one that more closely resembles pre-pandemic times.

By the numbers:

The quits rate fell to 2.4% in April, according to the Job Openings and Labor Turnover Survey, released this morning.

  • That is just a tick (0.1 percentage point) higher than the quits rate in February 2020 — and roughly in line with the average quits rate in 2019.
  • Even leisure and hospitality workers, once the poster child for the quits boom, are returning to pre-pandemic norms: the quits rate in this segment hit 4.6% in April — very close to the January 2020 rate of 4.4%, and well-below the peak 5.8% recorded last summer.

What they’re saying:

“We are pretty much back to a strong, robust labor market, but one that is no longer overheating,” says Julia Pollak, an economist at ZipRecruiter.

  • “One that isn’t plagued by widespread labor shortages that are wreaking havoc across the economy, and causing firms to offer off-cycle wage increases and dispense of all hiring requirements. The deck isn’t totally stacked in jobseekers‘ favor anymore.”

Flashback:

At the height of the Great Resignation, the overall quits rate most recently peaked at 3% in April 2022, when there were roughly 4.5 million quits in a single month.

  • Turnover of that magnitude had never been seen before — at least not since the Labor Department started collecting the data in 2000.
  • Workers were in such high demand that they felt confident enough to ditch current gigs for new (likely higher paying) ones.

The bottom line:

Americans who did job hop over the past few years have seen heftier pay gains. But that phenomenon, too, is fading — another sign of some heat coming off the labor market.

  • Job-changers saw annual pay grow more than 13% in April, according to payroll professor ADP — more than double the annual rate of job-stayers.
  • Still that was the slowest pace of growth since November 2021.