CommonSpirit Health announced Wednesday that it will acquire regional health system Steward Health Care in Utah for $685 million.
The deal marks CommonSpirit’s entry into Utah, expanding the hospital operator’s footprint to a total of 22 states.
CommonSpirit will acquire five hospitals from Steward, along with more than 40 clinics and other ambulatory services, the system said. The deal is expected to close later this year. CommonSpirit’s Centura Health will manage the Utah sites.
Dive Insight:
The acquisition comes on the heels of a thwarted attempt by HCA to purchase Steward Health Care last year.
The Federal Trade Commission was successful in blocking the deal after the agency alleged that a tie-up between the head-to-head competitors would harm patients around Salt Lake City by raising prices and lowering care quality.
CommonSpirit said the deal represents a “significant long-term growth opportunity” and extends the system’s reach into a new region that already has an established presence with a variety of services, including acute, post-acute and ambulatory care.
The Catholic health system released financial results Wednesday for the period ended Dec. 31, the nonprofit’s second quarter, which showed a $474 million operating loss. The system said labor shortages, higher staffing costs and a recent ransomware attack dragged on its results.
“CommonSpirit is taking a number of steps to bolster its financial sustainability,” the system said Wednesday.
But officials would not comment on whether those steps may include job cuts.
So far, the ransomware incident has cost the system $150 million, it said Wednesday. The figure includes lost revenue due to the interruption to business and costs to remediate the issue.
CommonSpirit said it is working with insurance carriers but is unable to predict the timing or amount it may receive following the cyber incident.
Wednesday’s acquisition news follows CommonSpirit’s recent announcement that it is dissolving its long-term joint venture with AdventHealth. For more than two decades, the two operated hospitals in Colorado and western Kansas. The two will now manage their respective hospitals.
About 64% of adults in a Medicaid-enrolled family in December said they did not know they may lose coverage once pandemic-era policy ends and eligibility checks resume on April 1, according to a survey from the Robert Wood Johnson Foundation.
The percentage of respondents who said they heard nothing about upcoming Medicaid renewals rose from June, when 62% said they knew nothing about the changes, the survey found.
Awareness was low across the board regardless of geographic region or a state’s Medicaid expansion status, according to the survey.
Dive Insight:
The federal government barred states from resuming Medicaid eligibility checks amid widespread job losses and other challenges during the pandemic.
Once eligibility checks resume, as many as 18 million people are expected to lose coverage, according to the Robert Wood Johnson Foundation.
About 7 million of those people are expected to gain coverage through the individual markets or employer-sponsored plans, though 8 million will not and will likely become uninsured, according to a report from Moody’s Investor Services.
Awareness levels regarding looming redetermination checks remained low and varied only slightly regionally, the report found.
Similarly, above 60% of respondents reported unawareness of Medicaid redeterminations both in Medicaid expansion states and those that haven’t expanded Medicaid, “which suggests the need for widespread outreach and education efforts,” the report said.
“Reducing information gaps about the change is a critical first step,” the report said.
In non-expansion states, people will need help learning about navigating marketplace options, while in expansion states they’ll need information on how to stay enrolled, the report said.
The suspension of eligibility checks led Medicaid membership to rise substantially during the pandemic, growing from 70.7 million members in February 2020 to 90.9 million in September, according to the Moody’s Investor Services report.
The end of the policy is expected to deal a blow to payers that have touted recent enrollment growth while hospitals could see more self-pay patients and “higher bad debt” for facilities, the Moody’s report said.
Here are 14 health systems with strong operational metrics and solid financial positions, according to reports from credit rating agencies Fitch Ratings, Moody’s Investors Service and S&P Global.
1. Ascension has an “AA+” rating and stable outlook with Fitch. The St. Louis-based system’s rating is driven by multiple factors, including a strong financial profile assessment, national size and scale with a significant market presence in several key markets, which produce unique credit features not typically seen in the sector, Fitch said.
2. Berkshire Health has an “AA-” rating and stable outlook with Fitch. The Pittsfield, Mass.-based system has a strong financial profile, solid liquidity and modest leverage, according to Fitch.
3. ChristianaCare has an “Aa2” rating and stable outlook with Moody’s. The Newark, Del.-based system has a unique position with the state’s largest teaching hospital and extensive clinical depth that affords strong regional and statewide market capture, and it is expected to return to near pre-pandemic level margins over the medium term, Moody’s said.
4. Cone Health has an “AA” rating and stable outlook with Fitch. The rating reflects the expectation that the Greensboro, N.C.-based system will gradually return to stronger results in the medium term, the rating agency said.
5. Harris Health System has an “AA” rating and stable outlook with Fitch. The Houston-based system has a “very strong” revenue defensibility, primarily based on the district’s significant taxing margin that provides support for operations and debt service, Fitch said.
6. Johns Hopkins Medicine has an “AA-” rating and stable outlook with Fitch. The Baltimore-based system has a strong financial role as a major provider in the Central Maryland and Washington, D.C., market, supported by its excellent clinical reputation with a regional, national and international reach, Fitch said.
7. Orlando (Fla.) Health has an “AA-” and stable outlook with Fitch. The system’s upgrade from “A+” reflects the continued strength of the health system’s operating performance, growth in unrestricted liquidity and excellent market position in a demographically favorable market, Fitch said.
8. Rady Children’s Hospital has an “AA” rating and stable outlook with Fitch. The San Diego-based hospital has a very strong balance sheet position and operating performance and is also a leading provider of pediatric services in the growing city and tri-county service area, Fitch said.
9. Rush System for Health has an “AA-” and stable outlook with Fitch. The Chicago-based system has a strong financial profile despite ongoing labor issues and inflationary pressures, Fitch said.
10. Salem (Ore.) Health has an “AA-” rating and stable outlook with Fitch. The system has a “very strong” financial profile and a leading market share position, Fitch said.
11. TriHealth has an “AA-” rating and stable outlook with Fitch. The rating reflects the Cincinnati-based system’s strong financial and operating profiles, as well as its broad reach, high-acuity services and stable market position in a highly fragmented and competitive market, Fitch said.
12. UCHealth has an “AA” rating and stable outlook with Fitch. The Aurora, Colo.-based system’s margins are expected to remain robust, and the operating risk assessment remains strong, Fitch said.
13. University of Kansas Health System has an “AA-” rating and stable outlook with S&P Global. The Kansas City-based system has a solid market presence, good financial profile and solid management team, though some balance sheet figures remain relatively weak to peers, the rating agency said.
14. Willis-Knighton Health System has an “AA-” rating and stable outlook with Fitch. The Shreveport, La.-based system has a “dominant inpatient market position” and is well positioned to manage operating pressures, Fitch said.
New Hyde Park, N.Y.-based Northwell Health began 2023 with a low, but positive operating margin, but labor costs are expected to increase again this year on the back of recent union activity in the state.
To offset such increases that were not anticipated in the 2023 budget, Northwell is evaluating opportunities to reduce expenses and increase revenue across the health system, which includes 21 hospitals and about 83,000 employees.
Michael Dowling, CEO of Northwell, spoke to Becker’s Hospital Review about the health system’s biggest challenge this year, how it approaches cost-cutting and why outpatient care is its biggest growth area.
Editor’s note: Responses are lightly edited for length and clarity.
Question: Many health systems saw margins dip last year amid rising inflation, increased labor costs and declining patient volumes. How have you led Northwell through the challenges of last year?
Michael Dowling: We ended 2022 with a low, but positive margin. We’ve been coming back from COVID quite successfully, and we’re back pretty much in all areas to where we were prior to the pandemic. Volumes have returned and we’re very busy. We came into 2023 with a positive budget and a positive margin. We anticipate that you’re always going to have challenges and disturbances, but it’s important to stay focused and deal with it. We have a very detailed strategic plan, which outlines our various goals, and we stick to it.
Q: What is your top priority today?
MD: The biggest issue for us today is labor costs. We have lots of union activity in New York at the moment. There were various nurse strikes in New York City at the beginning of the year. None of our hospitals were involved in those deliberations, but some of those hospitals agreed to contracts that have increases that were not anticipated in anybody’s 2023 budget. That’s going to have an effect on us. We have negotiations ongoing with the nurses’ union, and have 10 unions overall. About 90 percent of Northwell’s facilities have unions, so the bottom line is we are going to have expenses as a result of these contracts that were not anticipated in the budget. I don’t know the final number on these contracts yet, but it’s definitely going to be more than what we anticipated.
The unions in New York get a lot of government support and have become very empowered and quite aggressive. The bottom line is there’s more expense than we anticipated in our budget, so we need to figure out how to address that. We’re looking at everything across our health system to find expense reductions or revenue enhancements to be able to make up for the increased labor costs and be optimistic about ending the year with a positive margin. But we’re in a good place and are not like some other health systems that are struggling financially.
Q: Where are the biggest opportunities to reduce expenses or increase revenue to offset the increased labor costs?
MD: It’s a combination of a lot of things. We have a detailed capital plan that we may slow down. We hire about 300 people a week, so maybe we’ll target that hiring into specific areas and not be as broad based as we thought we could be. We will examine if we have specific programs or initiatives we can curtail without doing any damage to our core mission. It will end up being a portfolio of items; it won’t be one big thing. On the revenue side, we’re working very hard to increase our neurosurgery, cardiac, cancer and orthopedic businesses. Over the next couple of months, all of those things will be taken into consideration. The bottom line is we are going to come out of this winning.
Q: Looking three or four years down the line, where do you see the biggest growth opportunities for Northwell?
MD: Our biggest growth is in outpatient care. A lot of surgeries are moving outpatient, so we have to get ahead of that. Some think we are only a hospital system, but only about 46 percent of our business is from our hospital sector today. Home care is going to grow phenomenally, especially given the new technology that’s available. Digital health will also dramatically expand.
We’re also looking at expanding into new geographic areas and markets. It’s about positioning your offerings in places close to where people live, so you reduce the inconvenience of people having to travel long distances for care when it should be available to them closer to home. When you do that, you increase market share. We’re constantly increasing our market share by being very aggressive about going to where the customer is and providing the highest quality care that we can. Part of that is also being able to recruit top-line, quality physicians. When you do that, you attract new business because you have competencies that you didn’t have before. It’s a combination of all of these things, but there’s certainly no limit to the opportunities in front of us. We’re not in a world of challenges; we’re in a world of opportunity. The question is are we aggressive enough and do we have enough tolerance for some risk? We need to be as aggressive as we possibly can to take advantage of some of those opportunities.
Q: What is the biggest challenge on the horizon for Northwell?
MD: The biggest challenge is the huge growth in government payer business — Medicare and Medicaid. The problem with Medicaid — especially in a union environment — is it doesn’t cover your costs. The government is a big part of a potential future issue there. By increasing Medicaid, the more of your business becomes Medicaid and the worse you end up doing, unless you can increase your commercial payer business to continue to cross-subsidize. We also have a lot of union negotiations over the next couple of months, which will put a strain on our 2023 budget, but we will resolve it.
Q: How do you see hospitals and health systems evolving as CMS, commercial payers and patients continue to push more services to outpatient settings, where they can arguably be performed at a higher quality and lower cost?
MD: I think it’s going to continue to grow. For example, Northwell has 23 hospitals — 21 of which it owns — yet it has 890 outpatient facilities. We’ve been ahead of this curve a long time. Our primary expansion is in ambulatory care, not in-hospital care. Like I said, only 46 percent of Northwell’s total business is its hospital business. If you’re relying on the hospital to be the core provider of the future, you’re going to lose. You’ve got to take a little bit of a hit by going out and expanding your ambulatory presence. But the more you expand ambulatory and grow in the right locations, the more you increase market share, which brings more of the necessary inpatient care back to your hospitals. Our hospitals are growing and getting busier in addition to our outpatient centers because we are growing market share. If we enter a new community and see 100 people, five of them will need to be hospitalized. That’s a new market. Ambulatory cannot be disassociated from its connection to the inpatient market.
Q: Many financial experts are projecting a recession this year. How might that affect hospitals and health systems, and how can they best prepare?
MD: Even if we do have a recession, it doesn’t mean that people don’t get sick. In fact, people’s problems increase. Our business does not slow down if we have a recession; our business will probably increase. On the revenue side, it won’t necessarily affect our government reimbursement, which we don’t do well on anyway. The things you worry about during a recession is if employers give up the coverage of their staff. Then those employees with no insurance may go on a state Medicaid program, and that might affect hospitals.
In the healthcare sector, even in a recession, the need for hospital services actually increases. No recession could be as bad as what we experienced during COVID, yet we managed it. We had a problem that we didn’t even understand, and we worked through it. I think healthcare deserves an extraordinary credit for what was done during COVID. If there is a recession, we will deal with it. It’s just one of those things that happens, and we will respond to it in as comprehensive a way as we can. I can’t control it, but I can control our response. Leadership to me is about having a positive disposition; basically saying that whatever happens to you, you’re going to win.
As the U.S. prepares to end the COVID-19 public health emergency, hospitals are facing a major cut in Medicare payments used to treat patients diagnosed with the disease.
Since January 2020, hospitals nationwide have received a 20 percent increase in the Medicare payment rate through the hospital inpatient prospective payment system to treat COVID-19 patients — that policy ends May 11.
The sunsetting of the three-year policy is a key concern for the AHA because of its financial implication for hospitals already struggling with increased labor costs and inflation.
From January 2020 to November 2021, payments for the 1 million traditional Medicare patients hospitalized with COVID-19 totaled $23.4 billion, or more than $24,000 per patient, according to lobbying and law firm Brownstein.
The end of the policy also has the potential to increase medical costs for patients hospitalized with COVID-19. If patients must pay higher costs for COVID-19-related services, they may be less inclined to get tested or even seek treatment.
“It means there will be less testing in this country, and likely less treatment because not everyone can afford it,” Jose Figueroa, MD, assistant professor of health policy and management at the Harvard T.H. Chan School of Public Health, told Time Jan. 31. “Will this change the trajectory of the pandemic? It’s something we are going to have to watch.”
As of Feb. 8, the nation’s seven-day COVID-19 case average was 40,404, a 1 percent decrease from the previous week’s average. The rate of decrease has slowed in the last two weeks — the CDC’s last weekly report published Feb. 3 reported a 6.7 percent drop in cases.
The seven-day hospitalization average for Feb. 1-7 was 3,665, a 6.2 percent decrease from the previous week’s average and down from an 8.4 percent drop in cases a week prior.
On Wednesday, a joint Food and Drug Administration (FDA) advisory panel unanimously recommended that the anti-opioid overdose drug Narcan (known generically as naloxone) be made available in nasal spray form without a prescription. It’s highly likely the FDA will grant OTC approval to Narcan next month, which could make it more widely available to the public as soon as this summer.
The Gist: Narcan has become one of the most essential tools to combat the unrelenting epidemic of opioid-related drug overdoses, which claimed a record 107K lives in 2021. Even though the medication can be prescribed to at-risk individuals and others who are in close contact with drug users, access thus far has been limited mostly to emergency responders and outreach workers.
While the US has successfully reduced the availability of the prescription opioids that initially sparked the crisis, a majority of recent deaths are attributed to synthetic opioids like fentanyl. This much-needed policy change acknowledges that efforts to restrict drug supply have stalled, and shifts the focus to broadening access to effective harm-mitigation tools.
As community leaders on the frontline of the opioid epidemic, hospitals and providers can play a valuable role in publicizing expanded Narcan availability.
This week, the Biden administration released a roadmap for implementing three new drug pricing pilots through the Centers for Medicare and Medicaid Innovation (CMMI). These models seek to offer certain common generic drugs to Medicare beneficiaries for two dollars per month, test new ways for how Medicaid pays for expensive cell and gene therapies, and explore alternative reimbursement models for drugs that receive accelerated Food and Drug Administration approval.
The Gist: On the heels of last week’s State of the Union Address, the announcement of these pilots exemplifies the kind of health policy efforts we expect across the remainder of President Biden’s current term: smaller, incremental initiatives to curb healthcare costs at the margins.
But given that all these initiatives have lengthy timelines, in part to allow for industry input, they will likely require the support of the next administration, Biden’s or otherwise, to reach full implementation.
Responding to the Centers for Disease Control and Prevention’s (CDC) latest Youth Risk Behavior Survey for 2011-2021, an article in The Atlantic attempts to make sense of the historic levels of anxiety and depression being reported by today’s teens, especially girls and those who identify as lesbian, gay, or bisexual (the survey does not track trans identity).
The survey, which is the definitive measure of youth behavior and mental health in the country, found nearly 60 percent of teenage girls reported “persistent feelings of sadness or hopelessness”, and that the share contemplating suicide grew by 50 percent since 2011. The article explores several possible drivers, including a pandemic-induced effect that could subside, pervasive exposure to social media, the normalization of discussing mental distress, and the outcome of growing up with ongoing crises like school shootings and climate change. But none of the explanations fully accounts for the alarming crisis, nor do any of them present easily workable solutions.
The Gist: Echoing the drug overdose epidemic, the unfolding crisis in teen mental health is difficult for providers to address because many victims don’t access healthcare services until their conditions deteriorate to the point of requiring hospitalization, often from a suicide attempt or an overdose.
And when teenagers in mental health crisis present to emergency departments, hospitals are often forced to board them for days,as the number of psychiatric treatment facilities for teens has dropped by 30 percent from 2012 to 2020.
These data should be a call for providers to focus more upstream diagnosis and care, by partnering with children, families, schools, and other community organizations.
This week, a health system CFO referenced the thoughts we shared last week about many hospitals rethinking physician employment models, and looking to pull back on employing more doctors, given current financial challenges. He said, “We’ve employed more and more doctors in the hope that we’re building a group that will allow us to pivot to total cost management.
But we can’t get risk, so we’ve justified the ‘losses’ on physician practices by thinking we’re making it up with the downstream volume the medical group delivers.
But the reality now is that we’re losing money on most of that downstream business. If we just keep adding doctors that refer us services that don’t make a margin, it’s not helping us.”
While his comment has myriad implications for the physician organization, it also highlights a broader challenge we’ve heard from many health system executives: a smaller and smaller portion of the business is responsible for the overall system margin.
While the services that comprise the still-profitable book vary by organization (NICU, cardiac procedures, some cancer management, complex orthopedics, and neurosurgery are often noted), executives have been surprised how quickly some highly profitable service lines have shifted. One executive shared, “Orthopedics used to be our most profitable service line. But with rising labor costs and most of the commercial surgeries shifting outpatient, we’re losing money on at least half of it.”
These conversations highlight the flaws in the current cross-subsidy based business model. Rising costs, new competitors, and a challenging contracting environment have accelerated the need to find new and sustainable models to deliver care, plan for growth and footprint—and find a way to get paid that aligns with that future vision.







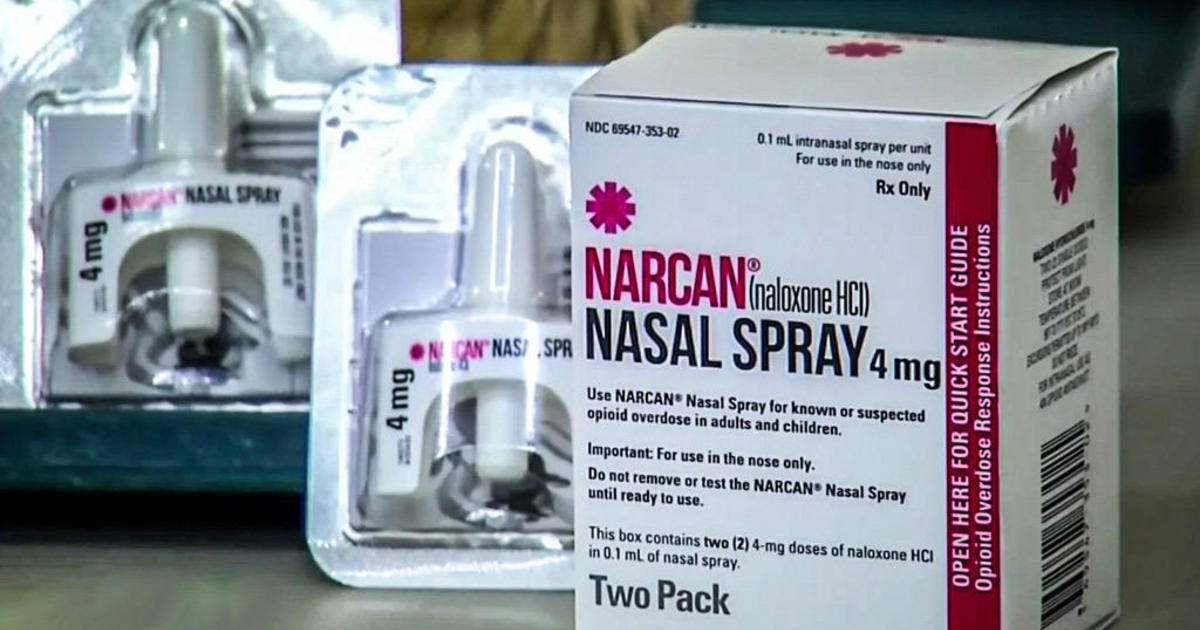



 HENRY KOTULA
